Chapter 10 Lower limb trauma I
Introduction#
Pointers to candidates
The mechanism and whether the injury is a high- or low-energy injury should be considered and mentioned a t the start of every answer.
All high-energy injuries should be approached in an ATLS protocol manner.
The candidate should be very familiar with the latest ATLS guidelines and be ready for the examiner
The candidate should also be very familiar with the BAPRAS/BOA guidelines for the management of open fractures as well as all the BOAST guidelines and base
Always ask for adequate imaging even if it is not provided or not available. This is in the form of
X-rays as well as CT scans where appropriate (including angiograms).
Always answer the question : if the examiner asks ‘how would you treat this injury?’ you should state what you would do rather than what options there are.
Polytrauma patients are also common questions in the viva and the candidate is expected to be very
Moran CG, Forward DP. The early management of patients with multiple injuries . J Bone J Surg Br.
2012;94B:446–453.
Structured oral examination question 1#
Femoral neck fracture in the young
Viva themes
Timing of surgery.
Type of reduction.
Surgical approaches.
Fixation methods.
What does the radiograph show (Figure 10.1)?
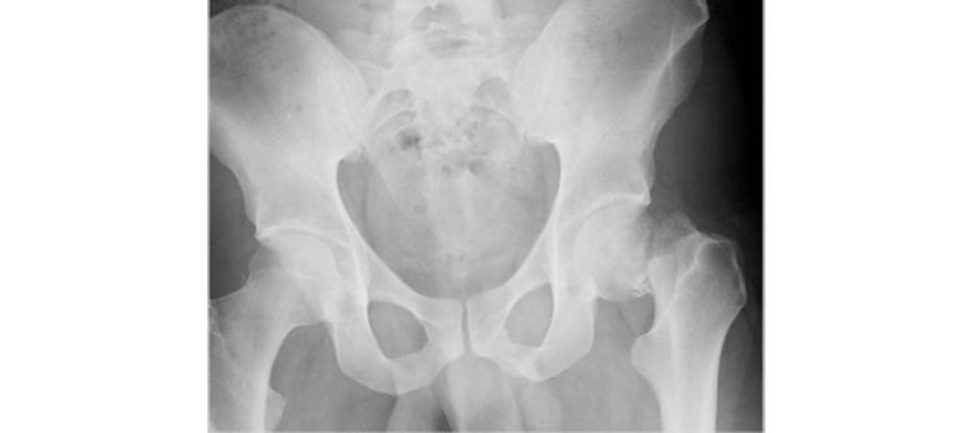
The radiograph is inadequate because it does not show the full pelvis and hips. Otherwise the radiograph shows a displaced subcapital intracapsular neck of femur fracture.
Why would you want a CT? You don’t normally get CT scans for every hip fracture that presents in casualty. CANIDATE : A CT could be obtained as part of a pan-trauma series to look for any other associated injuries. A CT can be useful to more accurately classify a fracture pattern to then guide treatment options.
The main role of CT would be in identifying occult femoral neck fractures in a painful hip with normal
This is the radiograph of a 29-year-old male who fell off his motorbike at 40 mph after slipping on ice. Discuss your management of this patient.
This is a high-energy injury and as with any such injury I would assess this
What are the key elements in this patient management?
Assessing the pattern of the fracture to ensure and plan for anatomical fracture reduction and fixation
What is the blood supply to the femoral head?
The medial and lateral femoral circumflex arteries arise from the profunda femoral artery and curl around the trochanteric region before branching proximally to supply the head.
The patient presented to casualty at 11 pm having sustained the fracture 2 hours beforehand. The SHO has booked the emergency theatre for the fixation to be done straight after a laparotomy as they have been told the risk of ON significantly increases after 6 hours. What will you do?
Timing to surgery used to be believed to be very relevant to avoid ON; however, this has recently been refuted in the literature. The general scrub staff may be unfamiliar with the trauma kit and it is not the ideal timet o be doing this type of surgery. The delay also gives me some extra timet o more fully explain the risk factors associated with fracture fixation such as non-union, ON and pos t-traumatic osteoarthritis to the patient.
If this was not reduced, what method would you do to improve it closed?
The Leadbetter is the technique that is described. The hip is flexed with axial traction, then adducted and brought into abduction and extension. This manoeuvre should not be attempted more than once to avoid the increased risk of ON.
How would you assess your reduction?
I would do so on both the AP and lateral views with fluoroscopy. Acceptable reduction is between 155° and 180°, respectively but ideally 160°. Beyond those ranges the rate of ON is said to increase from 7% to 53%.
If the hip did not reduce adequately in a closed manner, what would be your next step?
Although biomechanic al studies have shown no significant difference between the triangle vs. inverted triangle configuration, I personally prefer having the triangle configuration with two screws along the calcar and compression side of the neck of femur.
Any other methods of fixation?
It is possible to fix the fracture with a two-hole sliding hip screw. I would temporary stabilize the fracture with a de-rotation K - wire to prevent rotation and go on to use a cannulated derotation screw over the initial K -wire for additional rotational stability.
What does the literature say?
The literature would suggest quality of reduction is more important than implant choice. Biomechanical studies have reported th eDHS construct is stronger than CS. Singh et al. reported a better outcome (less hip pain, better hip function, higher patient satisfaction) in young patients with Pauwels type II and III treated with two- hol eDHS fixation but complication rate (re-operation rate, conversion to THA) did not depend on the implant used but quality of fracture reduction. 2
Any other approaches that can be considered?
but it can be challenging in muscular young male patients This requires two separate incisions, one anteriorly to reduce the fracture and the other laterally to insert the fixation device.
If you reduced the fracture closed, can you think of a surgical step that can be performed to reduce the rate of ON?
Although this is controversial it is said to reduce intra-articular pressure which in the acute seting of fracture haematoma can theoretically occlude the trochanteric anastomosis. This has been studied in acute slipped capital femoral epiphysis and shown to reduce ON, so it can possibly be extrapolated to the adult population in a similar fashion.
Apart from ON, what other complication are you concerned about in this patient?
The early complications would include wound infection thromboembolic events and deep infection. If using CS, I would touch weight-bear the patient for at least 6 weeks and follow him up closely with radiological monitoring until the 3- year mark to ensure that the femoral head has survived without untoward complications.
And with a DHS fixation?
Weight-bearing status would depend on adequacy of fixation and bone quality .
So, would you allow full weight-bearing or not?
It is unlikely that osteoporosis would be present in a 29-year-old male and a DHS construct has been shown
What does the literature say?
I am not sure any difference in outcome has been shown regarding weight-bearing status postoperatively guess]. [Bell]
Thankyou.
Figure 10.1 Anteroposterior (AP) radiograph of pelvis. Displaced intracapsular fractured left neck of femur.
Ly TV, Swiontkowski MF. Treatment of femoral fractures in young adults. J Bone Joint Surg Am.
2008;90(10):2254–2266.
Structured oral examination question 2#
Fractured neck of femur in the elderly
Viva themes
Multidisciplinary management.
Hip fracture pathway.
Use a method that allows full weight-bearing.
Cemented arthroplasty of certain ODE Prating.
This is an 83-year-old male who fell while gardening, sustaining this injury. He lives with his wife, who he cares for. He mobilized indoors with no aids but uses a stickout doors. He has a history of hypertension, hypothyroidism and angina. He is a non-smoker and rarely drinks. What does the radiograph show (Figure 10.2)?
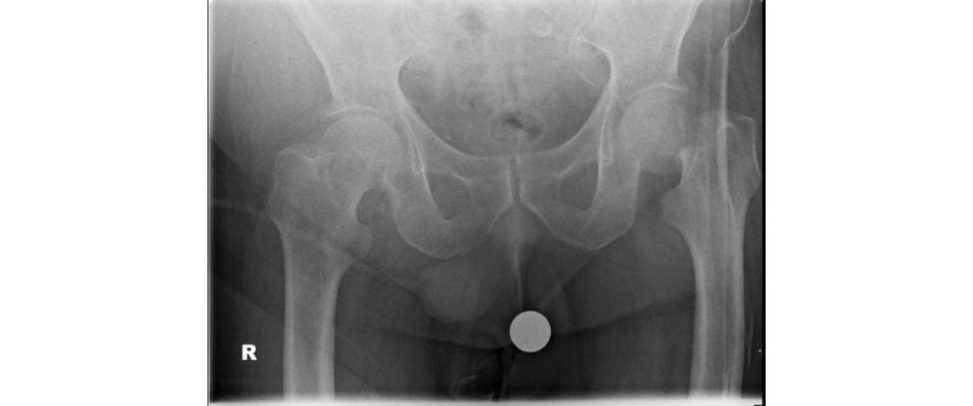
The AP pelvis radiograph reveals a left sided displaced intracapsular fracture of the neck of femur. I cannot see any evidence of a pelvic or pubic ramus fracture.
How will you assess this patient and what areas will you ask about?
I would find out more about his degree of mobility prior to his injury and ask about any comorbidities, systemic illness, red flag signs for any pathological lesion, as well as assess the reason for the fall. I would establish if he is oriented in time, place and person, take an AMTS and obtain a collateral history.
What would you look for in your examination and how would you work the patient up for surgery?
I would check the affected leg for shortening and external rotation Perform a neurovascular examination. I would check the skin and soft tissues surrounding the fracture and proposed incision site. I would make sure the patient had a recent chest X-ray and order a new ECG to identify underlying cardiac comorbidities. I would give the patient analgesia for pain and insert a cannula and start IV fluids. Bloods should be sent for FBC, U&E and a group and save. I would risk-assess warfarin reversal with Vit K. I would attempt to get the pa tientas quickly as possible out of the A&E department onto an orthopaedic ward and certainly within 4 hours of admission to the A&E department.
He has well-controlled angina, takes thyroxine for his hypothyroidism and is relatively independent but does have two carers who come and help twice a week. How do you want to treat him?
A displaced intracapsular neck of femur requires surgery and, in this case, given the degree of displacement, which seems like a Garden IV (JBJS Garden 1964) I would perform a cemented hip hemiarthroplasty using a polished double-tapered stem with a bipolar head.
As you see this was done as per your suggestion ( Figure 10.3). Would your management differ if this was an independent and healthy 68-year-old patient who goes for 5-mile daily walks?
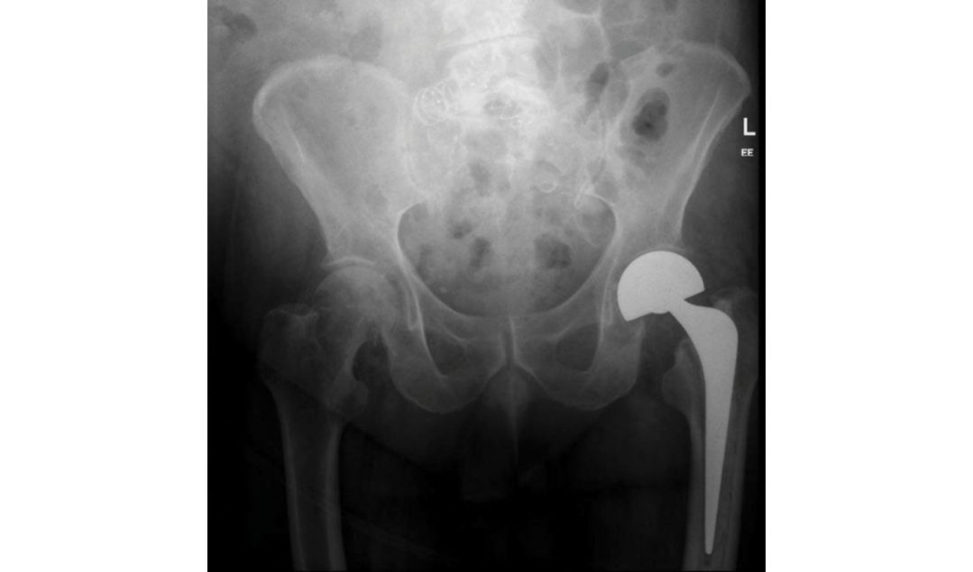
My initial assessment would be the same, but if the patient is independently mobile I would treat him inaccordance with the NICE and the BOAST guidelines and would offer him a total hip replacement. The NICE guidelines support such practice in a selected population, which include the mentally alert patient with good pre-injury mobility and who is relatively healthy. The patient described seems to comply with the criteria for a THR. I would prefer to perform a fracture neck of femur THR via the lateral approach as opposed to a posterior approach that I would choose for an arthritic hip. This ist o reduce the risk of a dislocation. Osteoporosis treatment, falls risk assessment and nutritional deficiency should be addressed. The patient’s pre- and postoperative care should be carried out via an MDT approach.
What time would you plan to do this case if the patient arrived in your hospital at 5 pm?
The patient should be reviewed by an orthogeriatrician, to be optimized preoperative lyas per national guidelines. The operation should be performed as soon as safe and possible, ideally within 24 hours, but no later than 36 hours as per the national guidelines.
What are the criteria for best-practice tariffs inpatients who have sustained a hip fracture?
Key features include: Surgery within 36 hours of admission. Assessment by orthogeriatrician within 72 hours of admission. Pre- and postoperative abbreviated mental test score AMTS) assessment. Secondary prevention off alls. Bone health assessment. Other aspects of this question could include: Evidence of THA in NOF fractures. Higher complication rates of TH Rin NOF vs arthritic hip? Infection rates. Thromboprophylaxis.
Figure 10.2 Anteroposterior (AP) radiograph of pelvis. Displaced intracapsular fractured left neck of femur.
Figure 10.3 Postoperative anteroposterior (AP) pelvis radiograph of cemented bipolar Exeter hip.
Garden RS. Stability and union in sub capital fractures of the femur. Bone Joint J. 1964;46B(4):630.
Hoskins W, Webb D, Bingham R, Pirpiris M, Griffin XL. Hip Int. 2017;27(5):415–424.
Structured oral examination question 3#
Hip dislocation
A 23-year-old motorcyclist has been involved in a high-speed head-on collision. He is brought into the A&E department and this radiograph has been taken in the resuscitation bay. Describe the radiograph and explain how you would manage this patient Figure 10.4).
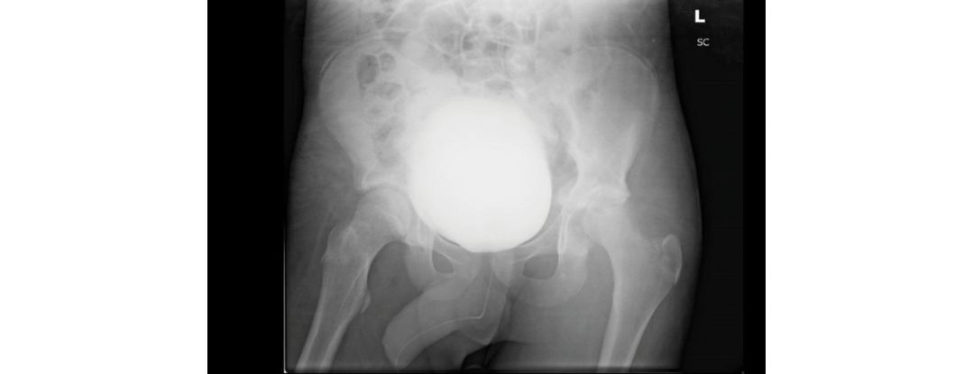
This is an AP radiograph of the patient pelvis with what appears to be a fracture– dislocation of the left hip.
Appears or is?
Is a fracture–dislocation of the left hip. These injuries are commonly associated with both factures to the femoral head and/or fracture to the acetabular wall, in this case a posterior wall fracture. The sciatic nerve is also at risk and would be a main point of concern. I would approach this patient according to the ATLS protocol, ensuring his C-spine is immobilized and making sure no life-threatening injuries are missed.
That’s fine. How would you proceed to manage his hip?
I would want to first assess his vascular status and check his pulses throughout his limb, starting with his femoral all the way down to his dorsalis pedis. I would then assess his neurology as I would beworried about a sciatic nerve injury.
Why would you get a full-length femur and a knee radiograph – it’s a surgical emergency, this will just delay hip reduction?
I would want to exclude a coexisting femoral shaft fracture or knee injury which could be missed otherwise. If there would be a significant delay geting in to theatre I may consider attempting to reduce the dislocation under appropriate sedation and analgesia in the emergency department. In theatre, I would perform the reduction with the patient supine on a radiolucent table, with my assistant applying pressure on the pelvis over the anterior superior iliac spines, while I apply longitudinal traction with hip flexion beyond 90°, with adduction and internal rotation followed by abduction external rotation and extension. Once reduced,
I would perform a test of stability. I would then place the patient on skin traction and obtain a postop
CT scan, looking at any intra-articular fragments and fractures. I would then refer this patient to a pelvic and acetabular surgeon for posterior wall fixation.
How would your management differ in an anterior dislocation?
I would need to perform a reverse Bigelow manoeuvre.
And if you were unable to reduce it closed?
In a posterior dislocation I would have to open via an extended posterior approach (Kocher–
How will you manage the CT findings?
The aim of the CT is to identify any associated fractures, determine the size of any intra- articular fractures, assess the quality of reduction andi den tif y any loose bodies in the joint.
How would you manage a femoral head fracture associated with a dislocation? CANDIDATE I would use the Pipkin classification as a guide to management (Table 10.1). Pipkin I fractures do not involve the weight-bearing surface of the femoral head and are usually excised. Conservative management is not recommended as fracture fragments may result in a non- congruent joint surface, pain on mobilization and w eight-bearing and later osteoarthritis of the joint. Type II fractures involve the weight-bearing surface of the femoral head and are anatomically reduced and fixed usually with headless compression screws. Type III fractures are difficult to reduce and fix and often require primary THA (if unreconstructable) or salvage THA if AVN develops. In type IV fractures the femoral and acetabular fractures should be managed separately, with reconstruction of the acetabulum and fixation of the femoral head fracture as required.
Figure 10.4 Fracture–dislocation, left hip.
Table 10.1 Pipkin classification of femoral head fractures.
Type I: Fracture line inferior to the fovea/ligamentum (small) Does not involve the weight-bearing portion of the femoral head
Type II: Fracture fragment includes the fovea (larger) Involves weight-bearing portion of the femoral head
Type III: As types I and II but with an associated femoral neck fracture High incidence of AVN
Type IV: Any pattern of femoral head fracture with associated acetabular fracture (coincides with Thompson and Epstein’s type V)
What surgical approach would you use to manage this injury?
The main deciding factors are associated fractures to fix and surgeon familiarity. I am most comfortable performing a posterior approach, which gives good access to areas of injured bone and capsule and is especially useful if a posterior wall fixation needs to be performed.
What complications would you warn the patient of from this injury?
The main complication following a hip dislocation is osteonecrosis of the femoral head and secondary osteoarthritis. Indomethacin is given routinely as a preventative measure.
What would be your diagnosis if the patient woke up in excruciating pain pos top with decreased sensation and loss of function distally, following closed reduction?
This is more common in posterior dislocations duet o the position of the head and neck in proximity to the nerve and the method of relocation.
Would you beworried about any other ipsilateral injury when you are faced with a hip dislocation?
Yes, apart from acetabular and femoral head fractures, one can get a neck of femur fracture.
Long-term wise, what will you tell the patient?
Around 20% of patients will require THA in the first 6 months following a femoral head fracture with a dislocation Around 55% of patients will have radiographic changes of osteoarthritis a t 10 years, although most patients function well.
Structured oral examination question 4#
Femoral shaft fracture
This is a 28-year-old male involved in a motorbike vs. car RTA leading to this injury. Describe what you see (Figures 10.5 and 10.6).
This is an AP and lateral radiograph of a comminuted displaced femoral shaft fracture at the junction of the proximal and middle thirds.
How would you approach this patient?
This is a high-energy injury and I would approach the patient according to ATLS protocols to ensure life-threatening injuries are treated first. I will then want to check sciatic nerve function and distal pulses, and check for any evidence of compartment syndrome. I would order a complete series of radiographs to include the ipsilateral hip and knee. I will place the patient on skin traction to give temporary fracture stability until definitive management is performed. Distal pulses should be checked before and after application of skin traction.
If there is a puncture wound, how would you manage it?
If there was a puncture wound then this is an open injury Gustillo –Anderson type 1. I would manage this as per the BOA/BAPRAS open fracture guidelines and the adapted BOAST guidelines. This would include antibiotics, picture, saline-soaked gauze and tetanus vaccine administration.
Assuming that this is an isolated limb injury and confirmed that it is only an ‘in to out’ puncture wound, how would you proceed?
I would use a trochanteric entry reamed antegrade cephalomedullary femoral nail. I would ensure that I have correct rotational alignment by having assessed the patient’s contralateral foot position. The goal is to get an isthmic fit and ream 1.5 mm above the required nail diameter. I would want to make sure that the femoral shaft fracture does not distract, and that the nail does not touch or perforate the anterior cortex due to the variability of the anatomical femoral bow and the bow that is built into the implant. If I had any doubts I would engage the plastic surgeons as ajoint orthoplastics case as per the BOA/BAPRAS guidelines.
What are the advantages of a trochanteric entry point compared to the standard piriformis entry point?
The piriform fossa is colinear with the femoral shaft but places the medial femoral circumflex artery at risk, particularly in adolescents and is technically more difficult to access. A lateral entry position increases the risk of varus malreduction, and an anterior entry position increases the risk of iatrogenic fracture.
How would you allow this patient to bear weight?
With this construct I would get him to fully weight-bear with physiotherapy input.
OK. Tell me about your choice of implant – in terms of its biomechanics.
The unsupported portion of nail is between the bone fragments. Bending stiffness is inversely proportional to the square of the working length. For a fracture located within 5 cm of the most proximal distal locking screw, the peak stress around the hole may exceed the endurance limit of the metal. The nail is loaded as a Cantilever beam.
Any other concerns about this injury?
Patella fractures and PCL injuries are also not uncommon, especially in dashboard injuries and front seat passengers.
How would this change your management/choice of implant?
Failure to recognize a non-displaced or minimally displaced associated neck fracture prior to fixation of the shaft can lead to displacement, a decrease in neck fixation options, atechnic ally challenging secondary procedure and increased risk of long-term sequelae.
If the femoral fracture is in the proximal third, then an antegrade cephalomedullary nail can be used to treat both. However, if the femoral fracture was distal I would choose to first perform a dynamic hip screw to rigidly fix the femoral neck fracture. I would ensure a closed anatomical reduction before fixation and use a DHS implant rather than cannulated screws as this offers a more stable fixation.
What about fixing the femoral shaft fracture first. This is more of a danger to life.
The femoral neck fracture has to be fixed as well as possible otherwise the patient may go on to develop AVN and require a THA at a very young age.
How easy is it to apply traction to the femoral neck fracture if the femoral shaft is broken?
Err ... Yes it will be difficult and it would be much easier to apply traction to the femoral neck fracture and achieve satisfactory reduction if the femoral shaft fracture is first fixed. Fixation of the shaft fracture follows as patient condition allows. Fixing the femoral head fracture first or secondis somewhat controversial.
What would you do if the femoral neck displaced during the case?
If it cannot be manipulated back then I would have a low threshold to perform an open reduction
What would your weight-bearing status be?
If I am happy with the fixation I allow patients to start weight-bearing as soon as they are happy and able to, with guidance of physiotherapy.
What are the postoperative complications you would be concerned with?
La ter on, I would be concerned with delayed union, non-union, AVN femoral head, post-traumatic osteoarthritis, leg length discrepancy, Trendelenburg gait and continued hip and leg pain.
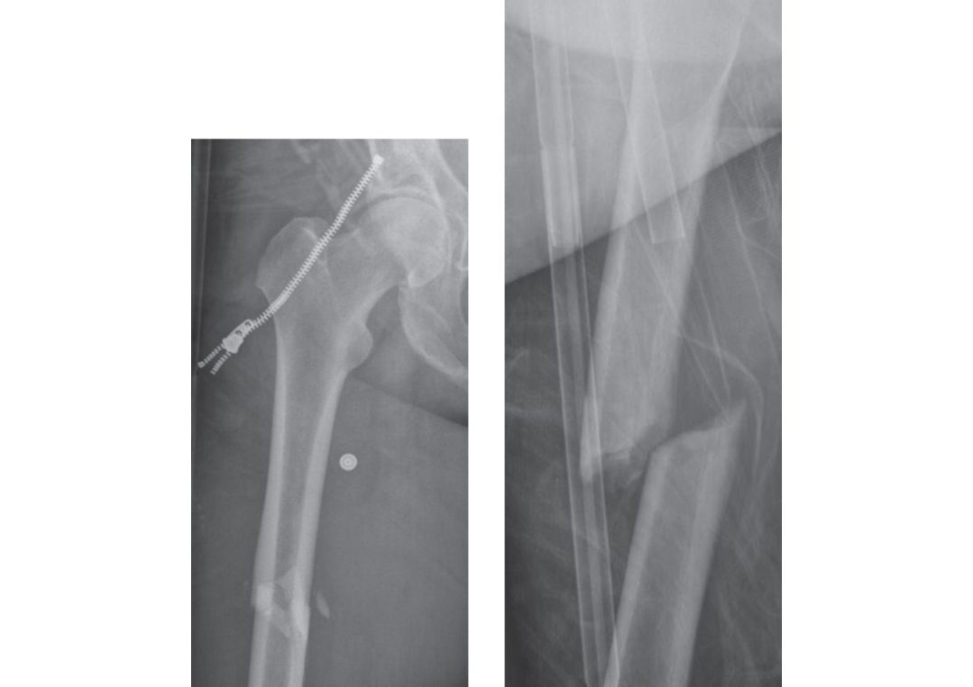
Figures 10.5 and 10.6 Anteroposterior (AP) and lateral radiographs of right femur.
Be diA, Ryu RKN. Accuracy of reduction of ipsilateral femoral neck and shaft fractures – an
Awareness of tip –apex distance reduces failure of fixation of trochanteric fractures of the hip.
Structured oral examination question 5#
Distal femur (periprosthetic fractures
Tell me about this X-ray of a 65-year-old man who fell at home and sustained this injury (Figures 10.7 and 10.8).
The current X-ray view is inadequate, and I would like to see X-rays of the full femur in two orthogonal views, AP and lateral, to ensure there is no other prosthesis further up in the femur like a hip replacement or a neck of femur fracture fixation. It does not appear grossly loose. Overall bone quality appears osteopenic.
How do you classify these injuries?
There is always some confusion as to whether examiners should be asking classification systems. As a candidate it is helpful to know a classification system, especially if it provides a direct guide to management.
How would you treat this fracture definitively?
If the patient was fit enough to undergo surgery, then my preferred method of treatment would be internal fixation of this fracture. (You can briefly mention A TLS protocol at the start, but do not waste time on this too much if the examiner has talked of definitive fixation.)
What do you think of this fixation ( Figures 10.9 and 10.10)?
The fracture has been fixed using a distal femoral locking plate using a combination of locking and non-locking screws and in a bridging mode. Although it is very unlikely to be an examiner’s own case that he/she is proudly presenting to you, still be discrete and professional.
What otherways are there of treating this fracture?
Any fracture can be treated non-operativ ely including this one, although it would be very difficult to control its position here as this is an unstable fracture and this would not be my treatment of choice in this situation.
all management options would need to be discussed with the patient and their family, including benefits and potential complications,
How do you know if the femoral component can allow a nail topass through?
Ideally, I would like to know the type of prosthesis that has been used. The paper by Jones et al. describes the commonly used knee implants int heUK that may or may not allow a nail topass through (Jones et al., 2016). Table 10.2 Classification of knee periprosthetic fr actures.3 I Undisplaced fracture Prosthesis intact II Displaced fracture Prosthesis intact III Prosthesis loose or failing Any type of fracture
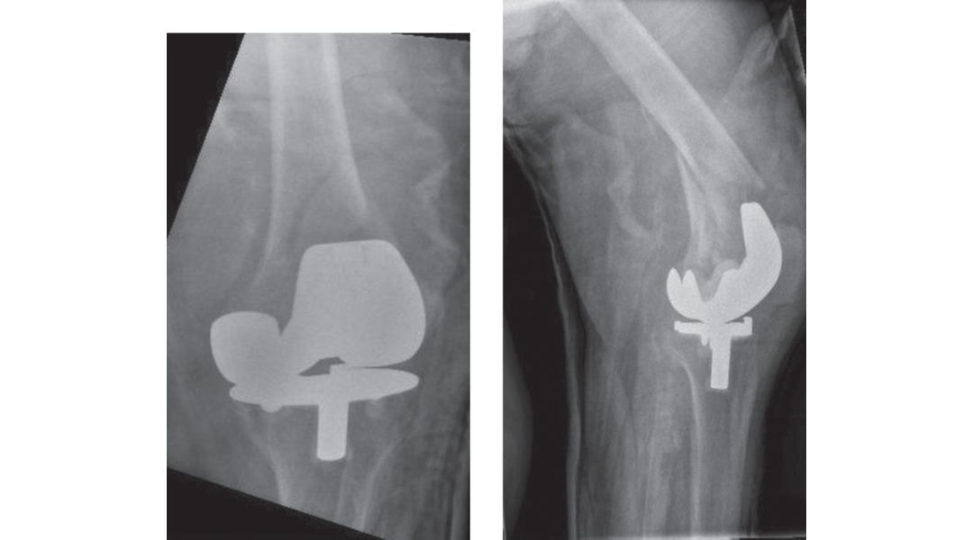
Figures 10.7 and 10.8 Anteroposterior (AP) and lateral postoperative radiographs, right femur.
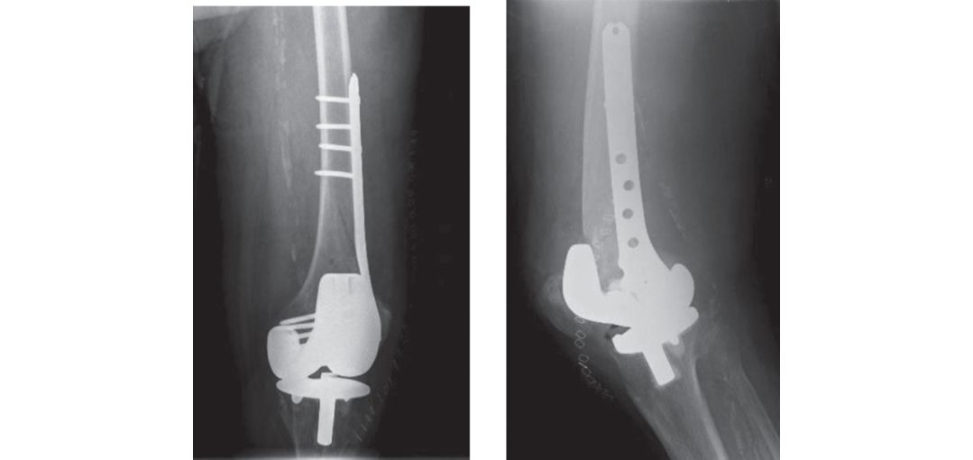
Figures 10.9 and 10.10 Anteroposterior (AP) and lateral postop radiographs, right femur.
Retrograde femoral nailing of periprosthetic fractures around total knee replacements.
Structured oral examination question 6#
Knee dislocation
A 19-year-old female on a bicycle was involved in an accident with a speeding motorbike at a cross-section. The cyclist remained alert and no other injuries were identified Shewas taken to the local Major Trauma Centre and this was one of her radiographs (Figure 10.11). Please describe this.
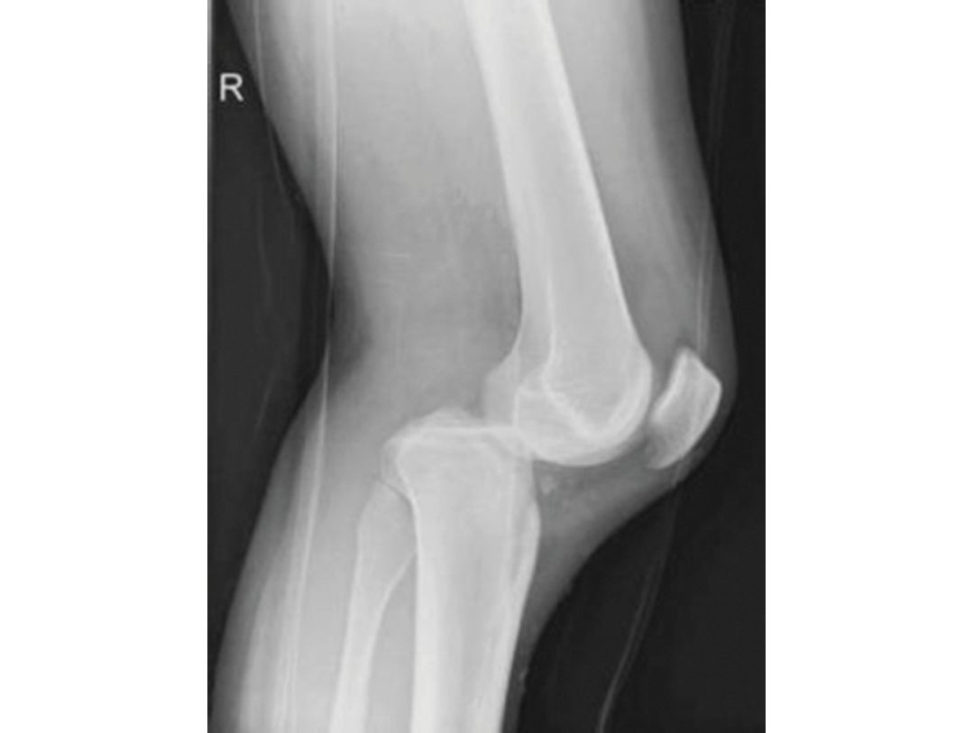
This is a lateral radiograph revealing a dislocation of the right knee. An AP radiograph is needed to determine whether this is a posteromedial or posterolateral dislocation.
How can dislocations be classified? (Note: the examiner didn’t ask you to classify this injury, but wants to see if you are aware of how this can be classified.)
One classification system is based on the tibial displacement Anterior dislocation is the most common, followed by posterior dislocation as in this case. The Schenk classification describes the dislocation according to the ligaments injured. KD I – multi ligamentous knee injury with only one cruciate ligament involved. Bicruciate injury with functionally intact collateral ligaments. Most common injury pattern. KD IV – both cruciates and both collateral ligaments ruptured (four ligaments injured). KD V – Multi ligamentous injury with periarticular fracture. Fracture/dislocation of the knee.
What is your initial management of a knee dislocation?
Given this is a high-energy injury, the patient should be approached using an ATLS protocol. Vascular injury is reported in the literature at a rate of 22–32%. Neurologic damage involving the common peroneal nerve is estimated to occur in approximately 25% of knee dislocations. Compartment syndrome is also a risk factor and should be monitored for in the first 24–48 hours. This would be with gentle in-line traction on the foot and anterior pressure on the posterior part of the tibia. If not, I would still document the neurovascular status and plan to take the patient to theatre for a reduction under
GA.
The knee was successfully reduced and remains so, but on your reassessment, there was no palpable pulse. The foot remains warm and pink. What are your next steps?
Suspicion of a vascular injury warrants immediate intervention. If time allows and no delay will be caused a CT angiogram would be very useful. An on-table angiogram can be performed in theatre. If there was concern about an ischaemic limb then a popliteal shunt would take precedence followed by external fixation and then formal vascular repair or bypass surgery.
And what if there is a pulse?
As this is a high-energy injury, I would discuss this with the radiologist and arrange a CT angiogram. If there is any difficulty in obtaining the CT, I would perform an ankle-brachial pressure index. An indexless than 0.9 in the context of this injury warrants surgical exploration. The benefit of the CT in such injuries is that it can detect intimal t ears in the popliteal artery which might be masked by a normal pulse. Many knee dislocations had intact distal pulses with no hard evidence of vascular damage. In this group, if the ABI is < 0.9, emergent angiography is done. Again, in this group, if the ABI is ≥ 0.90, patients are observed, and pulse checked frequently.
Which types of dislocations are vascular injuries most commonly seen in?
Around 20% of all dislocations have a vascular insult, with 50% being an anterior or posterior knee dislocation Anterior dislocations generally have an intimal t ear from the traction applied on the artery, while posterior dislocations more commonly lead to complete tear of the popliteal artery.
What is your order of ligament reconstruction in a multi ligament knee injury?
It all depends on the ligamentous injuries found on the MRI scan. Staged treatment simplifies the operative process and shortens operative time in thea cute phase, decreasing the rate of arthrofibrosis compared with acute surgery or repairing or reconstructing all injured ligaments.
How else can this injury be treated?
If the dislocation has been reduced and is relatively stable, and there was no neurological or vascular concert, the knee can be placed in a brace with early rehabilitation. Any areas of instability that remain can be addressed. The commonest complication of knee dislocations (pre- or post-reconstruction) is arthr ofibrosis leading to stiffness. Inf act, a large proportion of multi ligament knee reconstructions require an MUA to improve the range of motion.
Figure 10.11 Posterior dislocated right knee.
Structured oral examination question 7#
Open fractures of the lower limb

What would be your management?
This is an open fracture of the tibia and I would like to manage this as per the BOAST 4 guidelines. (You must know the BOAST 4 guidelines thoroughly.) As per these guidelines, such injuries should be managed jointly by the orthopaedic and plastic t eam. The fracture should be splinted in an above-knee backslab. (Be prepared to be asked about the Gustillo –Anderson classification of open fractures.)

soonest.
When should surgery be done?
There is evidence to suggest that the outcomes are better if done in a timely fashion by specialists rather than early surgery by less-experienced surgeons (Reuss, 2007). Debridement should be performed by senior plastic and orthopaedic surgeons working together within 12 hours of the injury for solitary high-energy open fractures and within 24 hours of injury for all other low-energy open fractures. Immediate debridement for highly contaminated wounds such as marine, agricultural or sewage.
What antibiotics will you give and for how long?
At debridement, co- amoxiclav (1.2 g) and gentamicin (1.5 mg/kg) are administered and continued for 72 hours or definitive wound closure, whichever is earlier.
How will you treat the fracture?
If primary closure is possible, and there is no significant bone loss, then my treatment of choice would be a locked intramedullary nailing of the tibia. Definitive skeletal stabilization and wound cover should be achieved within 72 hours and should not exceed 7 days. If there is bone loss or if the wound requires a flap cover by the plastics t eam, then I would consider definitive fixation using an external fixator device.
What other concerns would you have regarding this injury before or after the surgery?
As this is a high-energy injury I would be concerned about development of compartment syndrome
How would you deal with this?
However, if I was in any doubt about compartment syndrome, I would take the patient to theatre, in conjunction with the plas tic surgeon, for a fasciotomy. (Be prepared to talk about the recommended incisions for fasciotomy.)
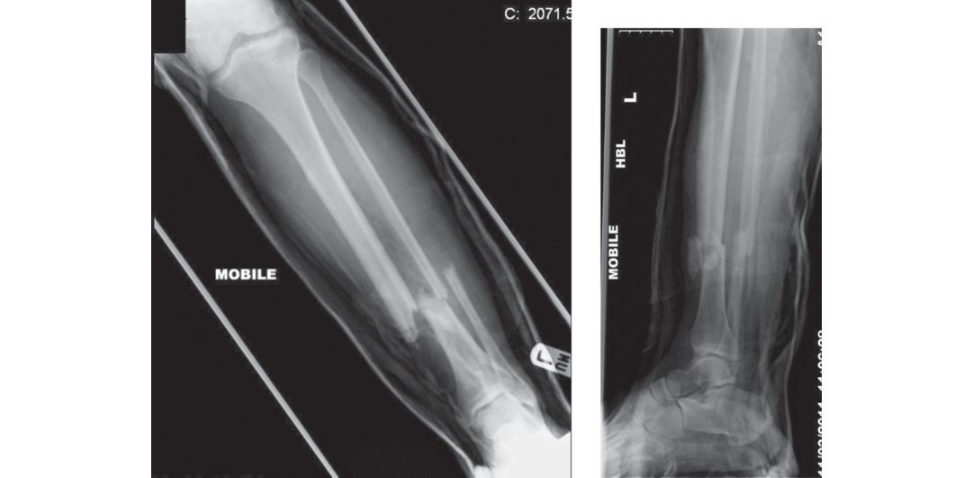
Figures 10.12 and 10.13 Anteroposterior (AP) and lateral radiograph, open left tibial fracture.
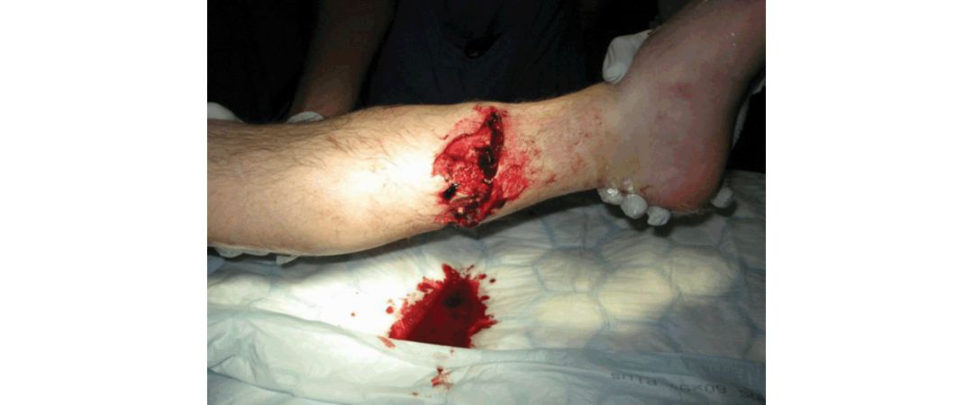
Figure 10.14 Open tibia fracture.
Reuss BL, Cole JD. Effect of delayed treatment on open tibial shaft fractures. Am J Orthop. 2007;36:215–220.
Structured oral examination question 8#
Tibial plateau fractures
This 45-year-old gentleman came off his motorbike and sustained the following injury (Figures 10.15 and 10.16). What are your thoughts and how would you manage the patient?
These are the AP and lateral view X-rays of a right knee. The most obvious abnormality here is a fracture of the proximal tibia involving both the tibial plateaus. Initial management in the A&E department would involve splinting the fracture in an above-knee backslab, providing pain relief and then planning for fixation.
This is a closed fracture and neurovascularly intact. What type of fracture is this? What other investigations would you want?
(Explain the types of Schatzker fractures and also that Types 4, 5 and 6 usually signify high-energy injuries and are more associated with neurovascular problems.) I would ideally want to obtain CT scans to define the fracture better and plan for further treatment and possibly also a CT angiogram to ensure there is no damage to the arteries.
How would you like to treat this fracture?
I would prefer to treat this fracture operatively. This would involve taking the patient to theatre and puting on a spanning external fixator across the knee away from the zone of injury. Following this, I would wait until the soft tissues se tile down before planning definitive fixation.
Where would you place your external fixator pins?
I would put two pins in the femur either anteriorly or anterolaterally and two pins in the tibial shaft a way
What would be your definitive fixation plans for this fracture?
The patient should be positioned supine on theo per ating t able that is broken to allow the knees to flex to 90°. I would like to fix this fracture using a dual-incision approach with an anterolateral and a posteromedial incision.
The two incisions should be at least 7 cm apart. The joint capsule is opened through a submeniscal arthrotomy. I would like to use plates and screws to but iress the posteromedial fragment first and then an anterolateral locking plate for fixation of the r est of the fracture.
How else could this fracture be fixed?
This fracture could also be fixed definitively using external fixator methods like circular frames (Ilizarov, TSF, TL-Hex, etc.).
Which treatment method of the two has better results?
The Canadian OTS multic entre RCT from 2006 (COTS, 2006) showed that functional results were similar in both
Why would you not use a single midline incision?
Single midline incisions are known to have poor results in these fractures as they involve a significant amount
How would you rehabilitate this patient?
(Always mention that this would depend on the type of fixation you have achieved, the comminution noted at the time of surgery, other associated injuries, etc. The postoperative regime should be tailor-made for each patient and depends to an extent on the fixation achieved.)
What complications could occur?
This is a serious injury and I would warn the patient of the possibility of compartment syndrome, infection, delayed
What about the final outcome?
In Rademakers et al. the overall incidence of osteoarthritis has been reported to be 9% compared to 27% if the axis deviation > 5°.
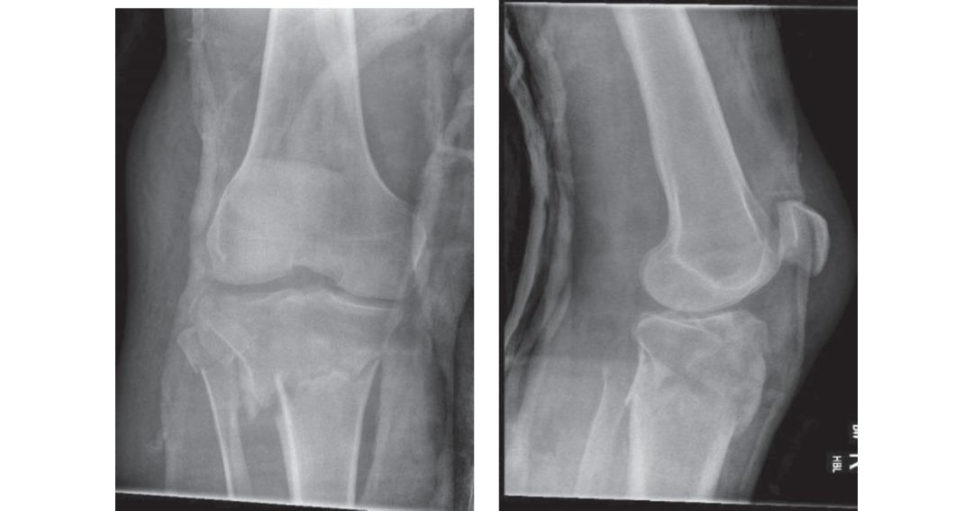
Figures 10.15 and 10.16 Anteroposterior (AP) and lateral radiographs, right knee.
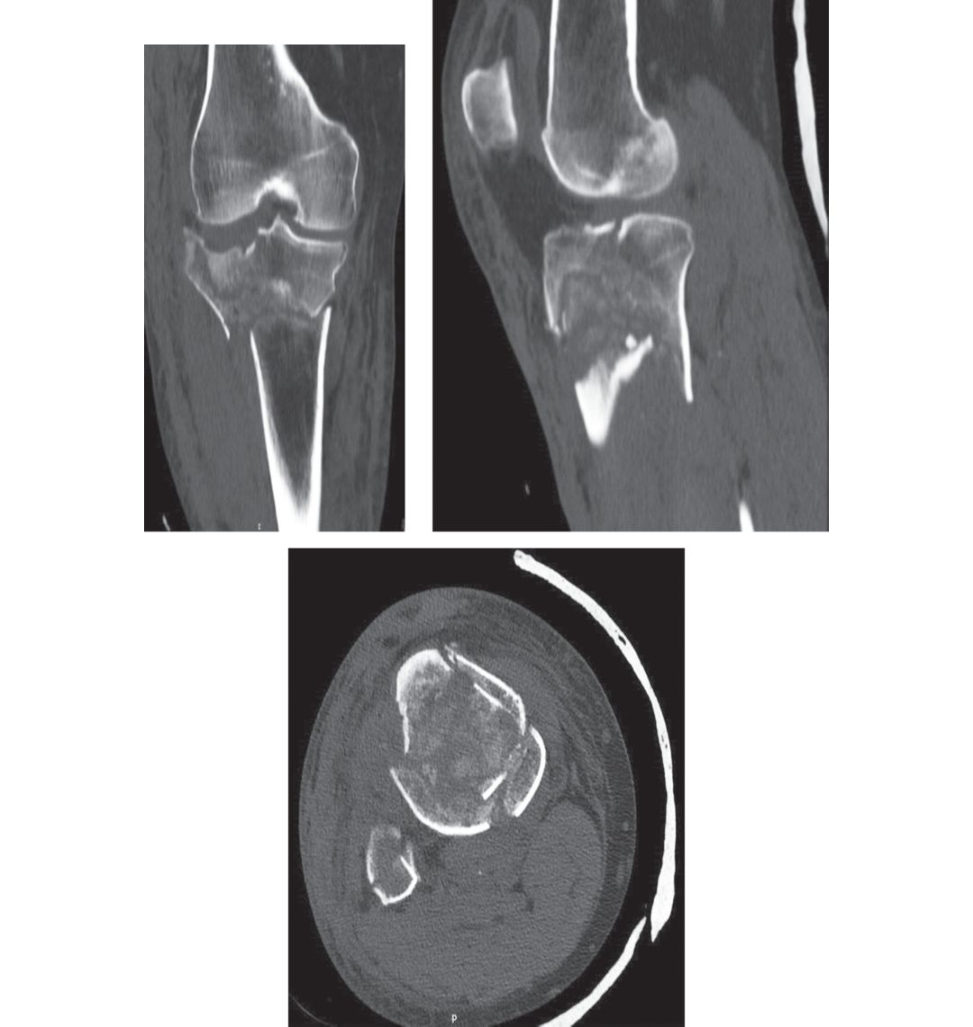
Figures 10.17, 10.18 and 10.19 Coronal, sagift al and axial CT images, right knee.
Schatzker J, McBroom R, Bruce D. The tibial plateau fracture. The Toronto experience 1968–1975. Clin
Orthop Relat Res. 1979;138:94–104.
Canadian Orthopaedic Trauma Society. Results of a mulft-cen tre, prospective, randomized clinical trial. J Bone Joint Surg Am. 2006;88(12):2613–2623.
Structured oral examination question 9#
Tibial plafond fractures
These are the radiographs of a 54-year-old cyclist who was hit by a van and sustained this injury (Figures 10.20 and 10.21). You are called in to the emergency room via a trauma call. Tell me what you see and your initial management plans.
There appears to be a fracture of the distal tibial plafond as well as the fibula. This is a high-energy injury and I would initially manage the patient via ATLS principles. If there are no neurovascular problems, I would aim to reduce the fracture–dislocation in the Emergency department using appropriate sedation and muscle relaxant depending on the local protocol.
What would you do if there was no pulse at your initial assessment?
I would still proceed to reduce the fracture–dislocation, but additionally I would call for the vascular team and plan to take the patient to theatre immediately if the pulse did not return following reduction.
If you needed to take the patient to theatre, what should be the preferred sequence of intervention?
The immediate intervention should be aimed a t restoring blood flow. The artery should be explored to check for any kinking of the vessels or any damage. Subsequent to this, I would aim to apply a bridging external fixator to stabilize the fracture and then the vascular surgeon should restore definitive flow through a primary repair or a graft or bypass.
What would you do after temporarily stabilizing the fracture and restoring blood flow?
I would be observant for compartment syndrome initially . I would base my treatment using a Span, Scan and Plan approach.
What would be your preferred mode of treating this fracture?
I would prefer to treat this fracture definitively with an external fixator as there may already be skin incisions that may compromise my approach for internal fixation.
If you were planning to perform internal fixation, how would you plan your surgery?
I would take advice from a plastic surgeon with regard to the skin incisions. I would aim to restore the fibular length first and then fix the
What are the typical fracture fragments that you get in a tibial plafond fracture?
The usual fragments are medial, anterior or anterolateral, posterior or posterolateral and occasionally a die-punch fragment.
What are the complications associated with pilon fractures?
Immediate intraoperative complications include damage to neurovascular structures and inability to close the wound if performing internal fixation; immediate postoperative complications includeD VT, PE, infection compartment syndrome.
Is there more incidence of arthritis with internal fixation or external fixation? Which type of fixation has better results?
Meta-analysis as well as randomized controlled trials have shown that they have equivalent results with equal incidence of complications including arthritis (W yrsch,
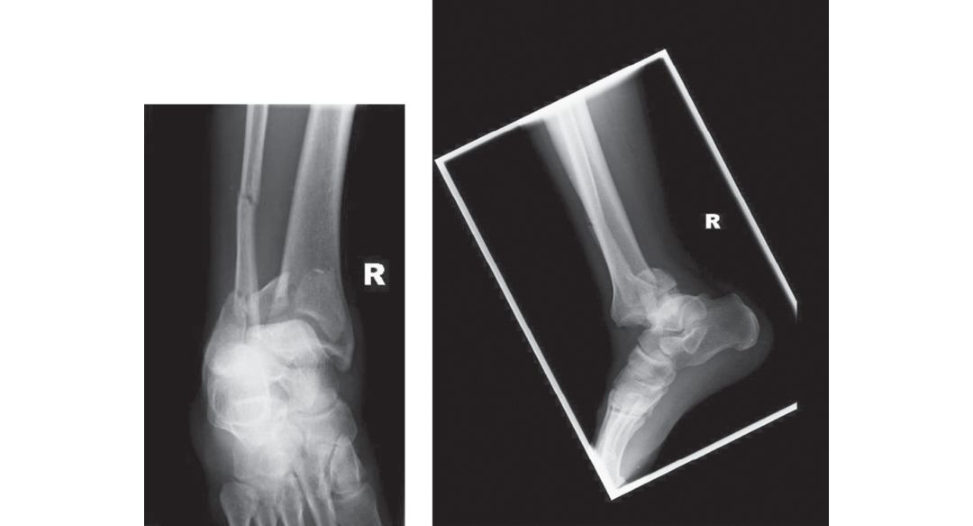
Figures 10.20 and 10.21 Anteroposterior (AP) and lateral radiographs, right distal tibia.
Wyrsch B, McFerran MA, McAndrew M, et al. A randomized, prospective study. 1996;78(11):1646–1657.
Wang D, Xiang JP, Chen XH, Zhu QT. A meta-analysis for postoperative complications in tibial plafond fracture: open reduction and
Notes
1. Gardner S, Weaver MJ, Jerabek S, Rodriguez E, Vrahas M, Harris M. J Orthopaed. 2015;12(2):75–80.
Comparison of the functional out come of DHS versus cannulated cancellous screws in Pauwels type II and III fracture neck femur in young adults.
3. Rorabeck CH, Taylor JW. Classification of periprosthetic fractures complicating total knee arthroplasty. Orthop Clin. 1999;30(2):209–214.