Chapter 16 Paediatric trauma
Structured oral examination question 1#
This 10-year-old boy was hit by a car while crossing the road and sustained a closed head injury with GCS 8/15. He has been intubated because he is combative. A secondary survey has revealed this associated limb injury (Figure 16.1).
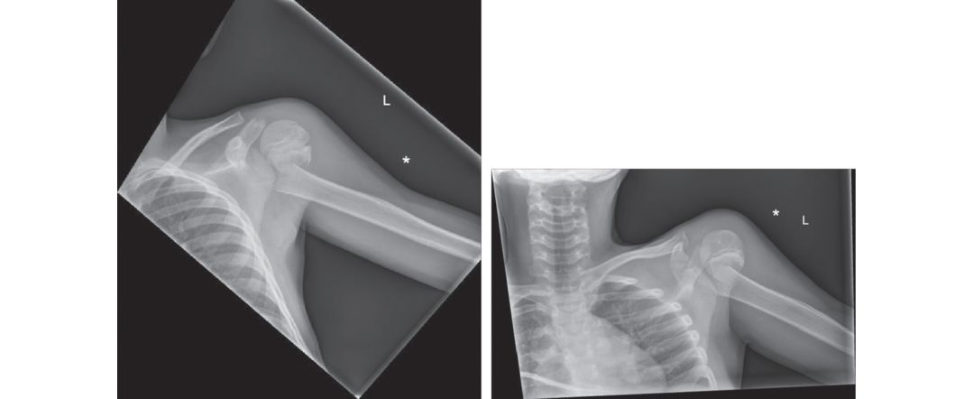
It’s not quite a lateral Y-view I’m suspecting as the radiographer couldn’t get the correct projection Therea transverse fracture of the metaphysis, which is angulated medially due to the pull of the pectoralis major.
Assume that there is no associated neurovascular deficit. How are you going to manage this patient?
My concern is that the fracture fragments are completely translated with no bony contact and the distal fragment is being pulled medially into the axilla. I would screen with the image intensifier to check the shoulder is in joint and realign the fracture with gentle traction.
What if it doesn’t reduce closed?
In terms of the fracture, I would stabilize this with retrograde K-wires from the lateral side through a mini-incision. The major structure at risk from percutaneous K-wires is the axillary nerve. The nerve is a branch of the posterior cord, and travels through the quadrangular space with the posterior circumflex vessels before going anterior around the surgical neck, underneath the deltoid.
What do you think about this postop radiograph (Figure 16.1c)? I thought these fractures were usually managed conservatively?
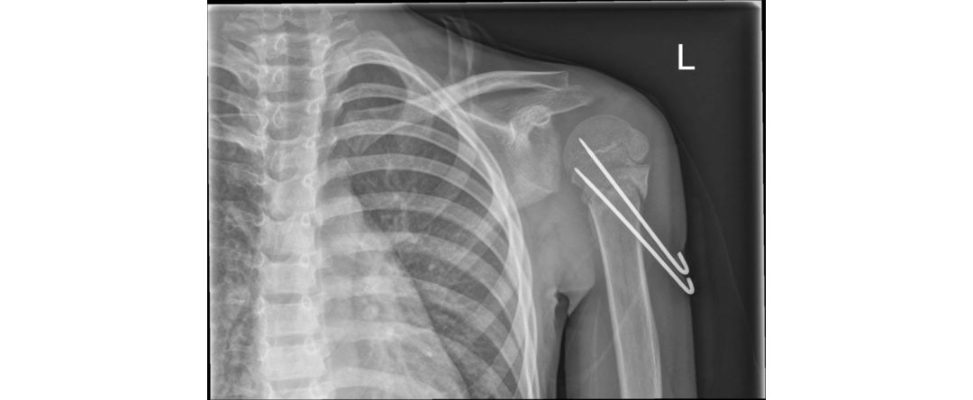
I can see the fracture is reduced and held with K-wires from the lateral side obliquely into the medial metaphysis. I would be careful about allowing the patient to mobilize before the wires come out at 4 weeks; I’d anticipate there might be limited hold in the metaphysis.
For proximal humerus fractures in young children, almost any level of deformity is acceptable, for instance, bayonet apposition, as the remodelling potential is so gr eat.
such as < 30° angulation or < 50% translation, and the reis a higher incidence of stiffness compared topa tien ts treated non-operativ ely [1].
Figure 16.1a and 16.1b Displaced proximal humerus fracture.
Figure 16.1c Anteroposterior (AP) radiograph, shoulder following K-wire fixation.
Structured oral examination question 2#
This 7-year-old child fell from swings in the park sustaining a closed injury (Figure 16.2a and 16.2b).
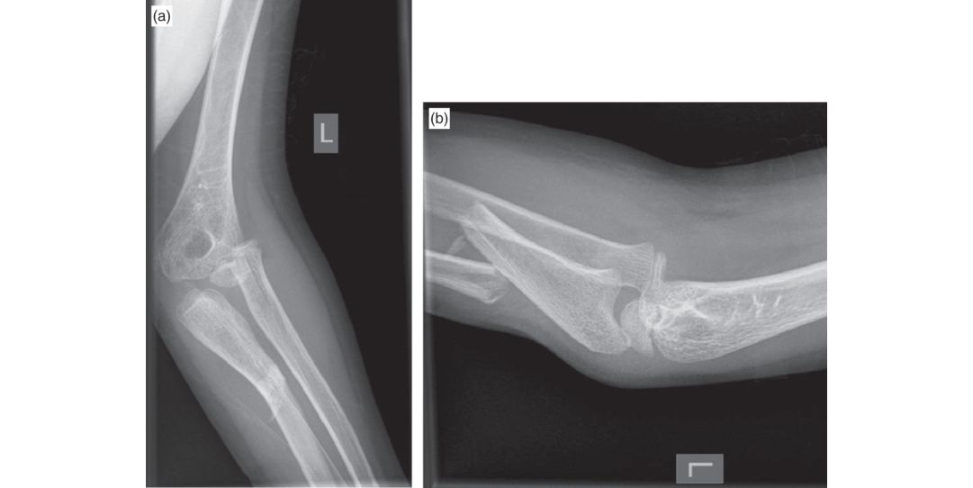
I can see AP and lateral radiographic views of the left elbow. This is a Monteggia injury where there is a displaced and volarly angulated ulna fracture in addition to an anterior dislocated radial head.
Let’s assume there is available timet o do this on the trauma list and you are taking the child to theatre. What are the principles of treating this injury What would be your surgical plan?
By restoring the ulna length this should reduce the radial head. I would initially attempt a closed reduction by traction. If I had an y doubts about the reduction, I would plate it.
How do you perform an elastic nailing? What problems do you anticipate arising if you try to use a nail for this?
Initially I ’d screen (with the image intensifier) and mark the physis and the fracture with a skin marker. The nail is sized according to one-third diameter of the isthmus. By pre-bending, the nail has elastic recoil, which exerts a force in the intramedullary canal to reduce the fracture. Elastic nails are best suited to diaphyseal fractures.
Let’s say the nail doesn’t work. Even when you plate the ulna, the radial head does not reduce. What do you do?
I’d recheck I had properly reduced the fracture. In this case I would suspect that the annular ligament is either torn or interposed, blocking reduction of the radial head. I’d open the radiocapitellar joint via aKo cher’s approach (between the anconeus and ECU).
Figure 16.2a and 16.2b Anteroposterior (AP) and lateral radiographs, left elbow.
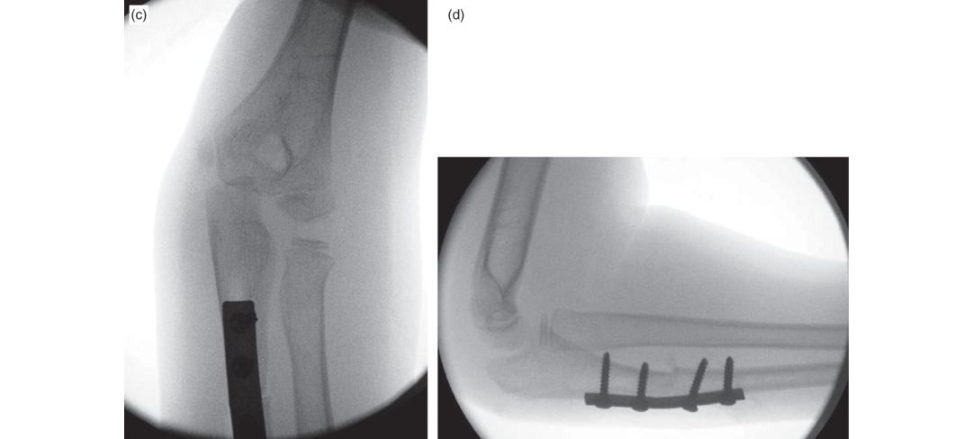
Figure 16.2c and 16.2d Intraoperative image intensifier anteroposterior (AP) and lateral radiographs, left proximal ulna.
Structured oral examination question 3#
This 6-year-old child is a new referral to the fracture clinic, please look at and describe these radiographs (Figures 16.3a and 16.3b).
This looks like a Milch type 2 and the fracture line extends from the trochlear groove into the metaphysis. A Milch type 1 is lateral to the ulnohumeral articulation: going through the capitellar physis into the metaphysis. Type 1: under 2 mm of displacement, indicating the presence of a cartilaginous hinge. Type 2: where there is between 2 and 4 mm of displacement with intact intra-articular cartilage on arthrogram. Type 3: greater than 4 mm of intra-articular displacement.
What problems can you foresee with this fracture?
These are intra-articular fractures and have a higher incidence of specific complications: Non-union due to synovial interposition from the joint surface, causing persistent elbow instability. In undisplaced fractures, assessing the intra-articular component of the fracture can be difficult on plain radiographs, as the distal humerus is cartilaginous. In these cases, an MRI or EUA and arthrogram may be useful to assess the fracture further.
How do you surgically manage displaced fractures?
For those fractures where the arthrogram demonstrates an articular hinge or mildly displaced (< 2 mm) fractures, the fracture can be stabilized with percutaneous divergent wires. For those fractures that are displaced, visualizing the articular surface is required. Reduce the fracture and hold with at least two divergent K-wires.
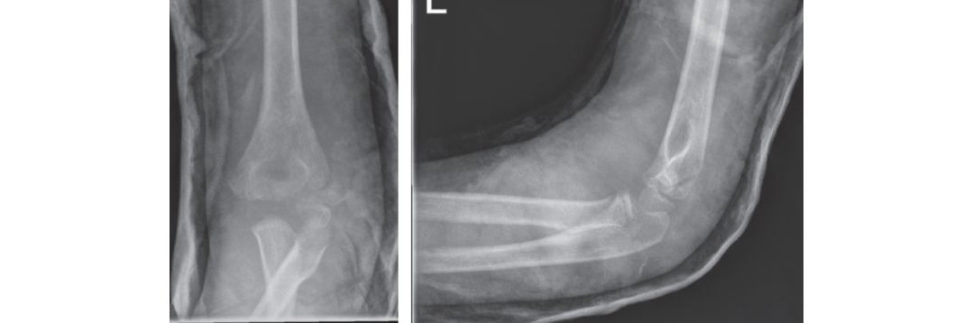
Figure 16.3a and 16.3b Anteroposterior (AP) and lateral radiographs, left elbow.
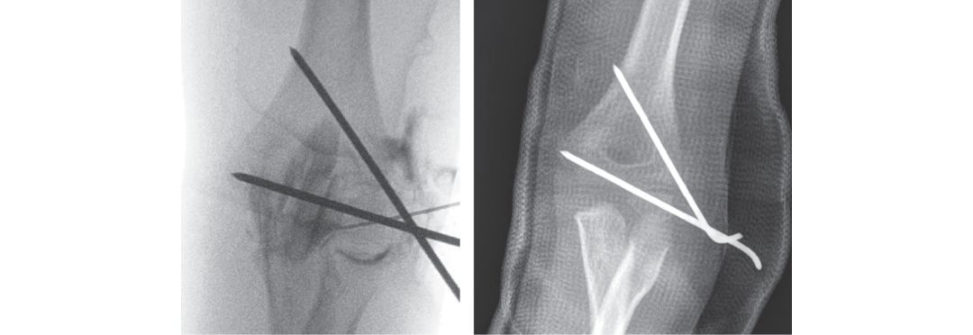
Figure 16.3c and Figure 16.3d Intraoperative arthrogram of left elbow and postop radiograph incast.
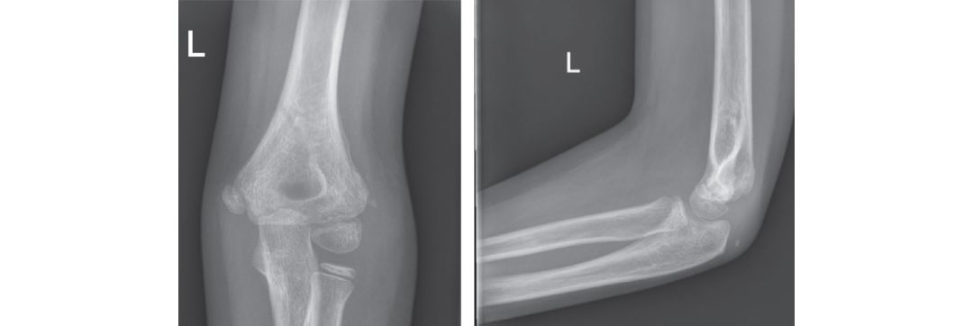
Figure 16.3e and 16.3f Anteroposterior (AP) and lateral radiographs, left elbow after healing.
Structured oral examination question 4#
This 7-year-old boy was waiting for his dinner and fell outside in the back garden (Figure 16.4a).
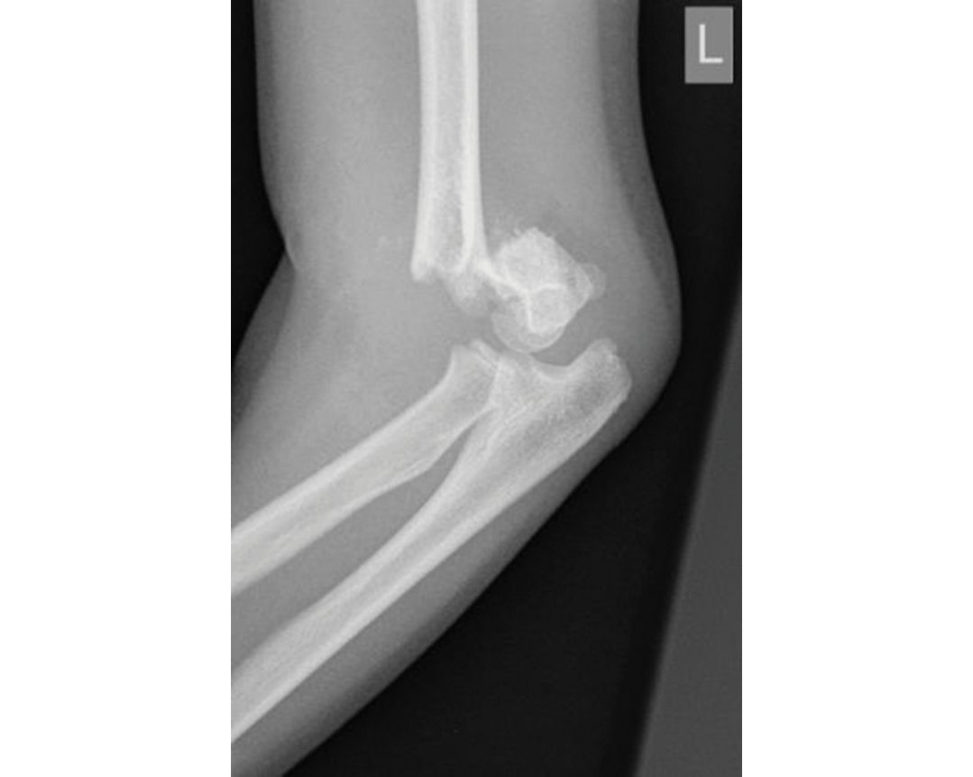
This is a lateral radiograph in a skeletally immature patient which demonstrates a displaced supracondylar fracture. Typically, the mechanism is a fall with the elbow extended and axial loading. I would check the motor and sensory function of the median radial and ulna nerves. I would splint in a position of comfort after intranasal diamorphine.
The child has a pink hand that’s perfused but no palpable radial pulse. There is no motor or sensory deficit.
While the evidence is a pink, perfused hand without any neurological deficit, it can be elevated and observed [2,3]:
He’s fasted, consented and ready. Explain what you are going to do.
I would reduce this by traction with the elbow in slight flexion. I would first check the AP to see I’ve got it out to length and correct for medial or lateral translation. I then flex the elbow with my thumb pushing on the olecranon, and depending on which best reduces the fracture, the forearm is either supinated or pronated. If the child’s fingers can touch their shoulder: this indirectly shows the fracture is reduced. I do this by laying a 2.0-mm K-wire on the skin and marking with a skin marker. Either lateral divergent wires or a crossed configuration is biomechanic ally stable, with maximal spread and avoiding crossing at the fracture site. On the medial side, I would extend the elbow to take the ulna nerve away from the epicondyle, then make a mini-incision to see the bone before placing and driving the medial wire in. I would screen the fixed construct under real-time imaging to check stability.
I’d recheck pulse and circulation before applying abacks lab.
You find the hand is white when you recheck his circulation!
If I thought this was the case I’d remove the wires, place him on straight longitudinal traction and c all the vascular surgeon, who would do an on-table angiogram and explore the brachial artery through an anterior approach.
Figure 16.4a Lateral radiograph, left elbow.
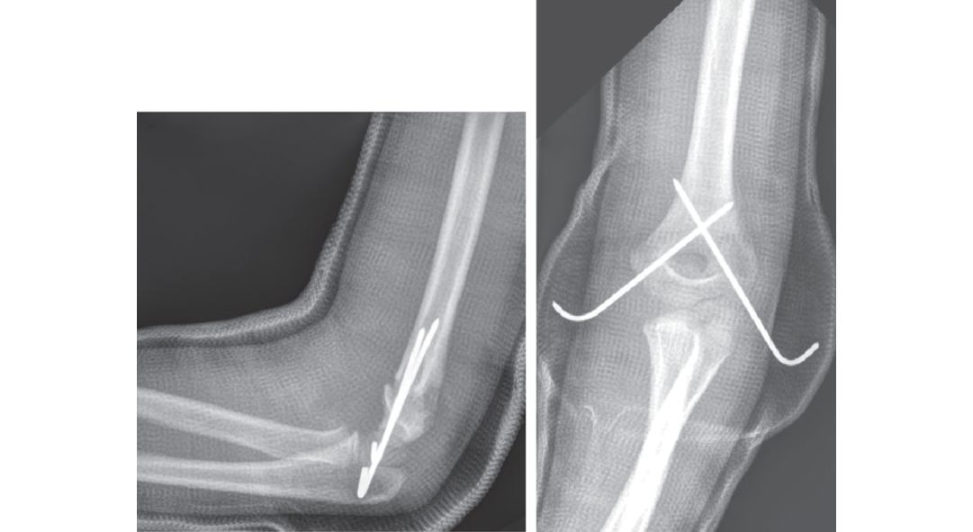
Figure 16.4b and 16.4c Lateral and anteroposterior (AP) radiographs incast.
Structured oral examination question 5#
This 13-year-old boy had a previous forearm injury which healed, and he was due to have an operation to remove the metalwork. He was involved in exuberant play and pushed over (Figures 16.5a and 16.5b). The injury is closed and neurovascularly intact.
The reis an elastic nail in the ulna with a double bend, with mid-shaft r e-fractures of both bones.
Could he betaken to theatre and have it manipulated, and a cast putback on it?
As he’s 13 years old, there isn’t much remaining growth. The mid-shaft position of the fracture also implies that this will have poor remodelling potential. I think trying to manipulate his forearm closed and achieve an adequate reduction of both bones is unlikely to work.
Are there any technical problems you anticipate while doing this?
Trying to remove the bent nail may be a problem, in which case I would open the fracture site and cut the nail.
Is it necessary to remove metalwork? Do you know any evidence?
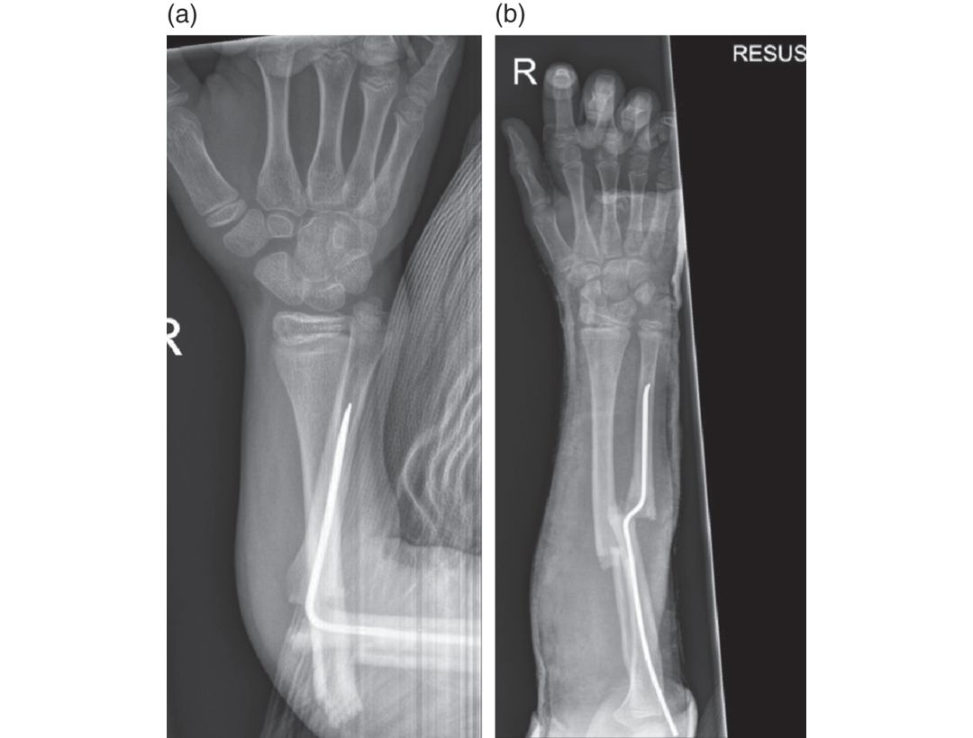
Figure 16.5a and 16.5b Anteroposterior (AP) radiographs, right forearm.
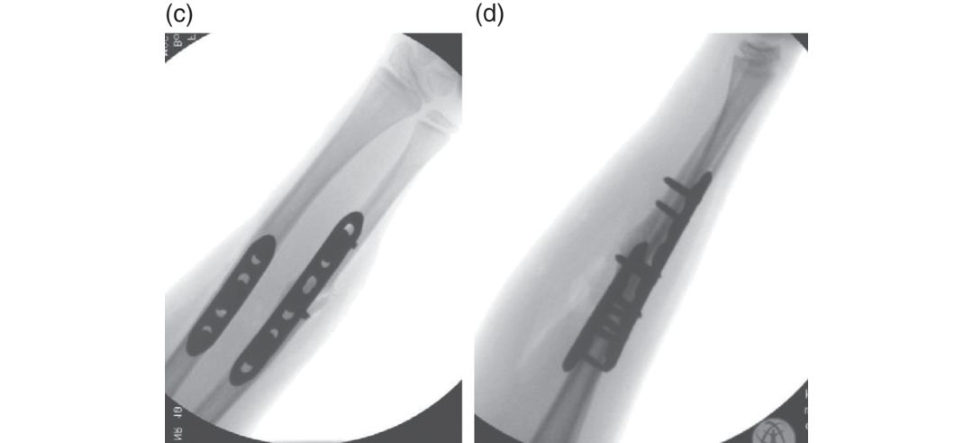
Figure 16.5c and 16.5d Anteroposterior (AP) and lateral intraoperative images.
Assuming there are no further complications then they can be left in situ. With the risk of subsequent periprosthetic fracture and the difficulty of excavating metalwork, some surgeons have a low threshold to remove paediatric metalwork.
There is morbidity associated with metalwork removal, which includes a 40% complication rate when.
Structured oral examination question 6#
This 8-year-old boy has had multiple previous fractures which have healed but left him with clinical deformities of the long bones ( Figure 16.6a). He had an innocuous fall which caused this injury (Figures 16.6b and 16.6c).
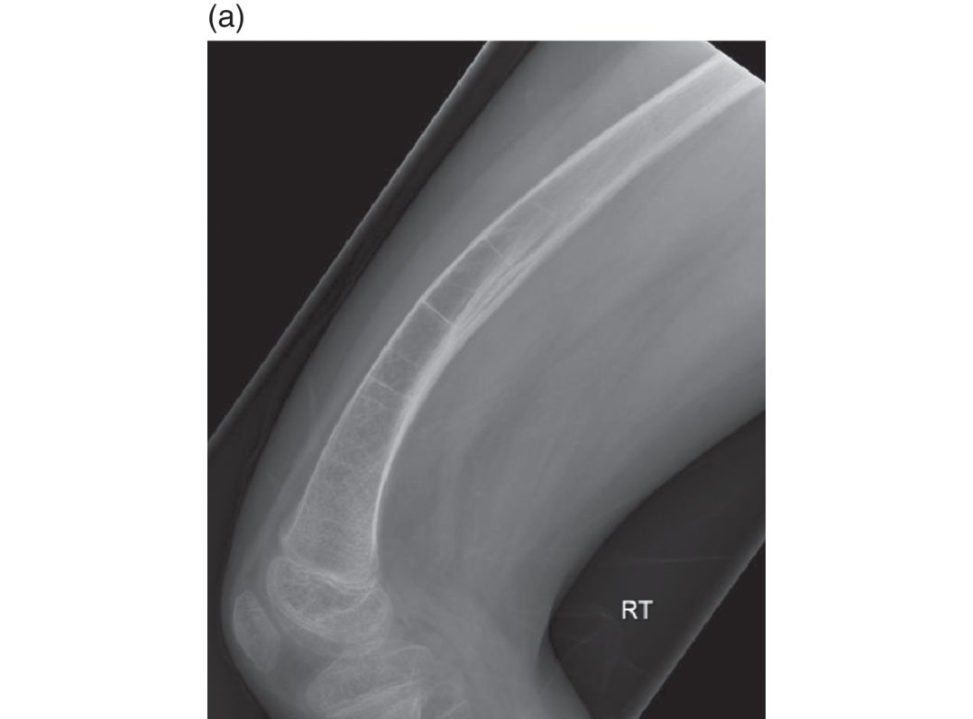
I can see a pre-injury radiograph of a right femur with a significant anterior bow and appearances of Park Harris growth arrest lines. On the right-hand side AP and lateral, there is an oblique fracture through the distal third of the femur with a Thomas splint.
What are Park Harris growth arrest lines?
Park Harris lines are transverse sclerotic lines in the metaphysis which correspond to stressor an insult to the bone and then resumption of growth.
Do you know of any paediatric orthopaedic conditions where we use bisphosphonates?
Osteogenesis imperfecta.
His sclera are blue and dad is affected. What type of OI does he have?
Likely Type 1 (according to Sillence): as they have blue sclera and the condition is autosomal dominant.
What is the treatment for this fracture? Are there any technical considerations?
I would discuss with a tertiary centre because of his pre-existing OI, but essentially the principles of management are to restore alignment and correct pre-existing deformity. The options are limited due to the anatomical abnormality and background osteopenia. I am aware of the use of growing telescopic rod systems. The rods have a trochanteric entry point with male and female sliding components. Postoperatively I will liaise with his physician about the commencement of bisphosphonate therapy.
Figure 16.6a Lateral radiograph, femur.
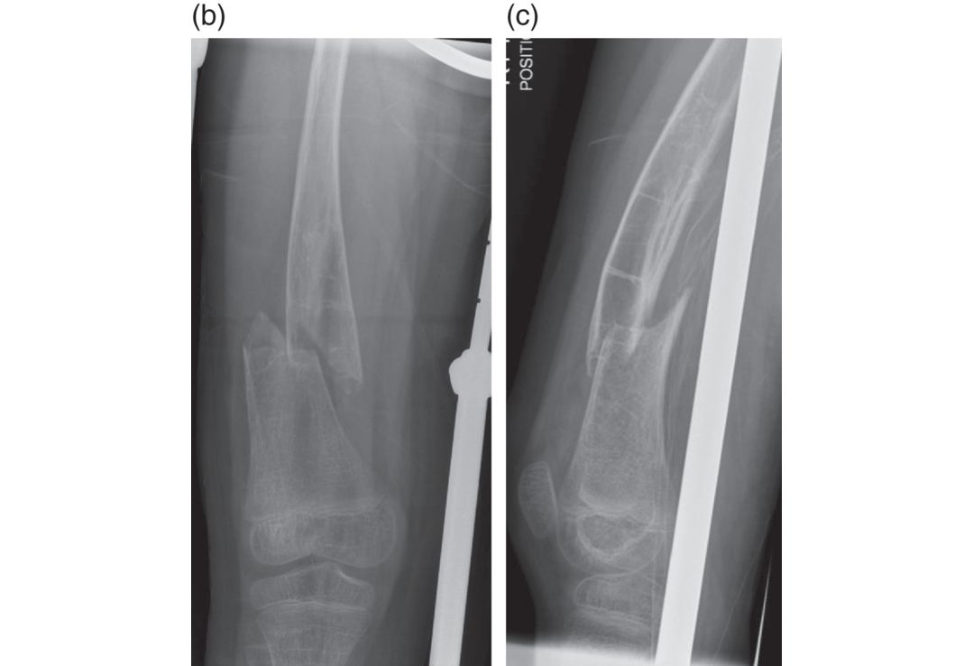
Figure 16.6b and 16.6c Anteroposterior (AP) and lateral radiographs, femur.
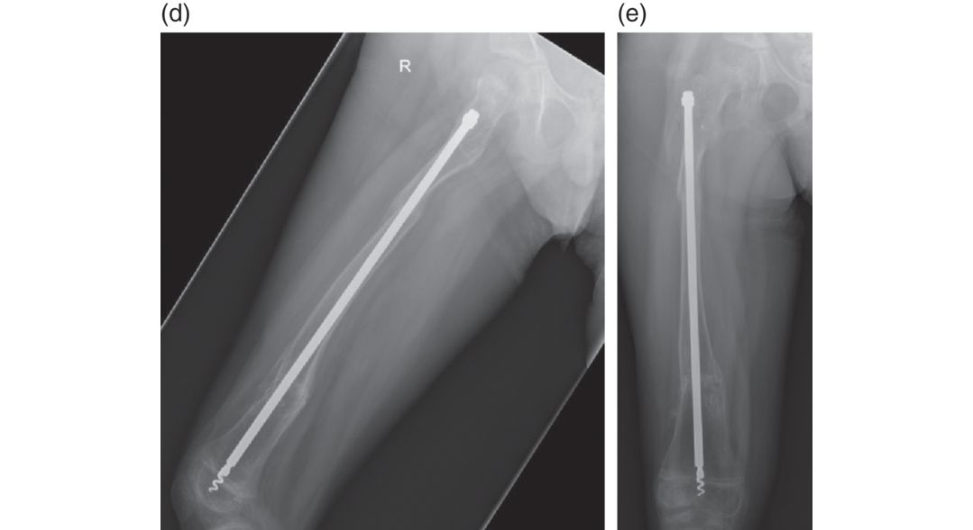
Figure 16.6d and 16.6e Lateral and anteroposterior (AP) postoperative radiographs, femur.
Structured oral examination question 7#
This 8-year-old girl sustained an injury walking home from school when she was hit by a car at low speed, pedestrian versus car (Figures 16.7a and 16.7b).
These are AP radiographs in a Kendrick traction splint used by paramedics at the scene as well as in a Thomas splint. I can see a short, oblique fracture of the femoral diaphysis, at the junction of the proximal and middle thirds. Is this a closed, isolated injury?
Yes. On secondary survey, you are happy this is an isolated injury and the patient is physiologically suitable for an operation, if you think it appropriate.
I would be inclined to treat this by elastic nails. It’s a fracture in a paediatric femur with an appropriate size of canal for elastic nails: typically, a child between 5 and 10 years of age. My set-up would be a Jackson table with my assistant applying traction on the leg. I would use retrograde nails via medial and lateral entry points about 2.5 cm above the distal physis. The nails are pre-bent, so the apex is at the fracture site.
Stable? What does that mean? Is it rigidly fixed? What type of bone healing occurs?
Fracture healing occurs by secondary bone healing with callus formation; this is a relative stability technique. The nails are far from rigid. In children greater than 50 kg bodyweight, stainless steel flexible nails can be used to increase the nail strength and have been shown to have a lower rate of malunion compared to titanium elastic nails [ 5].
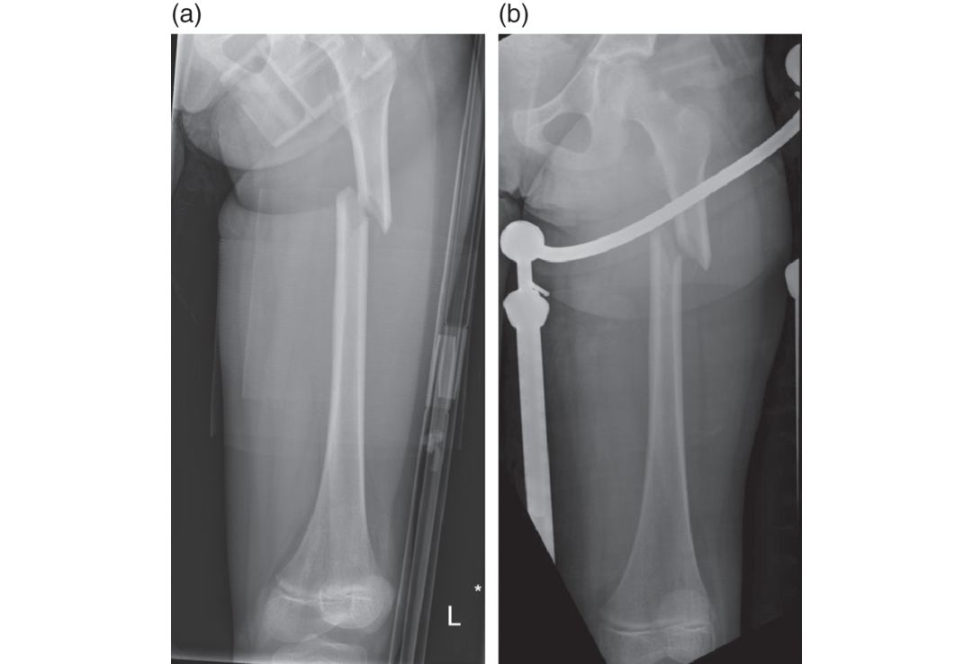
Figure 16.7a and 16.7b Anteroposterior (AP) radiographs, femur.
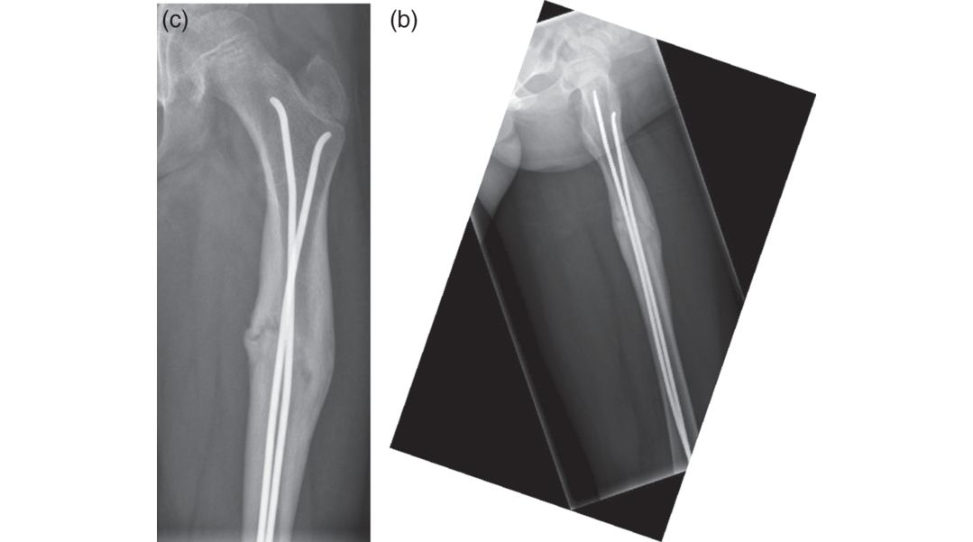
Figure 16.7c and 16.7d Anteroposterior (AP) and lateral postoperative radiographs, femur.
Structured oral examination question 8#
This 14-year-old boy was a trauma call from an RTA. He has sustained multiple rib fractures and a lung contusion on the same side as this closed injury to his leg. He’s had a pan-CT scan in A&E resus (Figure 16.8a) and is awake and stable on paediatric HDU. The general surgeons have said his liver laceration can be managed conservatively without the need for laparotomy and CT has excluded a pelvic injury.
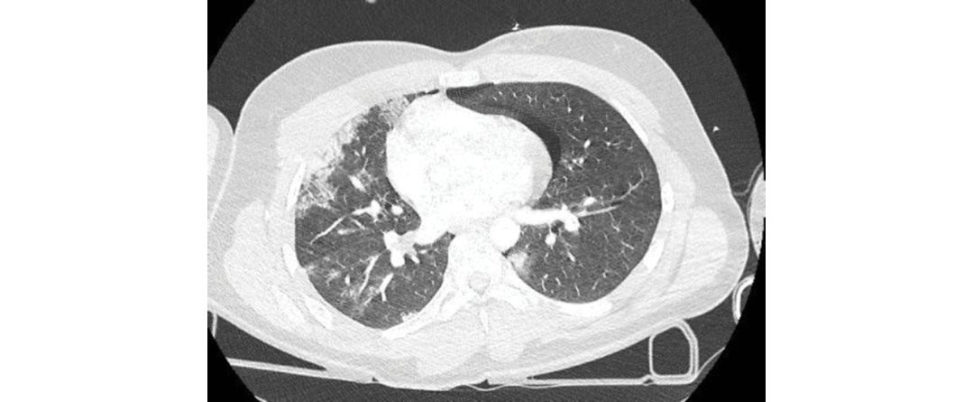
My priority would be the secondary survey on HDU. His lactate on blood gas and urine output are indicators of organ perfusion and whether he is physiologically safe to proceed. From the point of view of assessment of the distal femur fracture: I would check pulses in his leg, the condition of the skin, neurological status and for signs of impending compartment syndrome.
The ITU team says you can proceed, what is your plan?
My plan would be to fix his femur using a distal femoral locking plate. Hes also had a significant lung injury and there are risks from reaming in terms of fat embolus. I would approach this using a lateral approach, being careful around the blood supply to the physis. It might be possible to do a submuscular technique and slide the plate up: I’d have a low threshold for opening it to check reduction was adequate in terms of length and rotation.
Do you foresee any problems after this has been fixed? What do you warn him and his parents?
There is an incidence of valgus deformity associated with plating of femoral shaft fractures close to the physis and I would warn the parents we would monitor him for this during follow-up. As he’s almost at maturity I would not expect there to be a significant angular deformity or length discrepancy.
Figure 16.8a Axial CT, chest.
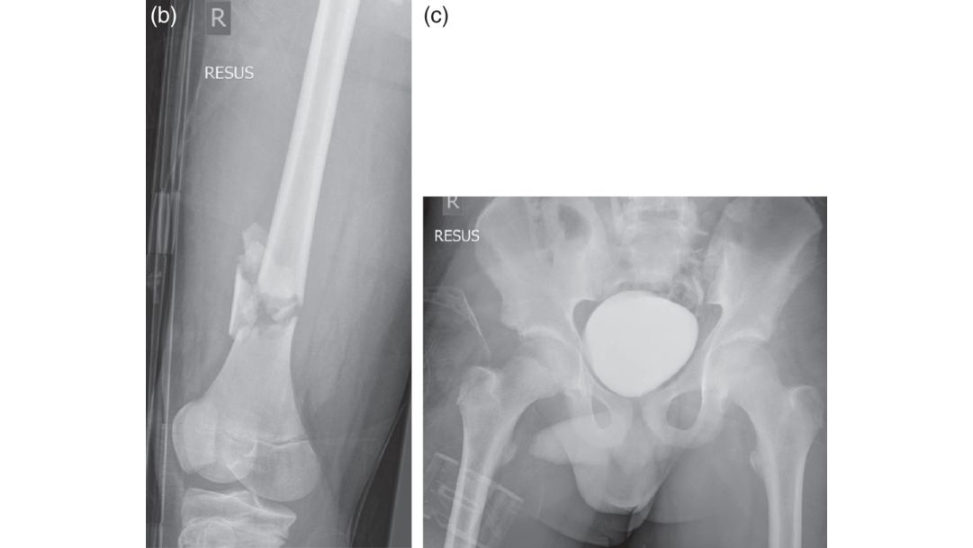
Figure 16.8b and 16.8c Anteroposterior (AP) radiographs, right femur and pelvis trauma series.
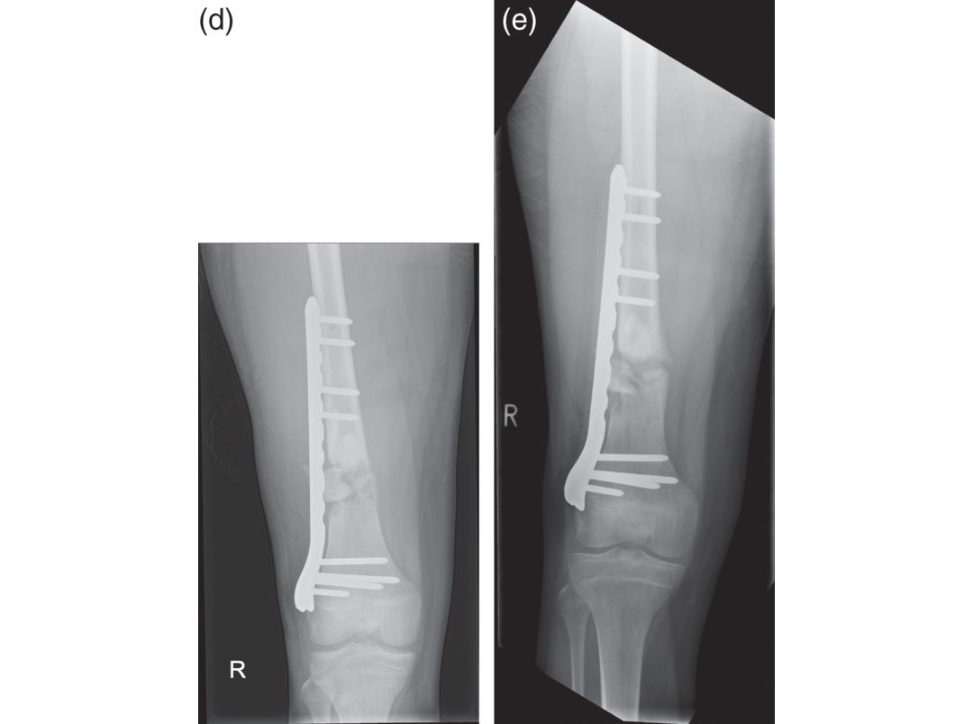
Figure 16.8d and 16.8e Anteroposterior (AP) postoperative radiographs, right femur.
Structured oral examination question 9#
This 13-year-old boy sustained this injury playing football (Figures 16.9a and 16.9b).
I can see an AP and lateral plain radiograph of an adolescent knee showing a comminuted tibial tubercle avulsion fracture. I would check for impending compartment syndrome as there is a risk of injury to a branch of the recurrent anterior tibial artery, which bleeds into the anterior compartment. Initial management is splintage, admission for elevation and planned definitive fixation.
Tell me about the Watson-Jones classification as modified by Ogden.
Type I is a fracture of the tibial tubercle apophysis (secondary ossification centre where the patella tendon inserts). Type II is at the junction of the apophysis and epiphysis. II Bis comminuted and the apophysis is displaced by the pull of the patella tendon. Type III is above the junction , where the fracture extends into the knee joint through the epiphysis.
What is your management plan?
This needs operative fixation to restore the integrity of the extensor mechanism. My preference is to use 4-mm partially threaded cannulated screws. After passing the screws I would screen the knee to check the fixation was stable when flexing to 90°. Pos topI would mobilize the patient touch weight-bearing with a hinged brace initially locked inextension, and then allow progressively more flexion over 6 weeks.
This boy is an elite sports person. Are there any future problems you need to warn his parents about?
He may require removal of the metalwork after the fracture has united if it is prominent or causes a bursitis and anterior knee pain. If there were any signs this was starting to develop, I would do an epiphysiodesis to complete the growth shutdown and he may then require a corrective osteotomy.
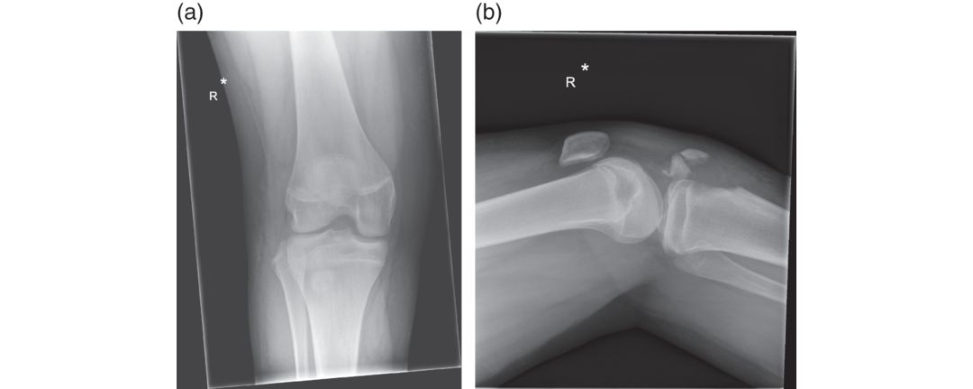
Figure 16.9a and 16.9b Anteroposterior (AP) and lateral radiographs, knee.
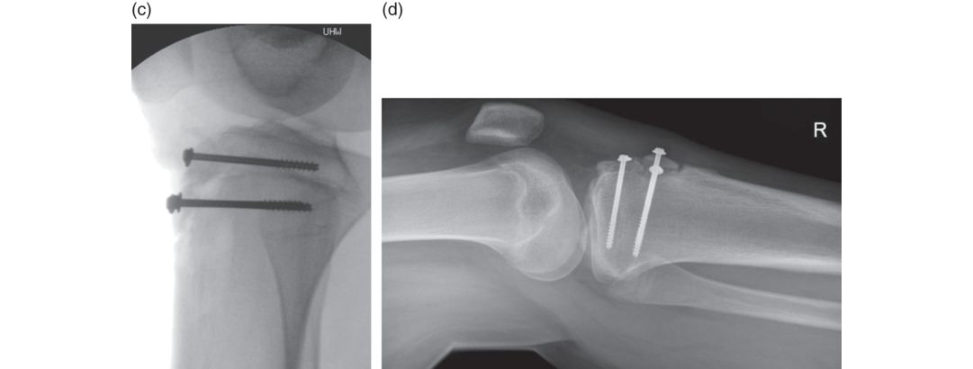
Figure 16.9c and 16.9d Intraoperative and postoperative lateral radiographs, right knee.
Structured oral examination question 10#
This 12-year-old girl attended A&E and was told she had a sprain after a trampoline injury (Figures 16.10a and 16.10b). She was allowed to weight bear with an ankle stirrup, although is struggling with pain when you see her in the fracture clinic.
I can see AP and lateral radiographs of a skeletally immature patient There’s evidence of an effusion within the joint and I can see a fracture line in the distal tibial physis exiting in to the plafond.
What do you mean by transitional?
Closure of the distal tibial epiphysis occurs in adolescents at 12–15 years of age, over an 18- month period. This is an injury when they are transitioning to skeletal maturity.
Is this a triplane fracture (Figures 16.10c–16.10e)? What is the management?
On the lateral X-ray typically, there is a Salter Harris II and a Salter Harris III on the AP, corresponding to the displaced anterolateral part of the physis. Any displacement > 2 mm at the articular surface is an indication for surgical intervention. In this case, I would see if I could obtain a closed reduction and percutaneously fix it with a partially threaded 4-mm cannulated screw from a lateral to medial direction. If I could not obtain reduction by closed means, I would openly reduce the articular surface with an incision over the fracture line to remove any potential soft -tissue interposition.
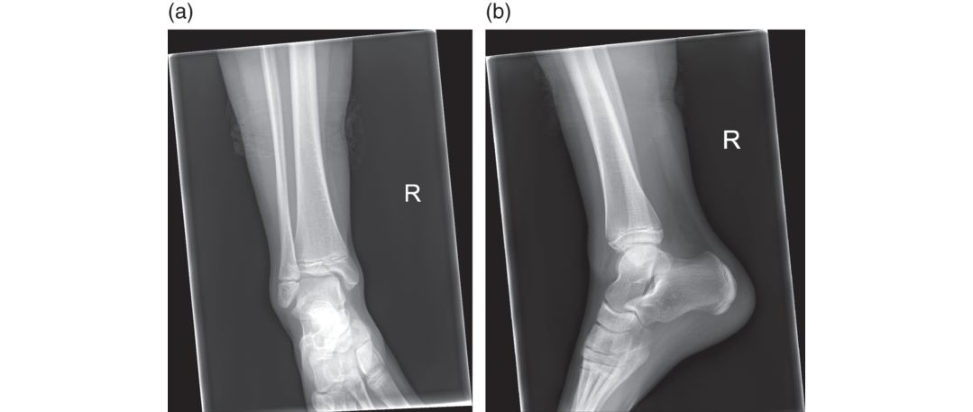
Figure 16.10a and 16.10b Anteroposterior (AP) and lateral radiographs, right ankle.
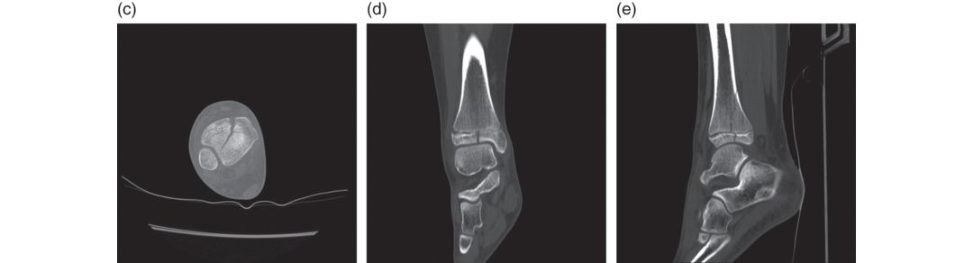
Figure 16.10c–16.10e Sagift al, coronal and axial CT slices respectively, right ankle.
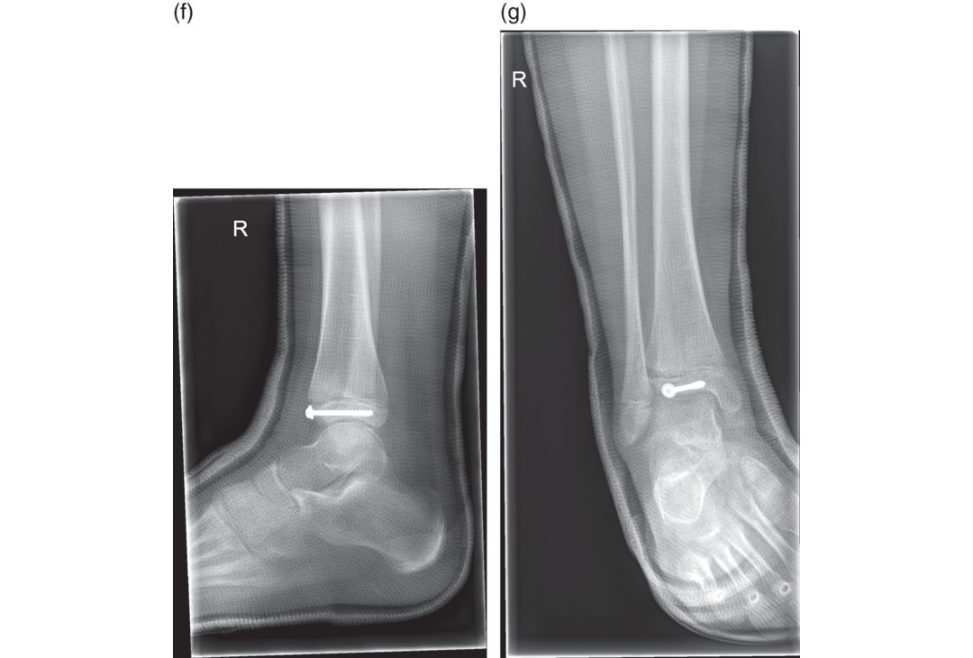
Figure 16.10f and 16.10g Postoperative lateral and mortise/ anteroposterior (AP) radiographs, right ankle incast.
References
1. Pahlavan S, Baldwin K, et al. Proximal humerus fractures in the pediatric population: a systematic review. J Child Orthop. 2011;5:187–194.
2. Mangat KS, Martin AG, Bache CE. The ‘pulseless pink’ hand after supracondylar fracture in children: the predictive value of nerve palsy. J Bone Joint Surg Br. 2009;91(11):1521–1525.
3. Scannell BP, Jackson JB, et al. The perfused, pulseless supracondylar humeral fracture: intermediate-term follow-up of vascular status and function . J Bone Joint Surg Am. 2013;95(21):1913–1919.
4. Langkamer VG, Ackroyd CE. Removal of forearm plates. A review of the complications. J Bone Joint Surg
Br. 1990;72(4):601–604.
5. Wall EJ, Jain V, et al. Complications of titanium and stainless steel elastic nail fixation of pediatric femoral fractures. J Bone Joint Surg Am. 2008;90(6):1305–1313.
Section 4