Chapter 8 Elbow
Terence Savaridas
Introduction#
Practise viva technique in a timed manner anda dap t your technique to illustrate your strengths.
The following are viva examples of common clinical scenarios. They provide useful supplementary information to the topic of the viva.
Elbow#
Make a list of conditions causing pain, locking, stiffness, flail and unstable elbow. Do not forget the nerves around the elbow while making your list.
Structured oral examination question 1#
Tennis elbow
36-year-old right-hand dominant manual worker, referred by his GP with a painful right elbow. His elbow radiographs are essentially normal. What would you like to do?
Well, I need to assess the patient elbow ... after I had asked the history of his pain.
Pain is on the lateral side, started gradually 3 months ago ... no history of injury, aggravated by using a hammer and was initially relieved by rest. Now it is constant. He has normal range of movements. The point of tenderness is just around the lateral epicondyle.
From history and examination I think he has got tennis elbow ...
What do you do to confirm the diagnosis?
I will test if the pain is reproduced by resisted wrist extension.
Well, he has more pain on resisted finger extension than wrist extension. Does it make you think more specifically?
...
Which tendons are involved in tennis elbow?
ECRB ...
Can EDC also be affected?
...
Well, tell me the pathophysiology of tennis elbow.
It’s termed as angiofibroblastic hyperplasia, which is ... hyperplasia of the angiofibroblasts ...
Do you know any other similar pathology around the elbow?
Golfer’s elbow, which is common flexor tendonitis.
Why do you say tendonitis? What is the difference between tendonitis and tendon osis?
...
Going back to the provocation t est, if he had tenderness over the lateral proximal forearm on resisted finger extension, what does it tell you?
Maybe the disease process is extensive into the common extensor muscle belly.
We’ll move onto the next scenario. This elucidates a simple scenario where the lack of a pause, to engage a structured taught process, leads to a jumbled poor answer that does not do justice to the candidate’s true level of knowledge. Is the candidate a classical example for tennis elbow misdiagnosis? Does the candidate deserve anything above a score of 4? Would you approach this subject differently? Think and analyze before looking into the performance of the next candidate.
36-year-old right-hand dominant manual worker, referred by his GP with a painful right elbow. His elbow radiographs are essentially normal. What would you like to do?
I want to know the history of his right elbow pain please.
It is on the lateral side, started gradually 3 months ago ... no history of injury, aggravated by using a hammer and was initially relieved by rest. Now it is constant.
I will proceed with his examination ... posture of elbow, range of movements especially looking for a lack of
He has normal range of movements. The point of tenderness is just around the lateral epicondyle.
I would like to know if he has tenderness anterior or posterior to the lateral
What does it tell you?
Anterior and distal to lateral epicondyle – ECRB tendinosis. Posterior and distal to lateral epicondyle – EDC tendinosis.
It is anterior and distal to lateral epicondyle. Tell me the provocation t est for ECRB tendinosis.
Pain on elbow extension/forearm pronation/fing ers flexion/wrist inextension against resistance.
What is the test for EDC?
EDC tendinosis should have pain on elbow extension/forearm pronation/wris t neutral/fingers extension/long finger extension against resistance.
Does the EDC provocation t est tell you anything else?
Yes. If EDC provocation t est produces pain over EDC origin, it suggests EDC tendinosis. Pain over radial tunnel – radial tunnel syndrome.
What do you understand by tennis elbow?
It is the tendinosis and not tendonitis of E CRB/EDC tendons.
Tell me the histological appearance of tendinosis.
Histologically, there are no acute inflammatory cells. There is granulation-lik e tissue consisting of immature fibroblasts and disorganized non-functional vascular elements called angiofibroblastic hyperplasia. If the tissue damage occurs at a rate which exceeds the tissues ability to heal, it causes tissue degeneration.
Do you know any other tendinosis around the elbow other than golfer’s elbow?
Yes, the posterior tennis elbow, which is triceps tendinosis.
Do you know any associated conditions?
Cuff pathology, Achilles tendinopathy and CTS.
Lastly, if you have a refractory tennis elbow what would concern you?
I would beworried about the possibility of other diagnoses such as radial tunnel syndrome, radio-capitellar arthritis posterolateral
Suggested reading#
EFORT Open Rev. 2016;1(11):391–397. htip://doi.or g/10.1302/2058-5241.1.000049
Key learning points
Tennis elbow is a degenerative tendinopathic process affecting mainly E CRB within the common extensor origin.
It is frequently seen in middle-aged individuals (35–50 years) who have excessive and repetiv
Be aware of typical presenting features (local tenderness, poor grip) and be able to describe tennis
Mills and the ‘chairlift t est (litiing the back of a chair with a thr ee-finger pinch (thumb, index and main fingers) and the elbow fully extended).
Differential diagnosis includes referred pain, PIN entrapment, lateral column elbow degenerate disease.
activity modification, physiotherapy, counterforce bracing/wrist splints, ultrasonography, NSAIDs and local cortisone injections.
Injection technique:
Quantity (2 –3 cm3).
Location anterolaterally below the extensor tendon, not intratendinous or subdermal.
Frequency: no more than three (6–12 weeks apart).
BEWARE: subcutaneous fat atrophy.
Rarely, in recalcitrant cases, surgery is offered.
Have an awareness of novel therapies: PRP injections, botulinum toxin, high-voltage electrical stimulation and extracorporeal shockwave therapy.
Structured oral examination question 2#
Osteochondritis dissec ans
Look at these radiographs of the right elbow of a 33-year-old patient and tell me the findings (Figure 8.1).
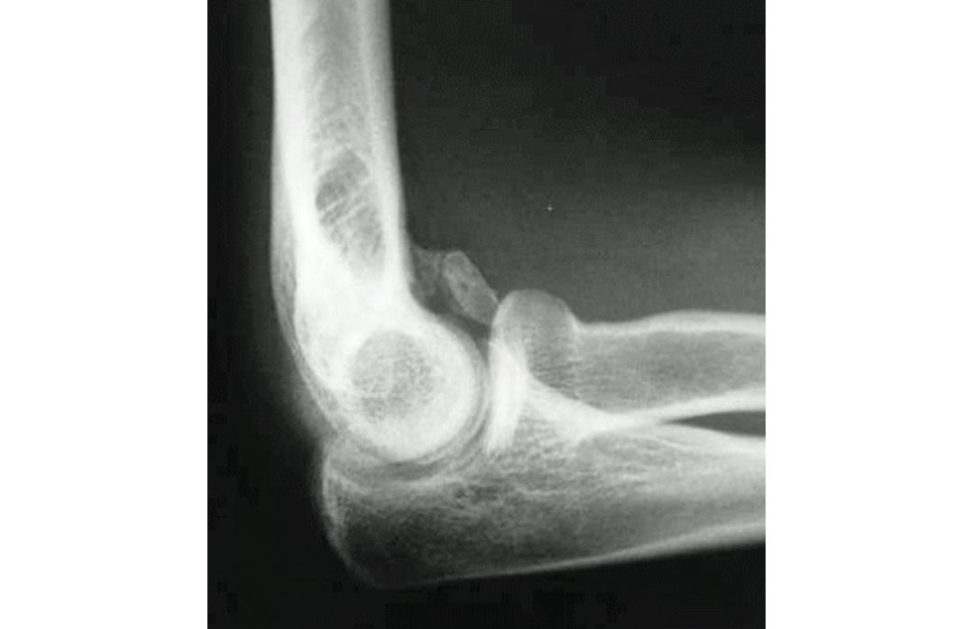
This plain radiograph of a right elbow shows one loose body in the anterior aspect of the joint.
What would you like to know if you are allowed to ask only one question?
I want to know his presenting symptoms.
He gets intermift ent painful locking symptoms. What is the diagnosis here?
Well he has a loose body in the elbow ...
Tell me the conditions which produce loose bodies in a joint.
Could be post-traumatic, secondary to osteoarthritis osteochondritis dissec ans (OC Dor synovial chondromatosis.
Now again ... What would you like to know if you are allowed one more question?
Did he have any injury in the past?
No, never ... What is your diagnosis here, keeping in mind that there is only one loose body in the elbow?
It could be either secondary to osteoarthritis or OC DandI could rule out a post-traumatic cause as he had no injury.
Can you look at the radiographs again and be more specific? [Showing the X-ray again to the candidate.]
I can see only one loose body. There is no calcification in the muscle or capsule.
What does it tell you?
It helps me to rule out myositis ossification and synovial sarcoma.
I want you to concentrate on the intra-articular pathology and try to narrow down your diagnosis between OC Dand osteoarthritis.
I would like to know the history of his symptoms and have more investigations to be more specific.
Well, he had unexplained painful elbow which lasted for about 18 months when he was 17 years of age ... What do you think is going on with this elbow?
It sounds like it may not be osteoarthritis ... it could be OCD.
If you had been consulting him a t the time of initial presentation 16 years ago, what would be your concern?
I would ... [Bell]
Figure 8.1 Anteroposterior (AP) radiograph of elbow.
Was this a good viva? Did he lack the knowledge of this subject of loose bodies?
Look at these radiographs of the right elbow of a 33-year-old patient and tell me the findings.
These plain radiographs of a right elbow show a well-maintained joint space with evidence of a solitary
What would you like to know if you are allowed to ask only one question?
Has this patient had problems with this elbow as a teenager? In particular , whether it impaired his performance in competiv e sport that involved repetiv
Yes, this patient had unexplained painful elbow that lasted for about 18 months when he was 17 years of age ... What do you think is going on with this elbow?
Well, I suspect he had osteochondritis dissec ans when he was 17, which explains the unexplained
It is anticipated that the prognosis for a full recovery is poor with presentation in older teenagers.
If you had consulted him at the time of initial presentation of OCD , what would you have done and why?
I would have advised him to return if he had functional restrictions duet o his elbow. It would have been useful to perform an MRI scan to assess lesion size and condition of articular cartilage. I appreciate that access to MR imaging would have been limited 17 years ago.
MR Iwas not widely available then. Are there any other investigations that may have been useful?
An elbow arthrogram with contrast would have been an option However, I suspect that, at theti mether e was also limited availability of arthroscopic elbow surgery. Therefore, the value of this invasive investigation would be limited except in a specialist centre.
This patient unfortunately had only one X-ray at the start of the presentation and as it did not show any obvious pathology, he was discharged from follow-up. What would you like to do now?
I would like to know his presenting symptoms. Has he had any treatment so farand what are his expectations?
He has had no treatment so farAnd can you tell me what would be his presenting symptom?
I would expect him to have intermift ent painful locking of the elbow with a limitation to full elbow extension.
Yes, that is his symptom. He wants to have something done to prevent these unexpected painful locking episodes.
I would perform an arthroscopic removal of the loose body.
Can you tell me another cause for one or two loose bodies in a joint?
In osteoarthritis the osteophytes can break and present similarly. But the radiograph would show evidence of osteoarthritis.
If you see multiple loose bodies, what is the diagnosis?
Candidate 2 has been able to control the viva by processing the information received and providing a thoughtiul answer.
Suggested reading#
Curr Rev Musculoskel Med. 2016;9(2):232–239. htip://doi.or g/10.1007/s12178-016-9342-y
Key learning points
OC Din the elbow is frequently an acquired condition affecting the capitellum secondary to repetiv e trauma.
It is frequently seen in adolescent athletes/gymnasts who participate in repetiv e overhead activity or axial loading of the elbow.
Patients present with pain on exertion. Patients that play through the pain tend to present with
Prognosis is poorer when presenting features first occur at a later age, following physeal closure.
Treatment is essentially non-oper at ive with activity modification in the v ast majority of individuals.
Structured oral examination question 3#
Rheumatoid arthritis elbow
What do you see in this radiograph of a 67-year-old lady’s right elbow (Figure 8.2a)?
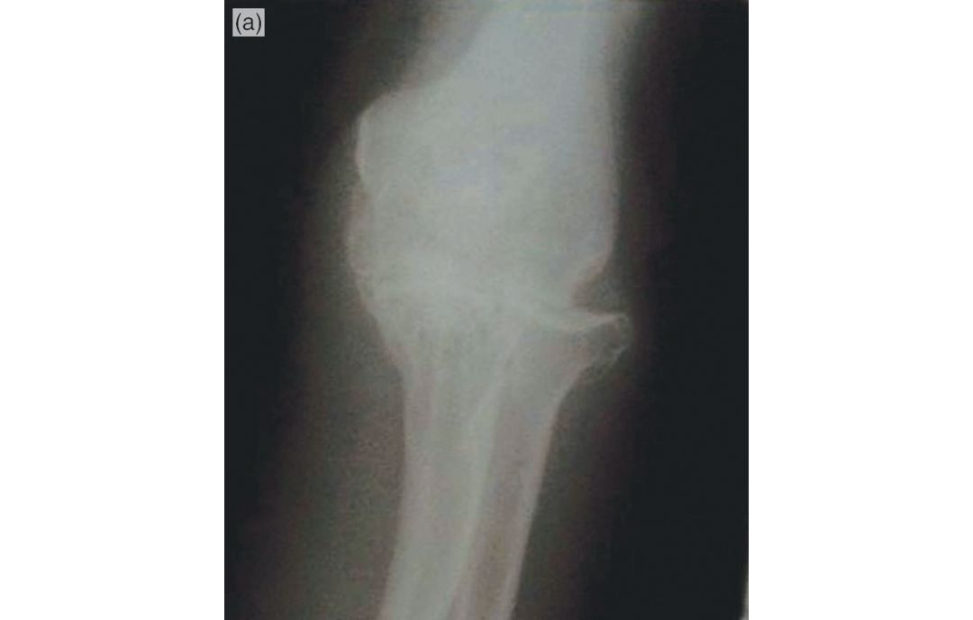
This radiograph shows extensive erosion of the articular cartilage which has involved both ulnohumeral and radiocapitellar joints. There is peri-articular os teopenia.
What could be the cause?
It is characteristic of inflammatory arthropathy and I suspect rheumatoid arthritis.
Indeed, this lady has had RA for the last 34 years. What would you like to do for her?
I want to know her presenting symptoms from this elbow. What are her expectations?
She has many joint problems and recently she is finding lack of strength in her right upper limb to do day-to-day activities. She has had no specific elbow treatments. She wants to do her normal household activities.
And more importantly check her hand function with regards to any tendon ruptures and posterior interosseous nerve function.
She has no valgus and varus stability but a good range of active and passive movements. Hand function is also good. Now how will you differentiate between PIN palsy and extensor tendon rupture?
The tenodesis test will assess tendon integrity. Well if there is no active extension of the fingers at the MCP joint and the tenodesis test shows no passive finger extension at the MCP joint on passive flexion of wrist, then the diagnosis is extensor tendon rupture.
What will be your management plan?
It is a multidisciplinary approach with re-consultation with rheumatologists and
She comes back after 3 months and says the brace has improved her life quality to some extent but finds it difficult as it gets wet in the kitchen and still has difficulties in the shower as she could not wear it in the shower.
This lady will likely benefit from a semi-constrained cemented total elbow replacement. I would explain to her that there is a recommended restriction of 5 lb inweight that she is able to lift in the arm post TER. In keeping
The patient will require a preoperative anaesthetic assessment that includes C-spine radiographs to assess the atlanto-axial joint.
Finally, what happens to juvenile rheumatoid joints?
In contrast to adult RA, juvenile RA produces stiff joints.
Figure 8.2a Anteroposterior (AP) radiograph of rheumatoid arthritis right elbow.
Who had control in this viva? Did this candidate get the questions he played for? Was his technique good? Now the next candidate approaches this table.
What do you see in this radiograph of a 67-year-old lady’s right elbow?
This radiograph shows extensive erosion of the articular cartilage which has involved both ulnohumeral and radiocapitellar joints.
What could be the cause?
It is characteristic of inflammatory arthropathy and I suspect rheumatoid arthritis. It is a flail elbow.
Indeed, this lady has had RA for the last 34 years. What features in the radiograph made you rule out osteoarthritis?
In osteoarthritis there will be joint space narrowing, subchondral sclerosis,
What is the bone quality here?
... The bone appears to be osteopenic ... could be disuse from pain or the disease process itself.
Now, what would you do for her?
I need to know the history of presenting complaints and I would examine the elbow.
She recently finds her right upper limb weak affecting her da y-to-day activities. In the examination the reis valgus/varus instability.
It is an unstable elbow from advanced RA. Therefore, I would do a total elbow replacement for her.
Is there anything you would consider prior to surgery?
Well I can try a splint if she is willing to try ...
She comes back after 3 months and says the brace has improved her life quality to some extent but finds it difficult as it gets wet in the kitchen and still has difficulties in the shower as she could not wear it in the shower.
Then I will proceed with the total elbow replacement.
Which nerve specifically would you like to assess in the RA elbow especially prior to total elbow replacement?
... Posterior interosseous nerve as it can be affected by the synovial swelling/dislocation of the radiocapitellar joint.
What would be the findings if she has PIN palsy?
There will be no active extension of the fingers at the level of MCP joints.
Do you know any other cause for the inability to extend MCP joints?
Yes, progressive rupture of extensor tendons called Vaughan–Jackson syndrome.
What if the patient presents with weakness of thumb DIP joint flexion?
This could be due to rupture of the flexor pollicis longus (FPL) tendon due to atirition
What name is associated with this?
Mannerfelt syndrome.
Is there any concern regarding this RA patient undergoing general anaesthesia?
These patients can have lung fibrosis ... apart from this, yes ... of course I will
Thankyou. Did he answer all the questions? Did he not possess the knowledge of the subject? This candidate answered each question adequately but did not provide any supplementary information to gain control of the viva in order to score a higher mark.
Suggested reading#
Ishikawa H. The latest treatment strategy for the rheumatoid hand deformity. J Orthopaed Sci.
2017;22(4):583–592. htip s://doi.org/10.1016/j.jos. (It is worth a look at figures 2 and
Jenkins PJ, Watis AC, Norwood T, et al. Total elbow replacement: outcome of 1146 arthroplasties from the
Scotish Arthroplasty Project. Acta Orthopaed. 2013;84(2):119–123.
htip://doi.or g/10.3109/17453674.2013.784658
Key learning points
RA is managed by a multidisciplinary team. RA is a systemic disorder. Understand its effect on the musculoskeletal system.
The aim of surgical intervention in RA ist o maintain patient function.
Understand the pathology and treatment options inV aughan–Jackson and Mannerfelt syndrome.
Develop a method to describe how to distinguish between a nerve palsy and a tendon rupture.
The semi-constraint, cemented TER (Coonrad–Morrey, Figures 8.2b and 8.2c) is a well-recognized
Semi-constrained linking mechanism behaves as a sloppy hinge, allowing some rotational and v arus–valgus play.
Allows early ROM (anterior flange provides AP and rotational stability).
Does not disassemble. The components are linked with a cobalt–chrome axis pin, which

Figure 8.2b and 8.2c Coonrad–Morrey linked semi-constrained explanted TER. Humeral component is porous-coated distally. Ulnar component has a plasma-spray metallic coating in its proximal third. Both components should be fixed with polymethylmethacrilate.
Structured oral examination question 4#
Post-traumatic O A elbow
Good morning. Here are the radiographs of a right-hand dominant 43-year-old man’s right elbow (Figure 8.3a). Tell me the findings.
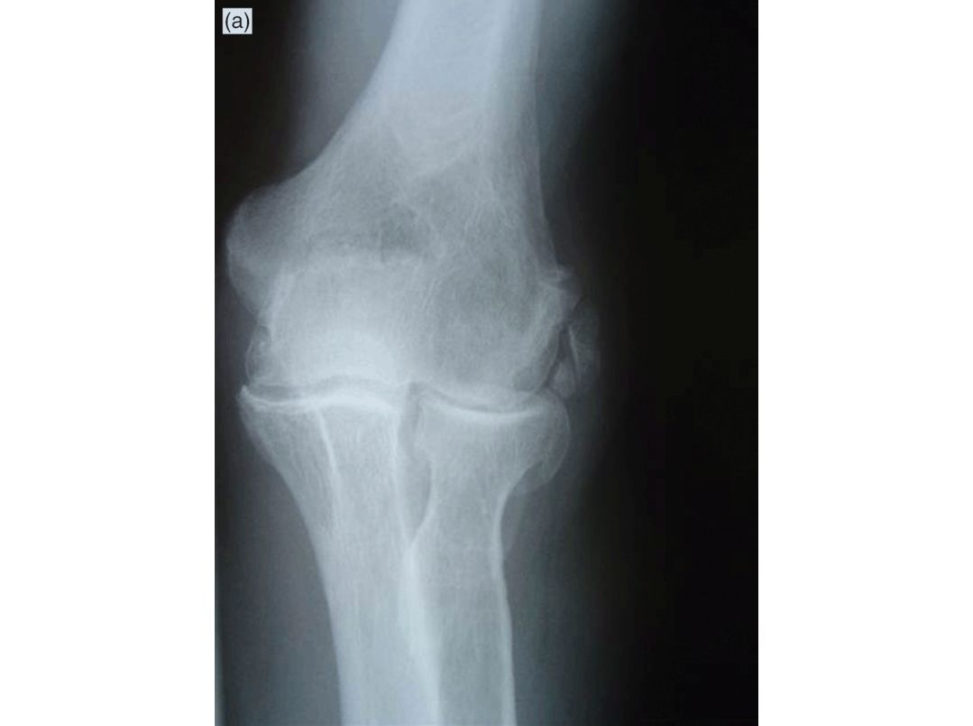
Good morning. These radiographs show narrowing of joint space on both ulnohumeral and radiocapitellar joints with subchondral sclerosis and
Well he had a dislocation of this elbow 8 years ago which was reduced in A&E and as he improved to full function in 8 weeks he was discharged from the fracture clinic. Now over the last 3 years he has had problems with this elbow. What would your advice be for this patient?
I want to know his present symptoms. How much does it affect his job? What are the treatments he has had so farAnd what is his expectation?
This elbow is affecting his job as he has got restricted movements – flexion extension from 50° to 110° and supination is only to 40°. He had a few intra-articular injections by his GP. He wants to have more movement in the elbow.
He has got post-traumatic osteoarthritis with stiffness. He is not presenting with pain as a main symptom. This patient is young and wishes to have an improved elbow ROM. This can be achieved either with an arthrolysis and debridement, either performed as an open column procedure or arthroscopically. The column procedure allows for joint arthrotomy, capsular release and excision of osteophytes through a limited lateral approach. In addition, he may require a TER in the future and I wish to avoid any surgical scars that may influence the position of a future incision for arthroplasty.
Can you show me the arthroscopic portals in this elbow picture (Figure 8.3b and 8.3c)?
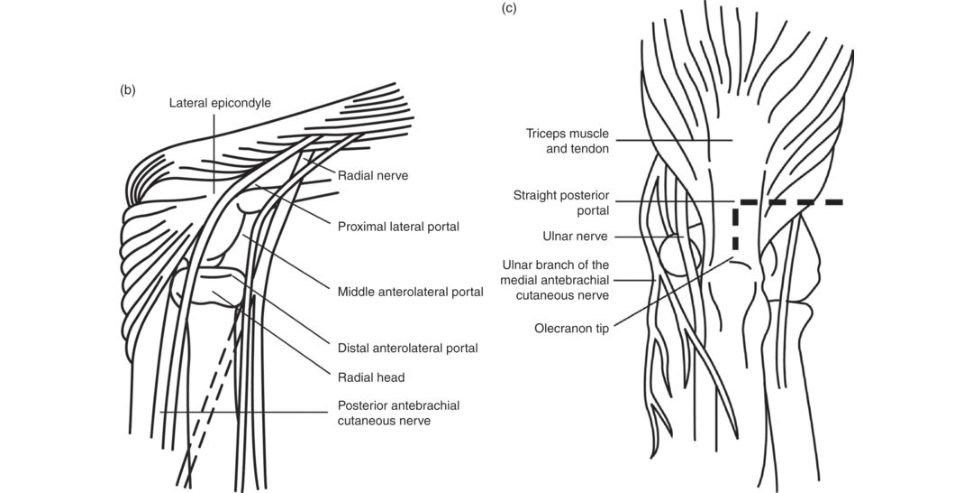
This is one of two frequently used as the initial en try portal to inflate the joint with saline. ANTEROLATERAL PORTAL : 1 cm distal and 1 cm anterior to the lateral epicondyle, between the radial head and the capitellum. This gives good access to the anterior aspect of the joint.
This is often created using an ‘inside out’ technique by cuting down onto the tip of the arthr oscope inserted using the anterolateral portal.
2 cm proximal to the medial epicondyle along the anterior surface of the humerus towards the radial head.
DIRECT POSTERIOR PORTAL : 1.5 cm proximal to the tip of the olecranon Access to olecranon fossae.
POSTEROLATERAL PORTAL : access to radiocapitellar joint.
Is the benefit of the debridement permanent?
No, it is not ... and varies between individuals.
The patient wants to know if there is any procedure that can provide long-lasting benefit.
The longer-lasting result can be achieved by a total elbow replacement ... But as this patient is only 43 and he is a manual worker and his dominant elbow is affected with
Figure 8.3a Anteroposterior (AP) radiograph of right elbow.
Figure 8.3b and 8.3c Arthroscopic portal sites of the elbow
How much will you score this candidate? Now a confident-looking candidate approaches the table.
Good morning. Here are the radiographs of a right-hand dominant 43-year-old man’s right elbow. Tell me the findings.
The radiographs show advanced osteoarthritis of his dominant elbow.
Correct. What would be your advice to this patient?
It depends on if he has pain, stiffness, difficulty with his job and also depends on his expectations.
Pain is not a main issue here. This elbow is affecting his job as he has got restricted movements – flexion extension from 50° to 110° and supination is only to 40°. He wants to have more movement in the elbow.
I will initially inject his elbow with steroids and send him for stretching physiotherapy.
The patient has had a few injections already and also physiotherapy from his GP and therefore he prefers to have a more definitive procedure.
Well if the injections have been tried without any success, I would advise a total elbow replacement.
Is there anything you could offer prior to TER?
[Suddenly losing confidence ...] Probably an attempt of manipulation under anaesthesia ...
Is MUA and passive stretching of a stiff elbow good advice?
... perhaps not ... as there is a small risk of myositis ossification.
In the last 30 years ... the number of implanted TER is in decline. Why?
...
Well 20–30 years ago the TER was commonly used for which group of patients?
Rheumatoid patients and it has declined because rheumatoid patients are better treated
What is the clinical finding in an advanced RA elbow?
Arthritis affects the entire joint, the ligament stability is also lost as RA is primarily
Have you seen a flail RA elbow recently?
No, I haven’t seen any which has progressed to radial head dislocation ... instead the appearance we see now is more like osteoarthritis.
Does this modification of disease pathology have anything to do with the declining number of implanted TER?
Yes, the TER failed earlier in this group.
This is because wea retreatings table disease-modified osteoarthritic RA elbows with the implant designed to treat flail elbows.
...
Would you like to offer anything else prior to TER for this young manual worker?
An arthroscopic washout?
Is there any ... [Bell] Did the confident start last long? Was the knowledge adequate to handle this scenario? Would you like to be this candidate on the day of the exam?
Suggested reading#
Basics of elbow arthroscopy partI: surface anatomy, portals, and structures at risk. Arthrosc Tech.
Chammas M. Post-traumatic osteoarthritis of the elbow. Orthopaed Traumatol Surg Res. 2014;100(1
Suppl):S15–24. htip://dx.doi.or g/10.1016/j.otsr.2013.11.004
Key learning points
Clarify patient expectations prior to recommending a treatment option and think about potential disease progression and likely future intervention.
Know the elbow arthroscopy portals. Accept that elbow arthroscopy is not a common procedure.
Structured oral examination question 5#
Posterolateral rotatory instability of the elbow
I have a problem with my left elbow Proceed.
Well, I want to know your age, hand dominance, your occupation and the nature of your problem please.
I am 47, right-hand dominant mechanic and incertain positions my elbow pops with pain.
Is the popping sensation on the inner side or outer side of your elbow?
The outer side ... yes, my thumb side.
Have you ever had any problem in your elbow as a child?
I had problems as a child in my right elbow, but now my right side is fine. My left side although I did not have any problem as a child, 3 years ago I had a simple dislocation.
What problem did you have on the right side?
My older sister pulled me by my right hand and my elbow became painful and the doctor had manipulated my elbow and told my parents not to let anyone pull me by my hand. And he said it was a pulled elbow ... where the radial head pops out.
I want to check if you have general joint laxity.
No, I am rather stiff. What do you think is wrong with my left elbow?
I think radial head dislocation ... probably secondary to annular ligament insufficiency
Whenever I push myself off the chair with my arm.
... I would like to perform an X-ray of your elbow to assess the radial head.
The X-ray is normal. Can you tell me about the ligaments around the elbow?
Sure. LCL has lateral ulnar collateral ligament (LUCL), annular ligament, radial collateral ligament and accessory collateral ligament.
Have you heard of posterolateral rotatory instability of the elbow?
... Did the candidate reach the diagnosis? Did he understand the clues given by the examiner? The next candidate arrives.
I have a problem with my left elbow Proceed.
Well, I want to know your age, hand dominance, your occupation and the nature of your problem please.
I am a 47, right-hand dominant mechanic and incertain positions my elbow pops with pain.
Have you ever injured your left elbow in the past? And in what position are you feeling the popping sensation in the elbow?
Well, I had a simple dislocation of my left elbow 3 years ago which was reduced in A&E. Now whenever I push myself off a chair using my arm I get this sensation.
I would like to assess your elbow.
What would you like to test?
I want to perform the pivot-shift t est to assess the lateral ulnar collateral ligament.
If the pivot-shift testis positive what is your diagnosis?
Posterolateral rotatory instability of the left elbow.
I had been told that I had ‘pulled elbow’ on the other side as a child. Could this be the same?
No, usually the pulled elbow setiles as the child grows and you had a definite injury to the left elbow.
What could you do for me to prevent these unpleasant episodes?
I need to perform an MRI scan to confirm injury to the LUC Land to see if the injury to the ligament is
My X-rays were normal. If the MRI scan shows injury to the LUCL, how will you manage this problem?
It may not be possible in your case as the injury was 3 years ago. My main inclination ist o reconstruct the LUCL using palmaris longus tendon or triceps fascia. Which candidate would you prefer to treat your elbow?
Suggested reading#
Posterolateral rotatory instability of the elbow: Part II. Arthrosc Tech. 2017;6(2):e407–e411.
htip://doi.or g/10.1016/j.eats.2016.10.012
Elbow dislocations: are view ranging from soft tissue injuries to complex elbow fracture dislocations.
htip://doi.or g/10.1155/2013/951397
Key learning points
Go back to the basics of a thorough history and examination.
The commonest cause of recurrent instability post elbow dislocation is posterolateral rotatory instability (PLRI).
Understand the stages of injury that occur in an elbow dislocation.
Be able to describe the pivot-shift t est. An easier testis the pushup from a chair.
As you would like to win the patient confidence while consulting in the clinics, it is vital to win the examiner’s confidence in each and every scenario, showing adequate knowledge expressed with correct technique.
Section 3