Chapter 3 Hip
Introduction#
There has been a change in emphasis in the oral questions in the last 2 years to higher-order thinking and judgement. If you haven’t managed periprosthetic joint infection (PJI) then it’s going to be doubly difficult to answer the real-life practical questions that are related to managing apa tien t with this condition.
We have aimed the candidates’ answers for a 7–8 score, so they are significantly more detailed than what would be required for a bare pass.
Structured oral examination question 1#
These are the radiographs of a 65-year-old gentleman who had a primary left THA 14 years ago (Figure 3.1a and b). Over the last 2 weeks, he has had increasing pain in the left hip and he has contacted his GP who has referred him back to you on an urgent basis Postoperatively, he was progressing well, and he has no history of any trauma. He is now unable to weight bear fully on the left leg and has night pain.
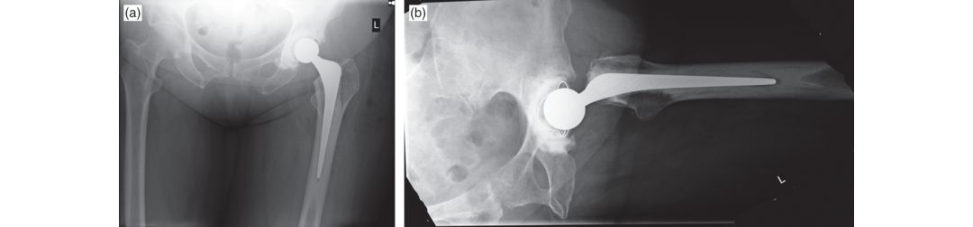
This is an AP pelvic radiograph showing a left cemented Exeter THA. My worry here is that this gentleman may have a periprosthetic joint infection.
how are you going to proceed with this patient?
I would want to take the patient to theatre and perform an aspiration of the hip to rule out infection.
You are sure? Are you not jumping in abit fastIs there anything else you might want to find out beforehand?
I would want to take a full history from the pa tientA number of patients who develop infection have early wound problems such as prolonged redness, indurations welling or discharge. Pain from an infected prosthesis is typically non-mechanical and unrelated to physical activity and not relieved by restI would also like to explore more fully host risk factors for infection such as diabetes, rheumatoid arthritis depression, obesity, hypothyroidism, immunosuppression (steroids, DMARDs), smoking and poor dention. Having taken a full history, I would perform a comprehensive clinical examination, looking a t the scar for any evidence of infection such as erythema, warmth, a sinus, etc. I would then request an FBC, CR Pand ESR to look for evidence of raised inflammatory markers.
How helpful are these?
(level 2) published a systematic review in the JBJS American edition in 2010 on the use of inflammatory markers for diagnosis of prosthetic joint infection. 1 They concluded that IL-6 is a much more sensitive test for infection.
What about diabetes as a risk factor for PJI?
The association between diabetes and PJI may be mediated by impaired leukocyte function and microvascular complications which may impair wound healing. Hyperglycaemia has also been shown to increase biofilm formation.
The paper reported that IL-6 was more accurate than CR Por ESR rather than sensitive The wound was oozy postoperatively but setiled down. A large part of picking up periprosthetic infection is obtaining a good history and examination along with a high index of clinical suspicion.2 How useful is a hip aspiration in diagnosing infection?
Figure 3.1a and 3.1b Anteroposterior (AP) pelvis and lateral radiographs demonstrating a left Ex eter THA.
(level 1) demonstrated a sensitivity of 0.86, a specificity of 0.94, a positive predictive value of 0.67 and a negative predictive value of 0.98 with initial imag e-guided aspiration in 180 patients undergoing revision hip arthroplasties. 3 They reported that aspiration alone is not sufficient for the diagnosis because of the risk of false positive and false negative results. A normal CR Pand ESR does not always exclude a PJI, however.
How would you perform a hip aspiration?
I would perform this in theatre under II control. If both are positive with the same organism this would be suggestive of infection.
What about if one aspirate only is positive?
If only one aspirate is positive then it is a tricky situation. It is a soft positive result and I think it would be reasonable to repeat hip aspiration 2 weeks later.
Joint aspiration did not grow any organisms after 48 h of culture. Is there anything else you may wish to consider in terms of establishing a diagnosis of a periprosthetic joint infection?
48 h for bacterial culture may not belong enough to identify certain bacteria.
Isn’t that normal for most labs to do?
My own local hospital policy is to perform extended culture for 5 days on any suspected PJI, but I am not sure if this has been universally agreed on. Synovial fluid culture has a sensitivity of 52% and specificity of 95%. Sensitivity a t 52% is poor. For hips, a WCC > 4200/μl and/or a granulocyte percentage > 80% has a sensitivity of 85% and a specificity of 90%. The Gram stain itself has a very low sensitivity (< 25%). There are modern biomarkers such as α-defensin (Synovasure, Zimmer Biomet), neutrophil elastase 2 (ELA2), bactericidal/permeability increasing protein, neutrophil gelatinase-associa ted lipocalin (NG ALand lactoferrin which have recently shown promise in diagnosing PJI, but there are still no reliable data to prove their sensitivity and specificity to date.4 One potential advantage of such biomarkers is the fact that they are not reliant on the bacteria and, therefore, pre-administered antibiotics should not affect their sensitivity .
Neutrophil granulocytes are indicators of bacterial infections (in acute infections).
What is α-defensin?
α-defensin is an antimicrobial peptide secreted by neutrophils to fight infection.
Are there any other tests you might want to perform that could diagnose infection before going ahead with surgery?
The use of nuclear imaging (technetium-99 triple-phase bone sc an, The AAOS clinical practice guidelines summary from 2010 reported a weak recommendation for their use.5,6
How do you classify periprosthetic hip infection?
Technetium-99 bone sc ans are sensitive but not specific. Some investigators have found that a negative scan rules out infection, others report that a scan can occasionally be negative with infection if the reis inadequate blood supply to the bone. A technetium-99m bone sc an identifies areas of increased bone activity through preferential up take of the diphosphonate by metabolically active bone. In the uncomplicated THA, uptake around the lesser trochanter and shaft is usually insignificant by 6 months, but in 10% of cases, uptake may persist at the greater trochanter, prosthesis tip and acetabulum for more than 2 years. The use of leukocyte scans is generally preferred, having a higher sensitivity (88 –92%) and specificity (73–100%), but their usefulness for the diagnosis of infection continues to be debated. Tsukayama et al. proposed a four-stage system consisting of early postoperative, late chronic, and acute hematogenous infections, and positive intraoperative cultures of specimens obtained during revision of a presumed aseptically loose THA.7,8 Early postoperative infection presents less than 1 month after surgery with a febrile patient and a red swollen discharging wound. Acute haematogenous infection can occur several years after surgery with a history of bacteraemia (UTI or other source of infection) and severe hip pain in a previously well-functioning hip.
McPherson et al. have also developed a staging system for periprosthetic hip infections that included three categories: infection type (acute versus chronic), the overall medical and immune health status of the patient and the local extremity (wound) grade.9
How do you diagnose PJI?
Major criteria are (1) a sinus tract communicating with the prosthesis and (2) two positive periprosthetic cultures with phenotypically identical organisms. The six minor criteria are (1) elevated ES Rand CRP, (2) elevated synovial leukocyte count, (3) elevated synovial neutrophil percentage (PMN%), (4) presence of purulence in the affected joint, (5) single positive culture, (6) positive histological analysis of periprosthetic tissue.
How will you manage this patient assuming that your diagnosis of an acute PJI is now made?
As the diagnosis of a PJI has been made within 2 weeks and assuming that there are positive microbiological results with a known organism and sensitivities to antimicrobial therapy, AD AIR should only be undertaken if the PJI is acute and ideally within 3 weeks of the PJI starting, The optimum management of a PJI involves a multidisciplinary team approach with MSK radiologists, The success rate of DAIR procedures is around 90–95%.10 The Oxford group have recently published a case control study comparing DAIR versus a two-stage revision showed a 98% 5-year survivorship rate
This patient had a delay in diagnosing the PJI and was only seen 2 months after the onset of their clinical presentation. How would you manage the patient now?
If there was a microbiological result with a known organism and sensitivities, then a single-s tage revision could be undertaken, especially if the patient had multiple co morbidities and the surgical stress of having a two-stage procedure might compromise the patient.
What are the prerequisites for a one-stage procedure?
It is also indicated in healthy individuals devoid of re-infection risk who have adequate bone and soft tissue for reconstruction and a lo w-virulence pathogen.
What are the reported success rates for a single-stage revision?
Raut et al. from Wrighting ton reported a success rate of 86% in 57 cases at average follow-up of 7 years despite many discharging sinuses.13,14 Hanssen and Rand summarized the results of single-stage exchange and found a cumulative success rate of 83% when antibiotic- loaded cement was used, but only 60% when it was not.15 A recent RCT has been started to compare a single- versus two-stage revision.16 In 11 studies with 1225 patients with a hip PJI receiving exclusively one-stage revision, the rate of re-infection a t 2 years was 8.6% (95% CI 4.5–13.9).
What are the advantages to performing a two-stage procedure?
It is particularly important to perform a two-stage revision with more severe infections or virulent organisms, as the success rate of a single-stage procedure is much less in these situations.
That’s not what I asked.
It is more versatile for reconstruction allowing the use of either cemented or cementless components and bone allograft in patients with severe bone loss.
What are the disadvantages of a two-stage procedure?
It can be difficult to nurse patients between stages and the second-stage surgery can be difficult due to soft -tissue scarring,
Have a look at this radiograph below (see Figure 3.1c). What is going on with the right hip?
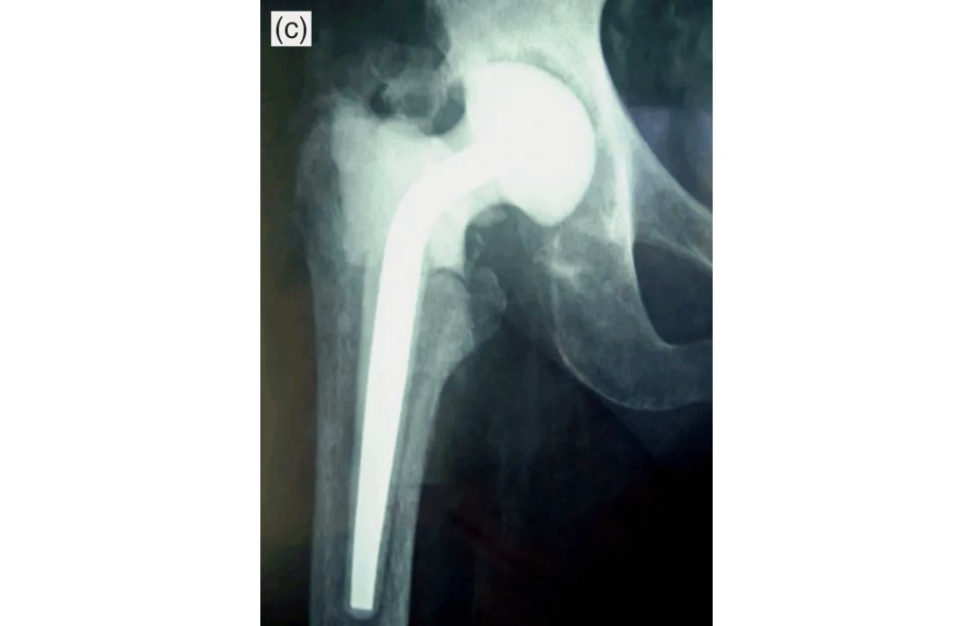
This is a cement spacer in apa tien t who has had a first-stage revision for infection and an articulating cement spacer such as a PROSTALAC spacer has been used. the THA spacer could be left inmore permanently if the patient medical condition precludes further surgery or the patient decided against second-stage revision.
you perform the first-stage revision, how long will you keep the patient on antibiotics?
A number of surgeons re-implant at 3 months, treating the patient with 6 weeks antibiotics and then a further 6 weeks without antibiotics regularly monitoring the CRP/ESR for any signs of elevation and checking clinical progress for any signs of reoccurrence of infection such as sinus discharge or increasing hip pain Antimicrobial therapy will be guided by the microbiology advice given and this is why the management of PJI is best undertaken as part of an MDT review.
Five of my last six THAs have become infected. What should I do?
Stop operating and investigate. I would undertake a root-cause analysis to identify the source or cause of these infections.
Go on.
A sterilization indicator should be present, and the packaging must be dry. There may be a breakdown in the precautions that must betaken by the scrub practioner during the procedure, such as the sterile field not being constantly observed and too much movement around the sterile field, including the opening and closing of doors and a wide space not being observed between scrubbed staff. Taylor et al. showed that sets opened outside the confines of the laminar hood have significantly higher colony-forming unit (CFU) counts during and after surgery.17 Very few centres follow Sir John
Charnley’s technique of opening the instrument sets under the canopy at each stage of the operation.
Madhavan’s paper from Bristol in the Annals of the Royal College of Surgeons England specifically looked at breakdown in theatre discipline during total joint replacement.18 They noted that slackness had crept into the theatre protocol, such as corridor from changing room to theatre and theatre personnel at ire.
Screening has shown that you, the surgeon, were found to be a Staphylococcus aureus nasal carrier. You have been treated with decolonization and are now clear. Would you mention this to your patients when you are listing them for joint arthroplasty?
Yes.
Are you sure?
Yes, patients should be informed that I was a nasal carrier at the time of listing for surgery.
Are you absolutely sure?
Yes, patients need to be told to make sure they are happy. surgery that they were previous nasal carriers but have been successfully treated
Do any papers that have looked at theatre sterility?
The classic paper on theatre sterility was published by Lidwell et al. in 1982.19 This was an MRC randomized study which showed a decrease in infection rates following joint replacements carried out in ultraclean theatres.
That’s fine. Let’s move on.
Reading list
Focus on BJJ 2012:
One stage exchange arthroplasty: the devil is in the detail
D.Kendoff; T. Gehrke
ENDO-Klinik Hamburg
Table 3.1 MSIS Workgroup standard definition for PJI.
Musculoskeletal Infection Society (MSIS) diagnostic criteria
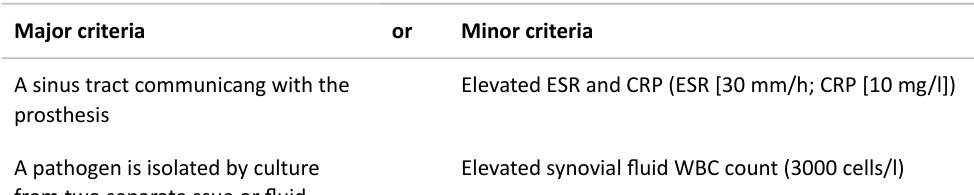
A pathogen is isolated by culture from two separate tissue or fluid samples obtained from the affected prosthetic joint
Elevated synovial fluid neutrophil percentage (65%)
Isolation of a microorganism in one periprosthetic tissue or fluid culture
5 neutrophils per high-powered field in 5 high-power fields observed from histologic analysis of periprosthetic tissue a t ×400 magnification
Figure 3.1c Anteroposterior (AP) radiograph of first-stage PROSTALAC spacer.
Structured oral examination question 2#
This is an AP radiograph of a 52-year-old female who presents to your clinic with non-specific right hip pain. She had a right metal-on-metal hip resurfacing procedure performed 3 years ago (Figure 3.2a).
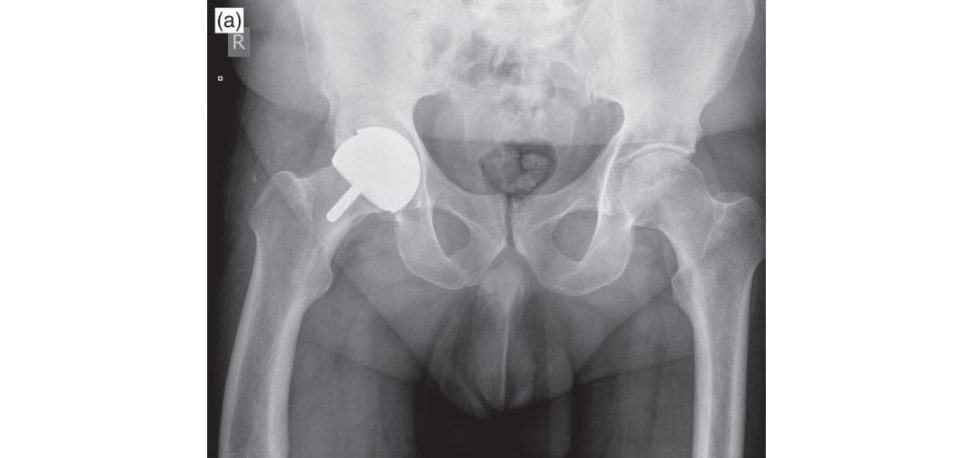
The AP radiograph demonstrates a higher abduction angle lateral opening) than normal. The current recommendations are for an acetabular abduction angle of 40°. The head size appears small; the current recommendations are that unless a minimum 46-mm head size can be used the procedure should not be performed because of the risks of ALVAL and pseudotumours.
What do you mean by a divot sign?20
A divot sign is a depression in the neck contour just below the junction with the femoral component often associated with a reactive exostosis.
What is a pseudotumour and what is the difference between ALVAL and pseudotumour?
ALVAL (aseptic lymphocy te-dominated vasculitis-associa ted lesion) is a histological diagnosis caused by metal particulate debris. This is diagnosed on an MRI scan. The umbrella term ‘adverse reactions to metal debris’ (ARM Dis now preferred to cover a wide spectrum of destructive involvement including metallosis, pseudotumours and ALVAL. In June 2008, the NJR first introduced the term ARMD for surgeons to select as an indication for revision surgery, given ARM Dis considered the most inclusive term for these abnormal reactions. Despite this, Campbell et al. reported that in 32 THA revised due to pseudotumour several patients demonstrated minimum wear features, suggesting a hypersensitivity c ause.21 Therefore, the origin of pseudotumours is probably multifactorial caused either by excessive wear, metal hypersensitivity , a combination of the two, or an as yet unknown cause.
What are the risk factors for pseudotumours?
Significant risk factors for the development of pseudotumour include female sex, ageless than 40 years, small component size, hip dysplasia and specific implant designs (ASR).
How are you going to investigate this patient?
A careful history and examination of the patient is required. Intrinsic causes include aseptic loosening , avascular necrosis, infection.
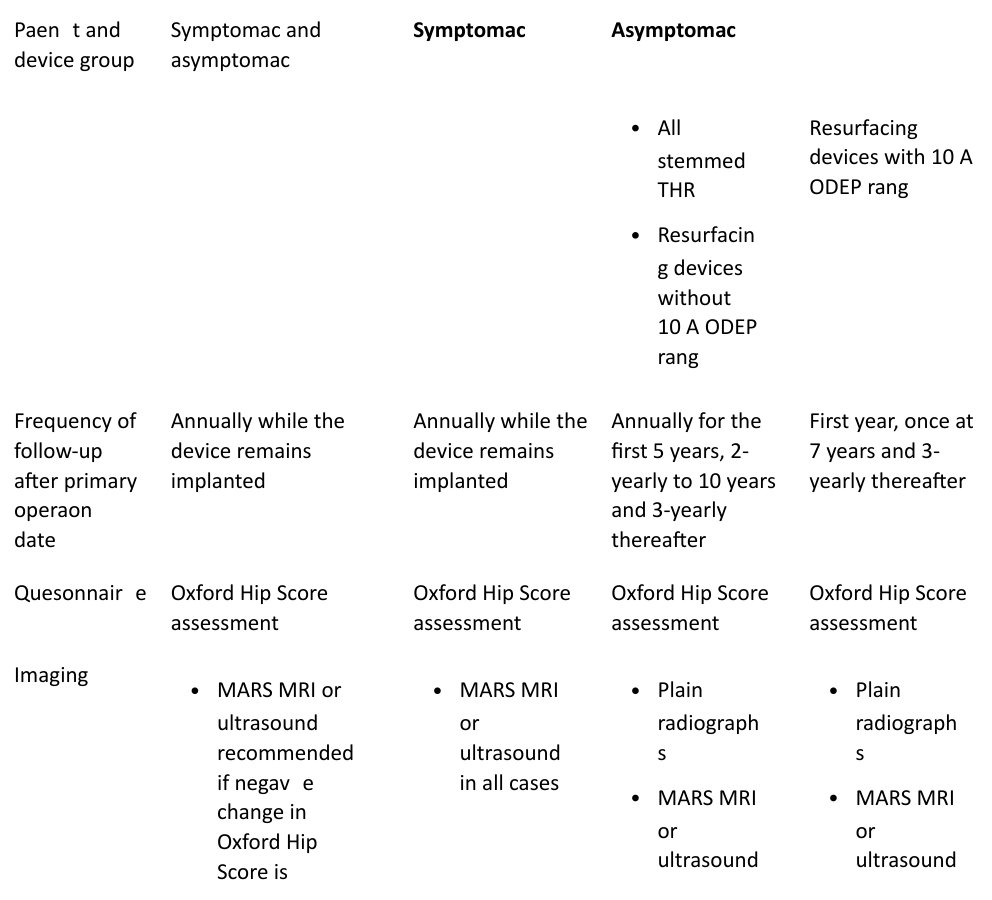
What are the latest Medicines and Healthcare Products Regulatory Agency (MHRA) recommendations (2017) (Prompt)? (Table 3.2.)
which is an ODEP 10 A device, inpatients who are asymptomatic, should bef ollowed-up in the first year, at 7 years and then every 3 years after that. Stemmed large MoM devices are higher risk than resurfacing hips and therefore the follow-up guidance is different and these patients require closer review.
Anything else?
I am not sure.
ALVAL may occur in both asymptomatic and symptomatic patients and early detection should give a better revision outcome if this is necessary. Essentially all MoM/r esurfacing hips require some clinical follow-up for life and should not be discharged even if well functioning.
Additional clinic slots are required for follow-up of MoM hippa tien ts and this can be a significant burden on resources. Interferes with new/follow-up ratios.
This is the MRI scan obtained. What does it show? (Figure 3.2b and 3.2c.)
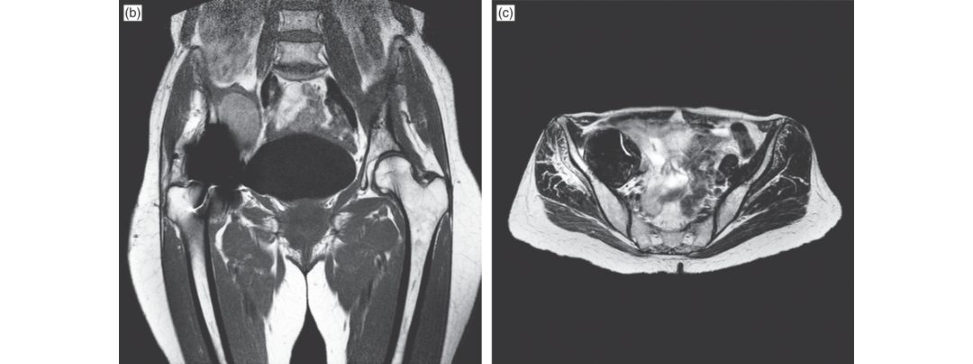
The MRI is a T2-weighted image coronal view, which demonstrates an intra-pelvic mass.
This was a pseudotumour. In fact, the mass could be felt clinically when examining the abdomen. What are you going to do?
This patient requires urgent revision surgery to the hip.
She is very scared of surgery and would prefer to avoid it.
I would stress the importance of early revision surgery as the longer the MoM resurfacing implant is left in place the more extensive the soft -tissue destruction will likely be.
What are the principles of surgery for pseudotumours?
The pseudotumour needs to be managed with aggressive debridement of all involved so tissue. It is important to do a thorough debridement of the abnormal tissue similar to the treatment of infection. The surgery should be performed by an experienced hip surgeon. We are already revising for a rare complication and we don’t want anything to go wrong again. It would be sensible to get a second opinion from an experienced hip surgeon as per British Hip Society guidelines to confirmand support the appropriateness of my management plan. In my region, all revision arthroplasty cases are discussed as part of a revision clinical network involving several hospitals within a geographical region. I would certainly ensure that this case is discussed with other colleagues within the revision network meeting.
What is the evidence that highly cross-linked PE improves clinical outcomes?
There was a double-blinded study from New Zealand (level 1 evidence) recently published in the American JBJS edition comparing HXLPE to conventional PE.
Why did surgeons bother with MoM hip resurfacing procedures? The old Charnley cemented hip replacement with trochanteric osteotomy worked equally as well with excellent long-term results reported from the surgeons at Wrighting ton.
reduced risk of dislocation improved femoral bone stock mass because the neck and most of the head are retained and ease of conversion to a THA if the implant should fail.
What are the contraindications for resurfacing?
extensive ON and severe obesity (BMI > 35 kg/m2). Other contraindications include a history of chronic renal disease, those with anatomical abnormalities in the acetabulum or proximal femur and certainly caution in w omen of childbearing age.
Is resurfacing contraindicated in women of childbearing age?
No, although most surgeons would now avoid a resurfacing procedure in a female regardless of whether they were of childbearing age.
Is there a role for resurfacing at all?
Data from the latest NJR annual report showed that less than 1% of all hip replacements were resurfacings.
What do you mean by trashing your hip?
Candidates should mention that: Nowadays very few resurfacing hips are performed (< 1% NJR data 14th report 2017). Surgery should ideally be performed by a specialized hip resurfacing surgeon.23 Cases should ideally be discussed with hip colleagues and a consensus view reached as to whether to proceed with resurfacing. Candidates should be able to discuss: The poorly performing implants (AS Rand subgroups of patient sat risk for ARMD (female sex, age < 40 years, small component size, malpositioning of the acetabular component, hip dysplasia, known nickel allergy).
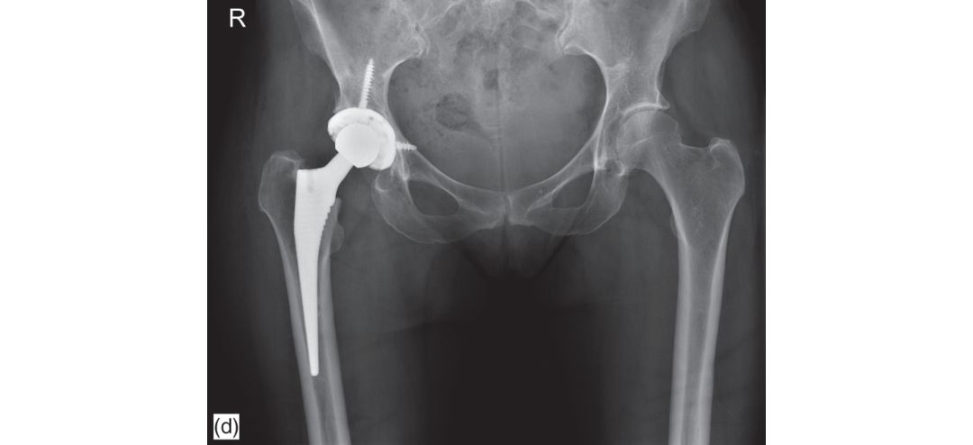
These are her postoperative radiographs (Figure 3.2d). We kept her non-weight bearing for 6 weeks as there was quite an extensive anterior wall defect in the acetabulum, but she has done very well. The hip pain has setiled, and the abdominal mass resolved. We were very lucky as the extensive soft -tissue destruction that sometimes can beseen with this condition was absent24.
What are the outcomes of hip resurfacing compared to conventional THA ?
The reis a higher revision rate in hip resurfacing compared to conventional THA .25
What factors are associated with higher revision rates for hip resurfacing procedures?
Causes of revision primary hip resurfacing procedure include fracture (39%), loosening/lysis 29%, infection 9%, ARMD (6%), pain (5%), dislocation (3%), other (8%). Australian Joint Registry 1999–2008. Resurfacing is rarely performed these days (< 1%), so the safest option is not to mention this as a possible arthroplasty option unless specifically brought into the discussion by the examiners.
Figure 3.2a Anteroposterior (AP) radiograph right MoM hip resurfacing implant.
Table 3.2 MHRA management recommendations for patients with metal-on-metal hip replacements.
Device implanted Hip resurfacing (no stem): Hip resurfacing (no stem):
- Female - Male (femoral head diameter > 48 mm) ·
Stemmed total hip replacement (THR):
· - Male (femoral head diameter ≤ 48 mm)
·
- Femoral head diameter < 36 mm ·
- All DePuy ASR hip resurfacing devices
·
Stemmed total hip replacement (THR):
- Femoral head diameter > 3 6 mm
·

Whole blood should be used to test for cobalt and chromium metal levels.
Figure 3.2b and c T1 coronal and transverse MR Iof right MoM hip resurfacing implant demonstrating ALVAL mass.
Figure 3.2d Anteroposterior (AP) radiograph of revised hip demonstrating uncemented THA with screw fixation acetabulum.
Structured oral examination question 3#
This is an AP radiograph of a 78-year-old man presenting with increasing right hip pain. He had a THA performed 17 years ago (Figure 3.3a).
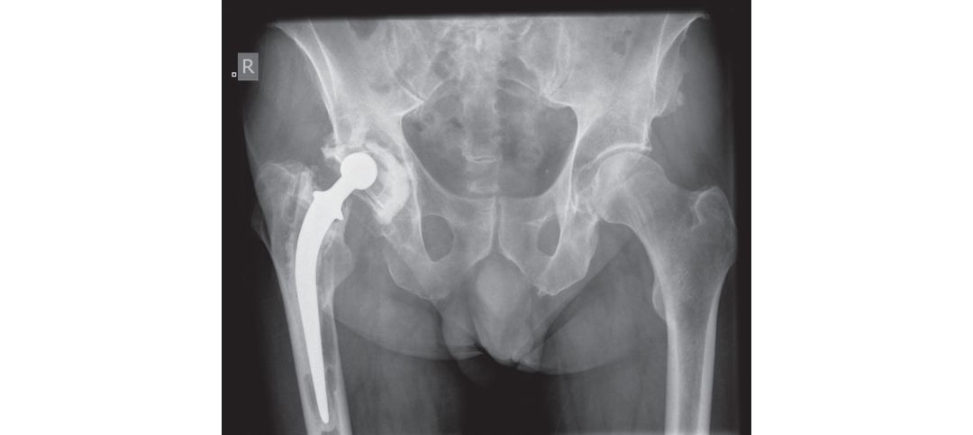
The AP radiograph demonstrates severe osteolysis of both femoral and acetabular components. Score 6 candidates should ideally be able to recognize a Charnley and Exeter stem. Score 7 candidates should recognize a Stanmore prosthesis (banana-shaped). Score 8 candidates should be able to weave in somewhere in the discussion that when revising a Stanmore prosthesis, it is particularly important due to its banana shape to clear the shoulder of the prosthesis removing any cement or bone overhanging the proximal aspect of the greater trochanter.
What are the different generations of cementing techniques?
First-generation cementing techniques involved hand-mixing of cement and finger packing of bone cementin the doughy phase into an unplugged, unwashed femoral canal. This reduced the incidence of gross voids and filling defects in the mantle.
Are you sure pulsed lavage was used?
The bone is thoroughly cleaned before cement insertion but not pulsed lavage.
What else?
This is important as uneven and excessively thin cement mantles are associated with early failure and revision.
Distal centralisers are often included as a third generation technique. Some books list only 3 generations of cementing techniques omiting the fourth.
How is cementing technique graded?
Radiolucency involving 50–99% of the cement–bone interface or a defective or incomplete cement mantle was graded ‘C’. Radiolucency at the cement–bone interface of 100% in any projection, or a failure to fill the canal with cement such that the tip of the s tem was not covered, was classified ‘D’.
What are you going to do?
I would want to take a full history from the patient. I would also want to exclude the possibility of infection (septic loosening) and would ask about problems with the hip postoperatively such as wound infection requiring washout or a prolonged course of antibiotics. A history of fever, chills or a sinus tract suggests infection. Night pain, rest pain or constant pain would also suggest infection. The pain is always improved with rest and rarely constant. With aseptic loosening of a THA examination may reveal shortening of the affected limb, an antalgic gait and a Trendelenberg positive testis usually present. Pulses and skin temperature should be checked to rule out a vascular cause for pain.
Assume there is no infection in the hip and referred causes of pain have been ruled out. What are you going to do?
I would assess the patient Find out how bad the pain is and whether the hip should be revised or whether symptoms are manageable and the patient can be reviewed regularly at the orthopaedic follow-up clinic.
The patient can only walkabout 200 yards before severe pain.
I would offer him revision hip surgery provided comorbidity issues have been optimized and the risks of surgery had been discussed and understood.
What are the complications that you would need to mention to the patient when consenting for surgery?
I would mention Infection. Nerve palsy (peroneal, sciatic femoral) 2–7%. In addition, the patient has significant bone loss on both the femoral and acetabular side, so I would plan to use donor femoral head allograft to attempt to restore bone stock. An osteotomy site can also go on to either malunion or non-union. I would warn him that he might need a period of partial weight bearing if there were concerns with initial implant stability due to excessive osteolysis and bone loss.
You mentioned about the bone loss. How do you plan for this?
Bone loss can be classified on the femoral side by using either the AAOS (Table 3.3) or the Paprosky classification system (Table 3.4).
Figure 3.3a Anteroposterior (AP) radiograph of loose cemented right THA.
Table 3.3 AAOS classification system for femoral defects.
I Segmental defect proximal (partial or complete)
intercalary greater trochanter
II Cavitary defect cancellous cortical ectasia (dilatation)
III Combined segmental and cavity defect
IV Malalignment rotational angular
V Femoral stenosis
VI Femoral discontinuity
Table 3.4 Paprosky classification system for femoral defects.
I Minimal metaphyseal cancellous bone loss with normal intact diaphysis
Type I defects are seen after removal of uncemented component without biological ingrowth on surface.
II Extensive metaphyseal cancellous bone loss with normal intact diaphysis
Often seen after removal of cemented prosthesis. Calcar deficiency and major AP bone loss
IIIA Metaphysis severely damaged with > 4 cm diaphyseal bone for distal fixation
- Grossly loose femoral component
- First-generation cementing techniques
IIIB Metaphysis severely damaged with < 4 cm diaphyseal bone for distal fixation
Type IIIB defects extend slightly further than Type IIIA; however, reliable fixation can be achieved just past the isthmus of the femur
- Cemented with cement restrictor
- Uncemented with substantial distal osteolysis
IV Extensive metaphyseal and diaphyseal bone loss/isthmus non-supportiv e
Extensive defect with severe metaphyseal and diaphyseal bone loss and a widened canal that cannot provide adequate fixation for a long stem
Acetabular bone loss
Acetabular defect classification systems are used to predict the extent of intraoperative bone loss and guide reconstructive options.
Several classification systems exist; the three most commonly used are the American Academy of
Orthopaedic Surgeons (AAOS) system (Table 3.5), the Gross and associates system (Table 3.6) and the
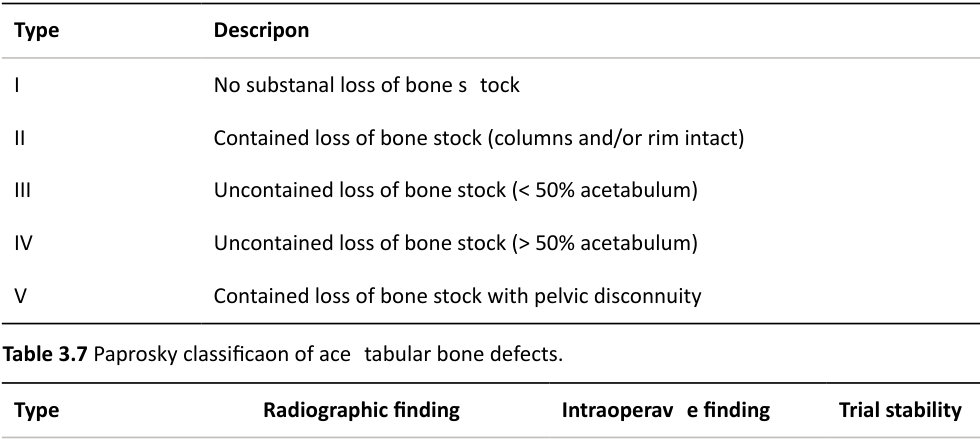
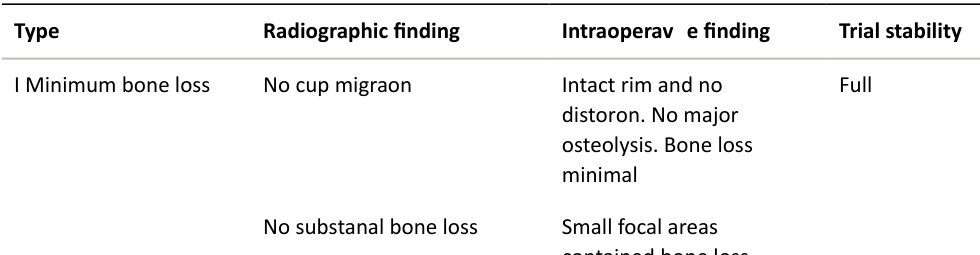
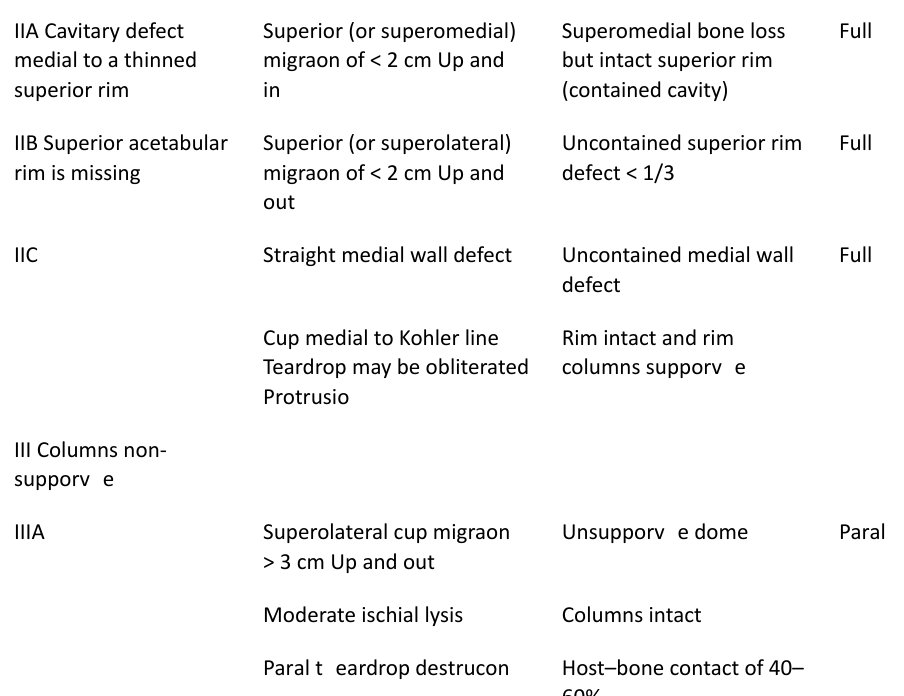
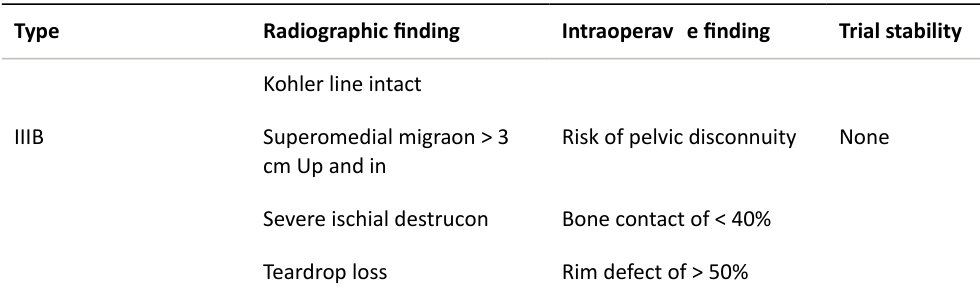
Paprosky classification system (Table 3.7).
Table 3.5 AAOS classification system for acetabular defects.
Type I Segmental defects
Peripheral – superior/anterior/posterior
Central – medial wall absent
Type II Cavitary defects
Peripheral – superior/anterior/posterior
Central – medial wall intact
Type III Combined segmental and cavitary bone loss
Type IV Pelvic discontinuity
Separation of anterior and posterior columns
Type V Arthrodesis
Table 3.6 Gross and associates classification system.
Columns intact
II Anterior and posterior columns intact and supportive
Migration less than 2 cm superomedially or laterally
Minimal ischial lysis
Minimal tardrop lysis
Migration medial toKo hler line
Gross and associates classification system (Table 3.6)
This classification is based on the nature of the bone graft needed for reconstruction determined on standard preoperative AP and lateral radiographs.
Paprosky acetabular bone loss classification
This classification is based on information that can be obtained from AP radiographs. Four radiographic criteria are assessed:
1. Superior migration of the hip centre
Indicates damage to anterior and posterior columns
Supero-medial indicates greater damage to anterior column
Supero-lateral indicates greater damage to posterior column
2. Ischial osteolysis
Bone loss inferior posterior column and posterior column
3. Teardrop osteolysis
Inferior anterior column and medial wall
4. Position of the implant relative toKo hler’s line
Deficiency of anterior column and/or medial wall deficiency
A trial component with full inherent stability does not change position when the surgeon pushes its rim or performs a trial reduction. A trial component with no inherent stability changes position with the simple act of removing the inserter.
The Paprosky classification (Table 3.7) is often used clinically in preference to the AAOS classification as it not only predicts bone loss encountered intra operatively, but also assists in determining reconstructive options.
How would you plan for surgery?
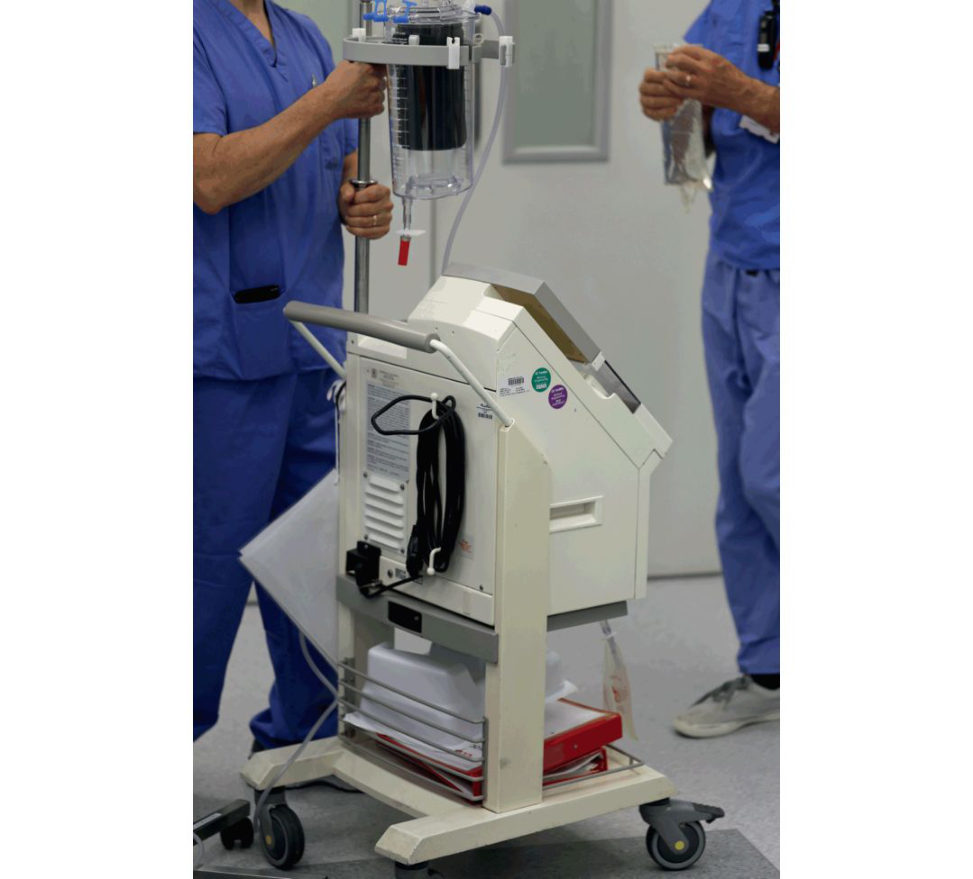
I would counsel the patient regarding the natural history of the condition and recommend revision is undertaken on an urgent basis as the situation is likely to deteriorate and may lead to catastrophic periprostatic fracture. I would cross-match for 4 units and make sure the cell saver(Figure 3.3b) was available.
What dose of tranexamic acid?
1 g IV and if needed a further dose of 1 g IV at closure. I would obtain the original operative notes to check what surgical approach was used and which implants were inserted. I would ideally make sure the case wasn’t performed at the weekend when fewer staff are generally available or last case on a Friday with the possibility of a long theatre overrun.27 I would need to make sure the implant removal kit would include curved and straight osteotomies for the cemented cup and femur, ultrasonic tools, high-speed burrs rongeurs, cement sp lifters, reverse hooks, drills and Dall miles cabling system. I would also hesitate touse cementas long-term results in revision cases can be poorI would plan to use a long-stem uncemented modular tapered fluted revision femoral implant, aiming for a good scratch fit distally. I would attempt to use at least a 32-mm head but preferably a 36-mm head, as this will significantly reduce the risk of postoperative dislocation. I would prefer to use a posterior approach, incorporating the old incision in to this if possible. If the risk of dislocation was deemed very high I would consider using an anterolateral approach or more preferably a posterior approach but with the use of a dual-motion acetabular cup. ‘I would’ is what YOU would do.
An ETO would simplify implant and cement removal, but as mentioned, in this particular situation I would prefer to avoid it.
I would use cement sp lifters to remove cement along with ultrasonic tools. Cement is split radially and longitudinally and then removed.
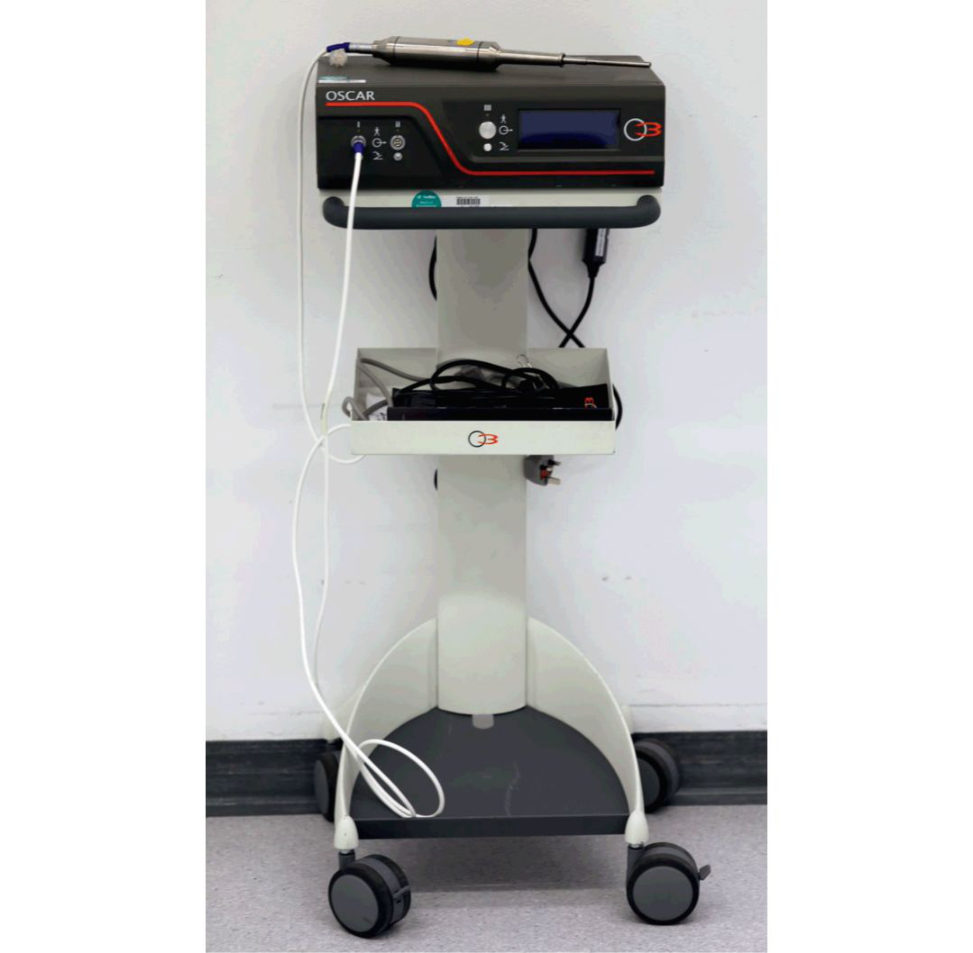
OSCAR (Figure 3.3c) (or a similar ultrasonic cement removal system) is useful forget ing through a distal cement plug. I would avoid levering the cement out as this risks an iatrogenic fracture, especially around the greater trochanteric region.
What about the acetabular component, if it’s cemented?
The safest way is to disrupt the PE cup from the cement using curved gouges. The extractor is then toggled to disrupt the fixation interface and allow removal of the component. High-speed burrs are sometimes needed tode bulk cement within acetabular anchoring holes.
And if the socket is uncemented?
The order of removal is component liner removal then screw removal (if there are supplementary screws) and finally metal shell removal. That is why it is important to have a good system in place whereby old medical records can be easily retrieved to look over well in advance of surgery. Removing any supplementary screws can be challenging and I would always have the Timex broken screw set available as well as a burr in case the screwheads are gone. Finally, to remove the metal-backed shell, the essential tool required here is the Explant (Figure 3.3d). This has been revolutionary in making the removal of an uncemented acetabular shell easier.

Figure 3.3b Cell saver.
Figure 3.3c OSCAR system.
Figure 3.3d Explant (Innomed) acetabular cup removal system.
Structured oral examination question 4
These are the radiographs of a 78-year-old lady who has been referred to the orthopaedic clinic by her GP because of increasing pain in her right hip. Would you care to comment on the radiographs? (Figure 3.4)
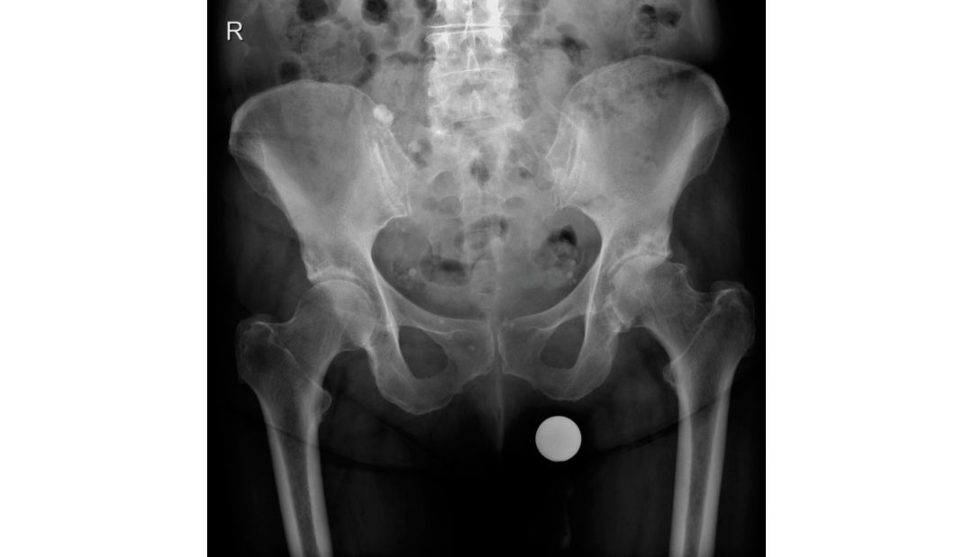
This is an AP radiograph, demonstrating lo wer lumbar vertebrae, both hips and proximal femur.
How is osteoarthritis classified?
OA is classified into primary OA when an obvious cause can be identified
What are the percentages of each type of OA?
Various studies have suggested that almost 90% of cases of OA are secondary.
How are you going to manage this patient?
I would take a full history and examination from the patient Specifically, I would want to know the location of pain and exclude referred pain from the spine. Pain radiating below the knee to the foot is strongly suggestive of radicular-type pain from the spine.
The patient struggles to walk a quarter of a mile. She has typical symptoms of advance dOA. What are you going to do?
Assuming that all conservative options had been tried and have been unsuccessful I would offer her THA.
What type of hip arthroplasty would YOU perform?
I would use a cemented Exeter THA.
Why this particular implant?
The Exeter THA has excellent peer-reviewed long-term data. This hip system provides me with the ability to deal with anatomical variants and to recreate offset and leg length and gives me a choice of bearing surfaces and head sizes.
It allows good initial fixation and excellent long-term survival.
It is an ODEP (Orthopaedic Data Evaluation Panel) 13A* rated stem.
What do you mean by anatomical variants?
The shape of the femur.
The shape of the femur is a more important consideration when using an uncemented implant and isless applicable for a cemented implant.
In smaller femurs oversizing of a femoral component may result in an incomplete or insufficient cement mantle of less than the recommended 2 mm uniform thickness.
What is the problem with using smaller stems?
I am not sure.
If you use a smaller stem there are concerns with stem breakage and implant failure.
The viva could have gone on to discuss stem geometry affecting cement stresses (avoidance of sharp edges,
What do we mean by a Dorr grading of the femur?
type B have a smooth metaphyseal– diaphyseal transition and type C do not have much difference in the sizes of these two regions.
how does this apply to uncemented implants?
We tend to avoid using uncemented implants inpatients with Dorr C femurs.
What are the survival figures like for the Exeter implant?
CORR 200828 Results of Exeter THA in younger patients < 50 years at 10–17 years FU Survivorship of the femoral stem from all causes was 99% No stem was revised
2. Petheram et al. Bone Joint J 201629
Results of Exeter THA at 20–25 years.
FU study of 382 cemented Exeter THA (350 patient sat a mean age of 66.3 years (17–94).
With an endpoint of revision for aseptic loosening orly sis, survivorship of the stem at
22.8 years was 99.0%
Figure 3.4 Anteroposterior (AP) radiograph demonstrating severe osteoarthritis left hip.
What are the design principals of the Exeter Stem?
The Exeter implant is a loaded taper model and becomes lodged as a wedge in the cement mantle during axial loading,
What approach would you use to the hip?
I am happy to use either the Hardinge or posterior approach to the hip.
Make up your mind. Which one are YOU going to do?
For the majority of cases I would prefer to use the posterior approach to the hip.
The posterior approach is considered easier to perform and is generally a quicker procedure, limiting operative complications such as blood loss anda naes thetic issues.
The sciatic nerve is at slightly more risk of being injured as well.
3 0 There is about double the risk of sciatic nerve injury using the posterior approach.
I would argue about the acetabulum beingless easy to visualize posteriorly as most surgeons believe the posterior approach provides better acetabular visualization, especially for revision cases. The pelvis tends to tilt more and so the degree of cup anteversion is usually underestimated leading to an increased risk of dislocation WhereI think the posterior approach does make a difference is a reduced incidence of Trendelenberg gait postoperatively and improved Harris hip scores compared to the anterolateral approach.
Talk me through the posterior approach to the hip.
I would then prepare and drape the patient and make an incision centred over the greater trochanter, approximately 15 cm in length. I would protect the sciatic nerve, being aware of its position and a void dissecting too close to it. I would place a large retractor over the anterior edge of the acetabulum at 2–3 o’clock. I would then place a Charnley spike into the posterior wall of the acetabulum and an additional Hohmann retractor inferiorly. This should give me a 360° view of the whole face of the acetabulum as recommended by BOA guidelines.
What are the pathological processes involved in the development of osteoarthritis of the hip?
Disruption of the integrity of the collagen network occurs early in OA allowing hyperhydration. The increased water content of cartilage causes softening, decreases Young’s modulus of elasticity and reduces its ability to bear load. Initial changes in OA involve damage to the tangential z one immediately below the articular surface, with disorganization of the collagen network, loss of proteoglycans and swelling. Cartilage catabolism results in release of breakdown products into synovial fluid, which then initiate san inflammatory response by synoviocytes. These breakdown products include: chondroitin sulphate, keratan sulphate, PG fragments, type II collagen peptides and chondrocyte membranes. The y also release cytokines, proteinases and oxygen free radicals (superoxide and nitric oxide) into the adjacent synovial fluid. These mediators act on chondrocytes and synoviocytes, modifying synthesis of PGs, collagen, and hyaluronan as well as promoting the release of catabolic mediators. Interleukin-1. Replication and breakdown of the tidemark.
Fibrillation.
Cartilage destruction with eburnation (polished, shiny smooth with an appearance like ivory)
of subchondral bone.
Is OA simply an ageing process of cartilage?
Several differences between ageing cartilage an dOA cartilage have been described suggesting ase parate disease entity .
[Interrupting] That’s fine that’s OK.31 What molecules are responsible for degrading the cartilage matrix?
The primary enzymes responsible for the degradation of cartilage are the matrix metalloproteinases (MMPs). They are secreted as inactive proenzymes that require enzymatic cleavage in order to become activated Once activated, MMPs become susceptible to the plasma-derived MMP inhibitor, alpha-2- macroglobulin In OA, synthesis of MM Psis greatly enhanced and the available inhibitors are overwhelmed, resulting innet degradation Interestingly , stromelysin can serve as an activator for its own proenzyme
What factors are responsible for inducing metalloprotease synthesis?
IL-1 is a potent pro-inflammatory cytokine that, IL-1 suppresses the synthesis of type II collagen and proteoglycans and inhibits transforming growth factor-β-stimula ted chondrocyte proliferation.
Structured oral examination question 5#
Osteonecrosis (ON)
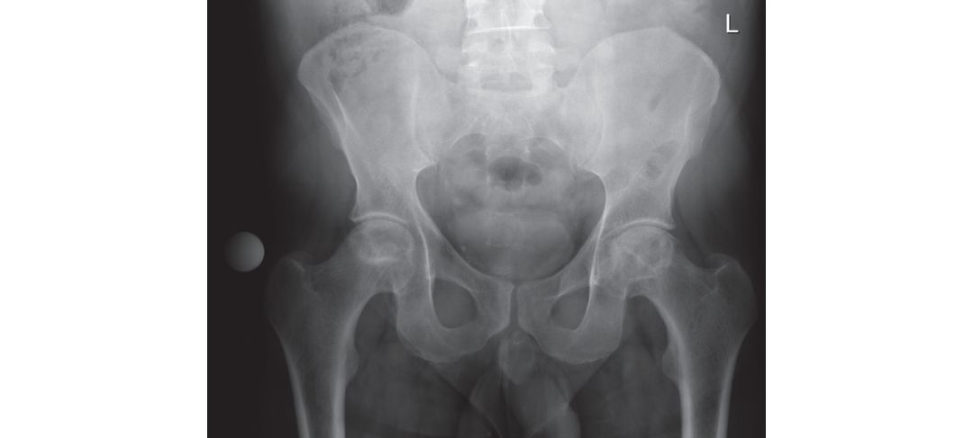
This is the anteroposterior (AP) radiograph of a 48-year-old man who presents to your clinic with several weeks history of progressively worsening bilateral hip pain. What do you think of the radiograph? (Figure 3.5a) CANDIDATE 1 : This is an anteroposterior (AP) view of the pelvis. The most obvious abnormality is patchy diffuse sclerosis with increased density in the superolateral aspect of the right femoral head (Ficat 2). The left femoral head has a possibly minimal osteoporosis and/or blurring and poor definition of the bony trabeculae (Ficat 1). The radiograph is suspicious of bilateral osteonecrosis. I would like to obtain a frog-leg lateral radiograph of both hips. I would look for the crescent sign, indicating subchondral fracture, a feature of osteonecrosis that is more obvious on a frog-leg lateral than AP projection. This is because the anterior and posterior margins of the acetabulum on the AP projection are superimposed over the superior portion of the femoral head, the usual location of the sign. When osteonecrosis is bilateral, it usually occurs in each hip at different times, and the staging of disease in each hip is often different. [Candidate score 7–8] CANDIDATE 2 : This is an AP pelvic radiograph showing both hips. There is nothing very obvious staring at me. There are no features of osteoarthritis such as joint space narrowing osteophytes or sclerosis.32 [Candidate score 4] What do you mean by osteonecrosis?
Osteonecrosis occurs due to interruption of the blood supply to the femoral head leading to ischaemia and cellular death.
What is the aetiology of osteonecrosis?
A number of conditions are associated with osteonecrosis. The most common cause is trauma secondary to fracture and/or dislocation of the femoral head.
Organ transplantation.
Systemic lupuserythematosus.
Gaucher disease.
Hypertriglyceridaemia.
Intramedullary haemorrhages.
Chronic pancreatis.
Figure 3.5a Anteroposterior (AP) radiograph of bilateral osteonecrosis.
AS IT GRIPS 3Cs (mnemonic)
Alcohol
Steroids
Idiopathic
Trauma
Gout Gauchers
Rheumatoid/radiation
Infection/incr eased lipids/inflammatory arthritis
Pancreatis/pregnancy
SLE/sickle cell/smoking
CRF/chemotherapy/Cassion’s disease
In approximately 10–20% of cases no cause can be identified.
What is the pathophysiology of osteonecrosis?
This damage can occur in one of five vascular areas around the femoral head: arterial extraosseous, arterial intraosseous, venous intraosseous, venous extraosseous and extravascular extraosseous. 1. Extraosseous arterial factors are the most important. 2. Intraosseous arterial factors may block the microcirculation of the femoral head through circulating micro emboli. 3. Intraosseous venous factors affect the femoral head by reducing venous blood flow and causing stasis. 4. Intraosseous extravascular factors affect the hip by increasing the pressure, resulting in a femoral head compartment syndrome. For example: fat cell hypertrophy after steroid administration or abnormal cells, such as Gaucher and inflammatory cells, can encroach on intraosseous capillaries, reducing intramedullary circulation and contributing to compartment syndrome.
5. Extraosseus extravascular (capsular) factors involve the tamponade of the lateral epiphyseal vessels located within the synovial membrane,
Specifically, how do steroids cause osteonecrosis?33
Jaffe et al. believe patients undergoing steroid treatment are in a hyperlipidaemic state, which can increase the fat content within the femoral head and raise intracortical pressure producing sinusoidal collapse and finally necrosis.35 Other investigators have proposed that this hyperlipidaemic state leads to fat embolism occluding the femoral head microvasculature, which initiates the pathophysiologic process.36 A recent study in rabbits suggests that the use of steroids can also damage endothelial and smooth muscle cells within the vasculature.
How common is steroids as a cause of osteonecrosis?
High-dose corticosteroids are the most common cause of non-traumatic osteonecrosis accounting for 10–30% of cases. The period from the start of corticosteroid treatment to the diagnosis of osteonecrosis ranges from 1 to 16 months (mean 5.3 months)
You mentioned the crescent line, what is its significance?
Therapeutic interventions are less likely to halt progression of the disease once this sign appears.
How does osteonecrosis of the hip present?
Although osteonecrosis can be clinically silent, typically apa tien t complains of pain, usually localized to the groin area but occasionally to the ipsilateral buft ock and knee. Physical examination reveals pain with both active and passive range of motion, especially with passive internal rotation. A careful examination of the contralateral hip should always be undertaken, as osteonecrosis is bilateral in 40–80% of cases.
How is osteonecrosis classified?
Several classification systems for osteonecrosis exist. Ficat and Arle tis the most commonly known and consists of four stages.38 Hungerford and Lennox later added a fit ihs tage (Stage 0) when MRI became available.39 Stage 0 (preclinical). Stage I (preradiological). Normal findings on radiographs and positive findings on MRI or bone scan. The MRI shows a double-line sign, consistent with a necrotic process. Stage II (pre-collapse). Stage III (collapse). Stage IV (progressive degenerate disease). Osteoarthritis superimposed on a deformed femoral head.
Any other classification systems?
Steinberg (Table 3.8) expanded the staging system into seven stages and quantified the amount of involvement of the femoral head into mild (< 15%), moderate (15–30%) and severe (> 30%),
Any others?
Other classification systems include the ARCO (Association Research Circulation Osseous) classification University of Pennsylvania system and the Mitchell MRI classification.
What is the Kerboull necrotic angle and its importance?
Patients with a Kerboull angle > 200° more commonly have poor results with certain bone-preserving procedures.
How are you going to manage this patient?
Results have been satisfactory when core decompression is combined with either non-vascularized or vascularized fibula gratis in patients with Ficat stage II lesions.
What are the pre-requisites for performing a free vascularized fibular graft (VF G)?
McKee from Toronto suggests the operation should be limited topa tien ts [scoring 7–8]:41 1. With 2 mm orless of femoral head collapse as measured on plain radiographs. 2. Who are 45 years of age or younger (and have a reasonable life expectancy). 3. Have had withdrawal of an identified ae tiologic agent. 4. Have no contractures about the hip.
What are the advantages of performing a free VFG?
The advantages of vascularized fibular gratiing include: Being able to perform a core decompression of the femoral head. The addition of vascularized bone and blood supply to the area of osteonecrosis enhances there vascularization process.
What complications can occur with a free vascularized fibular graft?
Ga skillet al. from a tertiary centre in North Carolina performing a large volume of VFG reported a 16.9% complications rate, 4.3% of complications require reoperation or chronic pain management.42,43 Donor site morbidity:
Great-toe flexion contracture (4.3%). Occasionally requires z-lengthening of the FHL tendon at the level of the medial malleolus.
Persistent weakness in the operated extremity (0.6%) either long toe flexors or peroneal group.
Mild persistent pain and tenderness at the ankle or distal osteotomy site (4.1%) usually after prolonged standing or moderate activity such as jogging.
Sensory deficits (1.7%). The sensory deficit was not always consistent with peripheral nerve or dermatomal distributions.
Superficial infection.
Table 3.8 Staging system of Steinberg et al.
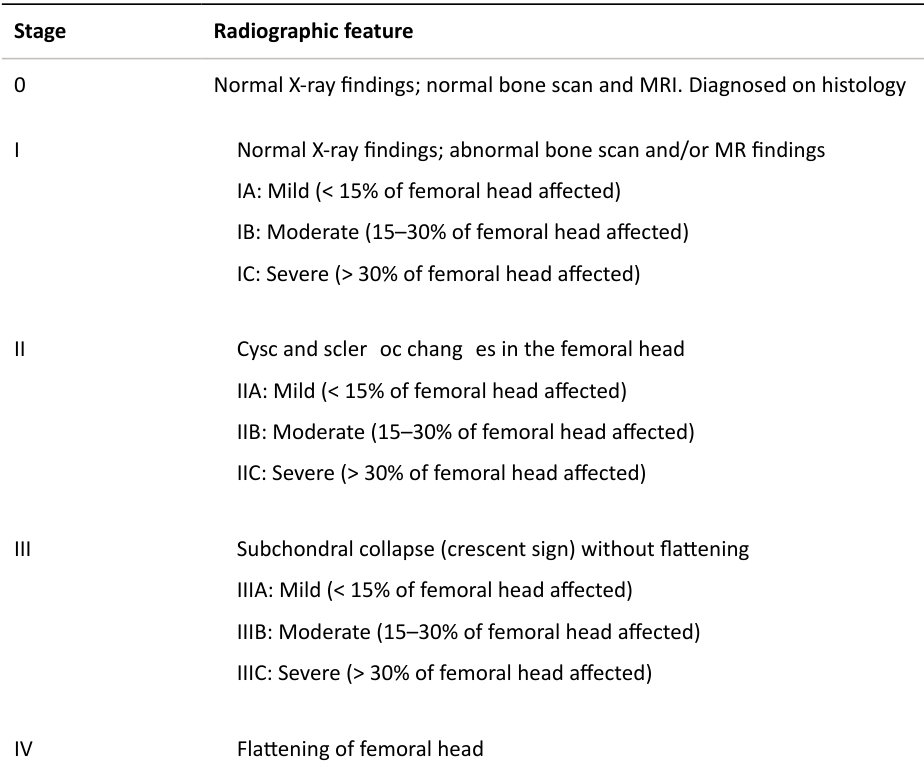
IVA: Mild (< 15% of surface and < 2 mm depression)
IVB: Moderate (15–30% of surface or 2–4 mm depression)
IVC: Severe (30% of surface)
Stage Radiographic feature
V Joint narrowing and/or acetabular changes (this stage can be graded according to severity)
VI Advanced degenerative changes
Graft site complication
Symptomatic lateral pin migration (2.4%). A Kir schner wire was used routinely to secure the fibular graft in its final position after placement in the femoral head.
Symptomatic heterotopic ossification (1.4%).
Femoral fracture (0.7%). All occurred in the intertrochanteric and subtrochanteric region after a fall.
Superficial infection (4%).
Deep infection (4%).
Haematoma (1%).
Trochanteric bursitis (1%).
What are the other techniques that can be used to manage osteonecrosis of the hip?
The trapdoor procedure is performed with an arthrotomy to dislocate the hip anteriorly, This can be used for Ficat stage III and early Ficat stage IV and reasonable results have been reported.
You have to be more specific than that; what do you mean by reasonable results?44
Michael Mont reported on a series of 30 hips Ficat stage III/IV at 5 years with 73% having good to excellent results.45
Any other options?
Sugioka et al. reported good to excellent results at 3–16 years of follow-up in 78% of 229 hips treated with the transtrochanteric anterior rotational os teotomy.46 Their results with this technically demanding procedure have not been reproduced by others.
Any new technique that has emerged in the last 2 or 3 years?
Stem cells have been used to manage ON.
Go on – do about the technique or results?
The first method is by stem cell culture in the lab to multiply the number of cells several millionfold.
In the second method, bone marrow obtained from the pelvis is centrifuged in the operating room to yield a bone marrow concentrate rich in stem cells.
C-arm image intensifier. Percutaneous core decompression drilling with a Kirschner wire (diameter
2.7 mm) is performed to perforate the interface between the necrotic lesion and healthy bone.
Following this, concentrated autologous bone marrow aspirate is slowly transplanted into the necrotic area under fluoroscopic control.
The patient had surgery on both hips. These are his postoperative radiographs (Figure 3.5b).
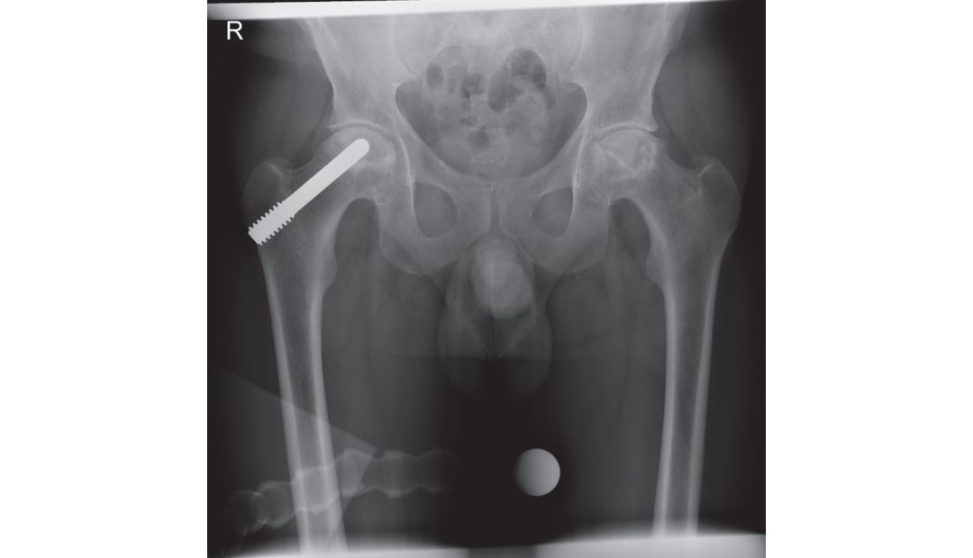
The AP radiograph demonstrates a metal core rod in the right hip.
What do we call this?
The patient has had a tantalum rod inserted into the femoral head.
Anything else?
The use of a trabecular metal ‘AVN rod’ has a number of atir active theoretical advantages,
The patient had core decompression performed on the left hip and a c ore decompression with tantulum rod inserted in the right hip. He initially got good pain relief from the procedures for about a year or so, but he returns to the orthopaedic clinic complaining both hips are now painful. The left side is worse than the right. What do you think of the radiographs?
The AP radiograph suggests osteonecrosis has progressed.
What will you do?
I would offer him bilateral hip arthroplasty, the left one being more symptomatic first.
What type of hip replacement would you use?
In view of his relatively young age I would perform an uncemented THA with a ceramic on HCLPE bearing surface.
What are the results like at 10 years for this bearing surface? What will you tell the patient about how long his hip will last?
The latest NJR report (15th, 2018) has shown a 5.33% (3.77% to 7.50%) RR at 14 years for males aged under 55 with an uncemented THA CoP surface.
Are there any other bearing surface options a vailable?
A ceramic-on-ceramic (CoC) bearing surface.
What are the advantages of using a ceramic bearing surface?
The advantages of using a ceramic bearing surface include superior lubrication, friction and wear properties compared with other bearing surfaces in clinical use. It is presumed that the lower wear rates lead to a lower rate of aseptic loosening and the need for revision surgery.
What is the incidence of squeaking?
The reported incidence of squeaking with alumina ceramic bearings varies widely from 0.45% in a series of 2716 ceramic implants to 7.0% in a series of 159 ceramic implants.
What are the results like for ceramic-on-ceramic hips?
UK NJR data report a 6.43% (5.17–7.98%) revision rate at 14 years for males aged under 55 with an uncemented THA CoC surface. Definitely avoid mentioning MoM resurfacing as an option in a viva scenario unless specifically brought up in the discussion by the examiners.48 Ceramic on X3 poly is becoming the preferred bearing option for young patients with most hip arthroplasty surgeons moving away now from ceramic-on-ceramic use.
Will there be any special issues removing the tantulum rod and performing THA?
I would use a Gigli and reciprocating saw to section the head, implant removal corer to take out the tantulum rod and then perform a conventional uncemented THA.
Are there any worries with tantalum material?
Studies suggesta trend towards an inferior outcome inpatients following conversion of tantalum rod to THA.49 There is also concern of residual tantalum metal within the joint space found in the majority of conversions.
These are his radiographs (Figure 3.5c). He had a large jumbo MoM performed on the left side and a large ceramic jumbo head THA performed on the right side. Do you have any worries?
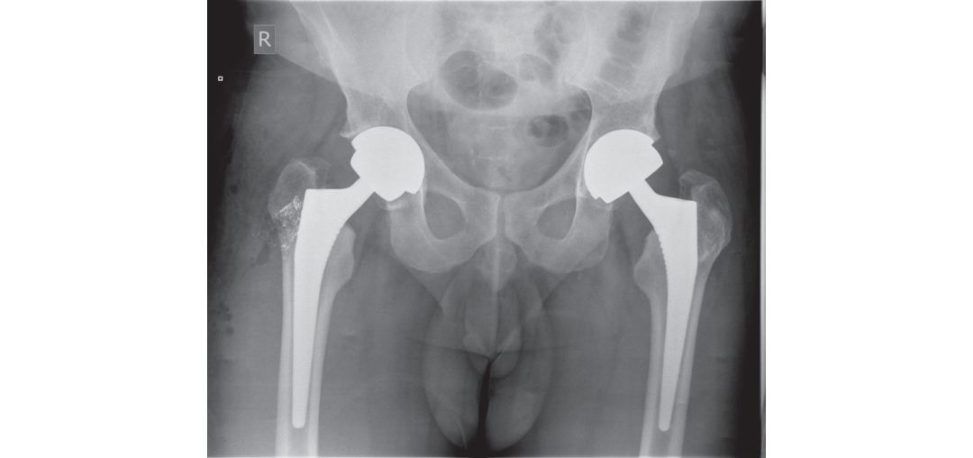
Concern was expressed regarding the trunnion at the ‘Morse’ taper where the large diameter metal head attaches to the stem with damage occurring from either wear or corrosion or both resulting in either loosening of the acetabular component, loosening of the femoral component or a metal reaction with necrosis and soft tissue damage Excluding the ASR implant these devices have a reported revision rate of 22.14% at 13 years (14th NJR data).
What about followup?
Pain in this group of patients should betaken seriously and investigated appropriately with cobalt chromium levels, a MARS MRI scan of the hip and OHS. Although each patient needs to be assessed individually I would have a low threshold for obtaining blood level ion measurements and MARS MRI even for asymptomatic patients if I had concern about ARMD.
What would you look for in the MARS MR Iof the hip?
MARS MRI scan is more important in the decision-making process to revise a MoM hip replacement than elevated cobalt/chromium levels. I would have significant concerns in any patients with surrounding muscle/bone damage visualized on MARS MRI. Solid lesions seen on MARS MR Iare more worrying than cystic Synovial thickness has a high sensitivity and specificity for ALVAL.
Is there a role for US of the hip?
Ultrasonography is a good screening tool, is cheap and has no radiation hazard.
What about the other ceramic hip?
There are some worries again regarding the trunnion where the large ceramic head attaches to the stem,
Why choose a Delta ceramic head over a cobalt chrome head?
It was originally thought that this would result in a lower revision rate with decreased clinically relevant wear rates. head–neck junction alloy composition also playing a part.
Figure 3.5b Anteroposterior (AP) radiograph of pelvis with tantulum rod inserted into the right hip.
Figure 3.5c Anteroposterior (AP) radiograph left MoM hip and right ceramic large jumbo hip arthroplasty.
Structured oral examination question 6#
This is an anteroposterior (AP) radiograph of a 73-year-old male who had a cemented THA performed 14 years ago (Figure 3.6).
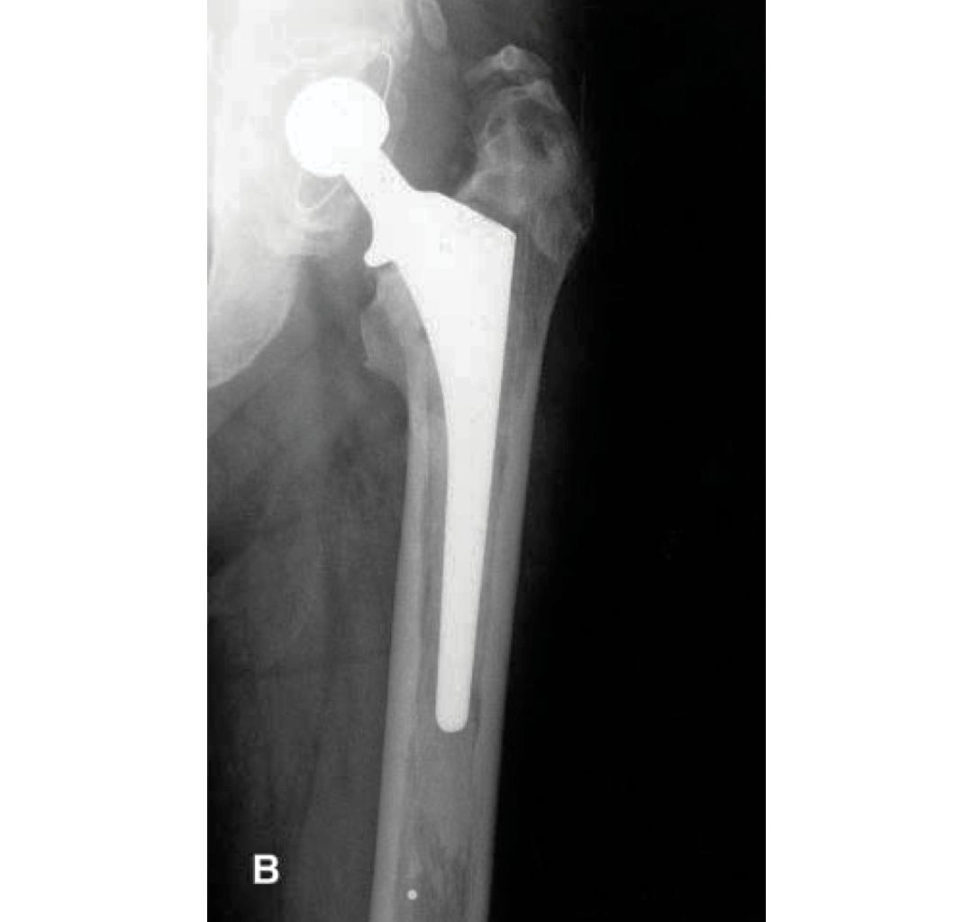
The AP radiograph demonstrates a cemented THA. I am unfamiliar with the implant, but both the cup and femoral stem have been cemented and most likely a 28-mm head size has been used. There are no significant lucencies in any of the DeLee and Charnley acetabular zones.
What areG ruen zones?
This is a widely used system in which the femoral component interface is considered in seven zones.
What mode of cemented femoral stem failure has occurred?
This is Gruen mode 1b failure. Pistoning subsidence of stem and cement within bone.
Briefly, what are the other modes of failure?
There is mode 1, apis toning subsidence of stem within cement mantle; mode 2, medial midstem pivot; mode 3, calcar pivot and bending cantilever fatigue (distal pivot).
what will you see radiographically with each mode of failure?
There is one mode of failure like a car windscreen wiper but I am not sure which one, I think it may be medial stem pivot mode 2, no sorry I think it is mode 4.
What do we mean by the term wear?
Wear is defined as a progressive loss of bearing surface from a material as a result of chemical (corrosive) or mechanical action Types of mechanical wear include adhesive, abrasive and fatigue.
What do you mean by abrasive and adhesive wear?
Abrasive wear occurs when two surfaces with microscopic irregularities or asperities slide past oneanother while in intimate contact.
Adhesive wear occurs when two opposing materials bond under contact load. These new particles then further contribute to wear from third-body abrasive wear.
The wear of UHMWPE in THA is mainly adhesive and abrasive.
What is freting w ear?
Freting occurs with small cyclic motions of one surface relative to another.
What are the wear sources in joint replacement surgery?
Wear sources include the primary articulation surface, secondary articulation surfaces, cement/prosthesis micromotion, cemen t/bone or prosthesis/bone micromotion and thir d-body wear.
What are the modes of wear in joint replacement surgery?
2. Mode 2 refers to a primary bearing surface rubbing against a secondary surface in a manner not intended by the designers (for example, a femoral head articulating with an acetabular shell following wear-through of the polyethylene). While several modes of wear often occur simultaneously, mode 1 accounts for the majority of wear in well-functioning hip or knee replacements.
What do we mean by effective joint space?
and hence wear debris, can gain access.50 In the acetabulum, wear debris can reach the interface through unfilled screw holes or via non-ingrown areas of the shell.
What is osteolysis?
Me tal or ceramic wear particles that are produced at the articulating surfaces of a hip prosthesis are also implicated but to a much lesser degree.
Osteolysis is influenced by the size and morphology of the UHMWPE particles Macrophages actively phagocytose (engulf) wear debris at the bone–implant interface.
These cytokines cause inflammation and trigger bone dissolution or resorption around the implanted region.
What factors influence osteolysis (wear)?
soft -tissue balancing) that affect joint loads and kinematics influence wear performance of THA (and TKA) (see Table 3.10). Patien t-specific factors that affect wear performance of THA (and TKA) include (see Table 3.11).
What do about osteoblastic regulators?
Three osteoblastic regulators (RANK, RANK Land OP Gare involved in bone resorption.
Figure 3.6 Anteroposterior (AP) radiograph of a loose cemented left THA .
Table 3.9 Implant-specific factors affecting joint wear.
Implant design choices
Modularity versus monoblock
UHMWPE component thickness
Bearing couple conformity
Fixation (cemented versus ingrowth)
Implant constraint
Implant impingement
Material
Metallic alloy (Co–Cr–Mo alloy versus titanium alloy)
Ceramic (alumina, zirconia, oxidized zirconium alloy)
UHMWPE (highly cross-linked versus conventional)
Bearing couple
Metal-on-UHMWPE
Ceramic-on-UHMWPE
Metal-on-metal
Ceramic-on-ceramic
Quality control
Lot-to-lot variability
Shelf-life and packaging of UHMWPE components
Sterilization process (radiation versus ethylene oxide)
Table 3.10 Surgical factors affecting joint wear.
- Surgical approach
- Component position
- Restoration of appropriate mechanical and rotational axes
- Initial stability and method of component fixation
- Soft -tissue balance laxity versus overconstraint)
- Subluxation or dislocation
- Third-body wear
- Surgeon experience
Table 3.11 Patien t-specific factors affecting joint wear.
- Activity le vel (activities of daily living , pivot-shift activities). Patients with active lifestyles often return to recreational activities that markedly increase joint-loading conditions (eg. running, jumping, pivoting , stair climbing)
- Body mass index and bodyweight. Increased bodyweight can be associated with increased magnitude of force and altered kinematics, although the detrimental effects of excessive weight can be counterbalanced by decreased activity levels and loading cycles that accompany a sedentary lifestyle
- Gait mechanics (level and stairs)
- Limb alignment
- Implant time in situ
- Preoperative diagnosis post-traumatic arthritis and AVN have been associated with higher prosthesis failure rates as usually arthroplasty is performed in younger, more active patients
- Comorbidities. A CL and meniscal injuries predispose to osteoarthritis in a young age group
- Special cultural demands (e.g. kneeling in Middle Eastern and Asian populations). Deep flexion for kneeling, load implants beyond current design characteristics (TKA)
- Revision versus primary surgery
Gold medal candidates#
Periprosthetic osteolysis is the loss of bone surrounding an artificial implant.
The interfacial membrane is composed primarily of two cell types, the macrophage and the fibroblast.
Aseptic osteolysis is thought to occur through a mechanism involving expression of bone resorptive cytokines such as interleukin-1β (IL-1β), interleukin-6 (IL-6),
RANK Lisa potent bone resorptive cytokine present on the membranes of bone marrow stromal cells, osteoblasts in bone
Macrophages express RANK and, when exposed to RANK Lin the presence of macrophage colony-stimulating factor (M-CSF), have been shown to differentiate into mature osteoclasts capable of bone resorption. Osteoclast activation is thus blocked.
What factors affect PE cup wear in THA?
Patient factors include younger age due to higher activity levels, obesity due to increased joint loading.
What is the current thinking about UHMWPE?
Three approaches are currently being investigate din an attempt to modify highly cross- linked UHMWPE so that the increased wear resistance provided by cross-linking can be maintained without the reduced fracture resistance that accompanies cross-linking:53 1. 2. A second approach involves sequentially irradiating and annealing polyethylene.
3. The third approach involves the photo-induced graft polymerization of 2-me thacryloyloxyethyl phosphorylcholine (MP Conto cross-linked polyethylene (CLPE).
Structured oral examination question 7#
This is a radiograph of a 68-year-old woman who has been referred up to the orthopaedic clinic by the physiotherapist-led musculoskeletal clinic with an 18-month history of left hip pain and difficulty walking (Figure 3.7).
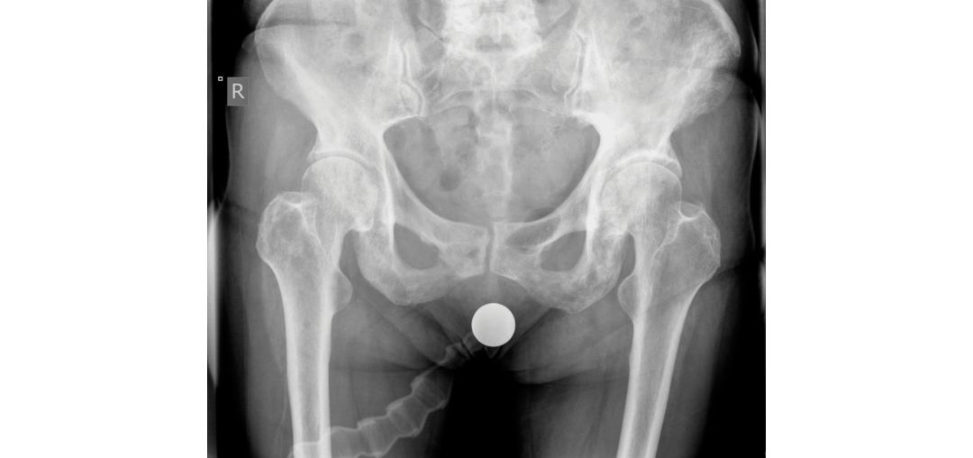
This is an anteroposterior (AP) radiograph of the pelvis demonstrating a coarsened trabecular pattern of the left hip, a thickened left cortex compared to the opposite hip, and increased density of the left hip compared to the right side. The radiograph is highly suspicious of Paget’s disease.
What is Paget’s disease?
Paget’s disease is a metabolic bone disorder of unknown aetiology characterized by a disorganized increase in osteoclastic bone resorption and compensatory osteoblastic new bone formation.
What causes Paget’s disease? What is the pathophysiology of Paget’s disease?
The primary abnormality of Paget’s disease is an intense focal resorption of normal bone by abnormal osteoclasts. The osteoblast activity is rapid such that the newly formed bone is not organized and remains irregular and woven in nature, prone to deformity and fracture.
What are the other radiographic features of Paget’s disease?
Radiographic features of Paget’s include: Advanced disease in the long bones is characterized by coarsened trabecula, bony sclerosis, bony enlargement, and deformity. Fine cracks may appear (stress fractures) which resemble Looser zones but occur on the convex bone surface.
Lateral radiographs of the lumbar spine demonstrate a ‘picture-frame’ vertebral body that is secondary to severe osteoporosis centrally and a thickened, sclerotic cortex.
The skull is involved in 29–65% of cases. It is seen in the early or lytic phase when osteoclastic resorption overwhelms bone production. A t a later stage a ‘coft on wool appearance’ represents mixed lytic and blas tic pattern of thickened calvarium.
Protrusio deformity of the pelvis is a common occurrence with advanced Paget’s disease.
What are the current theories regarding the aetiology of P aget’s disease?
The aetiology of P aget’s disease is still unknown. Electron microscopy has shown virus-like structures that resemble the paramyxovirus in osteoclast nuclei and cytoplasm of cells affected byP aget’s disease. Genetically, 5–40% of patients have first- degree relatives with the disease.
That’s fine. I am, however, sceptical about the cats and dogs theory. Moving on – what are the complications of P aget’s disease?
Complications of P aget’s disease include: Compression fractures of the vertebral body (commonest complication of spinal P aget’s). Most common in the lumbar region and typically single level, causing cord or nerveroot compression. An enlarged and deformed skull can lead to increased intra-cranial pressure, hydrocephalus or cranial nerve deficits such as facial palsy (narrowing of neural foramina), hearing loss or blindness (pressure on optic nerve).
What are the indications for THA in Paget’s disease?
The indications are similar to non-Pagetoid disease. It is also important to exclude insufficiency fractures, neurological compression in the spine or Paget’s sarcoma as a cause of pain.
How do you assess disease activity?
Patients with active Paget’s disease have raised alkaline phosphatase (AlkPhos) and urine hydroxyproline values. The higher the level the more active the disease is.
If the Paget’s disease is active what will you do?
I would refer him to one of my rheumatoid colleagues for a Pamidronate (Aredia) injection. The other option is the use of bis phosphonates or calcitonin to reduce bone-related pain, reduce postoperative bone resorption and decrease bleeding should surgery be required.
What are the technical issues of performing THA in Paget’s disease?
There is a tendency for excessive bleeding at surgery due to increased vascularity. Blood should ideally be cross-matched or at the least available from a group and saved within 10 minutes. Some surgeons use lateral offset liners and antipr otrusio cages, although this complicates surgery. There is some controversy as to whether there is an increased risk of heterotopic ossification occurring from the abnormalities of osteogenic differentiation in P aget patients Some surgeons routinely give prophylaxis to reduce the risk of HO [Score 6].
There is more than that when planning THA.
As bone pain is common in Paget’s disease and does not necessarily improve with THA a diagnostic local anaesthetic injection to rule out concurrent bone pathology may be indicated. Good-quality, full-length radiographs to assess the degree of deformity and the extent of bone involvement. Unrelenting hip pain and radiographic bone destruction suggests sarcomatous change.
Consider using cell salvage, Concurrent osteotomy may be needed if component alignment is difficult.
Marked protrusio can make hip dislocation very difficult.
You mentioned osteotomy, how often do you perform osteotomy when you perform THA for Paget’s disease?
In the majority of patients with Paget’s THA can be performed without need for osteotomy.
What type of hip replacement would you use?
Although there has been a trend in recent years to use uncemented components in Paget’s disease, in this patient I would use a cemented THA. She is 68 and hasP aget’s disease and I think it is a reasonable option in this situation. Although previous studies have recommended the use of cementin the last 20 years there has been a trend to use uncemented components. The biology of bone ingrowth for initial fixation of uncemented components depends, in parton the ability of bone to proceed through the early phase of fracture healing. Parvizi et al. reported on 21 cementless THA implanted against pagetoid bone; all were stable and demonstrated radiographic evidence of ingrowth at 7-year follow-up.54 Lusty et al. from Sydney, Australia reported medium-term results of 23 uncemented THA at 6.7 years follow up.55 There were three revisions, one stem for aseptic loosening and two stems after periprosthetic fracture.
Any special complications that can occur postoperatively?
There is a reported greater incidence of heterotopic ossification.
Anything else?
Dislocation.
No, I am not aware of an increased risk of dislocation.
Other authors have reported that osteolysis is not a problem following THA in Paget’s disease.57 Other complications include periprosthetic fracture around total hip implants
Figure 3.7 Anteroposterior (AP) radiograph demonstrating P aget’s disease of the left hemipelvis.
Gold medal candidates
What causes have been identified for the increased number and activity of Page tic osteoclasts?
Causes identified include: 1. Osteoclastic precursors are hypersensitive to calcitriol (1,25(OH) 2D3). 2. Osteoclasts are hyper-responsive to RANK ligand (RANKL), the osteoclast stimulatory factor that mediates the effects of most osteotropic factors on osteoclast formation. 4. Osteoclast precursor recruitment is increased by interleukin (IL)-6, which is increased in the blood of patients with active Paget’s disease and is over-expressed in pagetic osteoclasts.
Structured oral examination question 8#
DD His one of the most common hip viva questions that regularly gets asked in the oral viva examination.
We think this is because it is a fairly common hip condition with a lot to talk about. The story can go in many different directions.
These are the anteroposterior (AP) radiographs of a 66-year-old woman with bilateral hip pain (Figure 3.8). Would you like topass comment on them? CANDIDATE 1 : The AP radiograph demonstrates a severely dysplastic hip on the right side with secondary OA changes. On the left side again, there is dysplasia but to a lesser degree with again secondary OA changes present. [Score 5] CANDIDATE 2 : This is an AP radiograph of the hips and pelvis of a 66-year-old woman taken on the 16/5/11, which demonstrates severe bilateral dysplasia.58 There is a high dislocation on the right side, Crowe IV or Hartofilakidis III hip. There is no contact between the true and false acetabulum. The femoral head appears poorly developed, probably absent, with the femoral neck articulating against the iliac crest. The view of the proximal portion of the femoral canal on the right side suggests a very narrow medullary canal. On the left sid ether e is a Crowe III hip or Hartofilakidis II hip. There is a low dislocation and secondary osteoarthritis. 59 [Score 6–7] COMMENT60: The left side is a Hart ofilakidis I hip as the femoral head is still contained within the original acetabulum. With a low dislocation the femoral head is in contact, at least in part, with the true acetabulum and in this situation, this is the most severe deformity. In high dislocation, the femoral head and acetabulum make no contact and the head has migrated superiorly and posteriorly. Often in this situation the true acetabulum is reasonably well-preserved, although underdeveloped and osteoporotic. What do you mean by dysplasia?
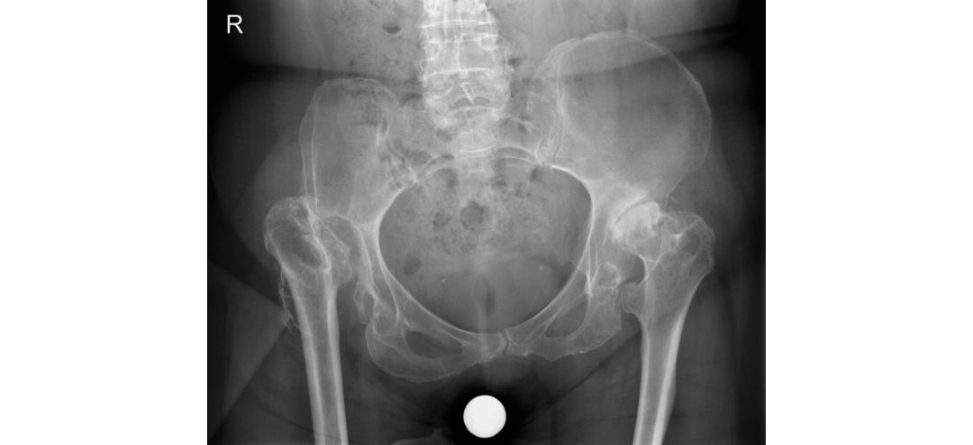
Dysplasia is lack of coverage of the femoral head, whether it is subluxed or dislocated.
How do you classify dysplasia?
The migration is calculated on an AP radiograph by measuring the vertical distance between the inter-teardrop line Cro weI isless than 50% subluxation, Cr owe II hips have between 50% and 75% subluxation.
[Interrupting] That’s fine. That’s OK. Any other classification systems that ?
[Sharp intake of breath, shaking of head and then silence.] No.
Have you heard of the Hartofilakidis classification?
I have, but I can’t remember the specifics.
The Hartofilakidis classification system, which divides DD Hin adults into three types: dysplasia, low dislocation and high dislocation. Many surgeons prefer this system, as it is more practical and simpler to use. What are the anatomical issues associated with DDH?
The anatomical differences are divided into acetabular, femur and soft -tissue issues.
That’s not all the differences. There are some you have missed. Do any more?
Muscles around the hip are usually shortened ander, er ...
The greater trochanter is small and posteriorly displaced, the femoral canal narrow, the acetabulum is usually small with poor bone quality, hip capsule elongated and redundant, psoas tendon hypertrophied, and abductors orientated transversely as a result of the superior migration of the femoral head. The femoral and sciatic nerves may be shortened and therefore more vulnerable to injury during arthroplasty surgery. What is the role of a CT scan in planning an operation for DDH?61 CANDIDATE 1: CT scans can be used to determine the available acetabular coverage and to estimate the degree of femoral anteversion. CANDIDATE 2: CT scans are useful in assessing available bone stock, and the morphology, dimensions and orientation of both the acetabulum and femur. Any leg length discrepancy can be precisely evaluated and allow for design of custom femoral implants. Various measurements include: femoral neck shaft angle anteversion of the femoral neck, medial head offset, position of the isthmus and height. The AP size of the acetabulum as measured by CT is often different from the supero-inferior size evaluated on plain radiographs. Proximal femoral anteversion is calculated by measuring the angle between the posterior bicondylar axis and the mediolateral dimensions of the medullary canal 20 mm above the lesser trochanter. These measurements are useful to know but how are they going to help you to plan surgery?
In the acetabulum following the abnormal anatomy too closely might lead to anterior instability if the cup is overanteverted.
In addition femoral anteversion may be difficult to recognize.
What are the technical difficulties in performing a THA in a DDH patient?
Crowe type II and III hips have a marked superolateral rim deficiency and anterior wall defect. Although it is technically difficult for anatomic placement of the acetabular component the forces on the THA are significantly reduced. Linde et al. found a 42% rate of loosening of cemented Charnley components after a mean of 9 years if the component was positioned outside the true acetabulum compared to 13% if placed inside.62,63
Any other options to deal with deficient superior coverage of the cup?
A small, uncemented cup can be placed in a high hip centre location. Hip instability is increased due to the use of a small femoral head component along with the risk of femoral–pelvic impingement either inflexion or extension.
What do we mean by cotyloplasty?
Mixed results have been reported, but there is a worry that future revisions may be difficult because issues with restoration of bones tock have not been addressed.64
How do you preoperatively plan for DDH surgery?
The degree of anteversion of the acetabulum should be defined as well as the adequacy of bone stock for satisfactory cup fixation and coverage. the preferred method of fixation (cemen t/uncemented) and need for bone graft.
On the femoral side the size of the femoral canal and the need for special or custom implants should be assessed.
The need for femoral shortening should be made preoperatively. The method and amount of femoral shortening need to be worked out beforehand.
Preoperative planning should also include the surgical approach to be used, solutions to deal with the hypoplastic acetabulum and femur, management of LL Dand restoration of abductor function.
What is the effect of anteversion of the femoral stem on THA?65
When there is more than 40° of anteversion, a corrective rotational osteotomy or a modular implant in which the version of the femoral neck can be varied may be necessary.
That’s not really the question I asked.
A large amount of femoral anteversion increases the risk of dislocation.
That’s correct, but not the whole story. You have already partly answered the question earlier on.
I am sorry, I don’t understand.66 Attempting to implant an uncemented stem in a deformed femur may result in a proximal femoral fracture.
How do you correct length inequality in DDH?
With Crowe type III and IV hips, if the cup is placed in the anatomic position femoral shortening is required. If one attempts to fully correct a significant leg length discrepancy a sciatic nerve palsy may occur. If permanent this can be a disabling complication from surgery and which patients are less willing to accept these days. The exact amount of lengthening that results in sciatic nerve palsy is not known. Acute limb lengthening of more than 2–4 cm during arthroplasty is associated with an increased risk of neural injury. Any lengthening more than 4 cm becomes very risky for a sciatic nerve injury and is generally not advised.
DDH stem needs to be used with a straight proximal medial geometry and without a metaphyseal flare.
Advantages of a subtrochanteric shortening osteotomy include preservation of the metaphyseal femoral region (which provides most of the rotational stability of the implant)
How do you reduce the risk of non-union?
Different subtrochanteric osteotomy geometries can be used. A transverse osteotomy is simplest and the resected bone can be used as an onlay graft. Avoiding the use of a cemented stem prevents the risk of the cement interfering with healing of the osteotomy site.
What are the principles of revision hip surgery with DDH?
Two major concerns are deficient acetabular bone stock and the position of the acetabular cup, particularly if the centre of the hip has not been restored during the primary procedure. However, a high hip centre does not correct leg length discrepancy, does not provide good bone stock for revision hip surgery and is associated with early acetabular loosening and a higher rate of dislocation because of ischial impingement.
Figure 3.8 Anteroposterior (AP) radiograph of the pelvis of severe bilateral DDH.
Structured oral examination question 9#
Periprosthetic fracture (PPF) around the hip
This is a 70-year-old man who was admift ed to the orthopaedic ward last night after a fall. He is generally fit and healthy although is on Warfarin for a mitral value replacement. These are his radiographs that were presented at the trauma meeting in the morning ( Figure 3.9a). What do you see?
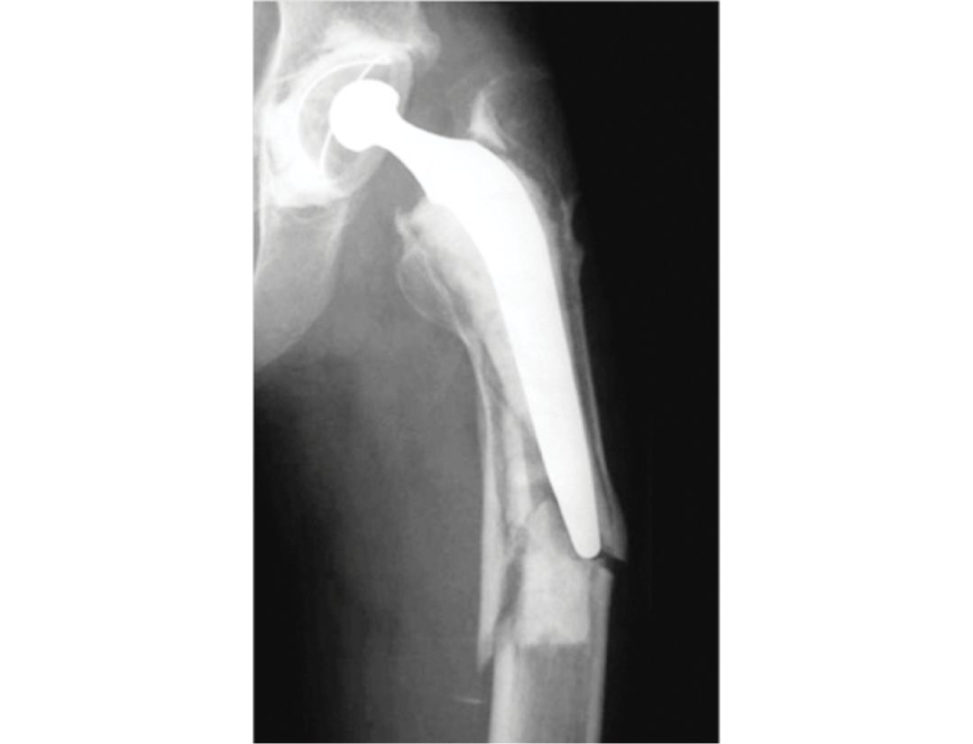
This is an AP radiograph showing a left Vancouver B2 periprosthetic fracture around a Charnley cemented total hip replacement.
What makes you state that this is a Vancouver B2 periprosthetic fracture?
A B2 fracture is around the distal stem or tip with significant communition and a looses tem with adequate bone stock.
Any difficulties with the Vancouver classification ( Figure 3.9b)?
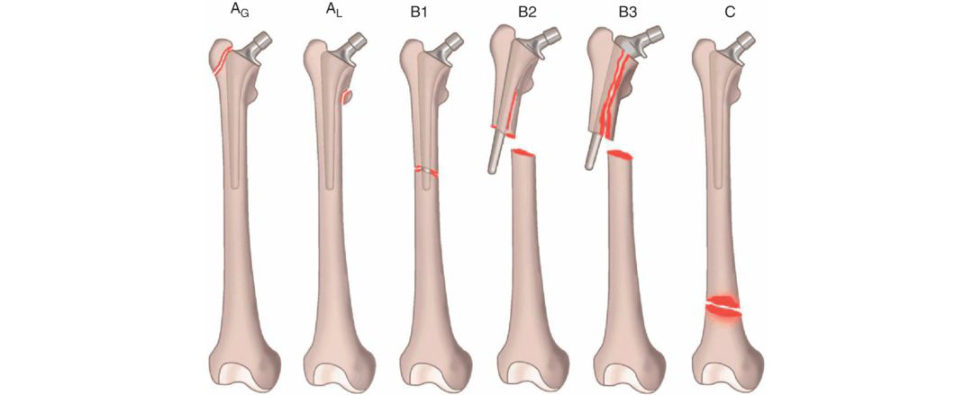
There are some difficulties differentiating between type B1 and type B2 on plain radiographs.
Are you aware of any more recent classification system?
The Vancouver group have recently published their Unified Classification System (UCS) for periprosthetic fractures around a hip or knee arthroplasty in 2014.67 Fractures are categorized A to F. Type A fractures involve the apophysis, e.g. greater trochanter fracture around a THA. Type B fractures involve the ‘bed’ of the implant, e.g. femoral shaft fracture around a stem, and are still graded B1, B2 and B3 as per the original Vancouver classification system.
What advantages does this classification system have over the Vancouver classification system?
The Vancouver classification system was based on the key principles of management of periprosthetic fractures.
there was felt to be a need to expand the Vancouver classification system to include three other types of fracture that may occur in combination or in isolation,
This is a B3 fracture as there is poor bone stock around the stem, which is loose. This patient is a 70-year-old male who had a left THA 20 years ago and had a fall sustaining this PPF. He has had a previous mitral valve replacement and is on warfarin. He is a diet-controlled type 2 diabetic. He is otherwise quite fit, well, is fully active and independent and still drives a car. What will be your management plan?
The review article by Schwarzkopf provides a good treatment algorithm for dealing with periprosthetic fr actures68 (Figure 3.9c). I would also seek advice from other senior colleagues who were experienced hip surgeons or discuss this case in a regional revision hip network. His Warfarin will need to be stopped but he must be covered with an alternative anticoagulant because of his MVR. I would use a posterior approach as this is an extensile approach and provides excellent acetabular and femoral exposure. This is a B3 fracture, which necessitates revision of the femoral stem, and I would bypass the fracture using a long-stem, titanium, modular fluted revision hip such as the ZMR or ARCOS system (which I am familiar with) (Figure 3.9d) in order to get distal fixation and provide rotational and axial stability. For the acetabular component, I would use an uncemented socket (such as a trabecular metal (TM) backed socket) with supplementary screws, but have augments available in case there are significant acetabular bone defects present (Figure 3.9e). A preoperative CT scan of the hip would be useful in helping identify significant acetabular bone defects, although from what I can determine on the radiograph shown to me, there doesn’t appear to be significant bone loss or any protrusio. My bearing surfaces of choice would be a ceramic head (36 mm ideally) with a highly crosslinked lipped polyethylene liner to help minimize the risk of a posterior dislocation.
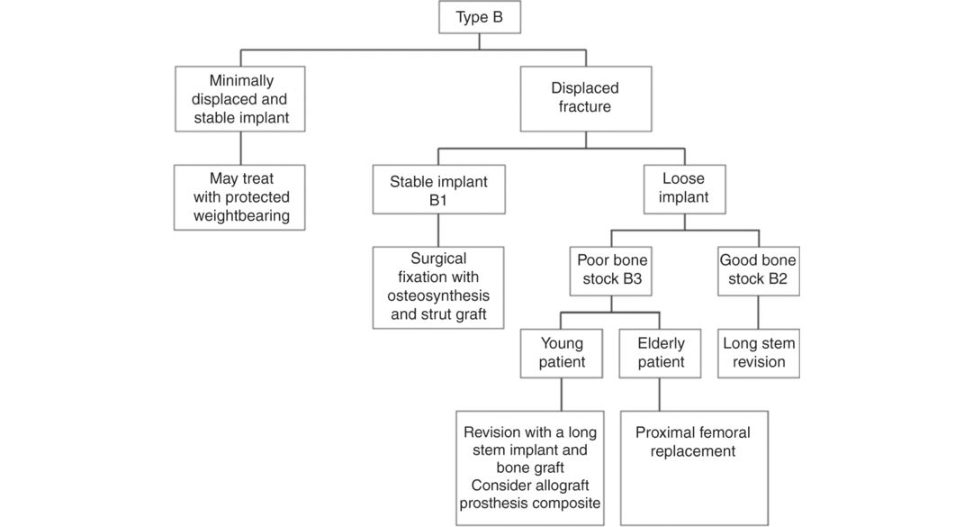
Why not just fix the fracture with a long femoral plate and leave the stem in situ?
The systematic review in the BJJ 2017 by Khan et al.69 from Notingham showed almost 30% reoperation rate compared to around 15% for revision ± ORIF.
Are there any other surgical options a vailable?
The paper by El-Bakoury in 201770 looking at B2 B3 fractures in 28 patients aged 75 over showed a 95% fracture union rate 100% survivorship of the revised hip at a mean 4 years follow-up. with a long cemented femoral stem for situations with extensive femoral bone loss including B2 and 3 periprosthetic fr actures.71
Are there any other options a vailable that you might need to consider if the patient was very frail and the bone quality very poor?
Another potential option would be to do a proximal femoral replacement (PFR). The study from Parvizi’s group72 looking at 21 patients with a B3 PPF showed a good outcome using a PFR.
You perform the operation revising the femoral and acetabular components using an uncemented acetabular socket, a long uncemented femoral fluted titanium stem and a ceramic-on- polyethylene bearing couple. All went well during the operation. Postoperatively, on Day 1, he appeared quite comfortable and had no neurovascular complications. On Day 2, you see him and he has developed a foot drop on the left (operated side. What will you do?
This patient has developed a foot drop secondary to some form of sciatic nerve injury. He was well immediately postoperatively, and this implies that the sciatic nerve must have been intact and working then. What type of anaesthesia was used (spinal/epidural, etc.) although, again, there was no foot drop initially postoperatively.
The patient has noticed that the thigh has swollen significantly and there is quite a lot of bruising and the soft tissues f eel tense.
My concern is that the patient has an evolving large haematoma, and this could be causing a sciatic nerve neuropraxia leading to a foot drop 48 hours after surgery. I would also seek urgent advice from the cardiologists and haematologists as to whether we can stop the warfarin and put the patient on an alternative anticoagulant such as IV heparin or LMWH. An urgent CT angiogram may also help identify any significant bleeding vessels which may be amenable to embolisation.
Figure 3.9a Vancouver B3 periprosthetic fracture left THA .
Figure 3.9b Vancouver classification of PP Far ound the hip.
Figure 3.9c Treatment algorithm B3 PF.

Figure 3.9d ARCOS uncemented revision femoral stem. Grit-blasted, anatomic bow.

Figure 3.9e TM revision shell with augment.
Structured oral examination question 10#
What does the radiograph show (Figure 3.10)?
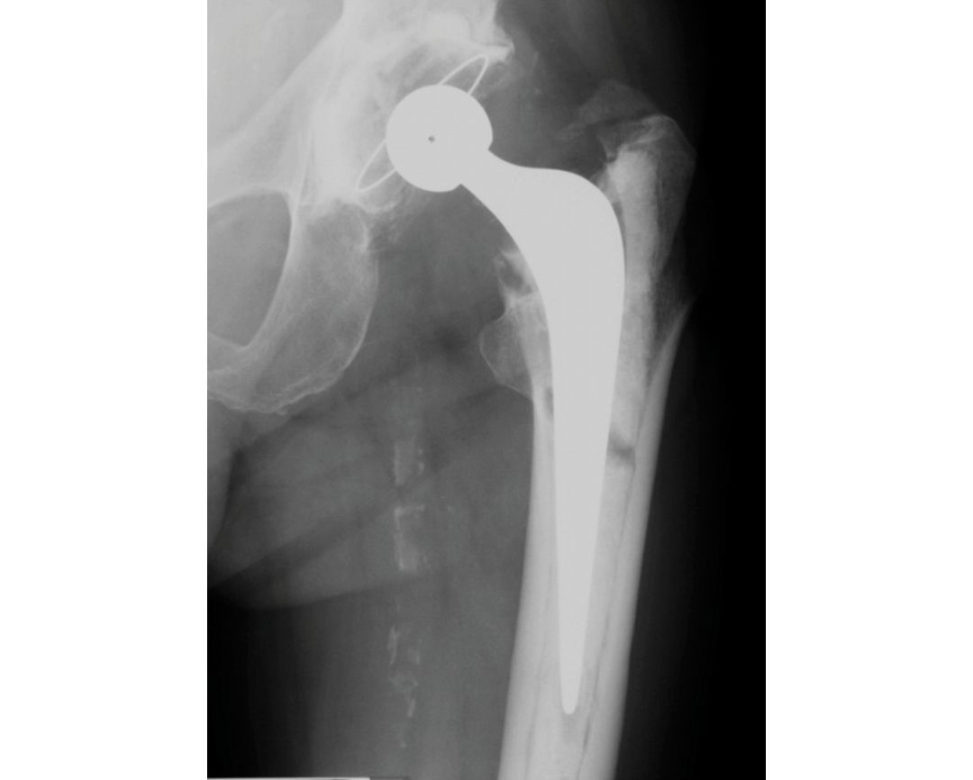
This is an AP radiograph of a cemented Exeter THA. The acetabular cup and stem are well fixed with an adequate cement mantle thickness which is greater than 2 mm.
Anything else?
The stem is in slight varus, but the cup is well aligned with no suggestion of excessive anteversion or retroversion or being too closed or open.
Anything else?
His femoral artery has a large amount of calcification present in its wall.
Anything else?
Not sure.
Look here; what do you think this lucency is?
This is a cement fracture.
What are the reasons for a broken cement fracture?
Cement mantle fractures are worrying as they are associated with early loosening and the need for revision surgery. Studies suggest that the initiating events that result in cement failure are due to stresses experienced at the cement mantle that exceed the fatigue endurance limit of both the stem–cement interface and the cement material itself. It is important to reduce cement stresses so as to minimize the risk of cement debonding and fracture.
how can high cement stresses be avoided?
By the creation of an optimally thick symmetric, and homogeneous cement mantle.
how do we achieve this?
Stresses experienced in the cement mantle have been shown to be highest at the stem tip and secondarily at the proximal–medial cement mantle.
Can you be more specific?73
A proximal–medial cement mantle greater than 10 mm orless than 2 mm in thickness is associated with a significant increase in cement fracture, radiolucent lines at the prosthesis–cement and progressive component loosening when compared to proximal–medial cement mantles that measure 2–5 mm in thickness.74 An asymmetrical distal cement mantle significantly increases the risk of implant failure. Best results for femoral components allow for 2–5 mm proximal medial thickness of cement mantle, less than 2 mm of proximal medial thickness of cancellous bone, a stem that fills more than half the distal part of the meduallary canal and a stem in neutral orientation. Worst results for femoral components occur with a cement mantle thickness >10 mm or in a femur with more than 2 mm proximal medial cancellous bone, those that filled half orless of the medullary canal and those in varus orientation.
Figure 3.10 Anteroposterior (AP) radiograph cemented Exeter hip with broken cement mantle.
What is the optimal cement mantle thickness?
The femoral stems of hips that have a 2–5 mm thick cement mantle in the proximal medial region have a better outcome than stems implanted with a thicker (>10 mm) or thinner (<2 mm) cement mantle.
What about the cement, how can this be improved?
Improvements in the inherent properties of the cement increased strength,
What measures can betaken intra-operativ ely to improve the quality of the cement mantle?
1. Canal preparation Use of correctly sized broaches that allow a mantle of adequate thickness,
Packing of the femoral canal with adrenaline soaked swabs, hypotensive analgesia to reduce bleeding, suction catheter and avoidance of blood/cement occlusions.
2. Cement preparation
Centrifugation or vacuum mixing to minimize pore formation and timing of cement injection to achieve optimal viscosity during insertion improves the cement mantle quality.
Occlusion of the canal using a distal plug,
Have you heard of boneloc bone cement?
This is a bone cement that was withdrawn quite soon after introduction because of unacceptable revision rates with its use.
What is the function of a centraliser?
Femoral stem centralizers were originally designed for double tapered, straight stems. Means the stem is “Non-end bearing”, the void below the stem allows a degree of stem subsidence without directly bearing onto the cement thus preventing cement cracking and deterioration. Stem subsidence into an air filled centralizer leads to low shear stresses, high compressive stresses and almost no tensile stress
What is the ideal cement mantle thickness?
I would aim for a cement mantle thickness greater than 2 mm as any less than this increases the risk of cement mantle fracture.
Have you heard of the French paradox?
No, I am sorry I haven’t.
Int heUK and USA, the first technique aims to produce a complete cement mantle of at least 2 mm in thickness and without ‘windows’. This has been called the French paradox in which implantation of a canal filling femoral component in a line to line manner is associated with a thin cement mantle75. This is Score 8 material not expected for the average Score 6 pass candidate. The discussion could move on to any number of topics related to cement use in arthroplasty surgery depending on how the viva is progressing. Barracks grading of cement.76,77 Generations of cementing technique. Charnley stem design.
Structured oral examination question 11#
A 52-year-old man has been referred to the orthpaedic clinic with a 6-week history of (right)78 hip pain. The pain was unrelated to trauma and was a severe, deep aching groin pain worse at night. The patient has a limp with pain on weight bearing and a positive Trendelenburg sign. These are his radiographs (Figure 3.11a). What do you see?
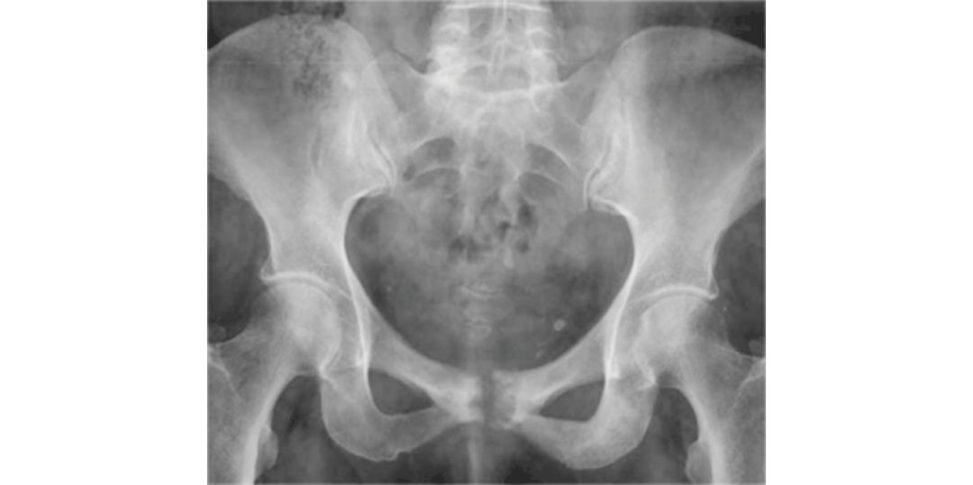
The anteroposterior (AP) pelvis radiograph shows no significant abnormality. 79 OR The anteroposterior (AP) pelvis radiograph reveals diffuse osteopenia of the right femoral neck and head. Do we have a lateral radiograph of the right hip?
That’s all we have got. What further investigations would be appropriate?
I would start by taking a full history and examining the patien t.80
That’s all been done. He has severe hip pain keeping him off work.
I would like to perform bloodtests (FB CUE, bone profile, LFT, cloting , ESR, CRP, PSA and serum electrophoresis). A CT scan is another option that would provide more information about the bone architecture.
This is his bone scan (Figure 3.11b). What does it show?
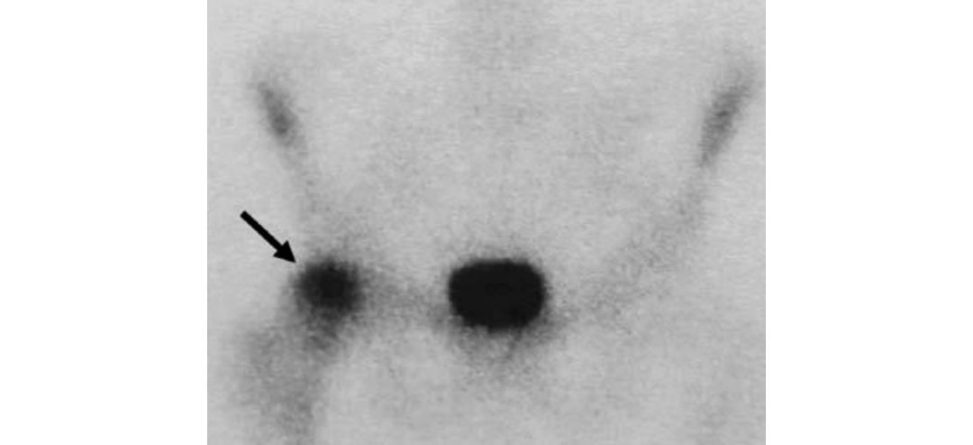
The bone scan shows heterogeneous intense uptake of isotope in the femoral head (mainly anterosuperior) and neck region.
These are his MRI hip images (Figure 3.11c). What do you see?
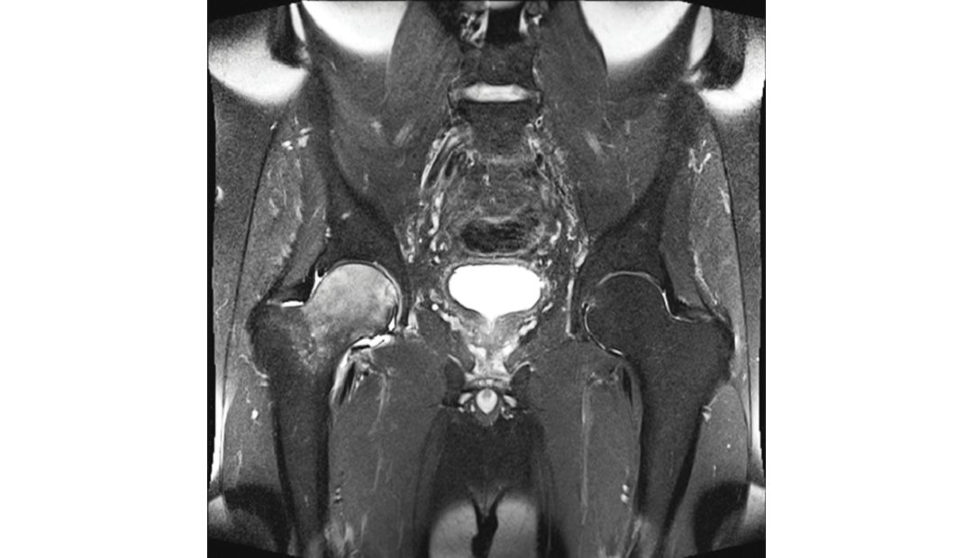
MRI images of the hips demonstrate decreased marrow signal on T1 images of the right hip with striking T2 hyperintensity in the same area.
What is the differential diagnosis?
The differential diagnosis is duet o other conditions that cause bone marrow oedema on MRI that include infection (septic arthritis), osteonecrosis , osteochondromatosis and reflex sympathetic dystrophy. In BMES one would usually find diffuse oedema but no focal defects or subchondral changes on T2 MR IOne would see low-signal intensity on T1-weighted images, high-intensity signal on T2-weighted images and short-tau inversion recovery (STIR) images. The bone scan in BMES is sensitive for early disease typically showing homogeneous increased uptake in the head and neck and sometimes the trochanteric region. In ON the isotope uptake is more localized and on MRI there are corresponding focal lesions in the same area (double line sign and subchondral changes), typically seen in the anterosuperior femoral head.
What other joints are commonly affected?
The hip is the most frequently affected joint (75%), followed by the knee, ankle, foot and tibial shaft.
What are the features of this condition?
The syndrome is characterized by acute disabling pain in the hip and functional disability without a history of previous trauma. Men are more commonly affected than women (3:1). Up to 40% of patients may show involvement of other joints. The ESR may be raised. There is controversy as to whether BMES may represent a very early reversible stage of osteonecrosis.
What is the natural history of this condition?
The disease is usually self-limiting and will resolve over a period of 6–12 months, 81 Patients should be followed-up with an MRI at around 2 months, with the focus on reducing oedema.
What are the treatment options?
rest and physiotherapy to help maintain strength and mobility of the hip. Other options are prostacycline infusion and there is limited evidence for hyperbaric oxygen. a faster recovery than in the conservatively treated group of patients.
Figure 3.11a AP radiograph of pelvis.
Figure 3.11b Nuclear bone scan.
Figure 3.11c The likely diagnosis is bone marrow oedema syndrome (BMES) or idiopathic transient osteoporosis of the hip (ITOH). The main differentiating feature from osteonecrosis is the lack of focal lesions typically seen in osteonecrosis.
Key points
Around 10,000–20,000 new cases of osteonecrosis (ON) are reported each year in the United
States. Bone marrow oedema syndrome (BMES) is a relatively rare disease.
ON and BMES similarly present in young and middle-aged patients with hip or groin pain.
Magnetic resonance imaging (MRI) is the most sensitive and specific diagnostic tool for both ON and BMES.
ON progresses to end-stage arthritis in as many as 80–90% of patients. BMES has an excellent prognosis, typically resolving within 2–9 months.
BMES should be treated non-operativ ely with protected weight-bearing and analgesics.
References
1. Ber bariE, Mabry T, Tsar asG et al. Inflammatory blood … Joint Surg Am. 2010;92(11):2102–2109.
2. This is teaching a candidate not examining them, and is no longer allowed by the ICB.
3. Spangehl MJ, Masri BA, O’Connell JX, et al. Prospective analysis of … . J Bone Joint Surg Am. 1999;81:672–682.
4. Wyatt MC, Beswick AD, Kunutsor SK, Wilson MJ, Whitehouse MR, Blo mAW. The … and meta-analysis. JBJS. 2016;98(12):992–1000.
5. It may be enough just to mention the uncertainties with nuclear imaging or you may have to quantify your answer a bit more fully.
Technetium-99 bone sc ans are sensitive but not specific. A technetium-99m bone sc an identifies areas of increased bone activity through preferential up take of the diphosphonate by metabolically active bone. In the uncomplicated THA, uptake around the lesser trichinae and shaft is usually insignificant by 6 months, but in 10% of cases, uptake may persist at the greater trochanter, prosthesis tip and acetabulum for more than 2 years. The use of leukocyte scans is generally preferred, having a higher sensitivity (88 –92%) and specificity (73–100%), but their usefulness for the diagnosis of infection continues to be debated.
6. This is sometimes referred to as Gustilo ’s classification.
7. Tsukayama DT, Estrada R, Gustilo RB. Infection after total hip arthroplasty. A study of one hundred and six infections. J Bone Joint Surg Am. 1996;78:512–523.
8. This is sometimes referred to as Gustilo ’s classification.
9. McPherson EJ, Woodson CHol tom P, Roid isN, Shufelt C, Patzakis M. Periprosthetic total hip infection. Outcomes using a staging system. Clin Orthop Relat Res. 2002;403:8–15.
10. Lötscher PO Clauss M, Sen diP, Kessler B, Graber P, Zimmerli W. … at a single centre. Bone Joint J. 2017;99(3):330.
11. Grammatopoulos G, Bolduc MEAt kins BL et al. … hip. Bone Joint J. 2017;99(5):614–622.
12. Buchholz HW, Elson RA, Engelbrecht E et al. Management of deep infection of total hip replacement. J Bone Joint Surg [Br]. 1981;63B:342–353.
13. Raut VV, Siney PD, Wroblewski BM. One-stage revision of infected total hip replacements with discharging sinuses. J Bone Joint Surg [Br]. 1994;76B:721–724.
14. With due respect, although Ra utis the first author, I think ‘Wroblewski from Wrighting ton has shown’ is easier to remember.
15. Hanssen AD, Rand JA. Evaluation and treatment of infection a t the site of a total hip or knee arthroplasty. J Bone Joint Surg [Am]. 1998;80A:910–922.
16. StrangeS, Whitehouse MR, Beswick AD et al. One-stage or … controlled trial. Trials. 2016;17(1):90.
17. Taylor GJS, Bannister GC. Infection and interposition between ultraclean air source and wound. J Bone Joint Surg Br. 1993;75:503–504.
18. Madhavan P, Blom A, Karagkevrakis B, Pradeep M, Huma H, … Ann R Coll Surg Engl. 1999;81:262–265.
19. Lidwell OM, Lowbury EJ, Why teW et al. Effect of … study. BMJ. 1982;285:10–14.
20. Occasionally if an examiner doesn’t know what a candidate is discussing they will enquire further. Be careful, however, as there is a very real danger you may irritate the examiners by coming across as a ‘know-all’.
21. Campbell P, Ebramzadeh E, NelsonS, Takamura K, DeS … Orthop Relat Res. 2010;468:2321–2327.
22. Deva nePA, Horne JG, Ashmore AMu timer J, Kim W, Stanley J. … controlled trial. JBJS. 2017;99(20):1703–1714.
23. Ideally, they should have published their resurfacing results in peer-reviewed journals and perform enough cases to justify continuing on with this procedure (GIRFT – geting it right first time).
24. This is an old-style viva as this type of going on background case discussionis no longer allowed.
25. Huo MH, Stockton KG, Mont MA, Parvizi J. What’s new in total hip arthroplasty. J Bone Joint Surg Am. 2010;92(18):2959–2972.
26. Barrack RL, Mulroy RD Jr, Harris WH. Improved cementing … J Bone Joint Surg Br. 1992;74:385–389.
27. Real-life working in the NHS understanding inherent practical difficulties rather than reading facts from a book.
28. Lewthwaite SC, Squires B, Gie GA, Timperley AJ, … Rel Res. 2008;466(2):324–331.
29. Petheram TG, Whitehouse SL, Kazi HA, et al. The Exeter Universal cemented femoral stem at 20 to 25 years: a report of 382 hips. Bone Joint J. 2016;98B:1441–1449.
30. Examiners should not teach candidates in the exam.
31. Know the biochemical differences between ageing and osteoarthritis inc artilag e as your examiners may want candidates to continue answering the question.
32. If you initially miss a subtle AVN spot diagnosis it is difficult to recover the viva past a bare 6 pass, especially if the candidates before and after you spot it without prompting.
33. Take your pick. On the day steroids, but you may be asked about alcohol, smoking, Caisson disease, sickle cell anaemia and transplant recipients, etc.
34. Johnson LC. Histiog enesis of avascular necrosis. Presented at the Conference on Aseptic Necrosis of the Femoral Head, St Louis, 1964.
35. Jaffe WL, Epstein M, Hey manN, Mankin HJ. The effect of cortisone on femoral and humeral heads in rabbits. An experimental study. Clin Orthop Relat Res. 1972;82:221–228.
36. Jones JP Jr. Fat embolism, intravascular coagulation, and osteonecrosis. Clin Orthop Relat Res. 1993;292:294–308.
37. Nishimura T, Matsumoto T, Nishino M, Tomita K. Histopathologic study of veins in steroid treated rabbits. Clin Orthop Relat Res. 1997;334:37–42.
38. Fica tRP. Idiopathic bone necrosis of the femoral head. Early diagnosis and treatment. J Bone Joint Surg (Br). 1985;67(1):3–9.
39. Hungerford DS, Lennox DW. The importance of increased … Clin North Am. 1985;16(4):635–654.
40. Steinberg ME, Hayken GD, Steinberg DR. A quantitative system for staging avascular necrosis. J Bone Joint Surg (Br). 1995;77:34–41. (Level 2/3 evidence.)
41. McKee MD, Waddell JP, Kudo PA, Schemitsch EH Richards … Canadian Med Assoc J. 2001;164:205–206.
42. Gaskill TR, Urbaniak JR, Aldridge JM 3rd. Free … Joint Surg Am. 2009;91(8):1861–1867.
43. Standard protocol is that Gaskill should be mentioned as the first author when quoting papers. There were 215 complications (a 16.9% rate) at the time off ollow-up, at an average of 8.3 years, after the 1270 procedures. Quote papers and results but be sensible about it.
44. Sometimes you will getaway with this type of general statement regarding results; other times the examiners will press you.
45. Mont MA, Einhorn TA, Sponseller PD, Hungerford DS. The … J Bone Joint Surg Br. 1998;80:56–62.
46. Sugi okaY, Hotokebuchi T, Tsutsui H. Transtrochanteric … results. Clin Orthop. 1992;277:111–120.
47. Jarrett CA, Ranawat A, Bruzzone M, Yossef B, … Joint Surg Am. 2009;91:1344–1349.
48. Less risk of viva meltdown.
49. Lewis POl sen O, Mckee M, Waddell J, Schemitsch E. Total Hip … E poster content, 2–5 June 2010, Madrid, Spain.
50. Schmalzreid TP, Jasty M, Harris WH. Periprosthetic … Bone Joint Surg [Am]. 1992;74A:849–863.
51. Tsao AK, Jones LC, Lewallen DC. What patient and surgical factors contribute to implant wear and osteolysis in total joint arthroplasty? J Am Acad Orthop Surg. 2008;16:S7–13.
52. For ease of learning and memorizing we have provided the information int able form. If the radiograph demonstrates amal aligned THA (cup open or stem in varus, etc.) tell this to the examiners as a probable cause of accelerated wear and then followup with other surgeon-related factors.
53. Ramage SC, Urban NH, Jiranek WA, Maift A, Beckman … Joint Surg Am. 2007;89(4):841–848.
54. Parvizi J, Schall DM, Lewallen DG, Sim FH. Outcome of uncemented hip arthroplasty components inpatients with Paget’s disease. Clin Orthop Relat Res. 2002;403:127–134.
55. Lusty PJ, Walter WL, Walter WK, Zicat B. Cementless hip arthroplasty in Paget’s disease at mediumterm follow-up (average of 6.7 years). J Arthroplasty. 2007;22(5):692–696.
56. Alexakis PG, Brown BA, Howl WM. Porous hip replacement in Paget’s disease: an 8–2/3-year followup. Clin Orthop Relat Res. 1998;350:138–142.
57. Ludkowski P, Wilson-MacDonald J. Total arthroplasty in Paget’s disease of the hip: a clinical review and review of the literature. Clin Orthop Relat Res. 1990;255:160–167.
58. It is not unreasonable to mention the patient’s age and when the radiograph was taken to the examiners with the first radiograph shown in the viva exam. An y is more irritating and wastes time.
59. The score is 6–7, as the candidate didn’t classify the left side correctly. If the candidate had correctly identified a Hart ofilakidis I hip it would be more towards the 7–8 mark.
60. Examiners aren’t allowed to teach. See first edition viva book.
61. This is probably one of the pre-agreed oral viva questions that the examiners need to ask.
62. Lin deF, Jensen J, Pilgaard S. Charnley arthroplasty in osteoarthritis secondary to congenital dislocation or subluxation of the hip . Clin Orthop. 1988;227:164–171.
63. The candidate’s answer isn’t particularly well structured.
64. Candidates can either volunteer this extra information or perhap s wait for the examiners to ask it!
65. Technically, the candidate hasn’t really answered the question.
66. The candidate is not quite appreciating what the examiner wants and has just gone a bit blank in the stress of the moment.
67. Duncan C. The Unified Classification System (UCS): improving our understanding of periprosthetic fractures. Bone Joint J. 2014;96B:713–716.
68. Schwarzkopf R, Oni JK, Marwin SE. Total hip arthroplasty periprosthetic femoral fractures: a review of classification and current treatment. Bull Hosp Jt Dis. 2013;71(1):68–78.
69. Khan T, Grindlay D, Ollivere BJ, Scammell BE, … Bone Joint J. 2017;4(Suppl B):17–25.
70. El-Bakoury AHo sny H, Williams M, Keenan J, Yarlagadda R. … and older. J Arthroplasty. 2017;32(2):541–545.
71. Tsiridis E, Amin MS, Charity J, Narvani AA, Timperley J, Gie GA. … report. Acta Orthop Belg. 2007;73:332–338.
72. Klein GR, Parvizi J, Rapuri V, et al. Proximal femoral replacement for the treatment of periprosthetic fractures. J Bone Joint Surg Am. 2005;87(8):1777–1781.
73. Dennis DA, Lynch CB. Optimizing the femoral component cement mantle in total hip arthroplasty. Orthopedics. 2005;28(8):S867–871.
74. Ebramzadeh E, Sarmiento A, McKellop HA, et al. The cement mantle in total hip arthroplasty: analysis of long-term radiographic results. J Bone Joint Surg Am. 1994;76:77–87.
75. El Masri F, et al. Is the so-called ‘French paradox’a reality? Bone Joint J. 2010;92(3):342–348.
76. Barrack RL, Mulroy R, Harris WH. Improved cementing … Joint J. 1992;74(3):385–389.
77. Banaszkiewicz PA. Improved cementing techniques and femoral component … in Orthopaedics. London: Springer; 2014:31–34.
78. The examiners may not specify a particular side, which will make the radiograph slightly more difficult to interpret.
79. Although the radiograph doesn’t show anything significant, try to avoid the terms ‘there is no obvious abnormality of bone’ or ‘there may be perhaps slightly more opacity in the right femoral head’.
Be definite in your answer.
80. You have to play safe and default to this standard reply for your first couple of viva questions, but it can start to irritate the examiners by your fitih viva question.
81. Turner DA, Templeton AC, Selzer PM, Rosenberg AG, … Radiology. 1989;171(1):135–140.