Chapter 11 Lower limb trauma II
Will Eardley, Mohammed Al-Maiyah and Patrick Williams
Introduction#
Alexander Suvorov would have done well in the trauma viva section of the FRCS Tr & Orth. Two citations atiribut ed to him underpin the approach to the exam: Train hard, fight easy and He who is afraid is half beaten. Approach and strategy is everything and this comes from a combination of practice and knowledge acquisition.
What they don’t hear, they can’t score you on. The examiners want a safe and sensible approach of the generalist, not eminence-based pracft ce of someone you may work for.
Treat each question as a chess g ame that is going to last five minutes.
Structured oral examination question 1#
A 35-year-old male lost control on a bend and came off his motorcycle yesterday; he has
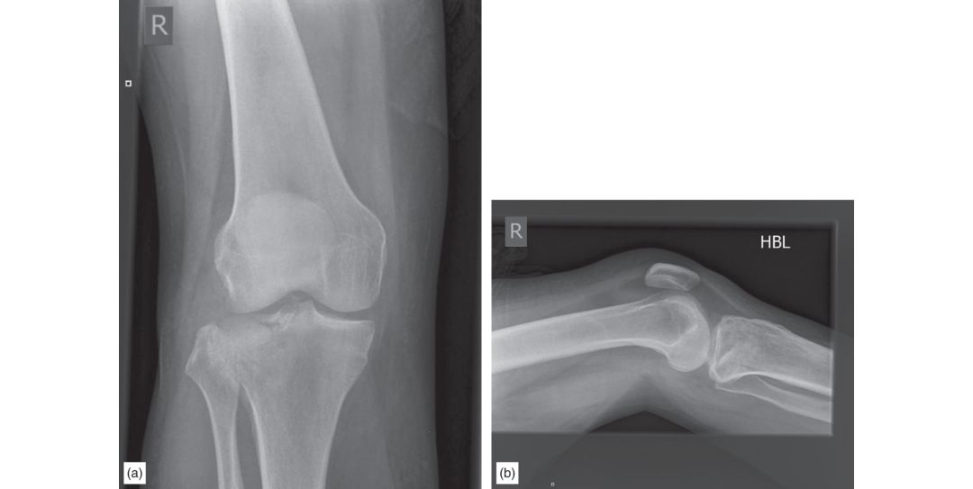
Figure 11.1a and 11.1b Anteroposterior (AP) and lateral radiographs of right knee demonstrating tibial plateau fracture.
Minute 1
What do you see? Here the next minute belongs to the candidate and you can take it whichever way you want to. However, there are essentials to be covered. In the first 30 seconds you are expected to comment on the following: Site of radiograph and its suitability – also always ask for two views if only one is given. Adult or paediatric skeleton. General features: fracture of the proximal tibia with depression of the lateral tibial plateau. In the next 30 seconds the candidate is expected to comment (without any prompt from the examiner) on the exact nature of the injury, such as Schatzker III fracture with more than 10 mm depression in the articular surfaces, comminuted, concern about the fracture going through the tibial spines and whether the medial side is intact. The candidate can end these 30 seconds by saying they will assess the soft -tissue envelope, the distal lower limb (palpating the distal pulses and providing a documented assessment of the named nerve function), ensure that a full tertiary survey has been performed and then plan further management of the fracture.
Minute 2
How would you investigate further?
A computed tomography (CT) scan to evaluate the fracture pattern as this helps to plan surgery, particularly with regard to approaches to the fracture and the philosophy of implant choice. (The examiner is then likely to produce slices of the CT.) Don’t get carried away at this point. It’s vital, in order to score points, that you comment on this constructively, i.e. how what you see may influence your approach/fixation. You should be at this stage by 90 seconds. Punctuation of the viva is important and helps you stay calm. Having done all this, take a breath and pause. Do NOT plough straight in with your plate of choice.
What are the treatment options?
[Take the next 30 seconds to describe operative and non-operativ e options in the generality. This must be based on the particular patient (recent alignment of consenting processes) and it is critical here that the information will be given to the patient clearly regarding the impact of differing treatment strategies on that particular patient with that particular injury.] Non-operativ e management would not normally be suitable in this patient This is due to the articular segment depression, which will impact on overall stability of the joint
Minute 3
At the two minutes mark you should have commift ed yourself to offering the patient operative intervention. Stick with the principles.
The principle of treatment is to restore the articular surface, stabilize and hold the fracture in such a fashion to allow early mobilization.
The options of surgical treatment include director indirect reduction, percutaneous or open fixation augmented with plate osteosynthesis or external fixation. Suggest at that stage you will do assessment under X-ray control for a ligamentous stability and if needed an arthroscopic assessment.
Minute 4 (yes, you are still going ...)
The examiner can then take the viva along two routes.
What is abut iress plate?
It is one of the modes of plate uses, along with compression, bridging and tension band, for example.
What is the role of knee arthroscopy?
(Be clear to state that pressure pumps are not to be used in order to avoid iatrogenic compartment syndrome due to extravasation of fluid, as well as the f act that you will use a bladder syringe through the arthroscopy cannula to washout the haemarthrosis before viewing the joint – this gives the examiner the impression that you have done the procedure before.)
What surgical approach will you use?
Anterolateral approach with the skin incision being longitudinal and if needed, a reverse L- shaped incision inside. The incision is curved anteriorly over Gerdy’s tubercle and is extended distally, 1 cm lateral
What about bone graft?
However, this procedure involves making a separate incision over the iliac crest to obtain the graft, which may result insignificant postoperative pain, neuro/vascular injury, haematoma, infection fractures and cosmetic concerns.
Anything else you can use?
It is thought to reduce the risk of subsidence of the fracture fragments occurring by maintaining articular congruency until the fracture heals.
What does the literature say?
There is some evidence to support the use of bone graft substitutes to fill fracture voids, but a lack of level I evidence.
Minute 5
Talk about graduated range of motion, protected weight-bearing and the concept that true non-weight-bearing is very difficult for patients and protected weight-bearing ‘as able’ depending on patient compliance is what is actually going to happen.
Stay calm. Assess the patient clinically, radiologically (including CT), rule out infection, soft -tissue problems, patient compliance and then proceed from the start, take out metalwork, align the articular surface, stabilize the fracture and mobilize again, often as a staged process.
What will you tell the patient about long-term outcome?
Not all patients however, are symptomatic. Wasserstein et al. reported that regardless of operative fixation, sustaining a tibial plateau fracture requiring surgery increases the likelihood of TK Aby 5.3 times. 1 Older patients and those with a more significant fracture were more likely to need TKA.
Evidence base
A 2015 Cochrane review commented that there was insufficient evidence to recommend a specific method of fixation or bone defect replacement technique. A review by the
EFORT group in 2016 agreed with the above, but also commented on the use of TK Ain older patients.
McNamara IR, Smith TO, Shepherd KL, et al. Surgical fixation methods for tibial plateau fractures.
Cochrane Database Syst Rev. 2015;9:CD009679.
Prat-Fabregat S, Camacho-Carrasco P. Treatment strategy for tibial plateau fractures: an update. EFORT
Open Rev. 2016;1(5):225–232.
Risk of total knee arthroplasty after operatively treated tibial plateau fracture: a matched-population-based cohort study.
2014;96(2):144–150.
Scoft CE Davids onE, MacDonald DJ, White TOKe ating JF. Bone Joint J. 2015;97(4):532–538.
Structured oral examination question 2#
A 79-year-old woman fell in her garden. She is generally quite independent, has a history of angina which
Minute 1
Please comment on the radiograph (Figure 11.2).
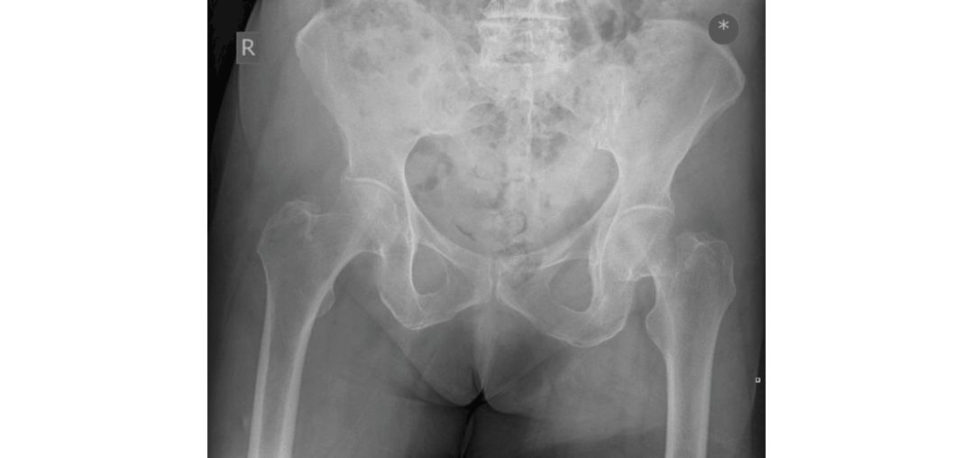
Figure 11.2 Anteroposterior (AP) pelvis radiograph demonstrating intracapsular fractured left neck of femur.
In the first 30 seconds you are expected to comment on the site of radiograph, its acceptability and the general findings it demonstrates.
The pelvic radiograph shows a displaced left-sided intracapsular neck of femur fracture in the presence
How will you manage this patient?
I would like to assess the whole patient The degree of mobility prior to injury, comorbidities, ‘red flag’ features for any pathological lesions, drug
Minutes 2 and 3
She has well-controlled angina and is otherwise independent.
My choice is THA using a well-proven cemented prosthesis provided the patient meets the NICE guidelines of being fit for anaesthesia, not cognitively impaired and able to mobilize independently pre-injury.1
Why do you prefer THA rather than hemiarthroplasty? It is more expensive!
Recent NICE guidelines endorse such practice in a selected population, which includes mentally alert patients with good pre-injury mobility levels and who are relatively healthy. This patient ticks all the criteria and will benefit from THA. My practice ist o use a relatively larger head, such as 32 mm or 36 mm, to counter the increased risk of hip dislocation. 2,3 Surgical technique should focus on the correct orientation of components, good soft -tissue balancing , restoration of hip offset and equalization of leg lengths. It also includes addressing any underlying bone abnormalities such as osteoporosis, risk assessment for falls and nutritional deficiency. With regards to price and impact on quality of life, THA is considered more cost-effectiv e.3
You keep mentioning NICE guidelines. What is a NICE guideline?
NICE clinical guidelines are recommendations for the care of individuals in specific clinical conditions or circumstances within the NHS.
So why do we use them?
NICE guidelines can be used to develop standards to assess the clinical practice of health professionals and can also be
What’s the problem with using NICE guidelines?
NICE guidelines do not replace a surgeon’s knowledge and skills, they are only guidelines to help a surgeon make an informed decision.
Minute 4
She arrives at 1800 to your ward. When will you undertake the surgery?
The surgery should be undertaken as soon as safely possible and ideally within 36 hours.4 It should not be rushed in the middle of the night; however, if the patient is fit for anaesthesia then the aim is for surgery on the next morning list with all the theatre staff, kit and consultant cover available.
Minute 5
This includes a higher risk of dislocation (7% vs. 1%), leg length discrepancy, cement pressurization side effects such as cement reaction, higher medical complication rate
(32% vs. 6%) and higher mortality rate. Length of hospital stay is also increased.
Evidence base
This topic is so common that, yes, you do need to know some numbers:
1. CG 124 – Hip fracture: management (1.6.3).
2. Injury volume 47, issue 10, October 2016, pp. 2144–2148: 7% dislocation rate compared to 1%.
3. NIHR HTA volume 15, issue 36: significant increased risk of early dislocation a t 1 year (RR 3.98) for
THA compared to HA and statistically significant increased risk (RR 2.4) for all follow-up periods up to
13 years.
4. NIHR HTA volume 15, issue 35: cost per QALY $1960 for THA.
5. Geriatr Orthop Surg Rehabil. 2014;5(3):138–140.
Structured oral examination question 3#
Minutes 1 and 2
This 49-year-old lady fellon some steps. Her left foot is very painful, bruised, swollen and she can’t weight-bear. The junior doctor went to see her in the Emergency Department, but he is not sure what the problem is, what do you think? (Figure 11.3.)
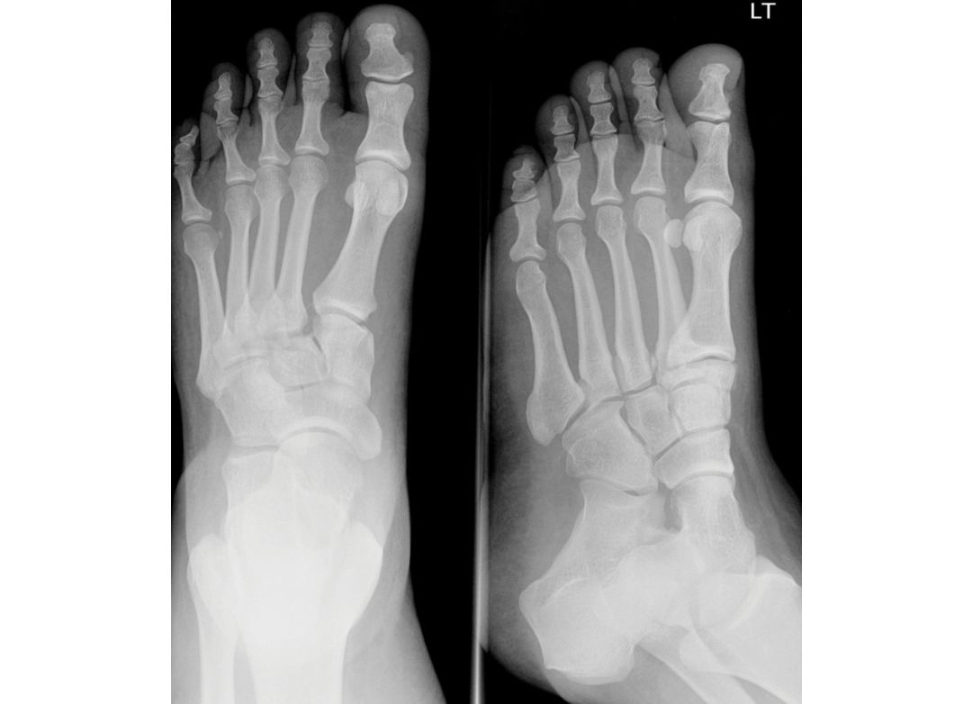
These are anteroposterior (AP) and oblique radiographs of the left foot. There is a diastasis between the base of the first and second metatarsals; features suggestive of ‘Lisfranc’ tarsometatarsal fracture dislocation. This is an avulsion fracture and could be from the insertion of the Lis franc ligament (medial cuneiform– second metatarsal) into the base of the second metatarsal (‘fleck sign’).
OK, how will you manage this patient?
I will carryout an examination of the footnoting: Soft tissues welling, pain and ecchymosis. Pain on passive abduction/pr onation. Compartment syndrome can be a feature of these injuries and I will include this in my differential. Following assessment, my initial management includes analgesia, elevation and splinting using a below-knee backslab. On admission to hospital I’ll arrange for regular, serial examination to detect compartment syndrome.
What would you do if the radiographs were inconclusive in diagnosing this condition?
MRI scan is useful in allowing direct visualization of the Lisfranc ligament itself, but I would discuss the MRI request with an experience musculoskeletal radiologist beforehand as images can sometimes be difficult to interpret.
Figure 11.3 Anteroposterior (AP) and oblique radiographs, left foot.
Minute 3
How do you treat Lisfranc tarsometatarsal fracture dislocation?
This depends on the severity of injury to both the bones and soft tissues and the degree of displacement of the fracture. There is a role for non-operativ e treatment for an undisplaced stable injury with a cast for 6 weeks with non-weight-bearing and regular clinical and radiological review. However, in the presence of subluxation or dislocation, then accurate reduction ands table fixation is essential. In this case, I would consider open reduction and internal fixation with screws and maybe plating , as required. I would use a dual dorsal incision approach.
Minute 4
What prognosis will you give this patient?
Post-traumatic osteoarthritis occurs in over 50% of cases, even if operatively treated with open reduction and internal fixation Residual pain and a stiff foot is a not uncommon complication of this injury Early identification of thein jury is key – up to 20% of tarsometatarsal joint complex injuries are missed on initial examination.
Minute 5
If this patient develops compartment syndrome, then how would you manage it?
In the BOAST guidelines regarding compartment syndrome, it is stated that there is no clear consensus on optimum management. For high-energy injuries such as following motorcycle trauma or in the intubated patient, my threshold to intervene would be even lower.
How would you manage the injury if the soft tissues around the foot were very swollen with significant disruption of the bony anatomy but no compartment syndrome?
In this situation a prompt reduction of these injuries improves the alignment and relieves the pressure to the surrounding soft tissues, a voids the potential for skin necrosis, helps avert the development of a compartment syndrome, prevents compromise to the neurovascular structures and allows a safe waiting period to be undertaken until
So, what are you going to do?
I would use an external fixator, applied to one or both sides of the foot to reduce
Evidence base
The main area of controversy around Lisfranc injuries is whether to treat them with ORIF or ORIF with primary arthrodesis. There was no difference between the groups in terms of overall complication rates or PROMs data. ORIF has shifted more towards using bridging plates rather than cortical lag screw fixation and
K-wires. For further evidence base look through the review article by M. Clare.
Does open reduction and internal fixation versus primary arthrodesis improve patient outcomes for Lisfranc trauma?
2016;474(6):1445–1452.
Clare MP. Lisfranc injuries. Curr Rev Musculoskel Med. 2017;10(1):81–85.
Structured oral examination question 4#
A 33-year-old roofer fell 20 feet when scaffolding collapsed under him, landing on his feet and sustaining an isolated injury to his heel.
Minute 1
This is a radiograph of his foot and ankle (Figure 11.4a). What are your thoughts?
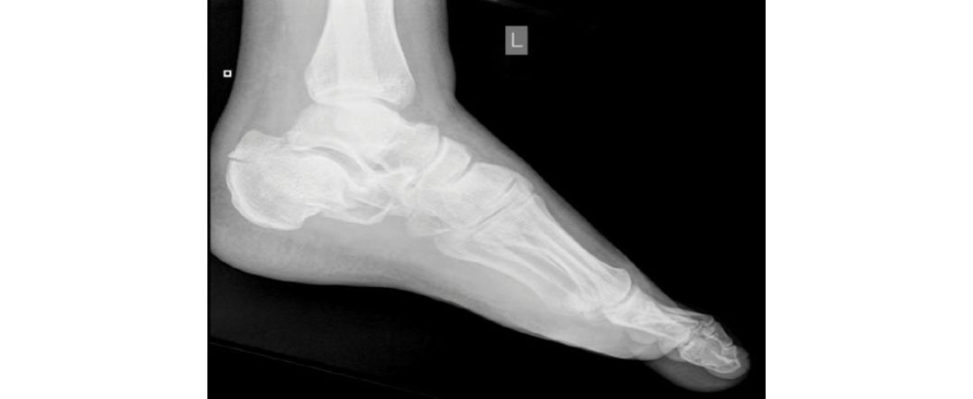
Regardless of the hindfoot trauma, the patient has had a significant fall, so initially I would assess the pa tientas a whole following ATLS protocol and screen for potential associated injuries. Vertebral compression fractures (10–15% of cases), fracture of proximal femur, knee (tibial plateau), ankle (pilon fractures) and other foot injures (contralateral calcaneum) must be looked for and excluded.
Figure 11.4a Radiograph left lateral foot.
Minute 2
Assume that there is no other injury. How would you manage this closed calcaneal fracture?
My management plan can be broken down into initial resuscitation followed by further investigation and planning for definitive treatment. Initial management includes analgesia, splinting , foot elevation and monitoring for compartment syndrome of the foot. I would organize a CT scan to assess the fracture personality and plan definitive treatment.
This is the CT scan you requested (Figure 11.4b), what can you see and what would you do next?
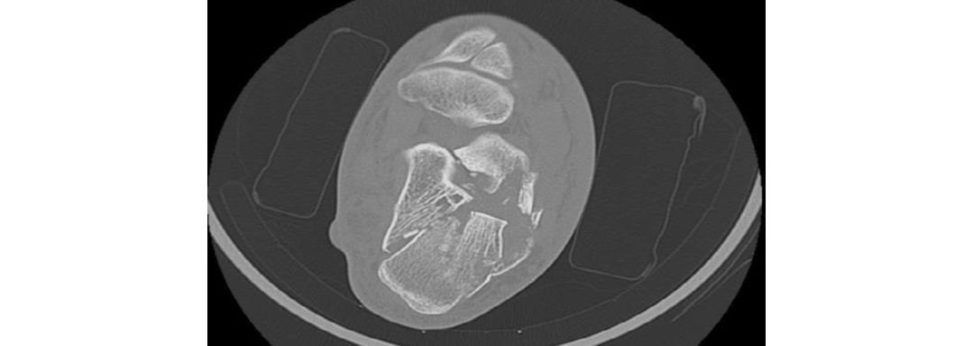
This CT scan axial section demonstrates shortening, varus deformity and considerable comminution. It also shows considerable heel widening.
Do you know any classification systems for calcaneal fractures?
The Sanders classification is a C T classification based on the number of articular fragments seen on a coronal view at the widest point of the posterior facet (Figure 11.4c). Type 1: Undisplaced posterior facet (regardless of number of fracture lines). Types 2, 3 and 4 are displaced fractures. Type 2: One fracture line (two-part intra-articular fracture). Divided into three subgroups on the basis of fracture line localization. Type 3: Two fracture lines in the posterior facet (three-part intra-articular fracture). Type 4: Comminuted fracture with more than three fracture lines in the posterior facet (four or more fragments).
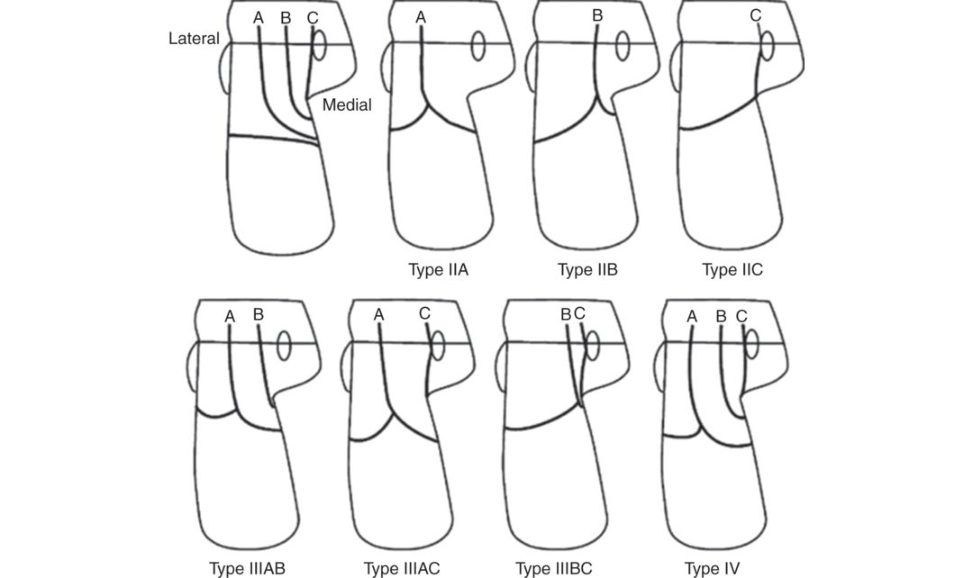
Figure 11.4b CT scan axial view left foot demonstrating calcaneal fracture.
Figure 11.4c Saunders classification of calcaneal fractures.
Minute 3
Following discussion with the patient you have decided to proceed with internal fixation. What are the aims/goals of surgery?
The aims of surgery are restoration of articular congruity while restoring calcaneal
How will you fix the fracture?
I would take full informed consent, in particular concentrating on the risks and benefits of both operative and non-operativ e management. The patient will be undergeneral anaesthesia with prophylactic antibiotics, tourniquet and in the lateral decubitus position with fluoroscopy control. I would use an L-shaped lateral incision halfway between fibula and Achilles tendon avoiding damage to the sural nerve. I would employ full-thickness flaps by taking the incision down to the bone and use bent K-wires as retractors. Postoperatively the patient would mobilize non-weight-bearing for 6 weeks followed by a further 6 weeks of partial w eight-bearing.
What are the complications from surgery?
osteomyelitis, increased heel width, sural nerve injury, persistent heel pain, scar hypersensitivity , tarsal tunnel syndrome and CRPS.
If the wound got infected, how would you deal with it?
I would want to prevent direct extension to bone causing osteomyelitis. I would attempt to keep in place the plate and screws but would remove the metalwork if the infection was not setiling. Occasionally amputation may be needed.
The patient complains of pain.
There are many causes of pain which include subtalar incongruity, penetration of screws into the subtalar joint or arthritis Lateral pain may be caused by lateral
What prognosis will you give for this patient?
There is about a 40% chance the patient will have long-term chronic pain after a significant intra-articular fracture.
Evidence base
Be careful. Treatment of calcaneum fracture is still a controversial issue and atir acts a lot of debate.
randomized control trial which demonstrated no difference inpatient reported outcomes between operative and non-operativ e management of intra-articular calcaneal fractures.
However, it is important to note that patient selection was based on the idea that patients could be managed by either method.
Another key paper is Buckle yet al.3 In this multic entre Canadian trial over 300 patients with displaced calcaneal fractures were evaluated comparing operative vs. non-operativ e treatment.
When they looked at subgroups of patients they found that those receiving workers compensation had a
Were not receiving workers’ compensation.
Were less than 29 years old.
Had a less severely displaced fracture.
Had a light workload.
Had an anatomic reduction.
In a later study, they noted that the overall cost of care of patients was less with surgical care than non-surgical management due to the need for additional
Structured oral examination question 5#
A 21-year-old motorcyclist is involved in a road traffic accident. He is fully conscious, alert and following a global
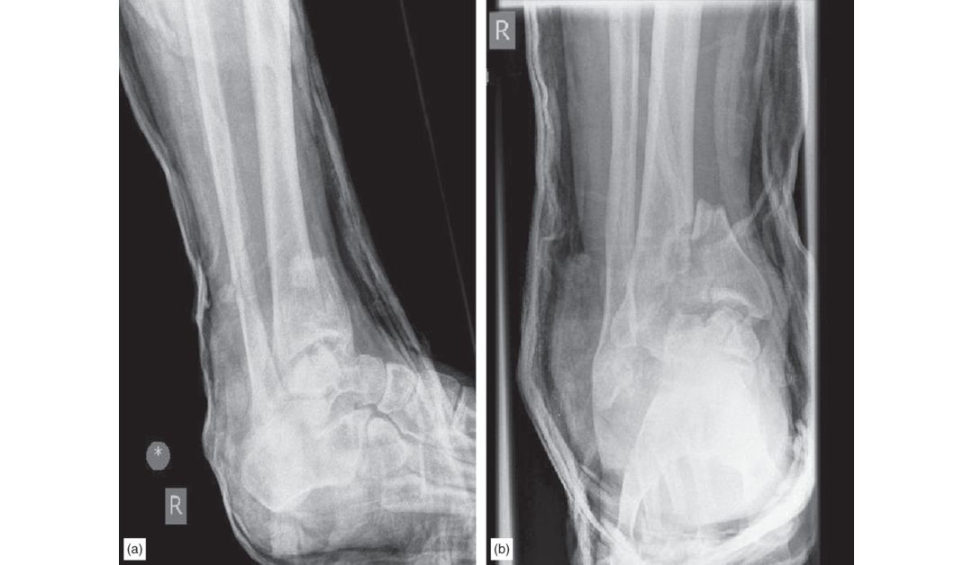
Figure 11.5a and 11.5b Anteroposterior (AP) and lateral radiographs, right lower leg.
Minute 1
Tell me how you would manage this injury.
This is a complex intra-articular multi fragmentary fracture occurring as a result of high-energy trauma. I would enquire about smoking, alcohol consumption, a history of diabetes or peripheral vascular disease, etc. which are important risk factors for soft tissue (and bone) healing. Examination would particularly assess the s tate of the soft -tissue envelope looking for any skin damage, contusion and fracture blisters. I would obtain radiographs of the post splinted leg to check for adequacy of reduction and commence serial assessment for compartment syndrome. Isolated closed injury is coded language to say the examiners just want you to focus on the management of this fracture. No need to mention A TLS. Ruedi and Allgower have classified these injuries into three types: Type 1 Non-displaced fracture cleavage of ankle joint. Type 2 Displaced fracture with minimal impaction or comminution. Type 3 Explosive fracture with significant articular comminution and metaphyseal impaction.
How does this classification system help you?
The Ruedi–Allgower classification system is based on the severity of comminution and
Minute 2
My principle of managing this case is: ‘span–scan–plan’. I would prefer a staged management approach for this fracture rather than going for early ORIF. I would consider early involvement of the plastic surgeons if the soft -tissue envelope was very badly compromised and especially so if the fracture was open. Span: I will placean external fixator in order to reduce and hold the fracture. This will also allow us to arrange timely definitive surgery. Scan: Following initial stabilization, computed tomography scanning will provide more details of the fracture type and pattern. The sc an usually influences the surgical approach chosen for definitive fixation. Plan: using the CT scan I can then plan the definitive treatment in detail; approach, how to fix fragments, what implant to use, timing of surgery, taking consent from the patient and ensuring all equipment, staff and company representatives are available.
Minute 3
When are you going to fix this fracture?
This is a serious and challenging injury to manage. The soft -tissue envelope needs to be resuscitated until it is in areason able condition (this may take up to 10–14 days to setile).
How are you going to fix this fracture?
The principles of fixation of an intra articular fracture are anatomical reduction, interfragmentary compression and absolute stability at the fracture site to allow early mobilization. The approach would be tailored dependent on fracture configuration as corroborated by CT scan prior to and with fluoroscopy during surgery. Looking at the fractures in the radiographs provided, I would favour an anterolateral approach that will allow me to reduce the pilon fracture, and approach the fibula as well as the talus. I would aim for anatomical reduction of the pilon fracture under direct vision and stabilize it with an anterolateral plate and then address the fibula and talus on their own merits. The fracture of the talus may well necessitate extending the approach and a release of the ATFL through a subperiosteal approach.
Anything else?
Sorry?
Anything else about the fracture pattern?
For score 7/8 candidates. There are three classic articular components of a pilon fracture that can be identified on axial CT scan.
How would you perform an anterolateral approach to the ankle?
The patient should be supine with antibiotics given and a thigh tourniquet applied. Because the anterior compartment muscles arise from the anterior fibula, the incision is usually not extended more than 7 cm above the ankle joint. Care is taken not to damage the superficial peroneal nerve which lies directly beneath the skin. This nerve crosses the surgical incision proximal to the ankle joint. It should be identified, mobilized, and protected throughout the surgical procedure. The fascia over the anterior compartment of the distal tibia is then incised sharply , beneath the superficial peroneal nerve. Distally, the extensor retinaculum is incised, and the anterior compartment tendons are all retracted medially. For score 8 candidates:
How will you fix the fragments?
The articular surface is visualized, and the impacted fragments reduced under direct vision. Occasionally if fracture reduction is difficult a distractor can be used to aid fixation. A locking plate is then applied to the distal tibia.
Any other methods?
A circular frame with limited minimally invasive internal fixation is a possible option, but I have no experience with this method of fixation.
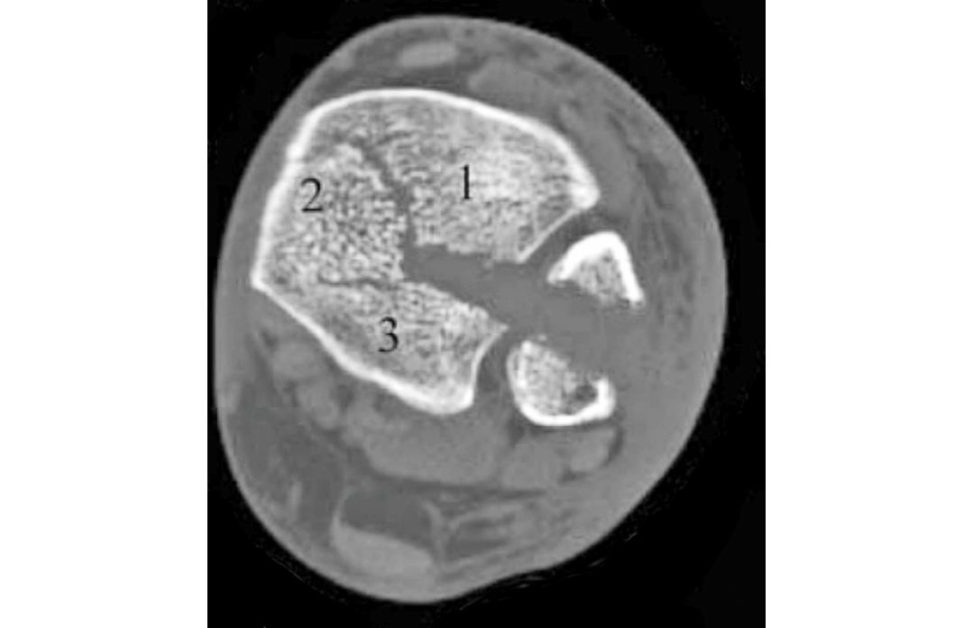
Figure 11.5c Classic articular components of a pilon fracture.
Minutes 4–5
How would you counsel the patient and their family regarding the outcome of pilon fracture?
These injuries represent a high-energy axial insult to the lower limb that leads to severe joint comminution, impaction and a large zone of injury. Delayed union, non-union, infected non-union and malunion can occur. Post-traumatic osteoarthritis may require arthrodesis or arthroplasty.
What is Hawkins’ sign, is it a good or bad sign?
The Hawkins’ sign is a good indicator of talus vascularity following fracture – it is therefore a good sign. It indicates that healing will occur without avascular necrosis.
Evidence base
The evidence base here is fairly disparate with no major RCTs. The general consensus is to use the ‘span–scan–plan’ approach.
Structured oral examination question 6#
A 50-year-old lady is a front seat passenger involved in a head-on road traffic collision. In the Emergency
Department she is diagnosed with dislocation of her native right hip.
Minute 1
What will be your initial management?
A native hip dislocation is a marker of a high-energy injury and I would assess the patient along ATLS principles utilizing an ABCDE approach. I would clinically examine her lower limbs looking at alignment, position and neurovascular status in particular that of the sciatic nerve.
Any clue as to whether it is posterior or anterior clinically?
With a posterior dislocation the leg would be shortened and internally rotated while with an anterior dislocation
It appears to be an isolated injury with paraesthesia in the sole of the foot; however, motor function is intact. How will you take it from here?
A traumatic hip dislocation is a surgical emergency because of the risks to the vascularity of the femoral head, dangers of chondrolysis as well as pressure effects on the surrounding soft tissues, especially neurovascular structures. I would order baseline bloodtests including blood group and save. I would take informed consent for a closed or open reduction undergeneral anaesthesia.
Minute 2
There is delay in geting the C T scan and you take her to the operating theatre. How will you reduce the hip?
I would attempt closed reduction undergeneral anaesthesia. I would position her supine on the table with the table height as low as possible. I would request the anaesthetist to use full muscle relaxant to make it easier to reduce the hip. I would screen the hip first before attempting reduction to exclude a neck of femur fracture and also assess the acetabulum using Judet views. If it is posterior dislocation, I would apply gentle traction on the hip (inline) and then gradually flex the hip and the knee, maintaining traction. Bigelow’s technique is with hip flexed to 90°, the affected leg is placed in an adducted and internally rotated position.
You manage to reduce the hip and get this radiographic image (Figure 11.6a). What are your thoughts?
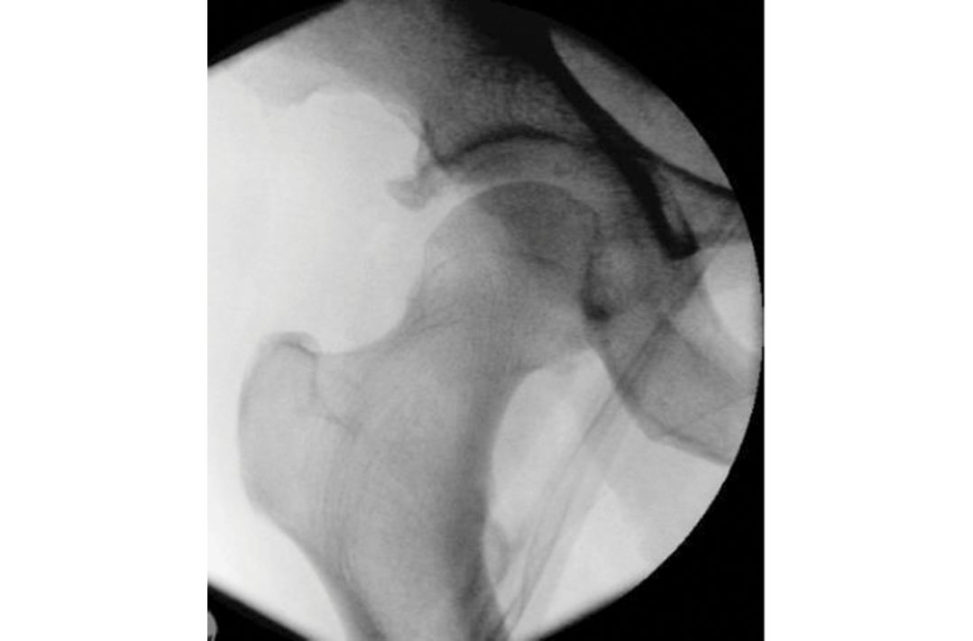
In the next 30 seconds you are expected to comment on the name of the patient site of radiograph and the exact nature of the injury. There is one more fragment on the superolateral lip of the acetabulum. The bony fragments are most likely to be from the acetabulum; however, femoral head fragments need to be ruled out.
Figure 11.6a Image intensifier (II) image right hip.
Minute 3
How will you assess this hip further?
In addition, I would carefully assess the hip for stability by screening the hip through a range of motion. A CT scan will be useful to delineate this further, if it has not already been done.
You get a CT scan done in the morning and this is one of the sections ( Figure 11.6b). What do you think?
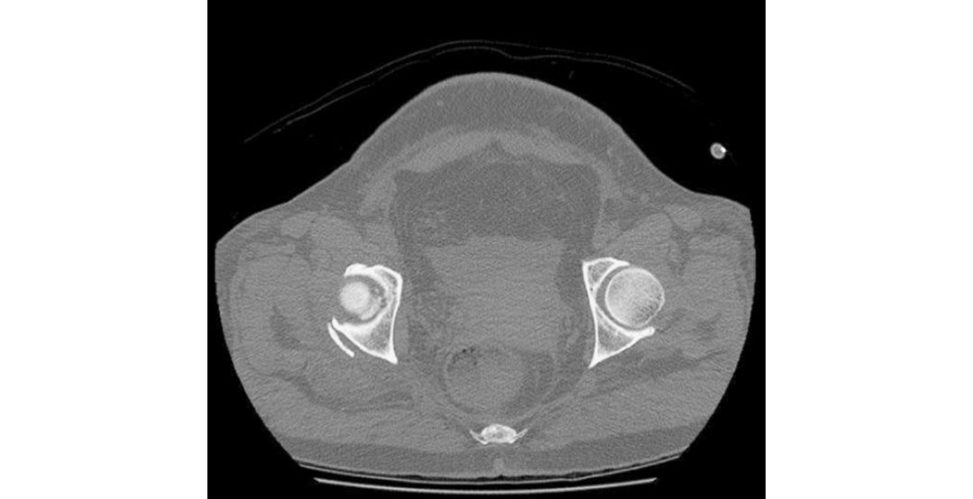
This may represent a fracture dislocation with compromise of the acetabular wall posterosupeiorly. I would, however, need to study the whole CT sequence to ascertain the extent of damage. After obtaining a postreduction C T if I wasn’t in an MTC I would discuss the images with the regional acetabular and pelvic reconstruction unit and get their advice.
What about an MRI scan of the hip?
While MRI will demonstrate labral tears and soft -tissue anatomy it has not been shown
How will you deal with the bony fragment in the hip joint?
This depends on a number of factors including the exact original site of the fragment, the size of it, the integrity of the weight-bearing dome and the stability of the hip. It will have to be an open procedure, although reports of arthroscopic intervention have been published. (Note: If the candidate does not have sound hip arthroscopy knowledge, then the safe option is open procedure and stay clear of hip arthroscopy.)
Figure 11.6b CT axial view pelvis.
Minute 4
You find that it is the posterosuperior lip of the acetabulum. Which approach will you use to fix the fracture?
The approach depends on where the bony fragment is arising from. I would position the patient on the fracture table in lateral decubitus. In the posterior approach to the hip I would respect the blood vessels supplying the femoral head and therefore would not takedown the quadratus (medial circumflex femoral artery). I would incise the short external rotators at least 1.5 cm from their insertions to again avoid damage occurring to the medial circumflex MCFA. If the fragment was large I would consider using a posterior plate one-third small fragment tubular or 3.5 mm reconstruction plate. If an anterior approach to the hip is needed either an ilioinguinal or Stoppa approach can be used.
Minute 5
What are the risks of posterior dislocation of the hip?
Immediate complications are sciatic nerve injury (10% with posterior dislocation fractures, and haemorrhage. Late complications are hip pain and post-traumatic osteoarthritis.
What other injuries are associated with this injury pattern?
This is determined by the direction of forces and may include patella fracture, PCL rupture, femoral shaft fracture, femoral neck and head fractures.
Evidence base
The evidence base here is largely based on expert opinion and there are no major RCTs.
Structured oral examination question 7#
A 78-year-old lady fell out of her bed while visiting friends in another part of the country and sustained this proximal femur fracture.
Minute 1
What can you see (Figure 11.7a.)? What are the treatment principles?
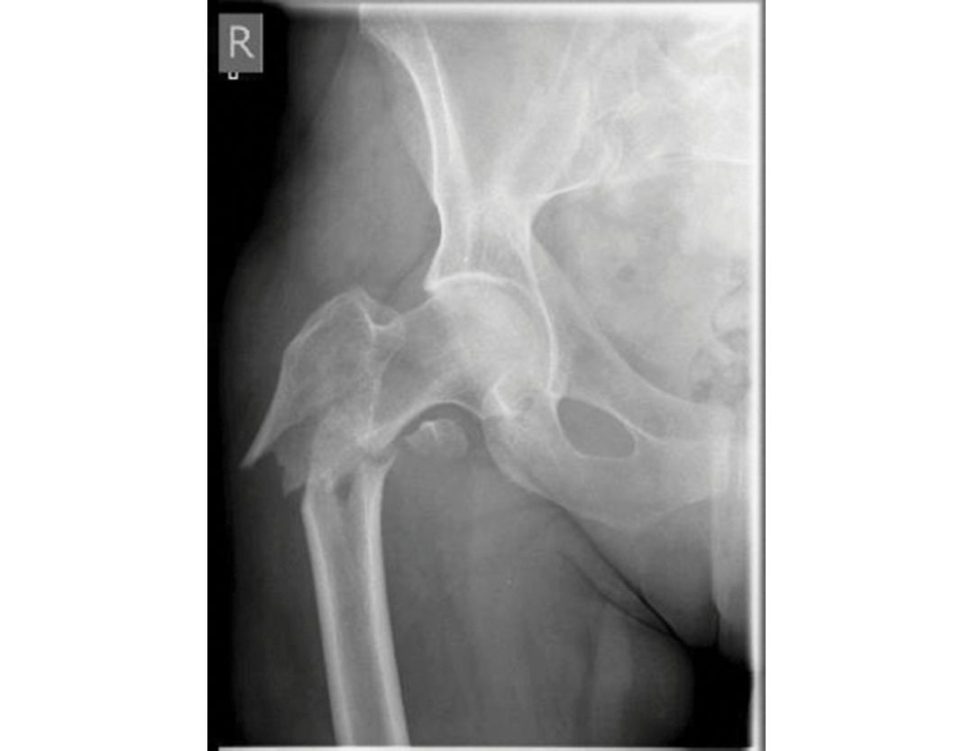
An AP radiograph of the right hip showing a reverse-obliquity inter-trochanteric fracture with subtrochanteric extension. I would like to see a lateral view; however, based even on the AP view, it is an unstable fracture pattern. W e need to consider the possibility of pathological fracture, although the available radiograph shows no evidence of that. Provided she is fit for surgery, I would aim to treat this fracture operatively and will do this within 36 hours of admission. I would use a cephalomedullary device to fix this fracture.
Figure 11.7a Anteroposterior (AP) radiograph of right femur demonstrating in ter-trochanteric fracture.
Minute 2
I agree. This lady was treated elsewhere initially with an extramedullary device. She presents 4 months down the line when you are on call with this complication, can you explain what happened (Figure 11.7b and 11.7c)?
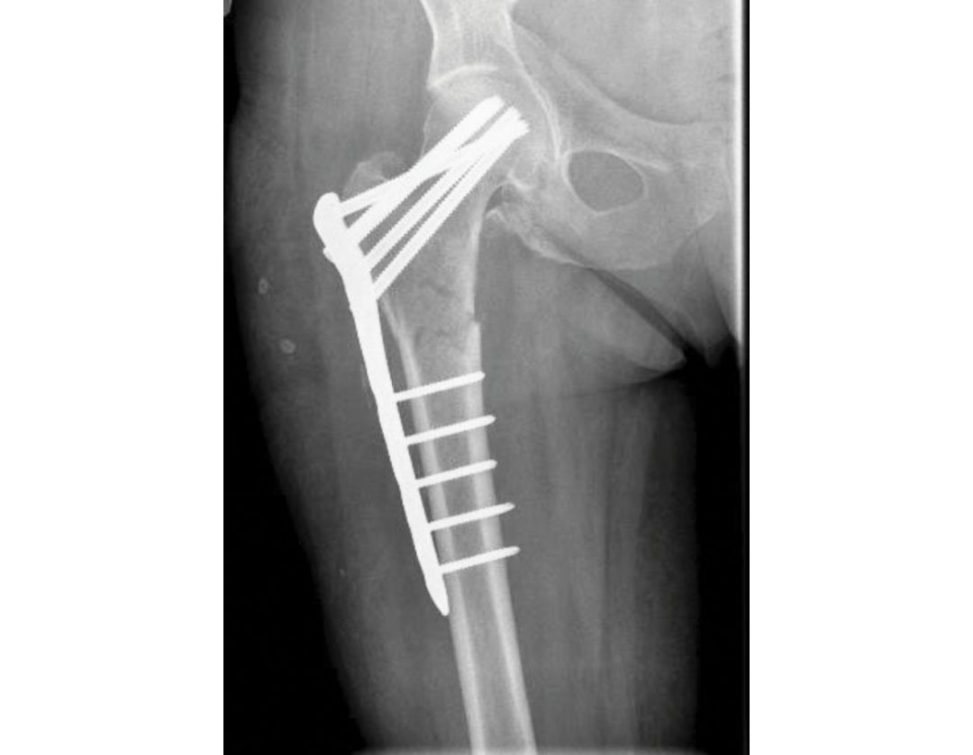
This lady was treated with a fixed angled locking plate. Two elements of fracture care are perhaps responsible for the implant failure – biomechanics and biology. Looking at the postoperative radiograph, there is a gap at the fracture site, especially on the medial side. On the other hand, there is a fracture gap and lack of compression, which will preclude primary bone union. This has resulted in delayed union/atrophic non-union at the fracture site. Essentially this fracture is in a surgical ‘no man’s land’ with none of the requirements of either primary or secondary bone healing. The implant has been under constant biomechanical load, which had led to the fatigue failure of the implant-grade steel. In this type of fracture, a cephalomedullary device has better biomechanical stability.
Figure 11.7b Anteroposterior (AP) radiograph, right femur, with fixed locking plate in situ.
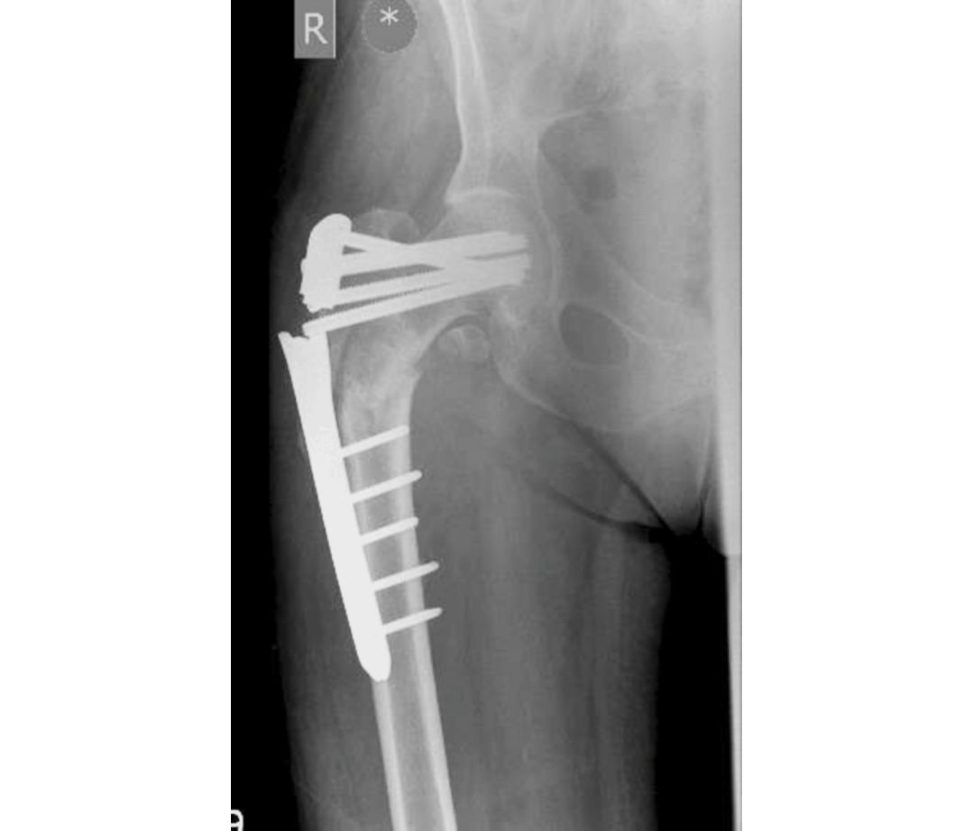
Figure 11.7c Anteroposterior (AP) radiograph, right femur, demonstrating hardware failure, 4 months postoperative.
Minute 4
You fixed it with this nail. What do you think about your check X-ray (Figure 11.7d)?
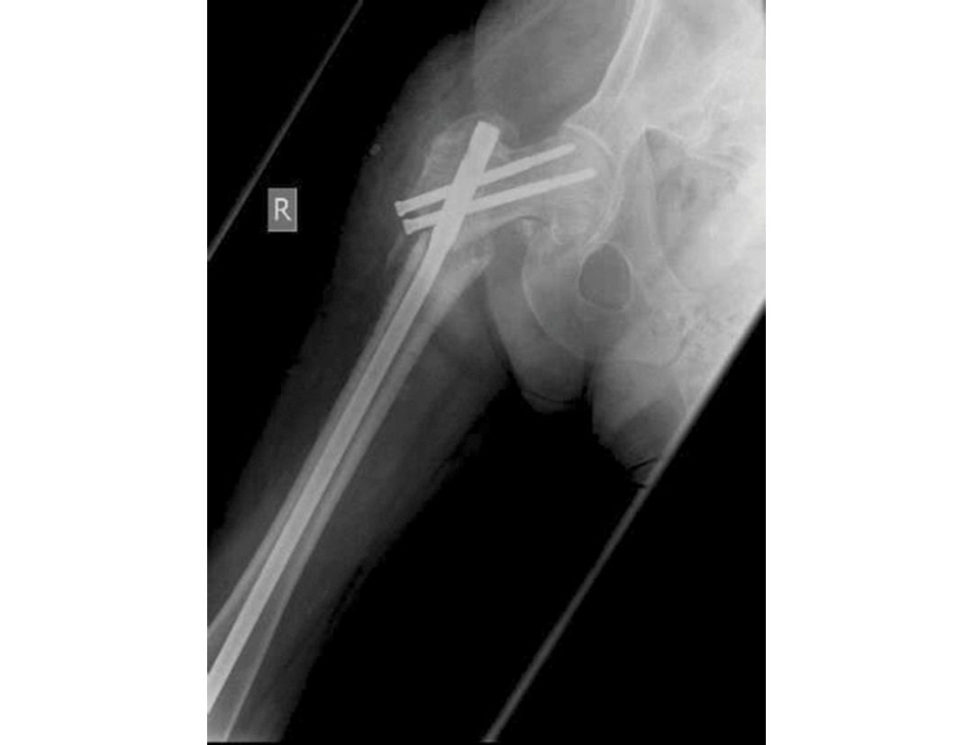
I fixed this?! I’m surprised as there are several fundamental issues with this construct. None of these features are ideal. In addition, the nail is probably undersized, it looks relatively small for the canal with only limited isthmic fit. Keep out of the politics of criticizing an y suboptimal fixation, especially in the exam. Keep it factually straight down the line with neutral comments.
Figure 11.7d Anteroposterior (AP) radiograph demonstrating non-union femoral fracture.
Minute 5
How will you follow-up this patient?
I would follow-up this patient with clinical reviews and serial radiographs. If there is no callus formation a t 6 months, I would consider exchanging the intramedullary nail.
Evidence base
A 2014 Cochrane review suggested that there is very poor evidence surrounding cephallomedullary
Intramedullary nails for extracapsular hip fractures in adults. 2014; Issue 9.
While the mechanical benefits of the intramedullary devices may not lead to improved outcomes in patients with a simple intertrochanteric fracture,
Be prepared to discuss the biomechanical differences between CMN and DHS.
Structured oral examination question 8#
A 72-year-old lady, fully independent with good health, was hit by a car when she was walking on a kerb.
She was brought to hospital with these two injuries. She was assessed following ATLS
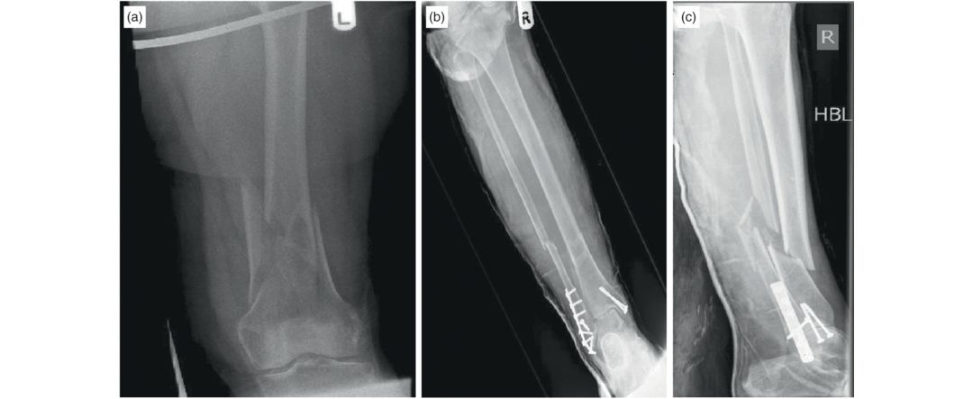
Figure 11.8a, 11.8b and 11.8c Anteroposterior (AP) radiograph, left femur, demonstrating supracondylar fracture femur, and AP and lateral radiographs, right lower leg.
Minute 1
What your thoughts about this patient management? Do you have any concerns?
This 72-year-old lady has multiple high-ener gy injuries. Elderly patients have a limited physiological reserve when compared to younger patients, so she needs to be closely observed, kept well hydrated and her general condition optimized before definitive treatment. The anaesthetic t eam and orthogeriatricians should be involved early in the plan for her treatment.
Minute 2
What implants are you going to use to fix these fractures?
For the left femur fracture it is an unstable, multi fragmentary, supracondylar fracture with femoral shortening. The aim is to reduce the fracture for length, alignment and rotation and then stabilize using a relative stability device. To do this I may need to use a femoral distracter for temporary reduction and then stabilize with either a nail or a plate. Failure in varus can be a problem for these fractures. Regarding the tibia fracture it is a distal third fracture that is periprosthetic in nature due to the presence of pre-existing implants from an ankle fixation.
Minutes 3–4
OK, have look on this radiograph (Figure 11.8d) and explain to me the technique the surgeon used and what the principles of such technique are.
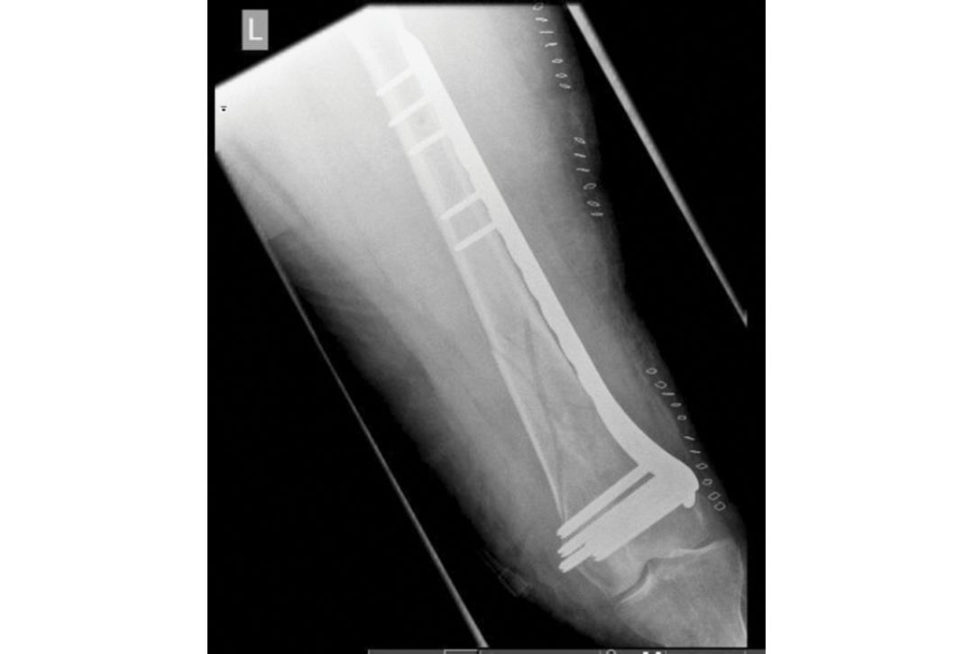
The AP radiograph shows a multi fragmentary fracture of distal diaphysis/metaphysis of the femur that has been stabilized with a fixed-angle plate, in bridging mode. Examining the skin staples, I can infer that closed indirect reduction and a less-in vasive technique was used. Length, alignment and rotation of the bone have been restored.
Can you explain why the surgeon put screws on either ends of the plate and missed the middle?
The surgeon intended to increase the working length of the implant (the distance between two points on either side of the fracture where the bone is fixed to plate or nail).
Figure 11.8d Anteroposterior (AP) radiograph, left distal femur with locking plate in situ.
Minute 5
You mentioned circular frames – can you tell me the principles of their use?
Circular frames consist of fixation elements such as tensioned wires or half pins attached to rings on either side of the fracture. This forms proximal ring blocks and distal ring blocks. They allow immediate weight-bearing and therefore are beneficial in the elderly and patients with limited compliance (Figure 11.8e).
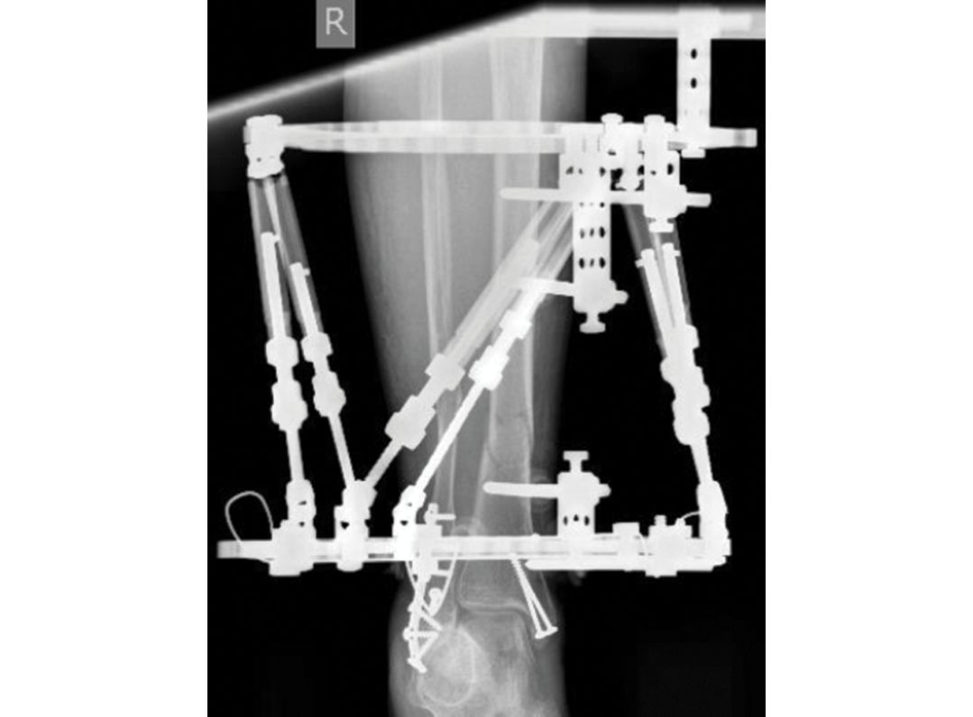
Figure 11.8e Anteroposterior (AP) radiograph, right distal tibia with circular frame in situ.
Structured oral examination question 9#
A 29-year-old female horse rider fell off her horse; she has been fully assessed
Minute 1
What are your thoughts (Figure 11.9a)?
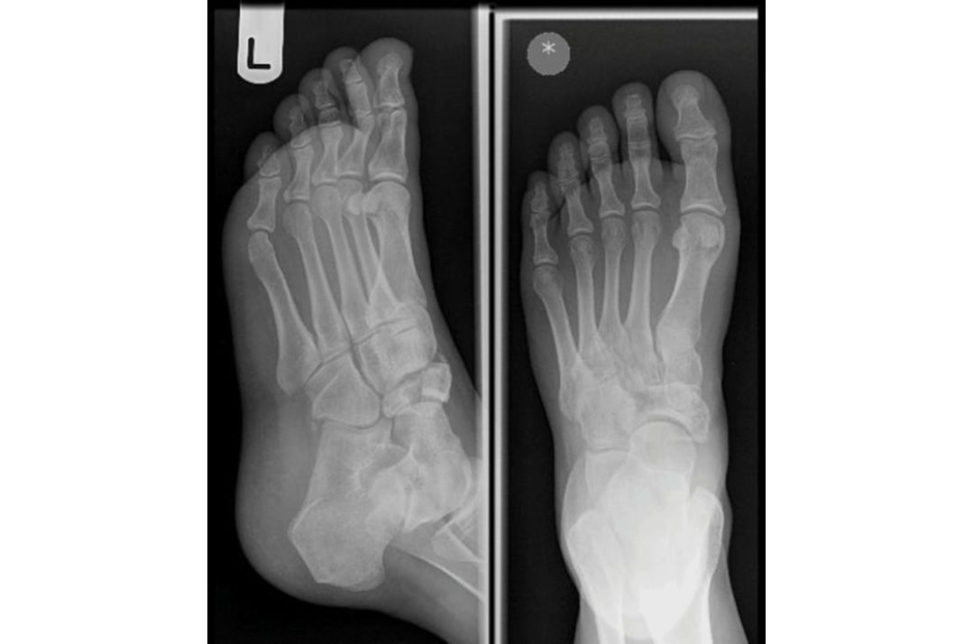
The radiographs of the left foot, AP and oblique, show a displaced, comminuted fracture of the body of the navicular. I would secure a relevant focused history, clinical examination in general of the patient and in particular of the foot, ruling out compartment syndrome, any neurovascular damage and assessing the soft -tissue envelope of the foot. I would initially tr eat the injured foot in abacks lab, with strict elevation and in termift ent cryotherapy, adequate analgesia and serial monitoring for any evolving compartment syndrome. This is probably worth knowing, although there is a move away in the exam from pure didactic learning of classification systems tousing a classification system as a guide to treatment. It is a useful guide towards difficulty of fracture reduction and eventual clinical outcome. Type 1 The fracture line splits the navicular into dorsal and plantar segments. Type 2 These are the most common injuries. The fracture traverses from dorsal lateral to plantar medial across the body of the tarsal navicular. Type 3 The fracture is characterized by comminution of fragments and significant displacement.
Figure 11.9a Anteroposterior (AP) and lateral radiographs, left foot.
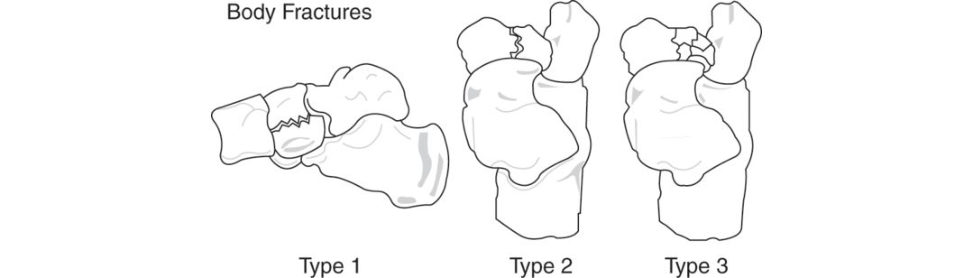
Figure 11.9b Sangeorzan et al. classification oft alar body fractures.
Minute 2
This is the scan you requested, what do you see and how would you manage it (Figure 11.9c and 11.9d)?
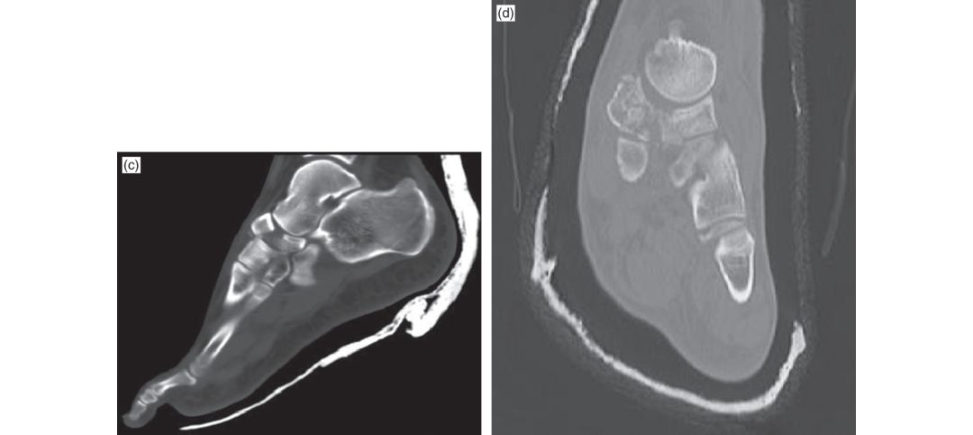
These are coronal and sagift al sections of the C T scan, and they confirm the radiographic findings of a displaced fracture of the body of navicular bone with comminution. It is an unstable displaced intra-articular fracture and I would therefore favour operative intervention rather than non-operativ e. The aim of the treatment is to have a mobile, pain-free and functional joint. Fractures with less than 2 mm articular displacement, no midfoot instability and noloss of bone length can be managed non-operativ ely. Non-weight-bearing cast for 6–8 weeks. In general, all navicular body fractures with >2 mm displacement require ORIF.
Figure 11.9c and 11.9d CT scan, coronal and sagift al sections of left foot.
Minute 3
Can you tellus about any possible complication associated with this case?
Early complications include infection nerve injury (branches of superficial and deep peroneal nerves), vascular injury (dorsalis pedis); and late complications include non-union and loss of medial longitudinal arch support, painful talonavicular joint, post-traumatic osteoarthritis, as well as avascular necrosis and collapse.
What are you going to tell the patient?
With a good reduction most have a reasonable prognosis, but few are normal. Sangeorzan et al. found that the type of
Minute 4
Why does non-union and avascular necrosis occur in this fracture?
The navicular, and this could be injured either at the time of the fracture or during surgery, which could lead to AVN, non-union and/or collapse of the bone resulting in a painful midfoot.
What surgical approach are you going to use?
Probably not scoring any real marks but avoids complete silence.] It is important to directly visualize the articular surface to ensure accurate reduction of the articular surface. I would stabilize the fracture with cannulated screws from lateral to medial; however, the eventual configuration of screws will depend on the fracture pattern. I would avoid extensive periosteal stripping over the dorsal navicular surface as this may disturb the tenuous blood supply of the central third portion of the body . Sometimes ase cond anterolateral incision is needed to help with reduction of a significantly displaced lateral fragment.
Minute 5
Take me through your consent process, in general.
I follow the General Medical Council guidelines on this subject and broadly run my practice along the lines of the domains of the GMC ‘Good Medical Practice ’. In particular: (a) I listen topa tien ts and respect their views about their health. (e) I respect the patient decisions. These are quite rare injuries.
Structured oral examination question 10#
He is a right-hand dominant manual worker. He sustained the closed, isolated injury below.
Minute 1
Talk me through your initial assessment and management of this patient in A&E.
I will then move on to perform an examination. This would include a general examination to ensure fitness for surgery before focusing on the injured limb. Following this assessment, I would want to put some simple first aid management steps in place including analgesia and application of a back -slab. I would also counsel the patient about the risks of compartment syndrome. I would ask nursing staff to conduct serial neurovascular checks.
How exactly would you assess neurovascular status for this injury?
At this level I would be concerned about the function of the small muscles of the hand supplied by median and ulna nerves as well as sensation in the median radial and ulna nerves. I would test motor function by resisting abduction of the fingers (ulna nerve) and opposition of the thumb (median nerve).
Minute 2
Despite elevation the patient develops increasing pain in his arm overnight and you are called to see him; how would you proceed?
As mentioned earlier , I would be concerned that this gentleman could be developing compartment syndrome. I would want to see him and assess accordingly. I would have a high index of suspicion if he had intractable pain, increasing levels of analgesia requirement and worsening pain on passive stretch. If, having reviewed the patient, I had a high index of suspicion of forearm compartment syndrome then I would need to think about taking this patient to theatre for fasciotomy.
Minute 3
You mentioned informed consent; what specific risks would you mention to this patient?
Intermediately, he would be at risk of infection, especially given the open wound, DVT/PE and he will need further surgery. Long-term, the risks include mal- or nonunion, stiffness, loss of function and complex regional pain syndrome.
Minutes 4–5
What are your principles of management in a case like this?
The aim of surgery is always to ensure the best possible outcome for the patient There are two main issues facing this patient compartment syndrome requiring fasciotomies and his forearm fracture which requires stabilization. I would make sure to discuss my plan, in detail, with the theatre team preoperatively and complete a surgical pause as per WHO guidelines prior to starting the case. I would achieve this by means of an open reduction and plate osteosynthesis with DCP type plates. If possible, I would utilize my fasciotomy wounds for this, although I may need a separate incision for the ulna fracture. Having fixed his fractures and completed his fasciotomies this patient will present another problem: exposed metalwork. To try and mitigate the risk of infection I would put a negativ e- pressure dressing on the wounds and continue prophylactic IV antibiotics un tilde finitive coverage can be obtained with direct closure or skin gratiing.
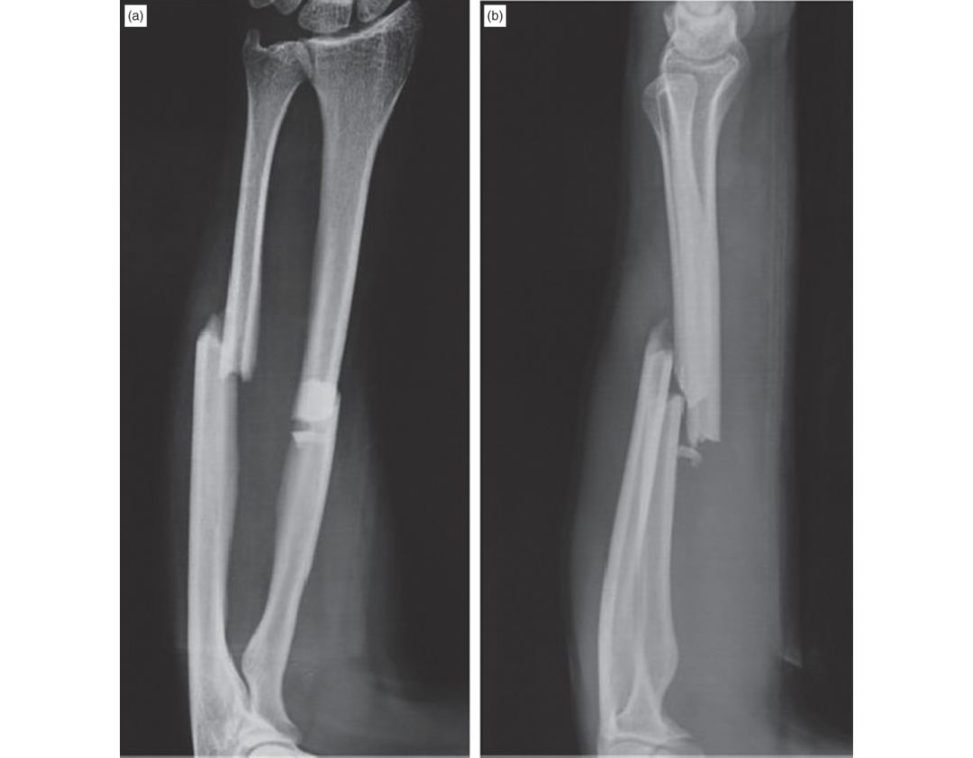
Figure 11.10a and 11.10b Anteroposterior and lateral radiographs, right radius and ulnar.
Evidence base
As stated in the BOAST 10 guidelines there are no RCTs on compartment syndrome and the guideline is based on, predominantly, retrospective studies.
Structured oral examination question 11#
A 49-year-old male is bought into the Emergency room having been blasted off his feet by an exploding air cylinder at work.
Minute 1
How would you initially assess this patient?
I would assess this patient utilizing the principles of A TLS. The cervical spine should be immobilized, and ABC assessed using simple monitoring and examination in the first instance. If the patient is not in extremis, then I would like to consider get inga trauma series CT and plain radiographs of any obviously injured limbs.
Minute 2
The patient is conscious but muddled. He is maintaining his airway and oxygen saturations. However, the ambulance crew were unable to cannulate him, he is tachycardic at 124 bp mand hypotensive at 90/56. He has a tender abdomen, an open distal tibial fracture with no evidence of major bleeding and a deformed forearm. Pelvic binder is in place. How would you proceed?
This patient is demonstrating signs of shock which is likely to be hypovolaemic. I would also want to obtain an ABG to look at pH, base excess and lactate levels as these are good surrogate markers of tissue perfusion. Further to this I would like to give the pa tienta dose of tranexamic acid (1 g IV), a tetanus booster and a dose of IV antibiotics inline with trus t policy for open fractures. I would also check the pelvic binder is positioned correctly.
Minute 3
Do you still want to send this patient for a CT scan?
Assuming the department is compliant with the Royal College of Radiology guidelines then obtaining a trauma CT should be a quick process and still allow continuing fluid resuscitation.
Minutes 4–5
CT scan shows evidence of a ruptured spleen and some blood in the pelvis but no active extravasation here. The patient is transferred back to the emergency where departmental radiographs are obtained of the patient limb injuries. The general surgeons are intending to take the patient straight to theatre for a splenectomy. How would you proceed?
This patient has multiple serious injuries. His splenectomy is life-saving and should take priority. From an orthopaedic point of view he has a confirmed open tibial shaft fracture, a closed forearm fracture and a potential pelvic injury which is being stabilized by the binder.
What do you mean by damage control orthopaedics?
It is designed to avoid worsening apa tien t’s condition duet o the ‘second-hit’ phenomenon. It focuses on haemorrhagic control, management of soft -tissue injury and provisional fracture stability.
Anything else?
DCO involves rapid emergency surgery to save life or limb – NOT involving complex reconstructive surgery. Splint fractures. Cast, traction, pelvic binder , ex-fix. Get back to ITU environment ASAP.
Following his splenectomy the patient has a pH of 7.35, base excess of –3 mmol/l and lactate of 2.0 mmol/l.
For the tibial fracture, debriding this as a combined case with a consultant plastic surgical colleague to ensure appropriate soft -tissue c over and follow-up will be possible. I would deliver the bone ends through the wound to debride these before reducing the fracture. My personal preference here would be an intramedullary nail. If adequate soft -tissue cover was not available, then I would debride as above before using a spanning external fixator to stabilize until the patient was able to better tolerate graft surgery.
Having dealt with the forearm, a repeat AB Gis obtained, this shows a pH of 7.35, base excess of –4.1 mmol/l and lactate of 2.9 mmol/l. Does this change your management?
Yes. This would entail a thorough debridement and then simple external fixation of the tibia. His tibial fracture can be formally stabilized in a planned fashion once his physiology has improved.
What is SIRS?
This is a condition characterized by systemic inflammation, or gan dysfunction and or gan failure.
How is SIRS diagnosed?
1. Heart rate > 90/min. 2. Breathing rate > 20/min, hyperventilation with decrease of arterial CO2 partial pressure (PaCO2) under 32 mmHg. 3. Temperature > 38.8°C or < 36.8°C. 4. Number of leukocytes < 4000/mm3 or > 12,000/mm3. Sepsis is defined as SIRS with detection of bacteraemia or bacterial focus. Continued reassessment and ability to change from ET Oto DCO.
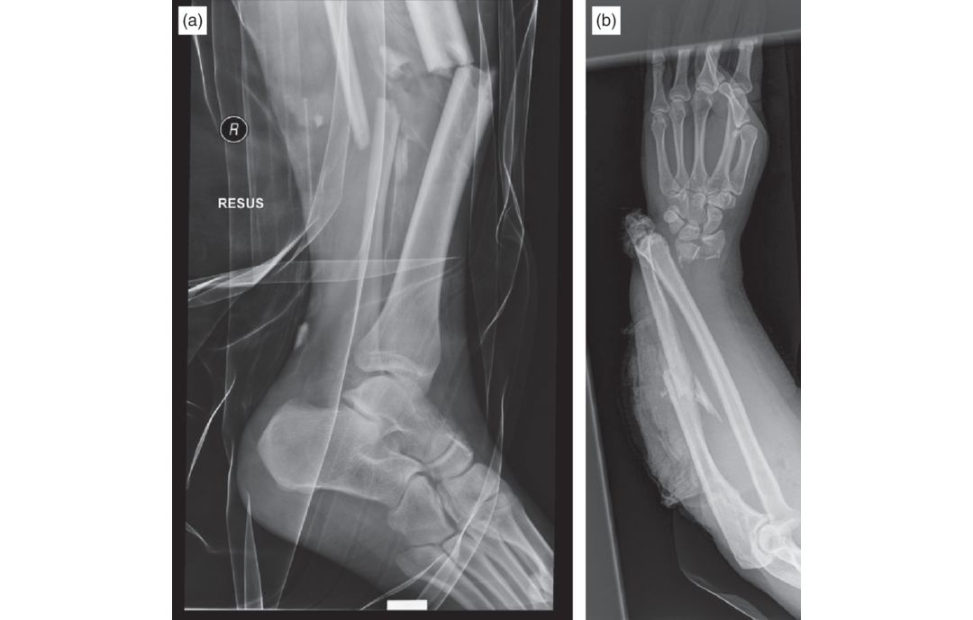
Figure 11.11a and 11.11b Lateral radiograph, comminuted fractured midshaft tibia and fibula, and anteroposterior (AP) radiograph, right radius and ulna.
Evidence base
NICE produced a guideline on major trauma in 2016. There islots of evidence around ETC/DCO and candidates should know some of it. It is also worth knowing about the
CRASH-2 trial and use of TXA; make sure you know how TX Aworks as well.
NICE Guideline No. 39 – Major Trauma: Assessment and Initial Management.
Complications are reduced with a protocol to standardize timing of fixation based on response to resuscitation .
Roberts I, Shakur H, Coats T, Hunt B, Balogun E. The CRASH-2 trial: a randomized controlled trial and economic evaluation of the effects of tranexamic
Structured oral examination question 12#
A 36-year-old lady sustained an open tibial fracture while horse riding. This is her radiograph at 10 months postop.
Minute 1
How would you assess this patient?
This patient has radiographic evidence of an atrophic non-union. I would start by taking a history. Important factors to drawout include pain, weight-bearing status, postoperative wound issues, completion of antibiotic therapy , comorbidities including diabetes, medication steroids and smoking history.
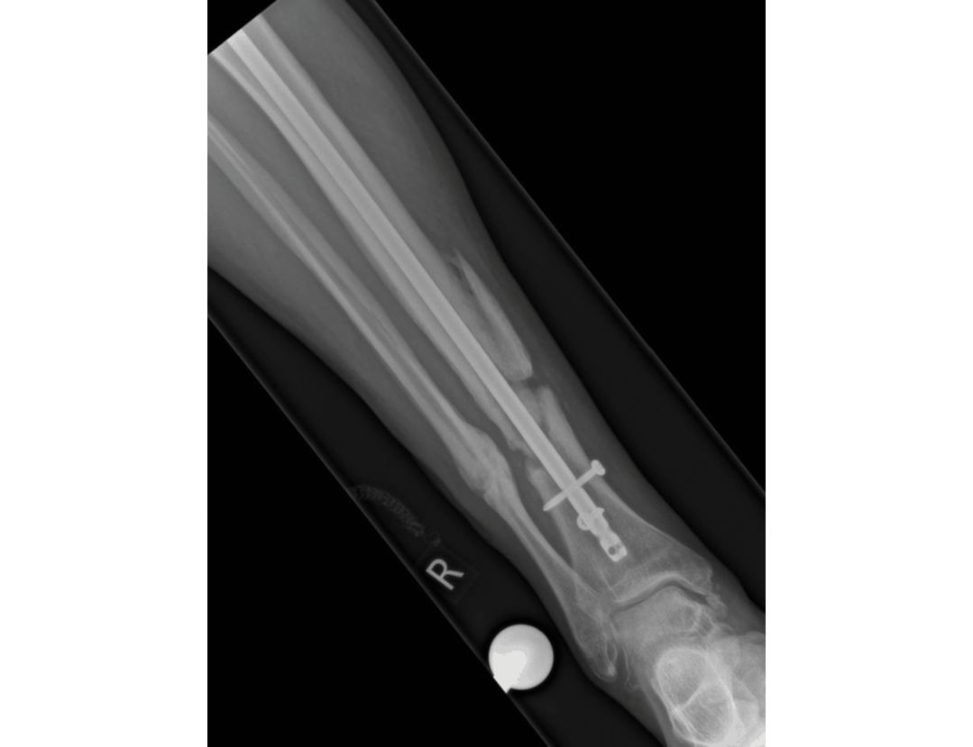
Figure 11.12 Anteroposterior (AP) radiograph, tibial non-union with IM nail in situ.
Minute 2
The patient is a fit and well, non-smoker who had an uneventiul postoperative recovery. She is struggling to weight-bear due to pain at the fracture site. What do you think is the cause of her non-union?
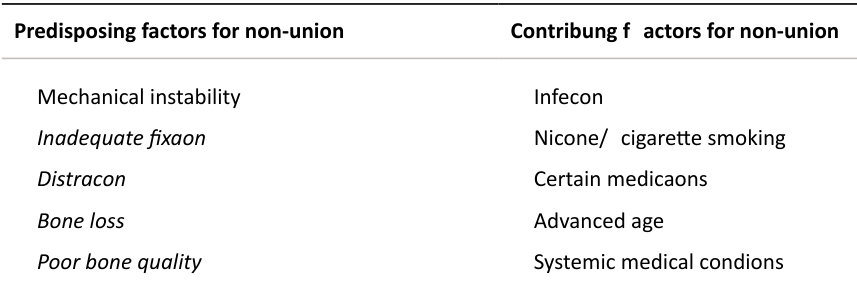
There are no negative patient factors. This is likely to be due to infection or inadequate blood supply to the fracture site. There are implant factors as well. Distraction a t the fracture site at the time of initial nailing may contribute to the development of a non-union. This is a basic candidate 6 answer, nothing special. On a bad day with more hawkish examiners down to a 5. See Table 11.1 for a more detailed answer. Table 11.1 Causes for non-union.
Poor functional le vel
Venous stasis
Burns
Irradiation
Obesity
Alcohol abuse
Metabolic bone disease
Malnutrition
Vitamin deficiencies
Predisposing factors for non-union Contributing factors for non-union
Inadequate vascularity
Severe injury
Excessive soft tissue stripping
Vascular injury
Poor bone contact
Soft tissue interposition
Malposition or malalignment
Bone loss
Distraction
Minutes 3–4
The patient bloodtests come back showing a CRP of 29 (< 4), ESR 40 (< 20) and a WCC of 13.4 (< 10.0). You perform a CT which shows no evidence of fracture healing, but there is a fragment of devascularized bone consistent with a buft erfly fragment. What management options would you give to the patient?
I would counsel the patient that I feel they have an infected non-union and then talk about the broad management strategies of conservative, non-operativ e or operative management. Non-operativ e management would involve treatment with suppressive antibiotics to try and allow the fracture to heal despite the infection. This is unlikely to work, as the bone ends are atrophic and therefore the biology of the fracture is unlikely to be favourable for healing even if the infection was suppressed. This would involve removal of the current nail, debridement of the fracture site, removal of all dead bone and reaming of the intramedullary canal. Finally, the reaming products are osteoinductiv e. After primary nailing these products are extruded through the fracture site, but at exchange nailing fibrous tissue will t end to confine the reaming to the medullary canal.
Are you sure that you are talking about infected tibial non-unions?
Pardon?
I think you may be talking about exchange tibial nailing for aseptic non-union.
The candidate has mixed up the management of infected and aseptic tibial non-unions. A number of authors report that the treatment of choice for tibial diaphyseal fracture non-union is reamed exchange nailing. However, in the presence of infection it is a more controversial option. The reis currently no consensus in the literature with regard to the use of exchange nailing for tibial diaphyseal fracture non-union in the presence of infection.
I would go for an external ring fixator to stabilize the fracture. I would send reamings and bone samples for culture and
What is the role of a circular frame in infected tibial non-unions?
Sorry?
What are the basic requirements for fracture healing?
Mechanical stability. Bone-to-bone contact. These factors may be negatively influenced by the severity of the injury and suboptimal surgical fixation which predisposes to non-union.
What factors predispose to instability at the fracture site?
1 Mechanical instability, excessive motion at the fracture site
Factors producing mechanical instability include:
Inadequate fixation (implants too small or too few).
Distraction of the fracture surfaces (hardware is as capable of holding bone apart as holding bone together).
Bone loss.
Poor bone quality (i.e. poor purchase).
If an adequate blood supply exists, excessive motion at the fracture site results in abundant callus formation,
2 Inadequate vascularity
Loss of blood supply to the fracture surfaces may arise because of the severity of the injury or because of surgical dissection.
Open fractures and high-energy closed injuries may strip soft tissues, damage the periosteal
Injury of certain vessels, such as the posterior tibial artery, may also increase the risk of non-union.
Vascularity may also be compromised by excess stripping of the periosteum as well as
Whatever the cause, inadequate vascularity results in necrotic bone at the ends of the fracture fragments.
These necrotic surfaces inhibit fracture healing and often result in fracture non-union.
3 Poor bone contact
Poor bone-to-bone contact at the fracture site may result from soft -tissue interposition, malposition
Whatever the cause, poor bone-to-bone contact compromises mechanical stability and creates a defect.
The probability of fracture union decreases as defects increase in size. The threshold value for rapid bridging of
Larger cortical defects may also heal, but at a much slower rate and bridge via woven bone.
The ‘critical defect’ represents the distance between fracture surfaces that will not be bridged by bone without intervention.
4 Infection
Infection in the z one of fracture increases the risk of non-union.
Infection may result in instability at the fracture site as implants loosen in infected bone.
Infection also produces poor bony contact as osteolysis at the fracture site results from ingrowth of infected granulation tissue.
Are there any other investigations you would like to obtain preoperatively?
Yes. I would like to obtain blood cultures to look for evidence of bacteraemia which may help guide antimicrobial therapy.
Minute 5
What are the principles of management of an infected non-union?
I would need to consider host factors, the microorganism involved, debridement, antibiotic therapy and reconstruction.
What is a biofilm?
An established biofilm structure comprises microbial cells and extracellular polymeric substance sEPS) produced by the microorganisms themselves.
Have you heard of the Masquelet technique?
No, sorry. Antibiotic-impr egnated cement beads or spacers are used for local antibiotic administration to the soft -tissue bed. In the case of infection following IM nailing the canal should be reamed for debridement and irrigation. A second stage of bone gratiing is performed around 8 weeks after the initial surgery. It act slik e a chamber around the bony defect to contain the bone graft ands timula te bone regeneration. This membrane should be disturbed as liti leas possible a t the time of the second stage.
Structured oral examination question 13#
A 33-year-old barrister slips on some ice and sustains an isolated closed ankle fracture. This is his radiograph in the Emergency Department.
Minute 1
Talk to me about this injury.
These are lateral and oblique radiographs of a left ankle showing a complex fracture– dislocation of the ankle such that the talus is almost completely displaced from the mortice and there is considerable rotation seen. The fibula fracture is suggestive of a Weber B injury. This is a serious injury. The leg should be placed in a below-knee back-slab followed by check radiographs to confirm satisfactory reduction of the ankle mortice.
OK. He is much more comfortable now and you obtain a good reduction. It is late in the evening and theatres are already busy with emergencies.
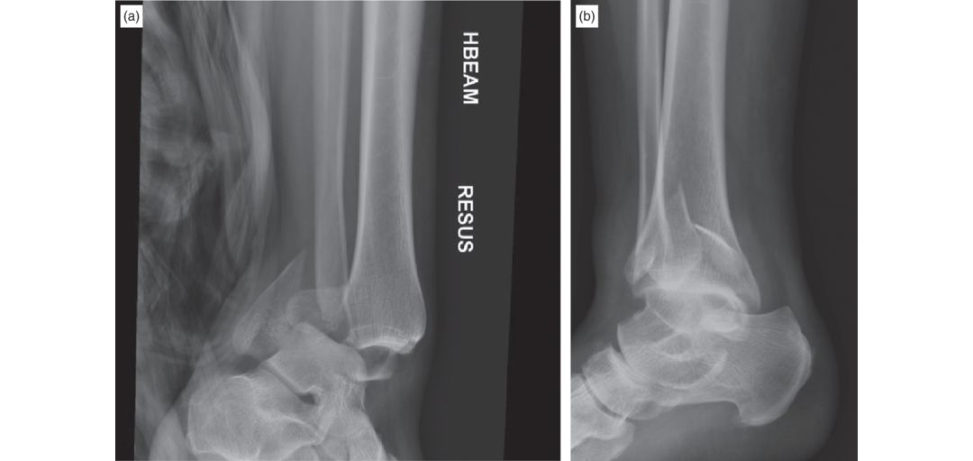
Figure 11.13a and 11.13b Oblique and lateral radiographs, left ankle showing a fracture/dislocation.
Minutes 2–3
Timing is important with these injuries due to soft -tissues welling. I would consent the patient for internal fixation and also for external fixation and I would discuss the fact that this is a significant injury with a risk of compromised function in the future.
What is debatable about operating in the presence of severely contused and swollen soft tissues with marked subcutaneous oedema? This practice would increase the risks of wound dehiscence, infection, need for plastic surgery involvement reoperations and adverse outcomes.
The key point is early fixation within 6 –12 hours of injury only. The paper from Giannoudis from Leeds in the RCSEng bulletin suggested a fast-track method to get ankle fractures into theatre on the day of injury with the development of a streamlined pathway for early surgery.8 The key point is early presentation within a few hours of injury. It is very rare for an ankle to be too swollen to undertake operative fixation on the day of admission, although each patient’s treatment should be decided on an individual basis.9 With anything controversial be very clear about what you are actually saying. Perhaps even better to stay clear of any controversy if you are just averaging a straighfoorward 6.
OK. You go to theatre and find the ankle too swollen to operate on with significant blistering already present and you achieve a good reduction with the external fixator. Please review the image and tellus what you would do now.
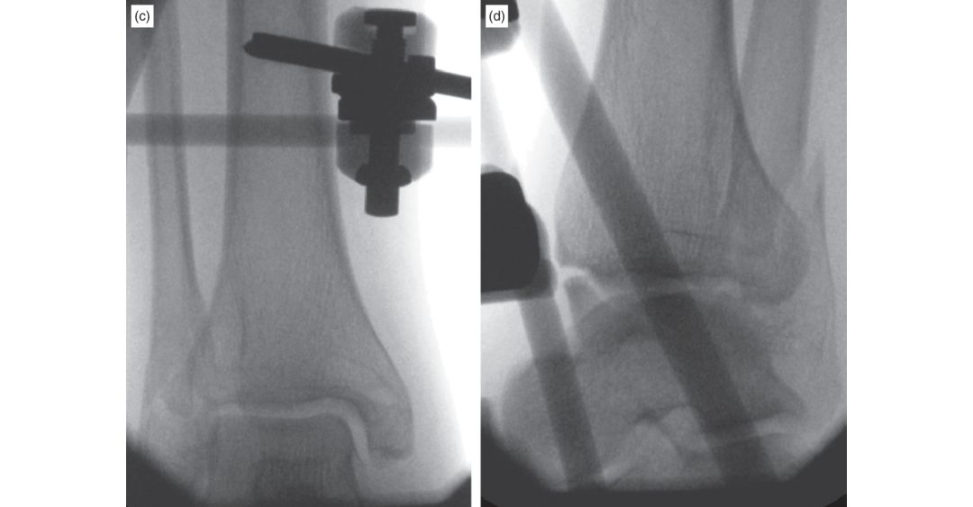
Figure 11.13c and 11.13d Anteroposterior (AP) and lateral radiographs of ankle following external fixator application.
Minute 4
The external fixator has been used in a triangular configuration and the reduction is satisfactory. I will advise the patient that definitive surgery may occur in about 10– 14 days. I would ensure the patient has had aDVT assessment and that the limbis properly elevated. With all complex ankle fractures, when planning reconstruction, 3D cr oss-sectional imaging is useful and so I would order a CT scan.
What are the concerns with temporary external fixator use?
Pin site infections, superficial wound infections and postoperative loss of reduction. Patients should be monitored for compartment syndrome and neuropraxia.
What elements in particular are you interested in evaluating here?
Stability in the management of ankle fractures is key. Ligament tension and fracture configuration contribute. (2006) as Types I–III and I find this useful to characterize and treat these fractures.
Here is the axial CT slice – what do you think?
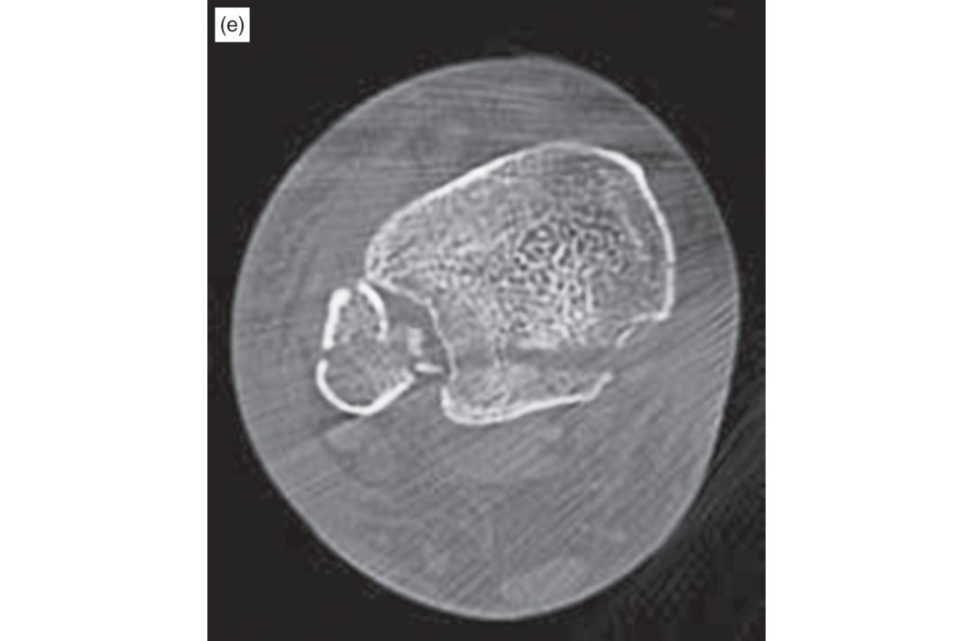
Figure 11.13e Axial CT slices, ankle.
Minute 5
This is a Haraguchi Type I as it is ‘wedge-shaped’ and essentially is a chunk off the posterolateral distal tibia ( Table 11.2). The posterior malleolus plays an integral role in ankle joint stability through its anatomical relationship with the posterior tibiofibular ligament (PTFL), which has been shown through cadaver studies to account for 42% of syndesmotic stability.
How would you fix this fracture?
I would fix the lateral malleolar fracture with a lag screw and 3.5 mm one-third tubular plate acting in a neutralizing mode. The posterior fragment can be fixed with lag screws inserted from anterior to posterior.
Anything else to fix the posterior malleolar fragment?
A plate could be used. Contoured one-third tubular plate acting as in bu tiress mode. The plate is not contoured, it will contour itself
How would you put the plate on?
Sorry?
What approach would you use?
Standard lateral approach to the fibula.
Any other approaches you are familiar with?
A posterolateral approach.
Tell me about the posterolateral approach.
Ehh?! [Bell]
Thankyou.
Deep dissection between FHL medially and the peroneal tendons laterally. The sural nerve is at risk and needs to be identified and protected.
The posterior surface of the tibia can be reached by retraction of the FHL and the deep posterior compartment medially.
Table 11.2 Haraguchi classification of posterior malleolus fracture of ankle
Type I fracture is an isolated PMF
Type II fracture is either a bi- or trimalleolar fracture associated with a Weber B orC fracture pattern.
Type III PMF is associated with an ipsilateral tibial diaphyseal fracture. This is further subdivided based on sagift al or coronal plane instability
Evidence base#
Solan MC, Sakellariou A. Posterior malleolus fractures. Bone Joint J. Published Online: 1 Nov 2017.
htip s://doi.org/10.1302/0301-620X.99B11.BJJ-2017–1072
Notes
1. Risk of total knee arthroplasty after operatively treated tibial plateau fracture: a matched-population-based cohort study.
2. Griffin D, Parsons N, Shaw E, et al. Operative versus non-operativ e treatment for closed, displaced,
Operative compared with nonoperative treatment of displaced intra-articular calcaneal fractures: a prospective randomized, controlled multic enter trial.
4. Baumgaertel F, Buhl M, Rahn BA. Fracture healing in biological plate osteosynthesis. Injury. 1998;29:3–6
5. Sangeorzan BJ, Benirschke SK, Mos caV, Mayo KA, Hansen ST Jr. 1989;71:1504–1510.
6. Banaszkiewicz PA, Sabboubeh A, McLeod I, Maffulli N. Injury. 2003;34(5):349–356.
Exchange nailing for nonunion of diaphyseal fractures of the tibia: our results and an analysis of the risk factors for failure.
8. Kheir E, Charopoulos I, Dimitriou R, Ghoz A, Dahabreh Z, Giannoudis PV. 2012;94(4):1–5.
9. Cost benefit with early operative fixation of unstable ankle fractures. 2006;88(4):405–407.