Chapter 12 Upper limb trauma I
Structured oral examination question 1#
Fracture dislocation shoulder
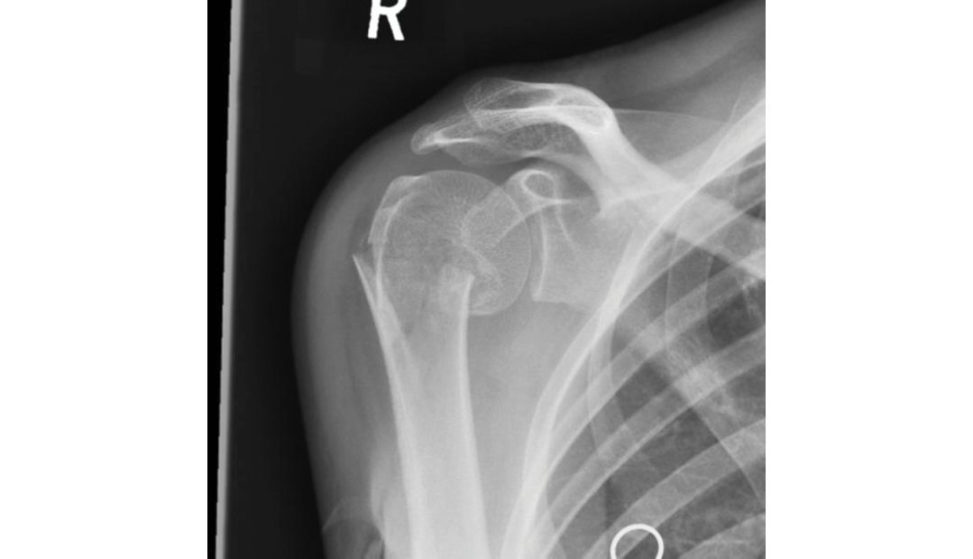
A 38-year-old left-hand dominant lady fellon to her right arm when outdrinking and attended the accident and emergency department the next day at 4 pm as the pain in the right shoulder had not setiled down. These are the X-rays of her right shoulder (Figure 12.1a). What is your diagnosis?
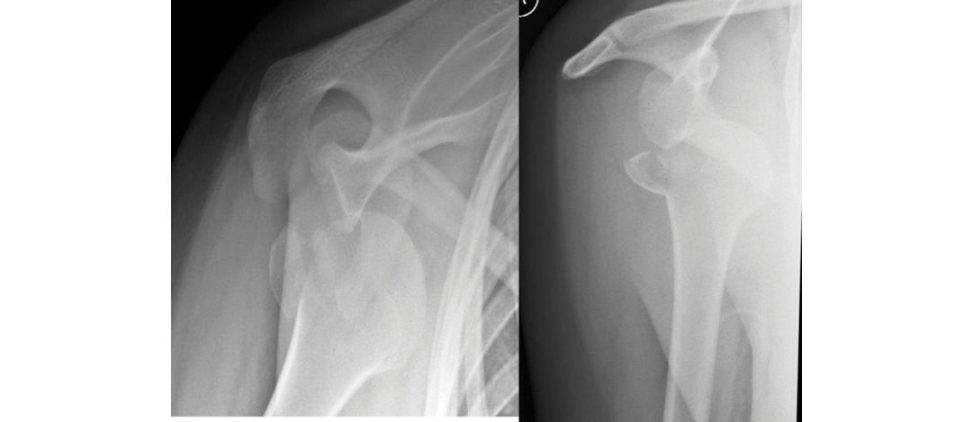
There is no visible evidence of fracture through the anatomical neck, although this occurs in about 10% of cases. This pattern of injury is more in keeping with this patient age than surgical neck fracture, which is more typically seen in an older demographic.1
How will you manage this condition?
Assess the patient according to ATLS protocol and exclude any neurovascular injury because brachial plexus injury is part of a recognized pattern comprising the ‘terrible triad’ of the shoulder.2 If there was suspicion of an undisplaced neck fracture, I would obtain an emergency CT to confirmand then plan for open reduction and fixation of both the neck and G T fractures. I would immobilize the limb in a shoulder immobilizer. After manipulation I would obtain anteroposterior and axial radiographs and repeat a neurovascular examination of the involved limb.
What are the risks and complications you anticipate?
During reduction the reis a risk of displacing an unseen humeral neck fracture or propagating the G T fracture through the neck.
Attempted closed reduction in the accident and emergency department has failed and it is 7 pm now. What will you do next?
If it is safe and within a reasonable time fr ame, I would take the patient for closed reduction undergeneral anaesthetic. After reduction I would reassess the neurovascular status. If there was a new neurovascular deficit, this may be due to nerve entrapment. In this situation, I would plan for a shoulder surgeon to explore the nerve and perform an open reduction in the morning.
What manoeuvre would you perform to achieve shoulder reduction?
Under complete muscle relaxation, I will use the traction/ countertraction method given that scapular manipulation has failed. This is the second most effective technique and the associated discomfort will not be
What other factors may prevent a closed stable reduction of the dislocation?
A large rotator cuff tear or axillary nerve injury may prevent the shoulder from remaining in joint. On occasion, the longhead of the biceps may get caught up posterior to the humeral head and prevent reduction.
Next day in theatre, closed reduction is achieved (Figure 12.1b). What will you do next?
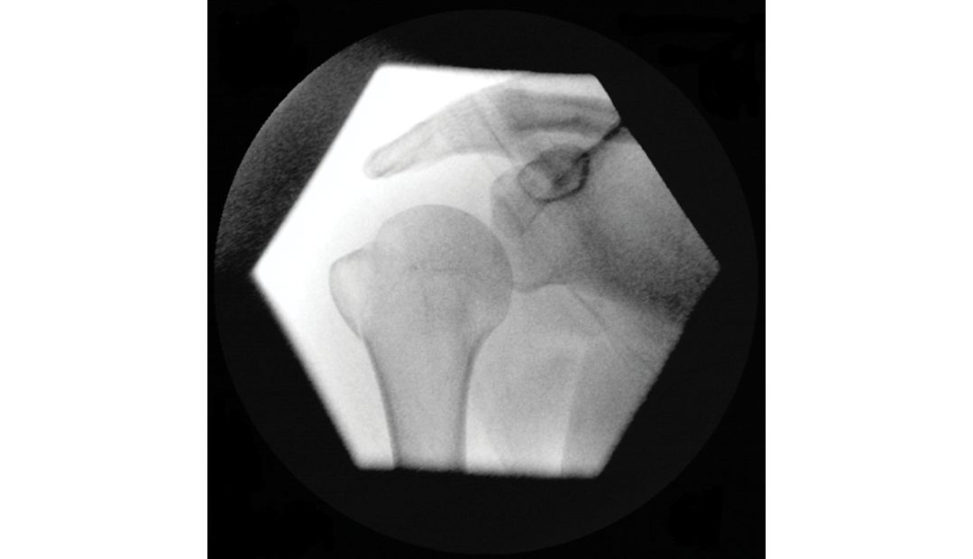
I will assess the greater tuberosity fracture reduction. If it isless than 5 mm superiorly displaced, I will treat it non-operativ ely with a polysling for 3
X-ray of right shoulder one week later is shown in Figure 12.1c. What will you do?
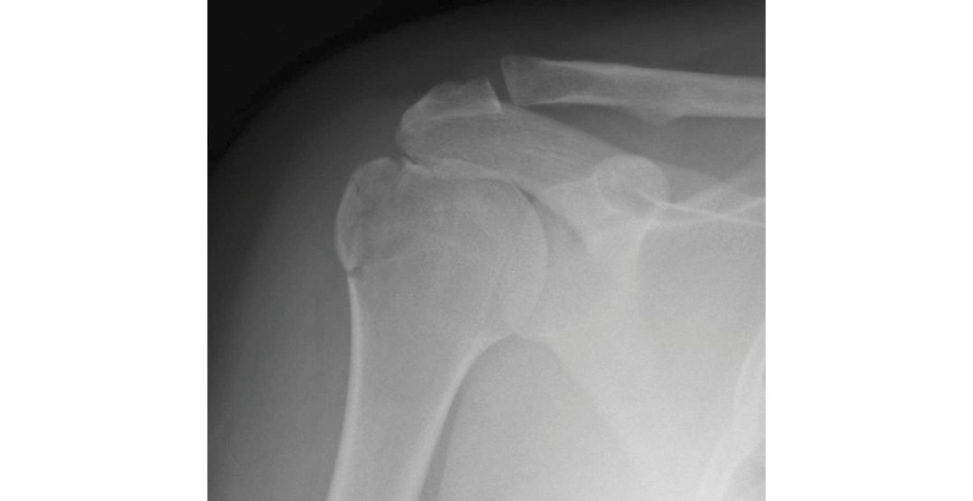
I will arrange a CT scan of the shoulder to assess the degree and direction of displacement as this is useful in borderline cases.6
The CT scan (Figure 12.1d) of the right shoulder shows no humeral neck fracture but significant displacement of the greater tuberosity. What will be your management strategy?
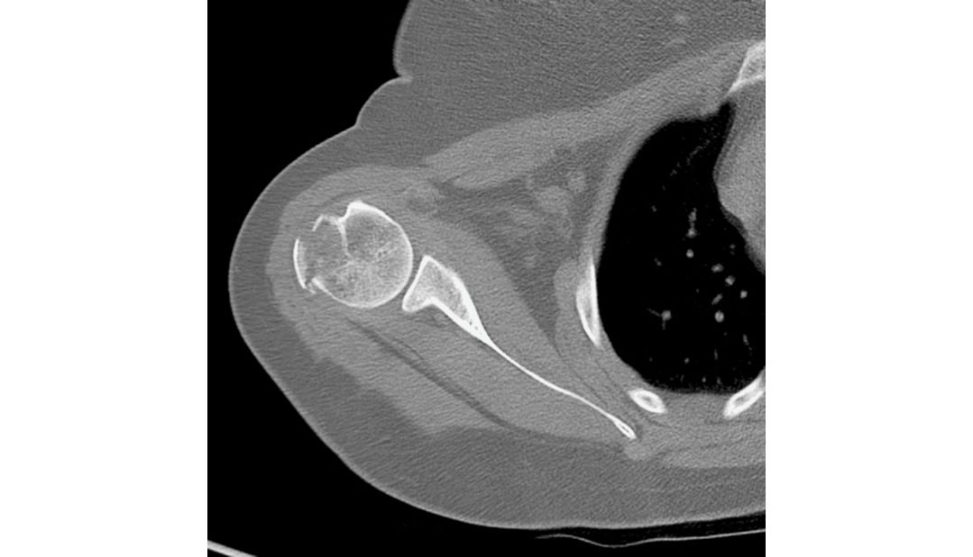
If the greater tuberosity fragment has posterosuperior displacement more than 5 mm,7 I would offer the patient reduction and fixation. 8
What are the risks of non-operativ e management of displaced greater tuberosity fracture?
Non-union, malunion, which effectively narrows the subacromial space, leading to mechanical impingement and consequent rotator cuff atrophy.9
Figure 12.1a Anteroposterior (AP) radiograph of right shoulder demonstrating fr acture/dislocation.
Figure 12.1b II films, relocated right shoulder.
Figure 12.1c Anteroposterior (AP) radiograph, right shoulder with greater tuberosity fracture.
Figure 12.1d CT image, right shoulder.
Structured oral examination question 2#
Right wrist fracture
A 24-year-old man fell down the last few steps of a flight of stairs and sustained an injury to his right wrist. His X-rays are shown in Figure 12.2a. What is this injury?
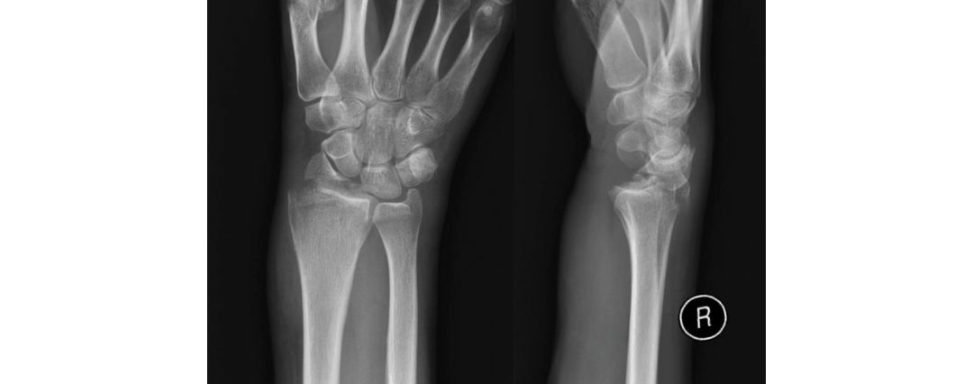
This pattern would be classified by AO as type B2.3 and its pathomechanism is suggested to be an avulsion of the styloid by the radioscaphocapitate ligament.10 On these images there is no visible scaphoid fracture or evidence of scapholunate ligament disruption however, this would be a common association.
What other injuries have occurred in addition to the radial styloid fracture?
allows subluxation of the radiocarpal joint.11 The distal part of the brachioradialis insertion is typically 17 mm from the tip therefore, there is no stabilizing force from the brachioradialis.12
How will you manage this injury?
Assuming it is an isolated closed injury, I will attempt closed reduction under sedation in casualty, apply a below-elbow moulded dorsal plaster slab, check the distal neurovascular status and get a repeat X-ray of the wrist.
Figure 12.2b shows a postreduction X -ray. How will you manage this injury?
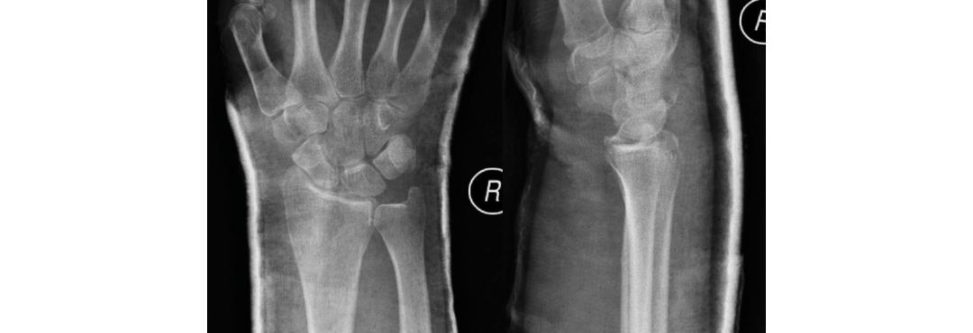
Postreduction X -rays show that the fracture is well reduced, and the radiocarpal alignment is satisfactory. Given that the CT demonstrated < 2 mm articular disruption, no carpal fracture and radiocarpal congruency, I would treat this in a moulded plaster and weekly radiographic follow-up.
Figure 12.2a Anteroposterior (AP) and lateral radiographs, right wrist.
Figure 12.2b Anteroposterior (AP) and lateral postreduction film, right wrist.
Structured oral examination question 3#
Comminuted elbow fracture
A motorbike rider came off his bike at around 80 miles/hour and has sustained an isolated injury to his right elbow. X-rays in casualty are shown in Figure 12.3a.
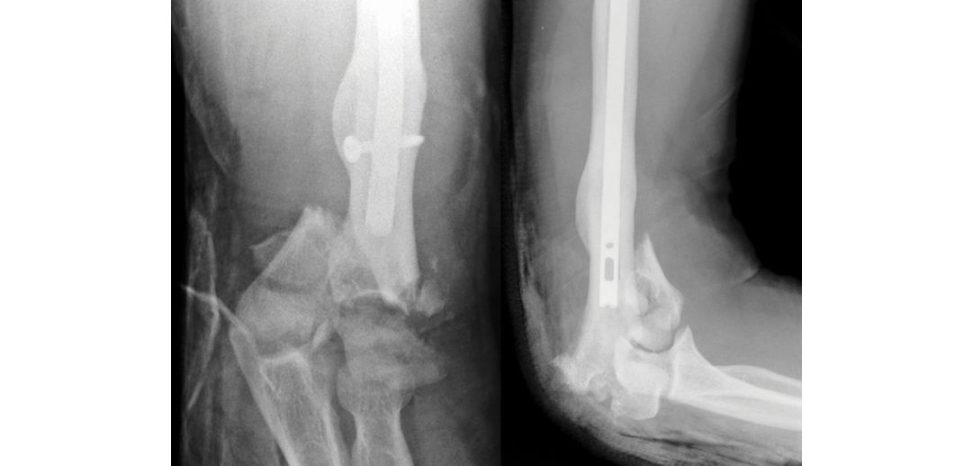
This X-ray of the right elbow demonstrates a bicolumnar distal humerus fracture. There is evidence of a well-healed distal humerus diaphyseal fracture which was stabilized with an intramedullary nail. I will also check if it is an open fracture.
How are these injuries classified?
Intra-articular fractures can be divided into partial or complete according to the AO classification. In type B fractures, a single column is involved while the articular surface of the other column remains incontinuity with the diaphysis – this is ‘partial articular ’.
This is an open fracture. How will you deal with the wound in casualty?
According to BOAST 4 and NICE guidance 37, in conjunction with Orthoplastics input, I will remove gross contamination but not irrigate the wound. I will start the patient on intravenous co-amoxiclav which will continue un til 72 hours after initial debridement or wound closure.
What will be the definitive management and its timing?
This will depend upon vascular status and orthoplastics input. If there is evidence of compartment syndrome, this would warrant immediate fasciotomy. Otherwise, the patient should betaken to theatre by a senior plastic and orthopaedic surgeon on a scheduled trauma list within 24 hours but ideally within 12 hours for high-energy injuries such as this. I would then irrigate the wound with 6 litres of gravity-assisted normal saline. Otherwise I would perform limited fixation of the articular fragments , apply a negativ e-pressure dressing and span the zone of injury with an external fixator.
If the wound is satisfactory and definitive stabilization is planned, how will you go about it?
In an appropriately marked, consented and anaesthetized patient, I would position in a lateral decubitus position. My approach would be posterior under guidance of plastics likely incorporating the existing defect. An olecranon osteotomy would aid visualization of this in tra- articular fracture. If the nail is still in situ, I would plan my fixation around this, although as the old fracture is well healed, removing the nail is an option if this would make fixation or arthroplasty of the new fracture easier. I would use one pre-contoured locking plate on each column. Ensure that every screw went through the plate. Every screw is anchored in a fragment on the other side. Screws should beas longas possible. Distal screws should interdigitate.
How will you stabilize the olecranon osteotomy?
With a traditional apex distal chevron osteotomy, there is increasing evidence that an extra- articulars tep-cut osteotomy may produce a more stable construct with a much higher bone contact surface area.17
This is the postoperative X-ray (Figure 12.3b). What will be your postoperative management?
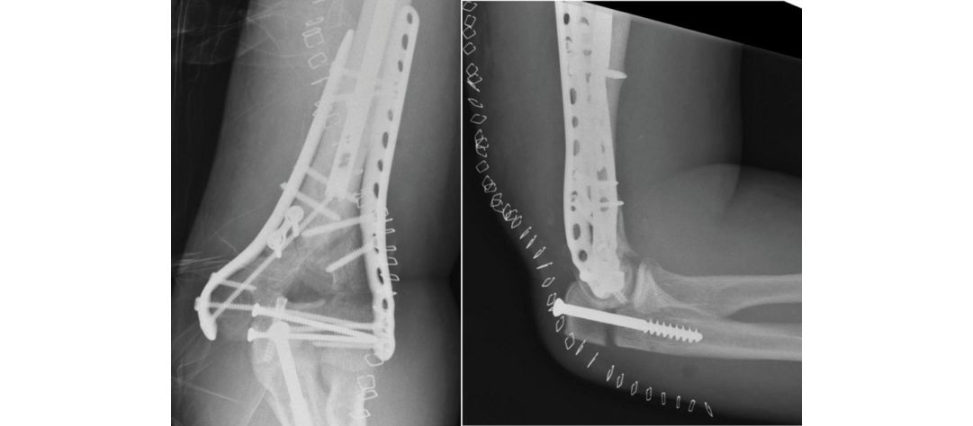
There is stable anatomical fixation of the distal humerus. If there were signs of radiological displacement or clinical non-union, I would revise the fixation using a screw with a washer.
I would consider the use of prophylaxis for heterotopic ossification.
Why not plate the osteotomy?
I would initially try to avoid plate fixation ast here is already a significant amount of metalwork around the elbow.
Figure 12.3a Anteroposterior (AP) and lateral radiographs, right elbow, demonstrating comminuted fracture.
Figure 12.3b Anteroposterior (AP) and lateral radiographs, right elbow, postfixation.
Structured oral examination question 4#
Monteggia fracture
A cyclist was knocked over by a car and he landed on his elbow. This is an isolated injury. His X-rays are shown in Figure 12.4a.
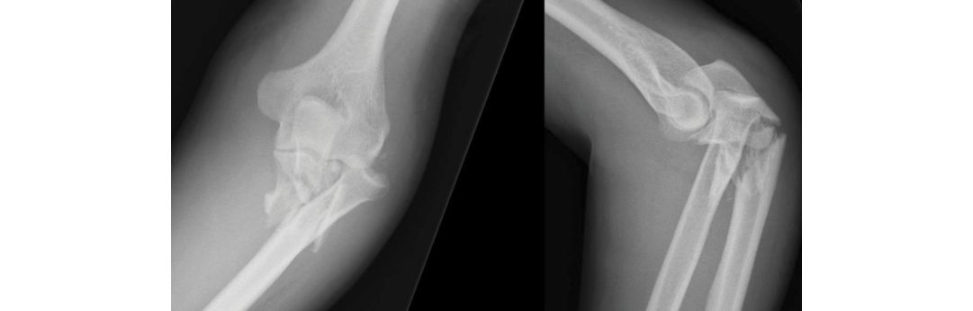
This is a Monteggia fracture–dislocation. This would be classified by Ba doas a Type 2 with disruption a t the proximal radioulnar joint. A radial head fracture is associated with this pattern of injury and should be carefully examined for. As with all high-energy injuries I would assess the neurovascular status for wounds indicating an open injury.
How will you manage this?
I will reduce the fracture in A&E, apply an above-elbow backslab then reassess the neurovascular status and check
Can this fracture be treated non-operativ ely?
The fracture is comminuted and is therefore unstable and will allow further dislocation of the joint with limitation of range of motion. The lateral ulnar collateral ligament is commonly injured with this pattern and may result in instability even if bony alignment is restored. Fixation allows early mobilization and reduced stiffness. I would use the posterior approach and assess for displacement of a coronoid fragment. Stabilization of the coronoid fragment may be achieved via a screw through the plate. I would then assess the range of motion and stability. If the radial head is fractured I would consider fixation or metallic replacement.
What are the causes for the radial head continuing to sublux after ulna fracture stabilization?
Capsuloligamentous, coronoid or radial head deficiency. For posterolateral instability, injury to the lateral ulnar collateral ligament is most likely to play a role. Annular ligament interposition is uncommon.
This is the postoperative X-ray (Figure 12.4b). What will be your postoperative management?
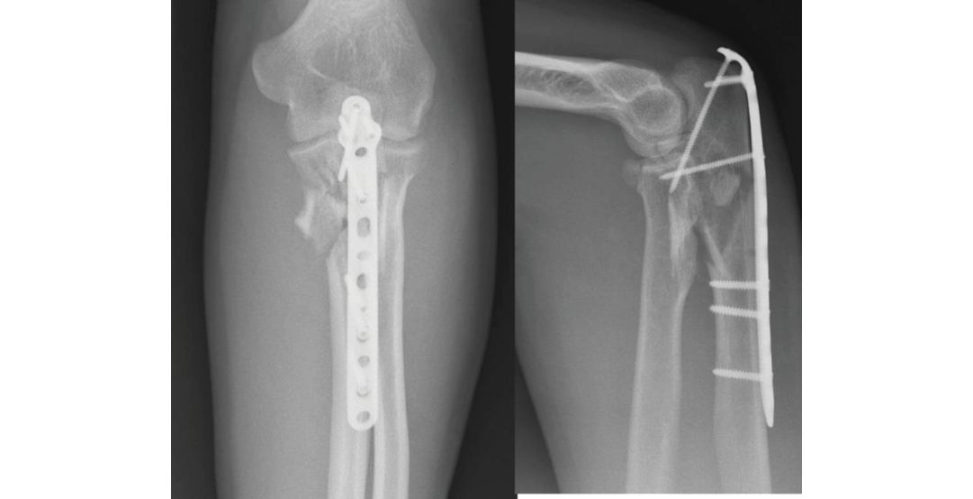
I will protect wound healing with a back-slab for 2 weeks then start physiotherapy with active movement as tolerated to prevent stiffness and f ollow-up the patient to make sure the wound and fracture have healed along with good functional out come.
Figure 12.4a Anteroposterior (AP) and lateral radiographs, Monteggia fracture–dislocation, right elbow.
Figure 12.4b Anteroposterior (AP) and lateral radiographs, right elbow, postfixation.
General reading#
Wong JC, Getz CL, Abboud JA. Adult Monteggia and olecranon fracture dislocations of the elbow Hand
Clin. 2015;31(4):565–580.
Structured oral examination question 5#
Galeazzi fracture
A 23-year-old male while on a night out fellon to his left hand and has come to casualty with pain and deformity. The X-ray of his left distal forearm is shown in Figure 12.5.
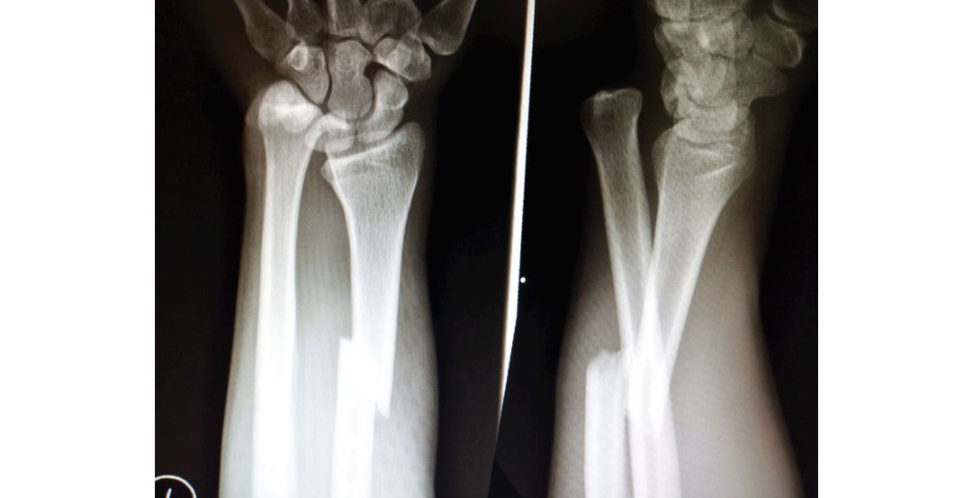
This is a Galeazzi fracture. I will assess the patient with regards to medical conditions, associated injuries, distal neurovascular status and whether it is a closed or open injury.
This is an isolated closed injury with no distal problems. How will you manage this injury?
I will try to reduce the fracture dislocation in casualty under sedation, apply an abo ve-elbow back-slab with the forearm in supination and get an X-ray of the forearm and wrist.
Check X-ray shows no change in position, it is 9 pm. What will you do?
If there are no signs of any neurovascular deficit, I will prioritize the patient in the next day’s trauma list for open reduction and stabilization of radial fracture
How will you fix this fracture?
I would use a dynamic compression plate of the radius through a volar Henry’s approach, aiming for absolute stability.
What are the prerequisites for primary osteonal fracture healing?
Absolute stability at the fracture site with a strain environment less than 2%, perfect reduction with the
During surgery the radius fracture is stabilized, but the distal radioulnar joint is still dislocated. What are the causes for this?
The radius fracture may have been fixed in either a shortened or angulated position. There may be disruption of the TF CC allowing redislocation of the DRU J.
Radius fracture reduction is satisfactory and there is no interposition, but the joint is dislocated. How will you deal with it?
This may be due to an ulnar styloid fracture – if so, I would open this, reduce it and fix using a tension band technique. Otherwise, I would explore the DRUJ via a dorsal approach and repair the TFCC and other soft -tissue restraints.
What will be your postoperative protocol?
He will need the arm in an above-elbow plaster (to immobilize the DRUJ) for around 4 weeks, at which point the K-wires can be removed and he can be put into a splint. A sugar tong splint would protect the DRUJ while allowing some elbow movement.
Figure 12.5 Anteroposterior (AP) and lateral radiographs, left forearm.
Topic reference#
Giannoulis FS, Sotereanos DG. Galeazzi fractures and dislocations . Hand Clin. 2007;23(2):153–163.
Structured oral examination question 6#
Humeral shaft fracture
A 58-year-old man sustained an injury to his arm when he fell from standing height. He is right-handed, suffers from hypertension and has a sedentary lifestyle. His X-rays are shown in Figure 12.6a.
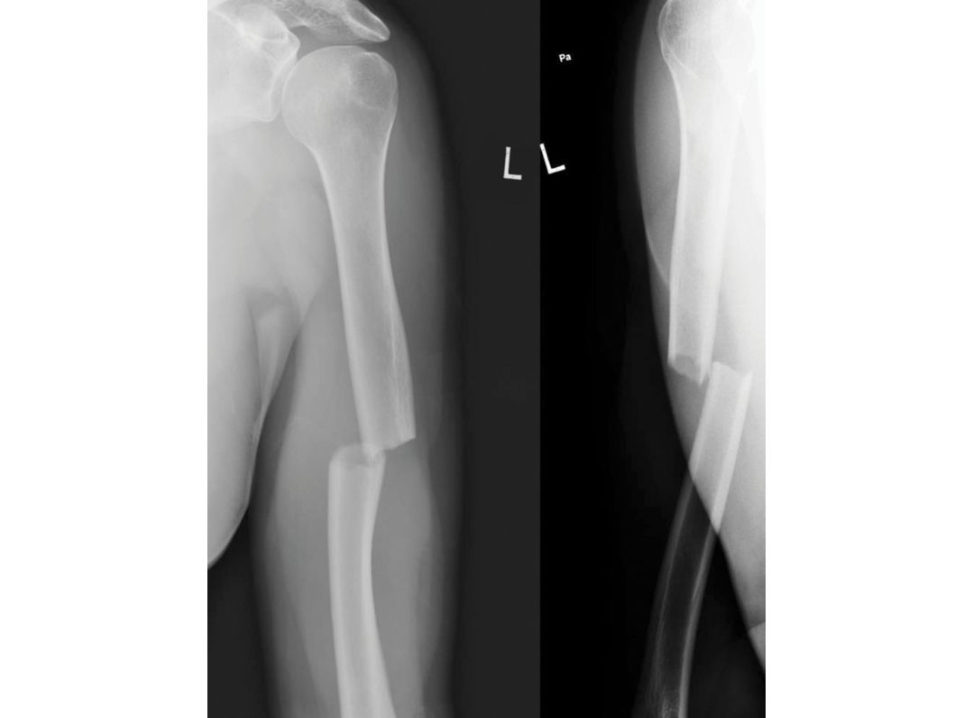
The X-rays show a simple transverse fracture of the right humeral shaft in the middle third, distal to the deltoid tubercle. I will check for other injuries, neurovascular status and whether it is a closed or open fracture.
It is a closed fracture with no associated problems. How will you manage it?
In casualty, I will apply a U-slab, then check for distal neurovascular status and get a check X- ray. Internal fixation would allow earlier mobilization and is one of the indications for surgery.
What will you do once the humeral brace is applied?
I will get a check X-ray to ensure the fracture has not displaced, then I will monitor the position with weekly serial radiographs for 3 weeks.
At 2 weeks the repeat radiograph (Figure 12.6b) shows some distraction a t the fracture site, what will you do?
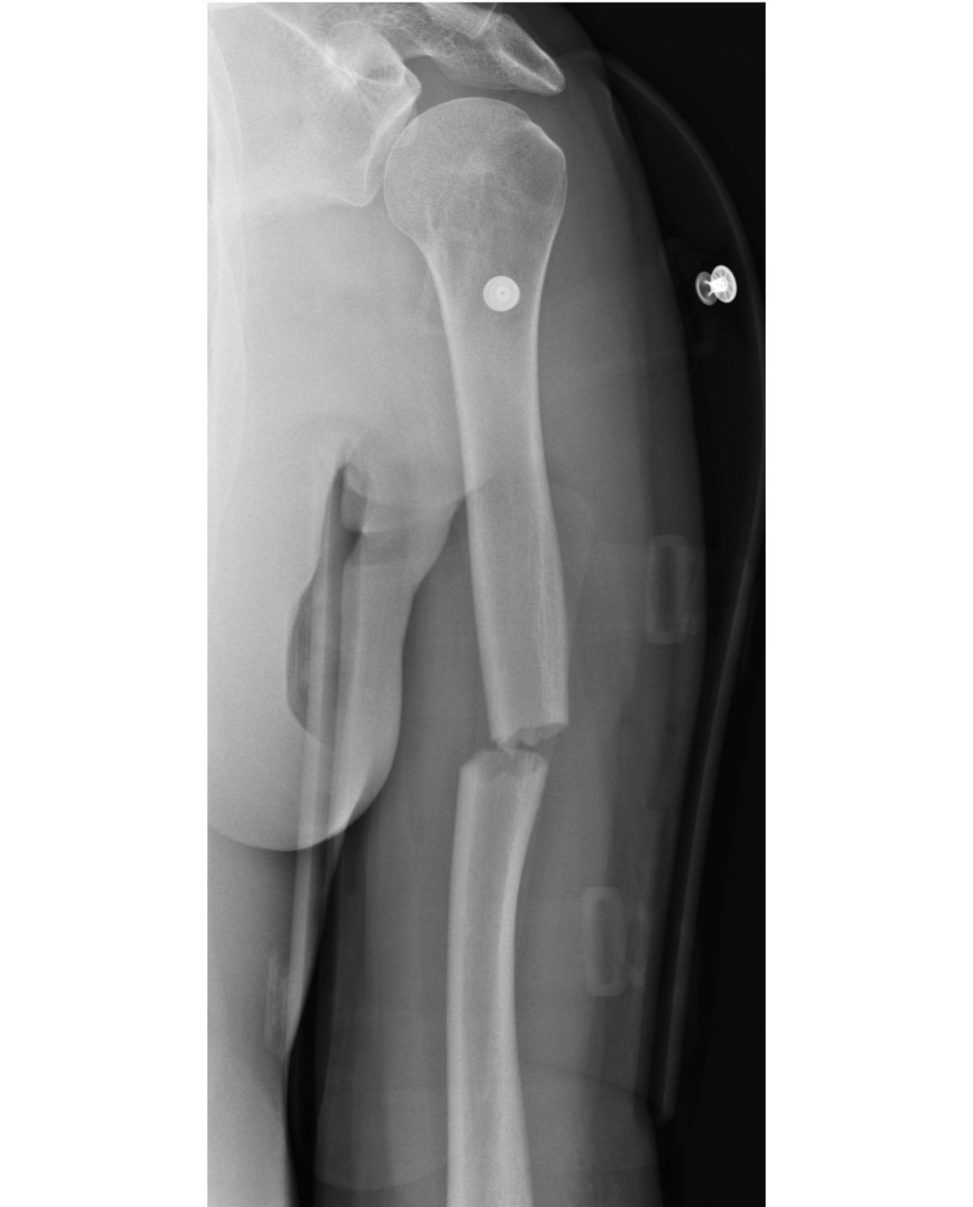
I will explain that the rate of non-union may be as high as 20% with non-operativ e and 10% with fixation. The fracture is transverse, the contact area is small; therefore, this fracture may be at a higher risk of non-union.
The patient does not want to wait and see. He is in a lot of pain and is struggling with the humeral brace. He is keen for fixation. What will you do?
I will discuss with the patient the advantages and risks involved inoperative fixation of humeral fractures. There are, however, risks of iatrogenic radial nerve injury, infection stiffness, implant failure and CRPS.
What operative intervention will you undertake?
Plate or nail fixation is possible, but I would offer plate fixation using a large fragment DC Pas this
This is the X-ray at 3 months (Figure 12.6c). What will you do?
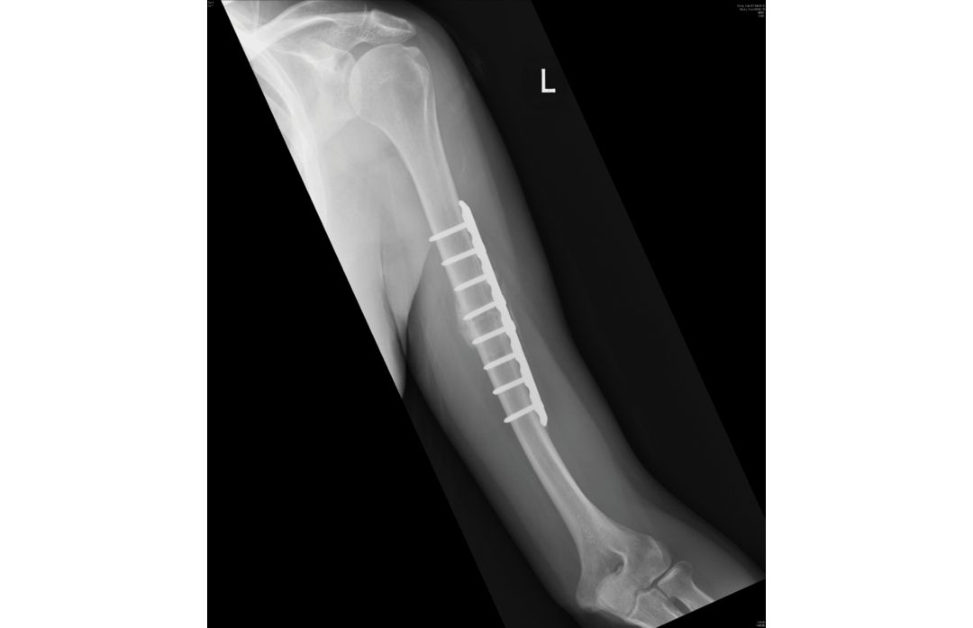
My first aim will be to rule out infection. I will also perform bloodtests – FBC, CRP.
The patient has no symptoms and is happy with progress with physiotherapy. Why do you suspect infection?
In a plate fixation, absolute stability is the aim. This means that the fracture will heal by primary intention. Although external callus can occur in plate fixations, in these circumstances the stiffness of the construct is lower and is flexible enough to allow secondary fracture healing as the working length is longer. A perfectly plated Swiss fracture does not go through endochondral repair.
Figure 12.6a Anteroposterior (AP) and lateral radiographs, transverse fractured left humerus.
Figure 12.6b Anteroposterior (AP) radiograph, distracted left humerus fracture.
Figure 12.6c Anteroposterior (AP) radiograph, non-union left humerus fracture post-plate fixation.
Structured oral examination question 7#
Clavicle fracture
A 70-year-old female falls awkwardly on to her left side and presents with pain and bruising to her shoulder.
There is evidence of a buft erfly fragment, and there is overlap of the bone ends indicating shortening. I would assess for any neurovascular deficit and assess the skin for any skin tenting.
How would you manage this patient?
I would discuss the pros and cons of conservative vs. surgical management. The potential advantages of surgery
What factors are predictive of a poor outcome with conservative management?
Smoking is the most strongly associated factor along with comminution and displacement. Robinson has demonstrated that the risk of non-union can be predicted according to independent risk factors of comminution and displacement in an older female.20 More recently, elevated PROMs at 6 weeks have also been demonstrated to be predictive of non-union.21 This information is invaluable in helping patients to decide whether to opt for surgery.
How would you fix this fracture?
I would use plate fixation as this has been demonstrated to have a lower rate of non-union than intramedullary fixation in comminuted fractures.23 In an appropriately marked and consented patient, I would position them in a beach chair position with the arm prepped . I would use a ‘necklace’ incision as this provides a more satisfactory scar.
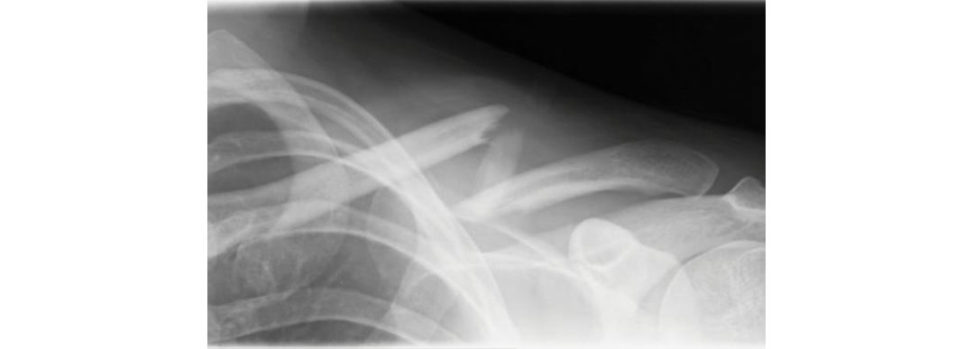
Figure 12.7 Anteroposterior (AP) radiograph, mid-shaft fractured left clavicle.
Structured oral examination question 8#
ACJ dislocation
A 25-year-old rugby player landed heavily onto the tip of his shoulder and is now complaining of pain on moving his shoulder – what can you see (Figure 12.8)?
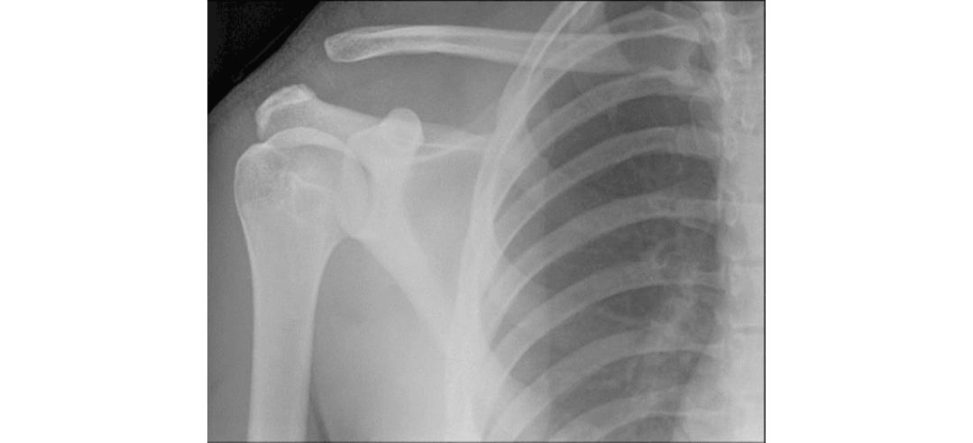
I would classify this as type 3 according to Rockwood, although the interobserver reliability of this system is limited.24 Therefore, it is important to assess stability clinically – the cross-arm adduction (sc arf) test may demonstrate painful posterior instability and this is an indication for surgery.
What is the sequence of pathoanatomy in ACJ injuries?
Initially the reis a sprain of the AC ligaments. Next the AC ligaments rupture and there is a sprain of the coracoclavicular (CC) ligaments allowing subluxation of the joint. Rarely, the clavicle can also displace inferiorly.
How would you manage this patient?
As previously mentioned, it is important to assess stability. In a stable injury I would manage this patient conservatively with a sling for 2 weeks followed by mobilization. The natural history for type 3 injuries has demonstrated that although there may be a permanent cosmetics tep-off (although this needs to be balanced with a surgical scar), the functional
What are the other surgical options and how do their outcomes compare?
The modified Weaver–Dunn technique has largely been superseded by anatomical reconstruction techniques, of which multiple studies have demonstrated superior PROMs data and a lower loss of reduction.
What are the indications for operative intervention?
Otherwise, the consensus is that types 4, 5 and 6 should be managed operatively in order to reduce the ACJ where the clavicle may have buft on-holed through fascia or lie subcutaneously.28 The art of managing these injuries is differentiating between type 3 and type 5 injuries, which may have very similar radiographs.
Have you heard about LARS reconstruction?
LARS is a synthetic ligament augmentation and reconstruction device. The fixation is via two tunnels and not an over-the-top approach, thus reducing clavicular erosions. Two tunnels are drilled in the clavicle either side of the coracoid process. The ends of the ligament are trimmed flush to the clavicle in order to avoid any irritating projections.
Figure 12.8 ACJ dislocation. The reis marked widening of the ACJ space with the distal clavicle positioned superior to the superior border of the acromion and a marked increase in the coracoclavicular distance.
Structured oral examination question 9#
Proximal humerus fracture
This 65-year-old lady has fallen onto her right side and sustained the following injury (Figure 12.9).
This is an AP radiograph of the left shoulder demonstrating a tw o-part, varus displaced, surgical neck of humerus fracture. I would take a history and examine the patient looking for evidence of neurovascular deficit – particularly in the axillary nerve. This fracture could be classified according to Neer, although the reliability and clinical relevance of this system has been demonstrated to be limited.
What other factors affect the prognosis of these fractures?
These are a medial metaphyseal extensionless than 8 mm, medial hinge displacement more than 2 mm and fracture patterns involving the anatomic neck.
What is the blood supply of the humeral head?
The classical understanding of the vascularity was that the anterior circumflex artery was the dominant supply via the arcuate artery.
How will you manage this patient?
I would discuss the options with regards to the fracture pattern, the patient’s comorbidities and functional expectations. In addition, the fracture patterns were categorized according to Neer rather than pathomorphology, and therefore it is difficult to differentiate whether there is a subgroup which would benefit from surgery. It is accepted that fracture morphology influences the decision whether to operate.32 Given that a residual varus deformity is associated with poor functional out comes,33 I would give this patient the option of ORIF .
What if you take this patient for ORIF and find that it is difficult to reconstruct?
In a fit and active 65-year-old patient, I would persist with fixation given that arthroplasty doesn’t have fantastic outcomes, and, in this age group, is likely to require revision; there is also evidence that reverse arthroplasty after failed ORIF still has reliable outcomes.34 If it was decided that a similar fracture was notre constructable then arthroplasty should be considered.
Figure 12.9 Anteroposterior (AP) radiograph of varus proximal humerus fracture.
Structured oral examination question 10#
A man presents to your fracture clinic complaining of pain in the antecubital fossa of the elbow and weakness of his biceps 4 weeks after injuring it at the gym. What is the likely diagnosis and how would you assess the patient?
In addition, I would assess the neurovascular status of the arm and perform a hook testI would take a history looking for risk factors such as anabolic steroid use and smoking.
Why might the hook test be difficult to interpret, and the muscle belly retraction be minimal?
In addition, the lacertus fibro sus may tether the tendon. In this situation, I would request an MR Ito clarify the diagnosis and assess for tendon retraction.
The MRI demonstrates a partial t ear.
Non-oper at ive management is an option in this situation; however, in the active patient pain symptoms may be persistent. There is a high rate of satisfaction reported for this approach.36
How would you approach this?
I would use a single-incision technique to relocate and fix the distal biceps tendon to the radial tuberosity. A number of fixation techniques are described, although acor tical buft on has demonstrated lower complication rate than suture anchors or transosseous screws.37 In this case, I would use a transverse incision over the
What complications are seen with this procedure?
Nerve injury is most commonly seen. The lateral antebrachial cutaneous nerve is most frequently affected followed by the posterior interosseous nerve and the superficial radial nerve. 38
Notes
1. Kim E, Shin HK, Kim CH. Characteristics of anis ola ted greater tuberosity fracture of the humerus. J Orthop Sci. 2005;10(5):441–444.
2. Groh GI, Rockwood CA. The terrible triad: anterior dislocation of the shoulder associated with rupture
A systematic comparison of the closed shoulder reduction techniques. Arch Orthop Trauma Surg 2017;137(5):589–599.
4. A systematic comparison of the closed shoulder reduction techniques. 2017;137(5):589–599.
5. Rouleau DM, Mutch J, Laflamme GY. J Am Acad Orthop Surg. 2016;24(1):46–56.
6. Janssen SJ, Hermanussen HH, Guift on TG, van den Bekerom MP, van Deurzen DF, Ring D. Clin Orthop Rel Res. 2016;474(5):1257–1265.
7. Verdano MA, Alia niD, Pellegrini ABa udi P, Pedrazzi G, Ceccarelli F. An analysis of displacement in greater tuberosity fractures. 2014;84(3):219–228.
Is arthroscopic technique superior to open reduction internal fixation in the treatment of isolated displaced greater tuberosity fractures.
9. Verdano MA, Alia niD, Pellegrini ABa udi P, Pedrazzi G, Ceccarelli F. An analysis of displacement in greater tuberosity fractures. 2014;84(3):219–228.
10. A systematic comparison of the closed shoulder reduction techniques. 2017;137(5):589–599.
11. Reichel LM, Bell BR, Michnick SM, Reitman CA. Radial styloid fractures. J Hand Surg. 2012;37(8):1726–1741.
12. Koh SAnder sen CR, Buford WL, Patterson RM, Viegas SF. J Hand Surg. 2006;31(1):2–8.
13. Ko muraS, Yokoi T, Nonomura H, Tanahashi HS atake T, Watanabe N. J Hand Surg. 2012;37(3):469–476.
14. Ilya sAM, Mudgal CS. Radiocarpal fracture–dislocations . J Am Acad Orthop Surg. 2008;16(11):647– 655.
15. O’Driscoll SW. Optimizing stability in distal humeral fracture fixation . J Shoulder Elbow Surg. 2005;14(1):S186–194.
Determining the efficacy of screw and washer fixation as a method for securing olecranon osteotomies used in the surgical management of intraarticular distal humerus fractures.
17. Zumstein MA, Rani gaS, Flueckiger R, Campana L, Moor BK. J Shoulder Elbow Surg. 2017;26(9):1620–1628.
18. Clement ND. Management of humeral shaft fractures; non-operativ e versus operative Arch Trauma Res. 2015;4(2):e28013.
19. Canadian OT. A multic enter, randomized clinical trial. J Bone Joint Surg Am. 2007;89(1):1.
20. Robinson CM, McQueen MM, Wakefield AE. J Bone Joint Surg. 2004;86(7):1359–1365.
Smoking status and the Disabilities of the Arm Shoulder and Hand sc ore are early predictors of symptomatic nonunion of displaced midshaft fractures of the clavicle.
The influence of shortening on clinical outcome in healed displaced midshaft clavicular fractures after nonoperative treatment.
Plate versus intramedullary fixation of two-part and multi fragmentary displaced midshaft clavicle fractures – a long-term analysis.
24. Ringenberg JD, Foughty Z, Hall AD, Aldridge JM, Wilson JB, Kuremsky MA. J Shoulder Elbow Surg. 2018;27(3):538–544.
25. Schlegel TF, Burks RT, Marcus RLD unn HK. Am J Sports Med. 2001;29(6):699–703.
26. Mah JM. General health status after nonoperative versus operative treatment for acute, complete acromioclavicular
Palmaris longus tendon graft versus modified Weaver–Dunn procedure via dynamic buft on system for acromioclavicular joint reconstruction in chronic cases.
28. Li X, MaR, Be diA, Dines DM, Altchek DW, Dines JS. Management of acromioclavicular joint injuries. J Bone Joint Surg. 2014;96(1):73–84.
29. Gracitelli MED oft a TA, Assunção JH, et al. J Shoulder Elbow Surg. 2017;26(6):1097– 1102.
30. Hetirich CM, Boraiah S, Dyke JP, Neviaser A, Helfet DL, Lorich DG. 2010;92(4):943–948.
31. Handoll H, Brealey S, Rang anA, et al. The ProFHER (PROximal Fracture of the Humerus: Evaluation by Randomisation) trial – a pragmatic multi centre randomised controlled trial evaluating the
32. Gracitelli MED oft a TA, Assunção JH, et al. J Shoulder Elbow Surg. 2017;26(6):1097– 1102.
33. Südkamp NP, Audigé L, LambertS, Hertel R, Konrad G. J Shoulder Elbow Surg. 2011;20(8):1207–1216.
Reverse shoulder arthroplasty for proximal humeral fractures: outcomes comparing primary reverse arthroplasty for fracture versus reverse arthroplasty after failed osteosynthesis.
35. Shukla DR, McAnany S, Kim J, Over leyS, Parsons BO. J Shoulder Elbow Surg. 2016;25(2):330–340.
36. Behun MA, Geeslin AG, O’Hagan EC, King JC. J Hand Surg. 2016;41(7):e175–189.
37. Watson JN, Moreƫ VM, Schwindel L, Hutchinson MR. J Bone Joint Surg. 2014;96(24):2086–2090.
38. Panagopoulos A, Tatani I, Tsoumpos P, Ntourantonis D, Pantazis K, Triantafyllopoulos IK. J Sports Med. 2016;2016.
39. Lund F. Fractures of the radius in starting automobiles. Boston Med Surg J. 1904;151:481–483.