Chapter 13 Upper limb trauma II
Structured oral examination question 1#
Lunate dislocation
What do these radiographs (Figures 13.1a and 13.1b) show?
These are PA and lateral radiographs of a wrist showing a lunate dislocation.
What signs are there on the radiographs which point to this diagnosis?
There is disruption of Gil ulas lines on both views. The lunate can beseen siting palmarly in the carpal tunnel.
What do you suppose was the mechanism of injury?
This is usually caused by high-energy trauma such as a road traffic collision or a fall from a height.
Why do you infer that?
This is a hyperextension injury in ulnar deviation: aMay field stage 4; Lower-energy hyperextension injuries might result in scapholunate ligament injury; this patient must have torn the scapholunate ligament; dislocated the lunocapitate joint.
How will you manage this injury?
This patient has sustained high-energy trauma, so first I would treat any life-threatening injuries. This needs an emergent reduction in A&E.
How will you reduce it?
Before reduction I would assess and document the neurovascular status of the hand with particular attention to the median nerve. The patient needs to be relaxed and sedated. I would then reassess and document the neurovascular status, apply a below-elbow plaster backslab and obtain plain radiographs to confirm reduction.
What if you can’t reduce it?
Ideally this should be done by someone who can proceed to definitive fixation, but reduction should not be delayed for this as it is imperative that the dislocation is reduced to protect the neurovascular structures.
How will you open the wrist?
If I still cannot reduce the dislocation, I will open the dorsum of the wrist. I would incise the third extensor compartment, lift EPL from its bed, then dissect into compartments 2 and 4 to reveal the dorsal carpal ligaments. I would then use a Berger flap to open the wrist joint.
Can you describe the Berger flap?
When elevating the flap, it is important to protect the intrinsic carpal ligaments, particularly the sc apholunate ligament which is most significant dorsally, although in this case I expect it to betorn.
OK, so let’s assume you are a hand surgeon and are prepared to manage this definitively. How will you proceed?
I would first reduce the carpus, by direct means if necessary, and assess the damage. I expect the scapholunate ligament and lunotriquetral ligaments to betorn. I would need to stabilize the carpal bones in their normal orientation using K -wires as joysticks and further K-wires to transfix the carpus. I would anticipate a rent in the volar capsule in conjunction with avo lar lunotriquetral ligament tear which I would repair directly with sutures.
What are the long-term outcomes of this injury?
As longas it was treated promptly, I would expect the median nerve to make a full recovery, although this is not guaranteed and depends on the degree of primary injury. Further surgery is required to remove the K-wires at 8 weeks, then intensive physiotherapy will be required to optimize function.
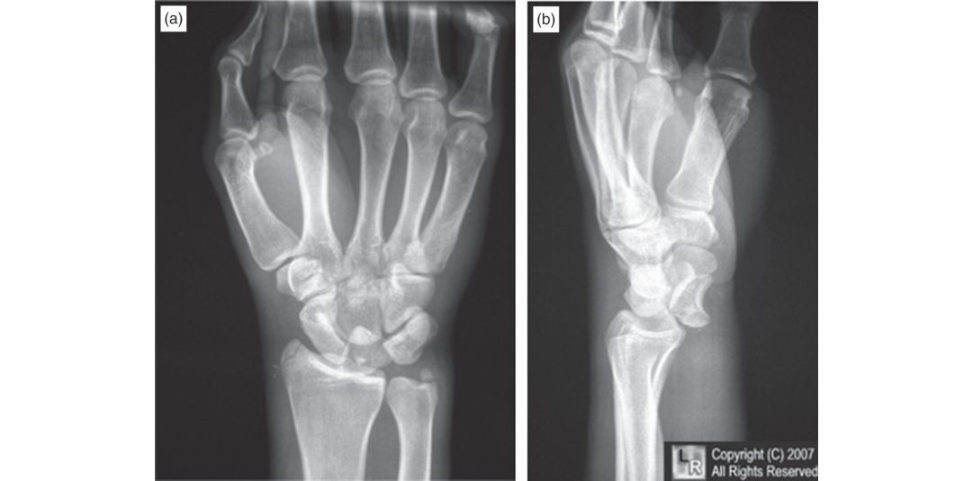
Figure 13.1a and 13.1b Posteroanterior (PA) and lateral radiographs, lunate dislocation.
References#
Capo JT, Corft SJ, Shamian B, et al. Treatment of dorsal perilunate dislocations and fr acture–dislocations using a standardized protocol. Hand (NY). 2012;7(4):380–387.
Berger RA, Bishop AT, Be tinger PC. New dorsal capsulotomy for the surgical exposure of the wrist. Ann
Plast Surg. 1995;35(1):54–59.
Structured oral examination question 2#
Jersey finger
This 15-year-old boy noticed that he couldn’t flex the end of his ring finger after a rugby match. What does the radiograph (Figure 13.2) show?
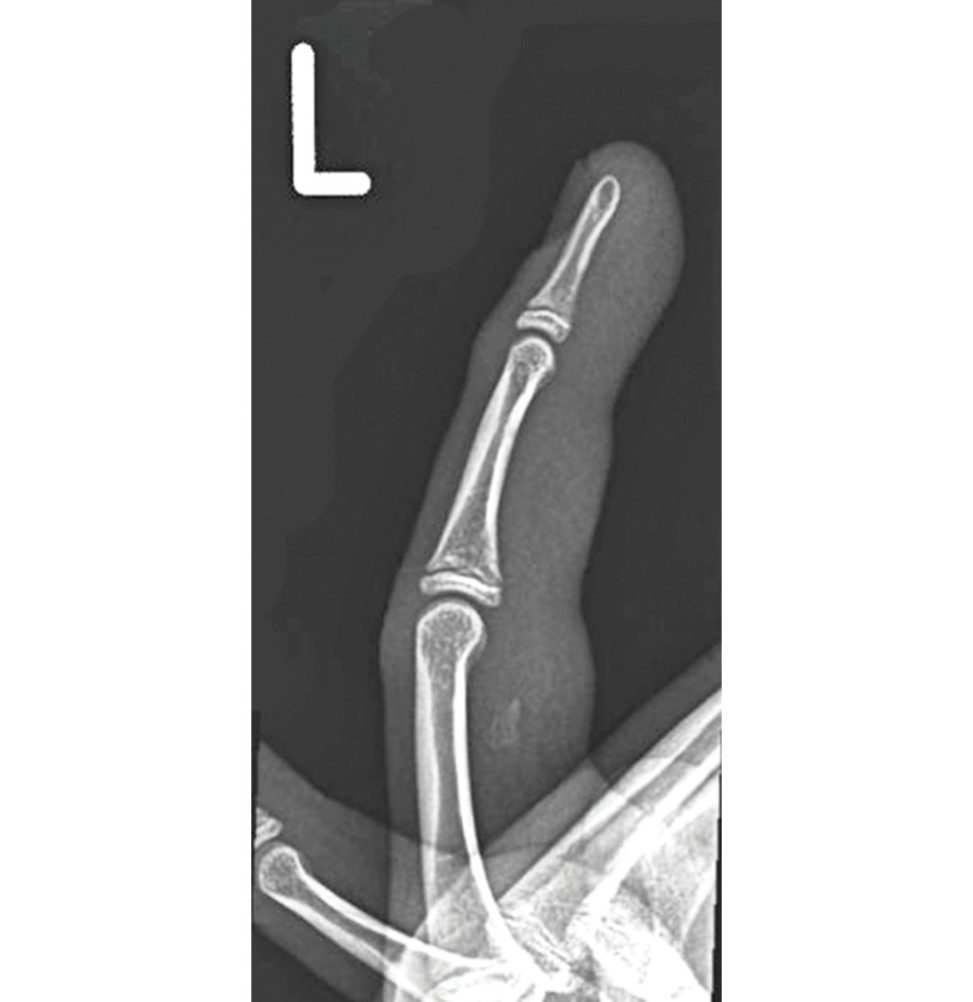
This is a lateral radiograph of a finger with a small avulsed fragment of bone siting volar to the proximal phalanx.
What is the typical mechanism of injury?
An extension force is applied to the finger while inactive flexion.
What is the anatomy of the flexor mechanism to the ring finger?
There are two flexor tendons. The FDS has its origin from the medial elbow and the radius. Each tendon has its own muscle belly. The tendon splits into two and inserts into the base of the middle phalanx.
What is the innervation of these muscles?
The median nerve supplies all FDS and, via the AIN, the radial two FDPs. The ulnar nerve supplies the ulnar FDPs.
How would you classify this injury?
Grade 1 retracts to the palm, grade 2 to the PIPJ, grade 3 involves a large fragment which sticks at the DIPJ, and grade 4 involves an avulsed fragment of bone which dissociates from the tendon, a so-called ‘double avulsion’.
In this grade 2 injury, what is preventing further proximal migration of the fragment?
The vinculae.
How will you treat this young man?
I would counsel him that there is a prolonged recovery period involving splintage and physiotherapy for around 3 months Alternatively, he may opt for non-operativ e management andre hab the finger with physiotherapy, accepting that active flexion will remain absent at the DIPJ.
What other possible sequel is there of treating this non-oper ativ ely?
He may develop a lumbrical plus finger.
What does that mean?
The function of the lumbricalis to flex the MCP joint and extend the IP joints. The patient cannot actively flex the DIP joint due to the avulsion, but also struggles to flex the PIP joint with FDS due to the intrinsic tightness.
What technique would you use to repair his tendon?
I would identify the avulsed tendon and deliver it through the pulley system back to the footprint. I expect I may need to vent the pulley system and would probably need to fully release A3 but would take care not to release all of either A2 or A4 as these are the key restraints to prevent bowstringing.
How would you anchor the tendon to the bone?
The bony fragment is too small to fix directly, but I wouldn’t excise it as it may improve the healing potential a t the insertion site.
What is the quadregia effect?
If the FDP to the operated finger is repaired too tight, as the patient attempts to make a fist, the operated finger contacts the palm first.
How would youre hab the patient after his tendon repair?
He needs early hand therapy with an early active motion protocol. This is to protect the repair and prevent adhesions forming.
Do you know of any evidence showing superiority of early active motion over static or passive protocols?
There was a systematic review by Staret al. published in the American Journal of Hand Surgery in 2013. They reported a higher risk of finger stiffness in the passive protocols and a higher risk of tendon rupture in early active motion protocols. Despite this, they suggested that modern improvements in surgical technique, materials, and rehabilitation now allow for early active motion rehabilitation that can provide better postoperative motion while maintaining low rupture rates.
Figure 13.2 Lateral radiograph, ring finger.
References#
Khor WS, Langer MF, Wong R, Zhou R, Peck F, Wong JK. Improving outcomes in tendon repair: a critical look at the evidence for flexor tendon repair and rehabilitation. Plast Reconstr Surg. 2016;138(6):1045e–1058e.
Starr HM, Snoddy M, Hammond KE, Seiler JG. Flexor tendon repair rehabilitation protocols: a systematic review. J Hand Surg Am. 2013;38(9):1712–1717.
Structured oral examination question 3#
Scaphoid fracture
This gentleman slipped on ice and fell onto his outstretched hand. What do the radiographs show (Figure 13.3)?
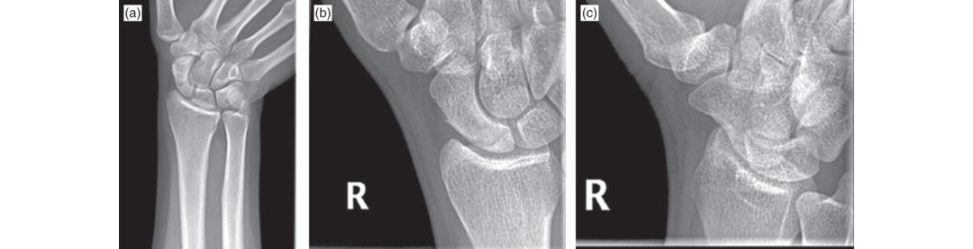
These scaphoid views demonstrate a fracture of the proximal pole of the scaphoid.
What position do you expect the wrist was in when the bone fractured?
Extended and radially deviated.
What would you expect to findon examination?
I would expect pain on the radial side of the wrist, with tenderness over the scaphoid tubercle and in the anatomical snutio x.
So, if he had presented as you describe but with normal scaphoid views, would you assume there was no fracture?
I would manage him in a below-elbow plaster and see him again in 1–2 weeks for further clinical assessment.
You work in a unit where it takes 6 weeks to get an urgent MRI scan. Would a CT scan suffice?
A CT scan would detect most scaphoid fractures, but the sensitivity for acute fractures is not as good as MRI.
OK, so back to our original scenario with an acute proximal pole fracture. How will you manage him?
Fractures of the proximal fitih of the scaphoid have a very high non-union rate approaching 100%.
Why is there such a high non-union rate with proximal fractures?
It comes via the dorsal carpal branch of the radial artery in a retrograde direction.
How would you fix the fracture?
Following appropriate consent and anaesthesia, I would utilize a dorsal approach to the scaphoid. I would make a straight incision starting a t Lister’s tubercle and extending distally for about 4 cm. I would incise the third compartment to expose EP Land retract it radially with the ECRB andE CRL tendons. I would then place a guidewire through the centre of the fracture fragment and fix it to the main body of the scaphoid with a differential pitch screw to apply compression.
It’s now 6 months later and the patient is still in some pain and has difficulty using the wrist in his work as a postman. The plain films show no signs of union. What will you do?
If there is none I would consider revision surgery with a vascularized bone graft.
Why is it important to achieve union with a scaphoid fracture?
In any case, if the fracture does not unite there is a high risk of the patient developing symptomatic degenerative changes in the wrist known as scaphoid non-union advanced collapse or SNAC.
What if the CT showed partial union of the scaphoid?
I would allow the patient to mobilize but to avoid contact sports. I would arrange a follow-up CT in 3 months’ timet o confirm union. Singh et al. published a study in 2005 in which a group of patients with partially united scaphoid fractures went on to unite.
Figure 13.3a, 13.3b and 13.3c Right scaphoid series.
References#
Strauch RJ. Scapholunate advanced collapse and scaphoid nonunion advanced collapse arthritis – update on evaluation and treatment. J Hand Surg Am. 2011;36(4):729–735.
Singh HP, Forward D, Davis TR, Dawson JS, Oni JA, Downing ND. Partial union of acute scaphoid fractures.
J Hand Surg Br. 2005;30(5):440–445.
Structured oral examination question 4#
Mallet finger
This 34-year-old lady presents to you with an injury to the tip of the middle finger sustained when she was struck on the end of the finger by a basketball during a game. What does the photograph (Figure 13.4a) show?
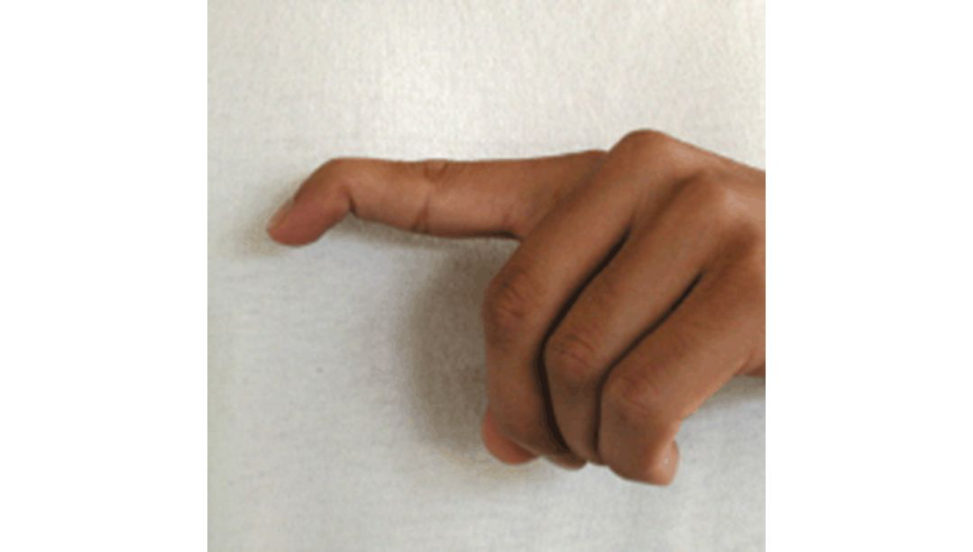
This is a clinical photograph showing the fingers of the left hand viewed from the ulnar side.
What is a mallet finger?
This is when the extensor mechanism to the distal phalanx has been disrupted.
How would you differentiate the two?
but I would obtain radiographs to differentiate the two and to characterize any fracture.
Why do you need to differentiate the two?
This would affect my management. Also, if there is a bony mallet it is important to establish whether there is any subluxation of the joint which would indicate surgery.
Here is a radiograph of this ladyfinger (Figure 13.4b). What does it show?
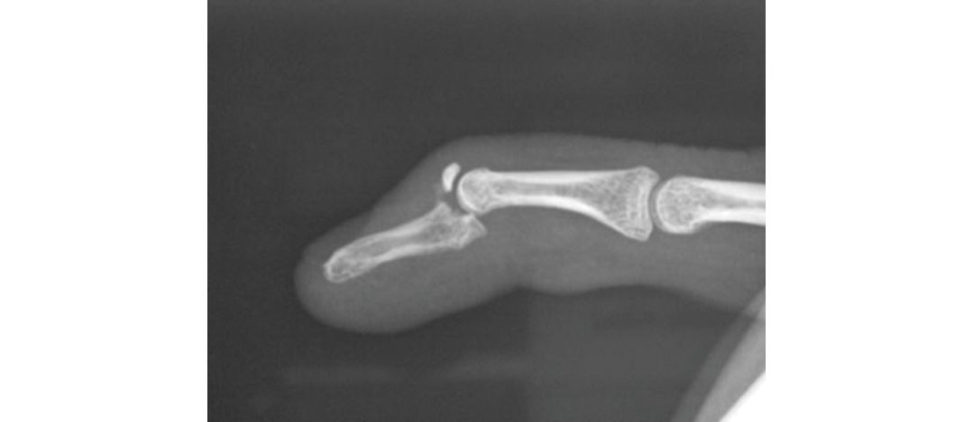
a flexion deformity at the DIPJ and subluxation of the DIP J palmarly.
How would you manage this injury?
If the joint congruity is restored, I would X-ray her weekly for 3 weeks to ensure the reduction was maintained. Assuming it doesnt slip, I would leave it in a splint constantly for 4 weeks, then at night and during risky activities for a further 4 weeks.
What if you couldn’t achieve a satisfactory reduction?
I would advocate reducing the joint and maintaining the reduction surgically. I would leave these wires proud for removal in clinic 4 weeks later.
Do you know any classification systems for this injury?
Type 2 is open. Type 3 is open with skin and tendon loss. Type 4 is a mallet fracture such as this one.
Type 4 is subdivided into (A) physeal fractures in children, (B) fractures 20–50% articular surface and
(C) more than 50% joint surface. This would be a C.
What are the potential complications of this injury?
An extensor lag is common but rarely significant enough to cause symptoms.
Figure 13.4a Clinical picture of mallet finger.
Figure 13.4b Lateral radiograph of bony mallet finger deformity.
Reference#
Sheth U. Mallet finger. Retrieved from www.orthobullets.com/hand/6014/mallet-finger
Ishiguro T, Itoh Y, Ya beY, Hashizume N. Extension block with Kirschner wire for fracture dislocation of the distal interphalangeal joint. Tech Hand Upper Extrem Surg. 1997;1:95–102.
Structured oral examination question 5#
Animal bite
A lady presents to you with a cat bite on the index finger that was sustained when she was breaking up a fight between two cats. There are puncture wounds over the palmar and dorsal surface of the index finger, which is swollen and red (Figure 13.5). What key findings are you looking for on examination?
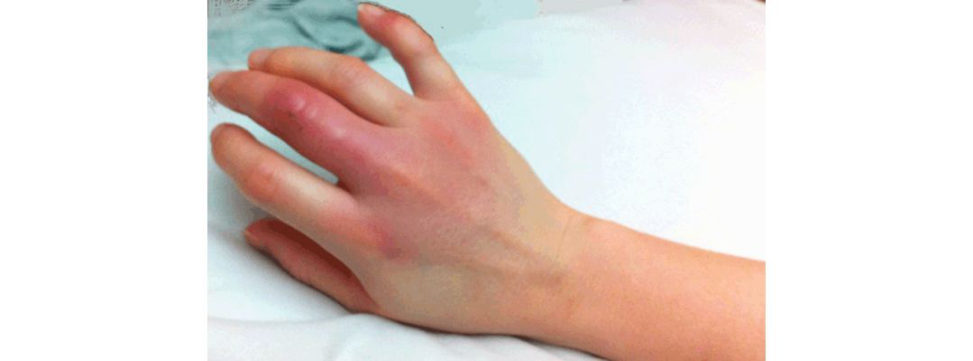
I would look for signs of injury to the neurovascular and.
How would you diagnose flexor sheath infection clinically?
I would look for Kanavel’s signs.
What is the classic organism that causes infection with c at bites?
Pasteurella multocida is classically associated with cat bites.
Let’s say you find convincing signs of flexor sheath infection. How would you manage this?
This is a surgical emergency. The patient needs to go to theatre as soon as possible, ideally within 6 hours, for a washout of the flexor sheath. I would immediately elevate the limb in a Bradford sling.
Talk me through your surgical technique.
I would not exsanguinate the limb forfear of driving infection proximally. I would open the region of the A1 pulley with an oblique incision in the palm, retract the neurovascular structures, open the flexor sheath proximally and take a sample of pus or fluid from the sheath. I would keep the patient on IV antibiotics and elevation and take them back to theatre for a second look and closure at 24– 48 hours.
Which antibiotic would you start empirically?
I would then await the sensitivities from microbiology and adjust my therapy accordingly.
What are the consequences of missing a flexor sheath infection?
The infection can spread into the palm and up the limb and the patient can become septic. The tendon or a pulley can rupture.
A slightly different scenario now. Let’s say there are no Kanavel signs. How would you manage this cat bite now?
I would admit the patient for elevation and plant o open and washout the wounds. If there were signs of flexor sheath contamination intra operatively I would wash this out too. If the patient can go to theatre within 6 hours and is not septic, I would hold off antibiotics un til samples can betaken.
Figure 13.5 Cat bite.
References#
2015. Retrieved from htip s://cks.nice.org.uk/bites-human-and-animal#!scenario:2.
Structured oral examination question 6#
Boxer’s fracture
This gentleman punched a wall during a night out. He presents to you the next day with a painful, swollen hand. What do these radiographs (Figures 13.6a–c) show?
These are AP, lateral and oblique radiographs of the left hand showing a fracture at the neck of the litile finger metacarpal.
What do you need to assess clinically?
If there is any full-thickness break in the skin, there is a high likelihood of the MCP joint being open. There is a risk of contamination from whatever the patient struck, which may have been another person rather than a wall.
What if you are not sure that there is a full-thickness wound to the skin?
If I was still unsure I would treat this as an open joint injury or open fracture.
How will you ensure intra operatively that the joint is not open?
Assuming the skin is broken, I would then open the skin sufficiently to inspect the extensor tendon and dorsal capsule. This would need to be approximately 2–3 cm. As the finger was flexed when the injury was sustained, it is important to assess the tendon intra operatively with the finger flexed.
Let’s say this is a closed injury and there is no rotational malalignment How will you manage it?
I would strongly recommend conservative management to the patient This would involve mobilization of the finger with the aid of a Bedford splint or neighbour strapping. I would explain that these injuries almost always will malunite, resulting in a pain- freehand with normal function.
What if the fracture were more proximal, let’s say in the shaft of the metacarpal?
This can be achieved by manipulation and plastering, but with a significant risk of displacement. Personally, I would stabilize the fracture with an intramedullary wiring technique according to Foucher.
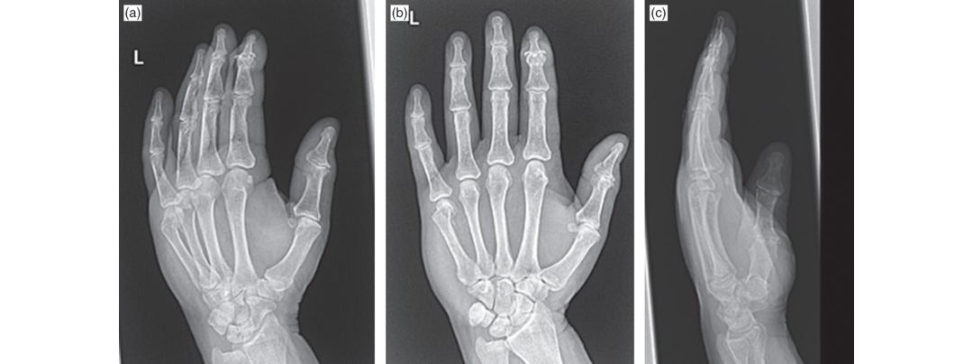
Figure 13.6a, 13.6b and 13.6c Anteroposterior (AP), oblique and lateral radiographs, left hand.
Reference#
Foucher G. ‘Bouquet’ osteosynthesis in metacarpal neck fractures: a series of 66 patients. J Hand Surg Am.
1995;20(3 Pt 2):S86–90.
Structured oral examination question 7#
Fight bite
Please describe this clinic photograph (Figures 13.7a and 13.7b).
It appears slightly erythematous, but there is no gross swelling or pus exuding.
What do you suppose is the mechanism of injury?
This type of injury is commonly sustained by punching someone or something.
Why is a fight bite injury a significant problem?
This could make the patient quite ill, but could also result insignificant damage to the joint, with long-term stiffness and dysfunction.
How does infection cause joint damage?
Metalloproteases are released by inflammatory cells which destroy the articular cartilage.
How will you determine whether the wound has breached the dermis?
I would have a very low threshold for treating this as a full-thickness wound as I find it quite difficult to be sure that the dermis has not been breached.
So how would you treat this patient?
This is a significant injury. My local hospital protocol for animal and human bites is to use co-amoxiclav 1.2 g IV tds. I would arrange plain X-rays to check for signs of fracture or foreign body. I would plan for surgery as soon as reasonably possible.
What operation would you do?
If there is any pus I will send a swab for microbiology. I will carefully assess the integrity of the extensor mechanism and joint. It is important to assess the joint capsule to determine whether this has been breached. Often it is and the joint will need washing out. I would assess the status of the articular cartilage and comment upon any defect. I would plan to return to theatre for a second look and formal closure in layers at 48 hours, assuming the wound was clean at that stage, otherwise a third operation may be needed.
And what would be your postoperative instructions?
Whether to mobilize at this point is controversial, but I would splint the hand in the Edinburgh position for comfort. I would see the patient again in clinic a few days later to check that the infection was subsiding and further surgery was not indicated.
What is the characteristic organism that causes infection with human bites?
Eikenella corrodens is the classic organism with human bites, but the most common infective agents are Streptococcus viridans and Staphylococcus aureus.
OK, let’s assume that you treat a particularly bad case which presented late, and although you were able to save the finger, the joint was destroyed and you see the patient 5 years later with a very stiff, painful, arthritic middle MCP joint. What can you offer him?
In manyways I would treat him much like any other osteoarthritis of the MCP J. This would be painkillers, splintage and lifestyle modifications. If I were to consider invasive treatment I would want to be sure the infection had fully resolved. If conservative measures failed and I was happy there was no residual infection, I would offer X-ray or ultrasound- guided steroid injection.
Why would you recommend fusion over replacement?
Fusion is a reliable way of relieving pain, but at the cost of stiffness. Anatomic MCPJ replacements are available and are a motion-pr eserving option, but come with risks of infection, wear and loosening. Professor Dias has presented his 5-year results in 13 joints. He had one revision for infection and three joints with evidence of loosening.
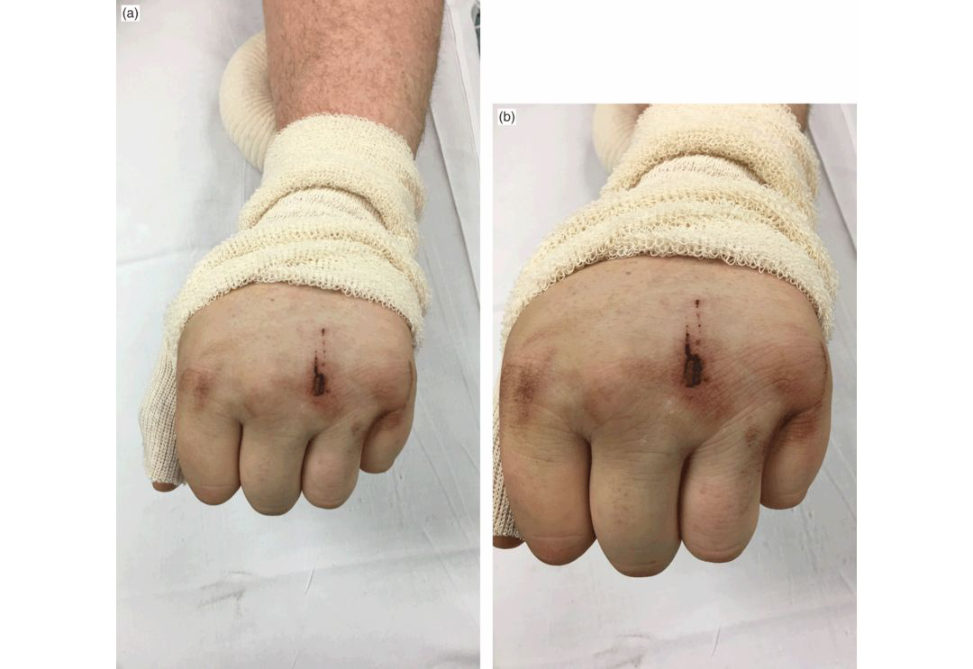
Figure 13.7a and 13.7b Clinical picture of a 21-year-old male presenting to accident and emergency department with a painful left hand following an injury.
Reference#
Singh H, Dias J. Surface replacement arthroplasty of the proximal interphalangeal and metacarpophalangeal joints: the current state. Indian J Plast Surg. 2011;44(2):317–326.