Chapter 15 Spinal trauma
Structured oral examination question 1#
Bifacet dislocation
A 53-year-old man was involved in a road traffic accident. He was driving the car and was wearing a seatbelt. This is the radiograph obtained in casualty (Figure 15.1a). What does it show?
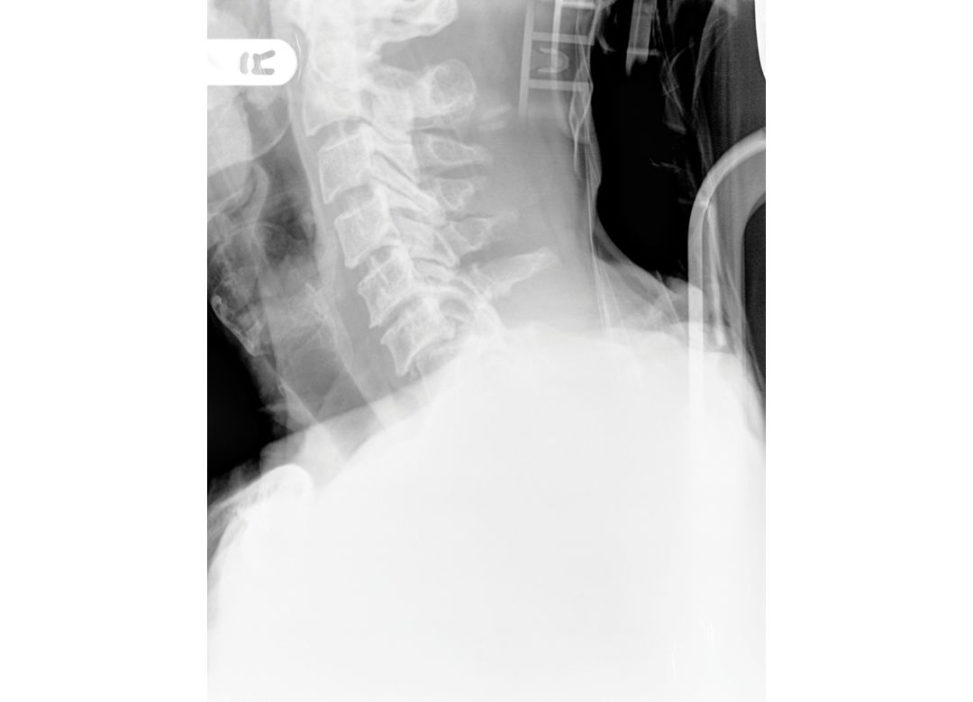
This is a plain lateral radiograph of the cervical spine that shows anterior translation of the C6 vertebra on C7. This translation is more than 25% so this is likely a bifacet dislocation. This is a bifacet dislocation. The C7/T1 border is not clearly seen and therefore this is an inadequate radiograph.
Assume there is no injury at C7/T1. How will you manage this patient?
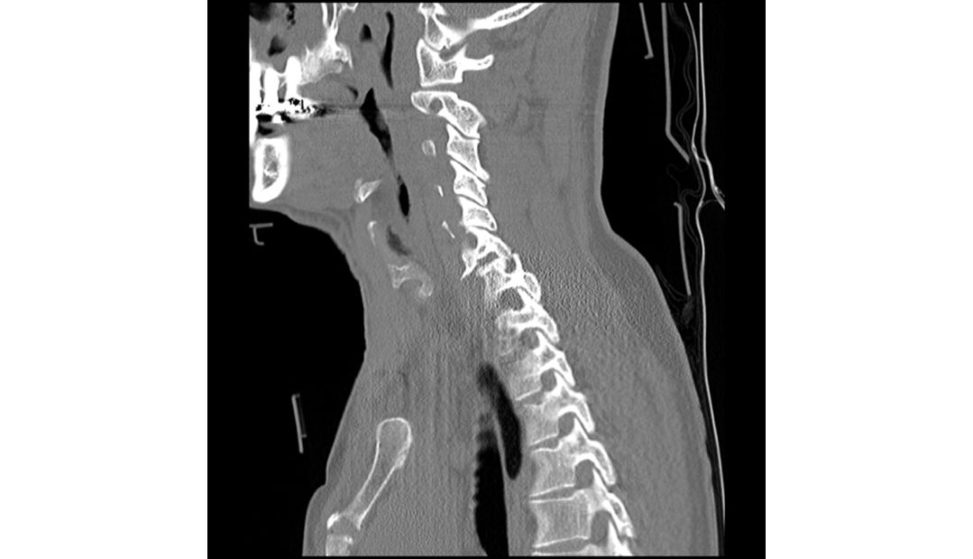
I will manage this patient according to ATLS guidelines. The aim is to protect the cord and maintain cord perfusion. I am mindful that 10% of patients have a fracture elsewhere so maintaining the patient supine on a spinal board with triple spine immobilization (rigid collar, sandbag, tape) and log-rolling is required. The incidence of neurological deficit with a bifacet dislocation is 50% so a full neurological assessment is required. Given the mechanism of injury and the injury identified I would obtain a trauma CT series (head, cervical spine, thoracic/lumbar spine, chest, abdomen and pelvis) to exclude any associated injuries (Figure 15.1b) [1]. This will allow them to then move on to discuss more definitive management of the injury (score 6). If a candidate is doing very well (score 7–8) they may discuss the more controversial areas of management (i.e. MRI versus no MRI prior to reduction (score 7) with evidence (score 8)). If a candidate is struggling with A&E management (score 4–5) they may not get past the initial management of the patient in the A&E department.1
Assume the patient is being managed in an appropriate spinal injuries unit.
I will then need to reduce and stabilize the spine.
How will you reduce the dislocation?
The dislocation can be reduced closed with traction or open with an anterior surgical approach.
Well of course all options apply , what would you do?
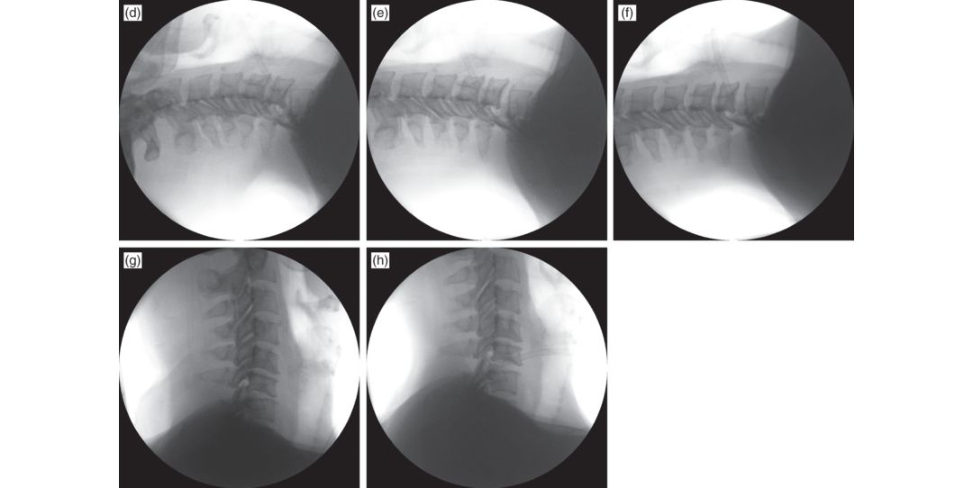
I would take the patient immediately to theatre and apply halo traction. Once the vertebral bodies and facet joints have been realigned traction can be reduced and a collar applied (Figure 15.1d –h) [2].
Would you not organize an MRI scan first?
This is controversial [3]. In an awake cooperative patient this is not required. An existing deficit will not have the potential to improve until the spine is realigned and an MRI delays this.
Are you telling me you would never get an MRI first?
If the patient were obtunded or uncooperative and notable to cooperate with serial examinations during reduction manoeuvres I would organize an MRI scan first [4].
How would you stabilize this injury?
An anterior cervical discectomy and fusion (ACDF). This can be done with a cage and plate or tri cortical iliac crest graf thar vested with a small sagift al saw) and a plate. A CDF with plating gives the injury a degree of stability before apa tien t is turned prone and the cord should not be in danger.
What would you do if closed reduction failed?
If a closed reduction f ails, an anterior or posterior approach should be performed to reduce the locked facet dislocation.
Key Points
When reduction occurs the disc herniation can be displaced posteriorly into the spinal canal, causing catastrophic deficit.
1. Before reduction.
a. Advantage – allows identification of disc herniation, which then provides an argument for proceeding with open discectomy rather than closed reduction.
b. Disadvantage – delays treatment which in the presence of neurological deficit might adversely affect outcome as cordis compressed for longer.
2. After reduction.
a. Advantage – allows identification of disc herniation that might dictate surgical approach, e.g. herniation behind vertebral body may require corpectomy.
b. Disadvantage – time-c onsuming and often these herniations are not clinically significant so should not affect treatment which is ACDF.
3. Not performed.
a. Advantage – facilitates more rapid reduction by avoiding delay. Studies suggest that closed reduction can be safely performed, provided that serial neurological examination is possible during this procedure.
b. Disadvantage – very small risk of worsening deficit by displacing disc herniation.
In an awake cooperative patient with deficit this has lift le chance of improving until cord compression is alleviated by reduction and the incidence of disc herniation is higher after closed reduction, but the incidence of neurological deficit is not, i.e. these herniations don’t appear to be clinically significant.
Figure 15.1a Lateral radiograph demonstrating C6 on C7 facet dislocation.
Figure 15.1b C6 7 facet dislocation par asagift al CT.
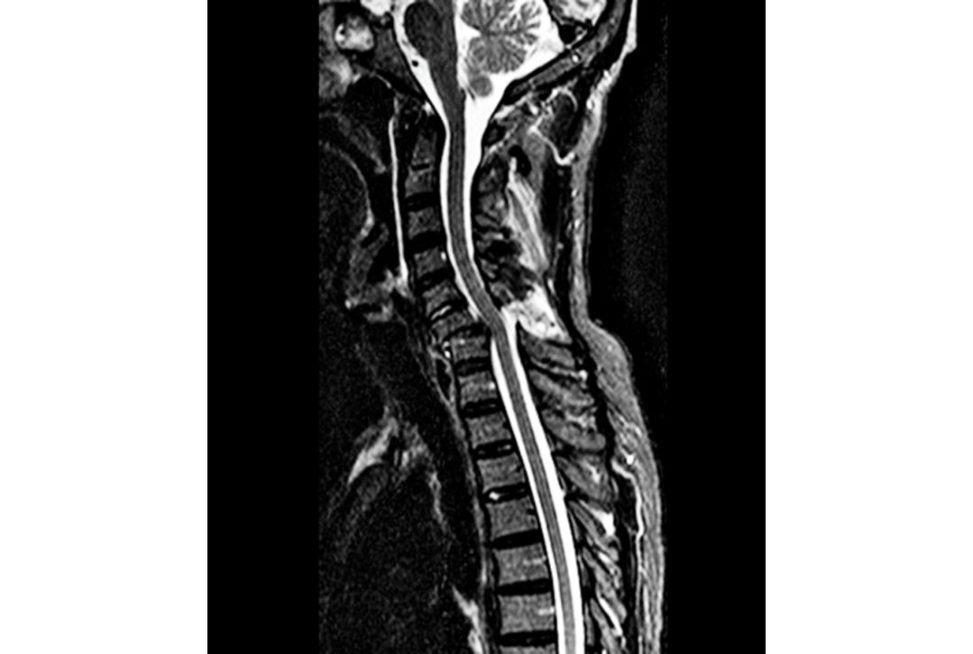
Figure 15.1c Parasagift al MRI stir of C6 on C7 facet dislocation.
Figure 15.1d–h Image intensification views of closed reduction of C6 on C7 facet dislocation.
References#
1. Arnold PM, Brod keDS, Rempersaud YR, et al. Differences between neurosurgeons and orthopaedic surgeons in classifying cervical dislocation injures and making assessment and treatment decisions: a multic enter reliability study. Am J Orthop. 2009;38:E156–E161.
2. Vaccaro AR, Falatyn SP, Flanders AE, et al. Magnetic resonance evaluation of the intervertebral disc, spinal ligaments and spinal cord before and after closed traction reduction of cervical spine dislocations .
Spine. 1999;24:1210–1218.
3. Grant GA, Mirza SK, Chapman JR, et al. Risk of early closed reduction in cervical spine subluxation injuries. J Neurosurg (Spine). 1999;90:13–18.
4. Hart RA, Vaccaro AR, Nachwalter RS. Cervical facet dislocation: when is magne tic resonance imaging indicated? Spine. 2002;27:116–118.
Structured oral examination question 2#
Incomplete cord injury
A 75-year-old female presents with abnormal neurological findings having fallen onto her face. What does the MRI scan show (Figure 15.2a)?
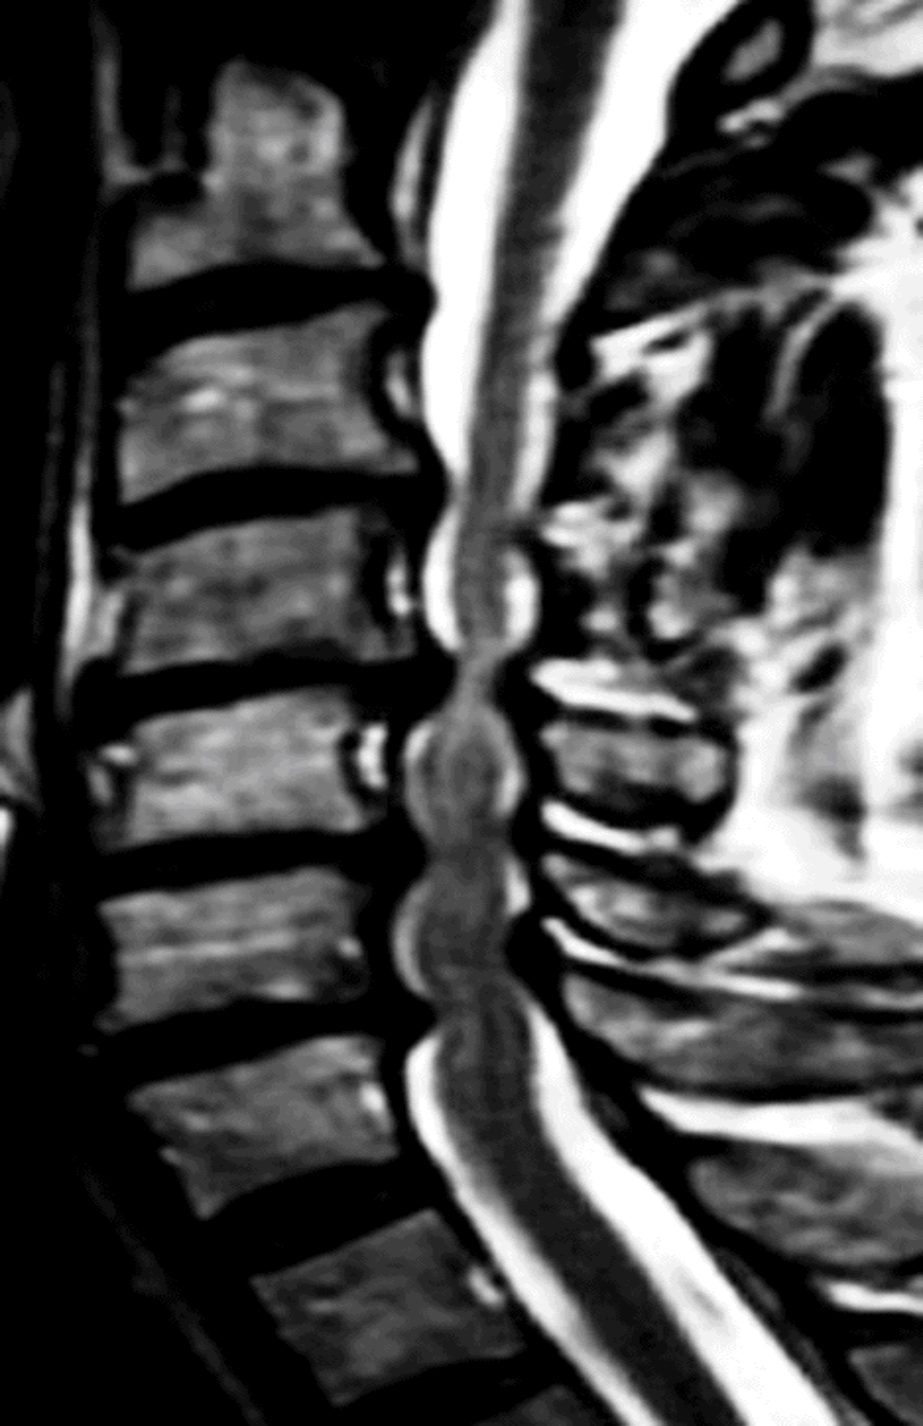
At C4/5 where the narrowing appears severe (but requires axial cuts for proper assessment) there is focal high signal change in the cord, which is either myelomalacia (spinal cord damage due to compression) or oedema (due to the acute injury).
What pattern of injury do you expect?
It is likely that the pattern of injury is one of central cord syndrome. It is the most common incomplete spinal cord injury. The pathophysiology is one of anterior osteophytes and posterior infolded ligamentum flavum compressing the cord.
What do you think the clinical features will be?
The upper limbs are affected to a greater extent, with the motor deficit especially apparent in the hand.
What is the pathophysiology of the condition?
The original description of the condition was based on post-mortem studies that demonstrated a destructive haematomyelia, but more frequently this is absent, and the injury caused by oedema alone.2 If haemorrhage is present this has been correlated with a worse injury and limited neurologic recovery.
How will you manage this person?
Initial management of such an injury in the emergency department would include a full ATLS work-up. It is also important to perform serial neurological examinations especially to check for any deterioration in function, as this is ast rong indication to consider surgical decompression.
Would you give steroids?
I am not sure of the specifics of the literature, but there is very litile hard evidence to support the clinical benefit of steroids in the management of acute SCI, but plenty of evidence documenting their harmful side effects.
What about prognosis?
Central cord syndrome has a good prognosis although full functional recovery is not likely. It is usual to see significant early neurological recovery. If there is a plateau in recovery with MRI-proven cord compression, or if there are signs of instability, surgical decompression and stabilization should be considered [1].
What surgical approach would you use?
The optimal surgical approach is a matter of debate. As a general rule, the ideal surgical approach should target the site of predominant compression of the spinal cord: anterior, posterior, or combined.
Are you aware of any other incomplete cord syndromes?
Anterior cord syndrome affects the anterior two-thirds of the spinal cord via anterior spinal artery lesions. Brown–Sequard syndrome is a hemi-section of the spinal c ord, seen with a penetrating trauma. If a candidate is progressing well with the viva, they may be asked to drawout the spinal cord tracts and spend more time discussing anterior cord and Brown–Sequard syndromes.
Key Points
Central cord syndrome has a reasonable prognosis. Historically, non-surgical treatment was advocated for CCS.
Early surgery is indicated if there is instability from a co-existing fracture that requires stabilization [ 2].
If the cause of the CC Sis a large central disc protrusion, early surgery is supported.
The Surgical Timing in Acute Spinal Cord Injury Study (STACIS) suggests decompressive surgery should be.
Figure 15.2a T2 sagift al MRI scan, cervical spine. C5–7 hyperintense signal.
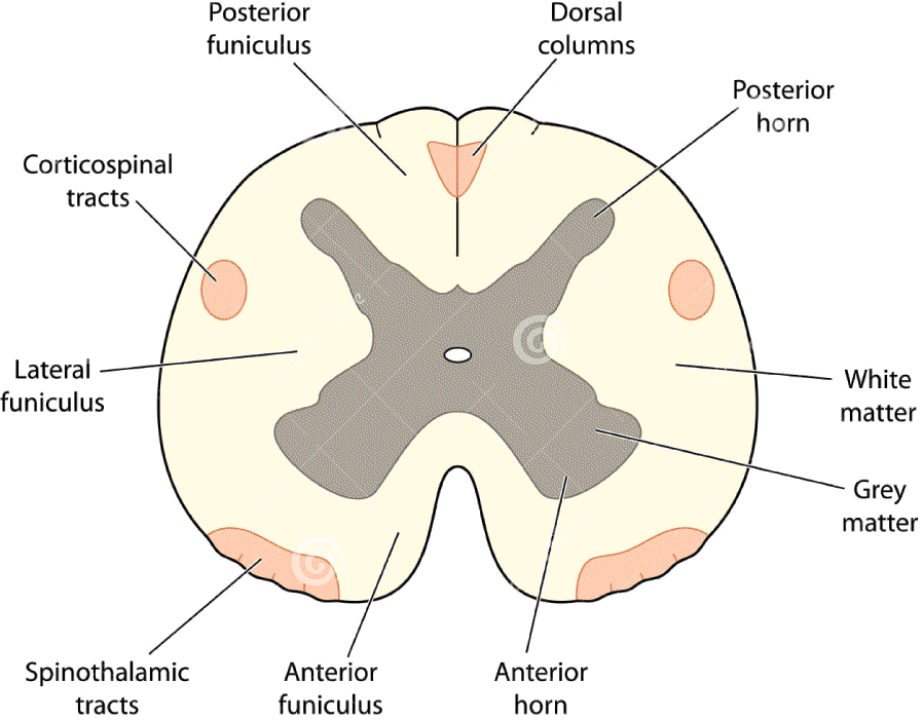
Figure 15.2b Cross-section of spinal c ord.
References#
1 Samuel AM, Grant RA, Bohl DD, et al. Delayed surgery after acute traumatic central cord syndrome is associated with reduced mortality. Spine. 2015;40:349–356.
2. Fehlings MG, Vac caroA, Wilson JR, et al. Early versus delayed decompression for traumatic cervical spinal cord injury: results of the Surgical Timing in Acute Spinal Cord Injury Study (STASCIS). PL oSONE.
2012;7:e32037.
3. Anderson KK, Tetreault L, Shamji MF, et al. Optimal timing of surgical decompression for acute traumatic central cord syndrome: a systematic review of the literature. Neurosurgery. 2015 77:s15–s32.
Structured oral examination question 3#
Thoracolumbar burst fractures
What does this X-ray (Figures 15.3a and 15.3b) show?
There is a fracture of the T12 vertebral body (it is reasonable to say a vertebral body at the thoracolumbar junction but L5/S1 not visible so exact level difficult to be sure) with greater than 50% loss of the vertebral body height.
What is a stable spine?
Under physiological load the spine is sufficiently stable to prevent significant pain, neurological deficit and progressive deformity.
So, is this fracture stable?
At the thoracolumbar junction a fracture with this much loss of height.
What is your management?
I would manage the patient according to ATLS principles. This will ensure optimal c ord perfusion. There may be other treatment priorities identified, eg. concurrent abdominal trauma. The initial aim ist o prevent secondary injury by protecting (neutral spinal alignment) and perfusing (appropriate resuscitation) the c ord. I would assess the patient for signs of neurogenic shock.
Do you mean neurogenic shock?
It is important to exclude other causes of hypotension, however (10–15% of patients with spinal injuries have visceral injuries), before atiributing hypotension to neurogenic shock.
So, is this likely here?
The majority of sympathetic innervation has come off the cord before T12, so no. Spinal shock is possible. It is a temporary loss of spinal cord function and reflex activity below the level of the injury.
What is the importance of spinal shock and how do you know when it’s over?
The importance of spinal shock is that one cannot evaluate the neurologic deficit until the spinal shock phase has resolved.
Is there any further imaging you would obtain?
A CT scan would be helpful to more fully assess fracture morphology.
You have just told me the fracture is unstable, we are going to treat it as an unstable injury, so is a CT really needed, are you not just using up limited NHS resources?
This is testing higher -order judgement and the appropriate reasoning for use of musculoskeletal imaging.3 The ICB place a lot of importance on these types of questions as the y deal with the real-life world of NHS clinical practice rather than just reading facts from a book for an exam. The majority of orthopaedic units would request a CT scan.
Would an MRI not be better?
An MRI scan is better at picking up disc herniations, epidural or subdural haematomas, ligamentous injuries and spinal cord parenchymal injury. In the absence of neurological deficit, it is usual to request a CT.
So how would you manage this fracture?
The fracture is unstable.
Key Points
Protecting the cord and perfusing the cord to prevent secondary injury are paramount. Lumbar burst fractures (L3–L5) without neurological deficit are usually treated conservatively.
There is no general consensus on how to treat neurologically intact thoracolumbar burst fractures (T10–L2), which can be treated with extension orthoses or with surgery [2].
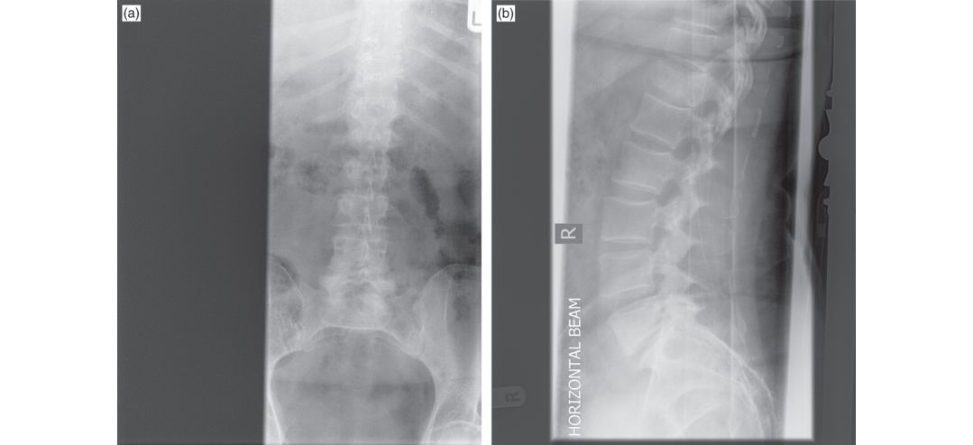
Figure 15.3a and 15.3b AP and lateral radiograph burst thoracolumbar fracture.
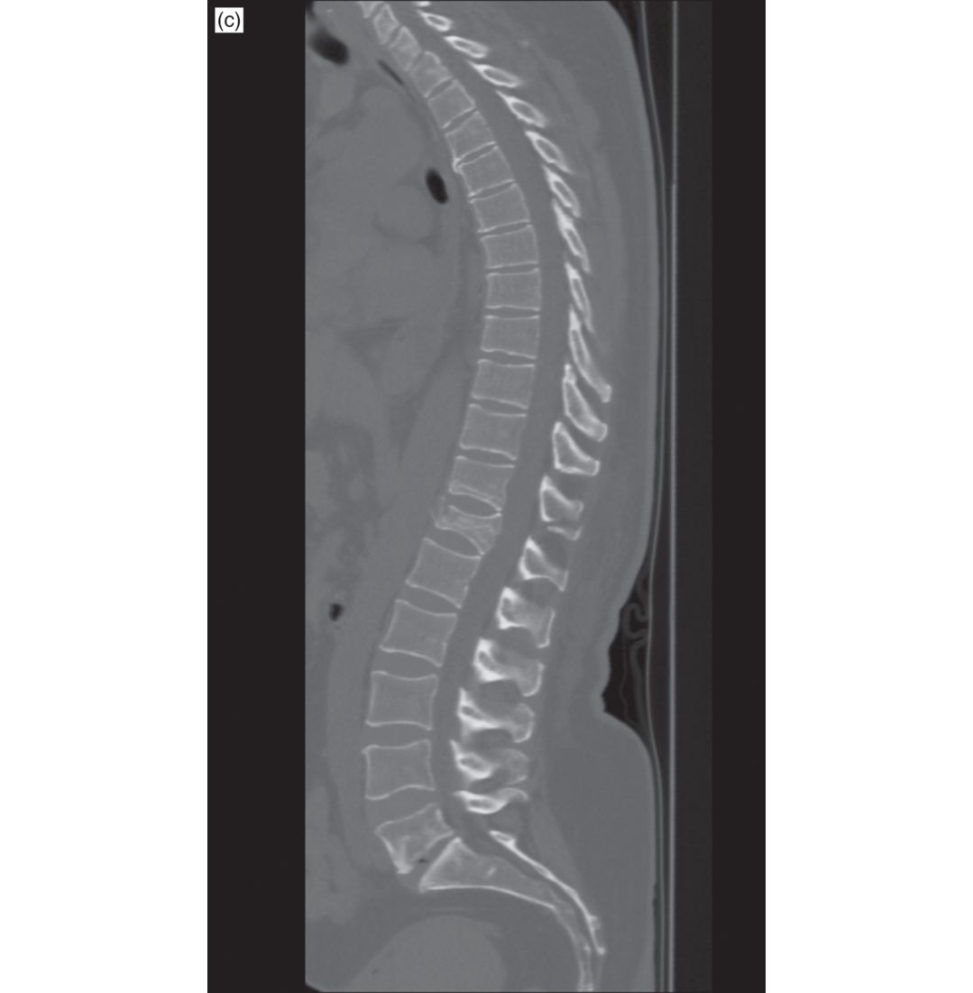
Figure 15.3c Sagift al CT T12 burst fracture.
References#
1. Wood K, Buft er manG, Garvey T, et al. Operative compared with non-operativ e treatment of a thoracolumbar burst fracture without neurological deficit. A prospective randomized study. J Bone Joint
Surg Am. 2003;5:773–781.
2. Siebenga J, Leferink VJM, Segers MJM, et al. Treatment of traumatic thoracolumbar spine fractures: a multic enter prospective randomized study of operative versus nonsurgical treatment. Spine.
2006;25:2881–2890.
Structured oral examination question 4#
Odontoid peg fractures
Introduction
The management of type II odontoid fractures in the elderly is controversial for several reasons.
There is supportive evidence of successful outcomes for both non-surgical and surgical management.
There is uncertainty regarding the consequences of non-union, with some authors arguing that a stable fibrous union in an asymptomatic patient > 65 years is acceptable.
It would be expected that candidates should be able to describe radiographic features and discuss the Anderson and D’Alonzo classification system [3].
What does this X-ray (Figure 15.4a) show?
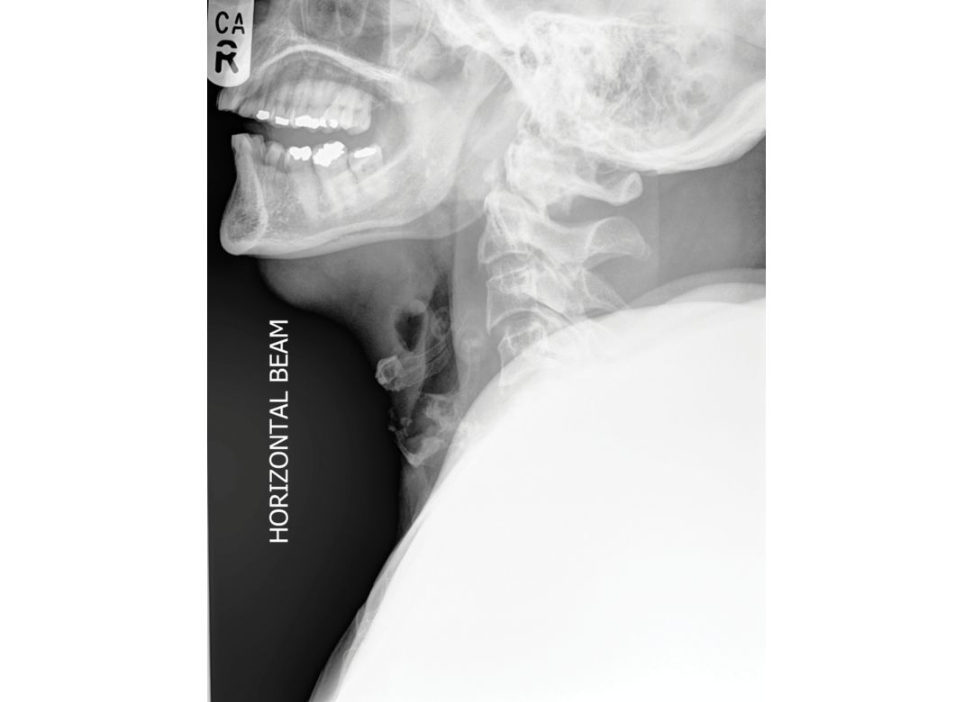
The most obvious abnormality is a fracture through the base of the odontoid peg (process) of C2 with posterior angulation.
Yes, are you aware of any classification systems for this type of injury?
This classifies fractures according to their location within the peg Type I fractures (< 5% cases) affect the tip of the odontoid and are caused by avulsion of the alar ligaments. Type II injuries (> 60%) run through the base of the odontoid peg. Type III injuries (30%) involve the vertebral body; they run through the metaphyseal bone of the vertebral body.
So how does this classification guide your management?
Type I injuries, which are rare, are usually managed in an Aspen collar.
Is this always the case?
Type I avulsion fractures can indicate occipito-cervical instability.
And the other types?
Type III injuries are likely to heal and so I would treat them conservatively. Type II injuries are more likely to go on to non-union and so they are the injuries for which I would consider fixation as an option as opposed to conservative treatment.
So, do you normally operate on Type II peg fractures?
They usually occur on older patients (> 65) and so I would prefer to manage them non- operatively in an Aspen collar.
Are there any factors with Type II injuries that would make it more likely that they would go on to non-union to guide your decision?
Yes. If there is more than 5–6 mm fracture displacement, if there is angulation > 10°, posterior displaced fractures (non-union rate > 70%), smokers, delay in diagnosis and patients over the age of 65.
What will you do if the patient finds the Aspen collar difficult to wear and he wants to take it off as it is too uncomfortable?
If I was worried he was going to take the collar off I would counsel him that it would be very dangerous to do so and could result in paralysis or death [2].
What are the surgical options for treatment of a Type II fracture?
The two options are posterior C1/C2 fusion (either Magerl transarticular screws or Harms C1 lateral mass/C2 pedicle screws) or direct anterior single- or double-screw osteosynthesis of the dens of C2 [4]. The benefit of C1/2 fusion is that it is a reliable operation that is not dependent on the fracture configuration, is biomechanic ally more secure but results in loss of rotation. The patient would need to be prone and dissection involves the risk of brisk bleeding from the C1/2 venous plexus or injury to the C2 nerve.
What factors would guide your choice of surgery?
In this situation I would choose to perform a C1/2 fusion instead. Relative contraindications to screw fixation include large BMI, fracture older than 3 weeks or poor bone quality.
Yes, let’s move on. Key Points Type I odontoid peg fractures are rare. They are usually treated conservatively. Type III fractures generally heal and are also treated conservatively. Type II fractures in the young are treated with a halo jacket unless there are risk factors for non-union, when surgery is advocated. Type II fractures in the elderly are usually treated with an aspen collar. The risks of surgery are significant and halo jacket treatment has a high complication rate including pin-site infections and loosening, skin breakdown, pneumonia or respiratory insufficiency, facet joint stiffness, and loss of spinal reduction. A number of elderly patients find Aspen collars uncomfortable to wear, made worse by the fact they need to beworn for several weeks. Complications from surgery include postoperative haematoma, dysphagia, hoarseness, damage to the vertebral artery, and neural injuries. Complications of non-operativ e treatment include the risk of non-union, catastrophic neurological injury with subsequent falls or late-onset progressive myelopathy. Progressive myelopathic changes may occur inpatients who develop a non-union. However, a stable pseudarthrosis is often adequate in the elderly low-demand patient and late translation is unusual. Many elderly patients have significant comorbidities so the risk of catastrophic neurological injury with non-operativ e treatment isless than the morbidity and mortality associated with surgery.
Figure 15.4a Lateral cervical spine radiograph demonstrating odontoid peg fracture.
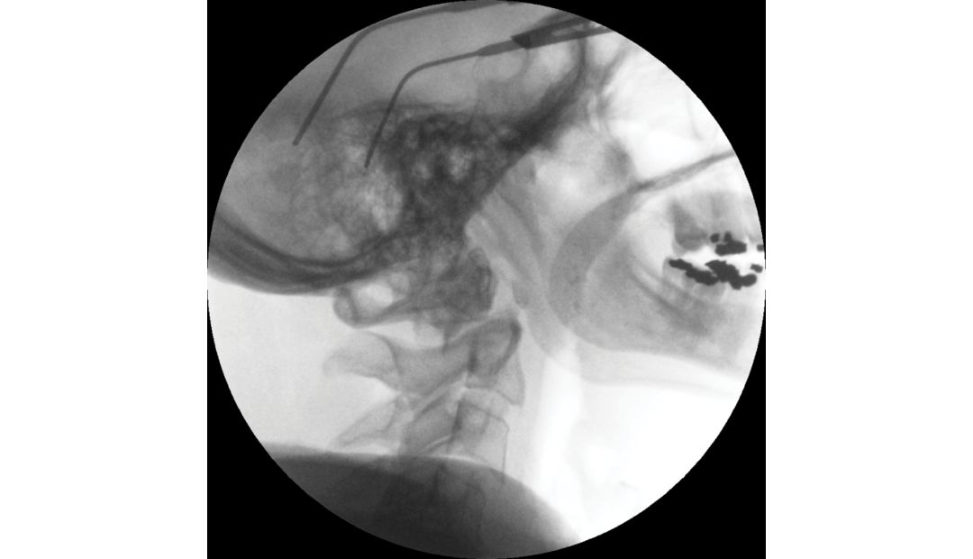
Figure 15.4b Image intensifier view, lateral cervical spine radiograph demonstrating odontoid peg fracture.
Table 15.1 Anderson and D’Alonzo classification of peg fractures according to fracture location.
- Type I – Avulsion fracture of the tip of the dens
- Type II – Fracture between the base of the transverse ligament and the body of the vertebrae
- Type III – Fracture running through the body of the vertebrae
References#
1. Koivikko MP, Kiuru MJ, Koskinen SK, Myllynen P, Santavirta S, Kivisaari L. Factors associated with non-union in conservatively treated type II fractures of the odontoid process. J Bone Joint Surg Br.
2004;86(8):1146–1151.
2. Kuntz CIV, Mirza SK, Jarell AD, Chapmen JR, Shaffrey CINe well DW. Type II odontoid fractures in the elderly: early failure of non-surgical management.Neurosurg Focus. 2000;8(6):e7.
3. Anderson LD, D’Alonzo RT. Fractures of the odontoid process of the axis. J Bone Joint Surg Am.
1974;56:1663–1674.
4. Grauer JN, Sha fiB, Hilibrand AS, et al. Proposal of a modified, treatment-oriented classification of odontoid fractures. Spine J. 2005;5:123–129.
Structured oral examination question 5#
Hangman’s fracture
What does this X-ray (Figure 15.5) show?
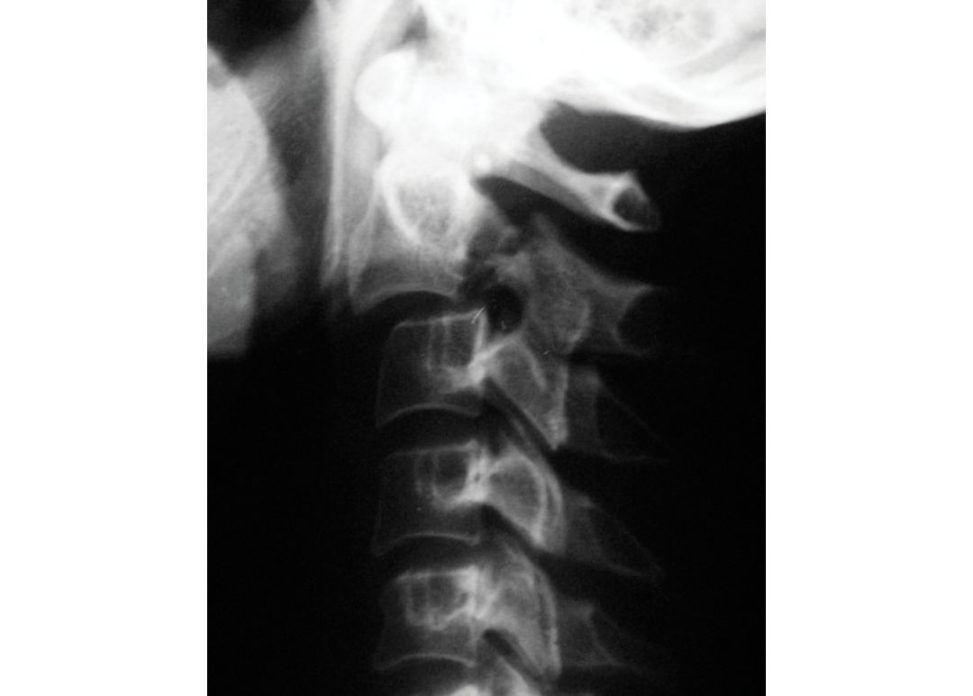
It is a lateral radiograph of the cervical spine. The most obvious abnormality is an anterior subluxation of C2 on C3.
Do you know what we call this fracture?
It is a traumatic spondylolisthesis of C2, also known as a hangman’s fracture.
What is the mechanism of injury?
The accident is usually a head-on collision with another vehicle or with a fixed object such as a lamppost. It is a hyperextension injury.
How do these fractures present?
It is relatively unusual for these fractures to present with a neurological deficit unless.
Do you know any classification systems for this injury?
Yes, I am aware of the Levine classification. It grades the injury as Type I with bilateral pars interarticularis fractures and no displacement. Type III injuries also involve C2/3 facet joint dislocation.
Did you say Levine?
Yes.
It was originally described by Effendi, whose classification system was revised as you describe by Levine and Edwards. How would you manage apa tien t with a hangman’s fracture?
Levine and Edwards suggest in their paper that Type I injuries are essentiallys table due to the intact ligamentous restraints (principally C2/3 disc) and are likely to heal with external immobilization in a hard collar. Type II fractures have an intact anterior longitudinal ligament. Type III fractures are inherently unstable and require urgent reduction of the facet dislocation.
Key Points
There has been much debate over management of these fractures over the years with no clear management that is shown to be appropriate for all cases.
Two reviews that have been published regarding the management of these fractures have similar ideas [1,2].
Otherwise these injuries require stabilization (C2 direct osteosynthesis – transpedicular screw fixation). If the C2/3 disc integrity is compromised, C2/3 fusion is required, which can be done anteriorly with a discectomy and bone graft (or posteriorly).
Figure 15.5 Lateral cervical spine radiograph demonstrating hangmans fracture.
References#
1. Li XF, DaiLY, Lu H, Chen XD. A systematic review of the management of hangman’s fractures. Eur Spine
J. 2006;15(3):257–269.
2. Greene KA, Dickman CA, Marciano FF, Drabier JB, Hadley MN, Sonntag VK. Acute axis fractures: analysis of management and outcome in 340 consecutive cases. Spine. 1997;22(16):1843–1852.
Structured oral examination question 6#
Chance fractures
They account for approximately 15% of all thoracolumbar injuries and are most commonly seen at the thoracolumbar junction.
What does this picture show (Figure 15.6a)?
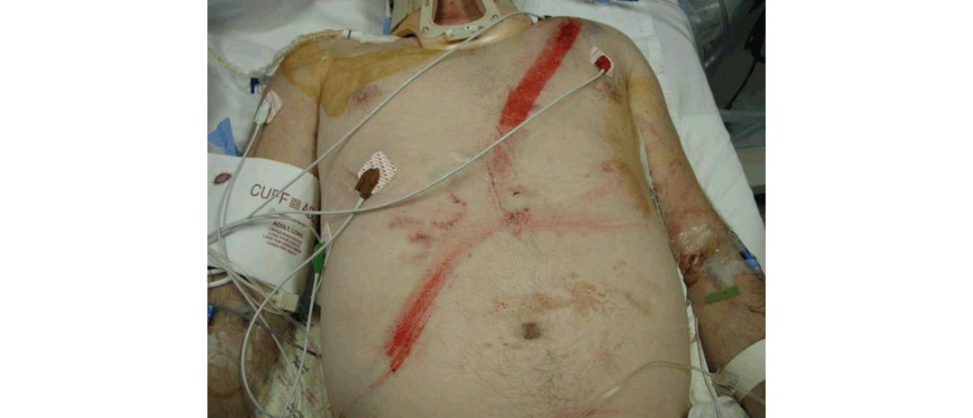
There is gross bruising in a horizontal configuration across the lower anterior abdominal wall.
What do you think has happened to her?
I would imagine that she has been involved in an RTC restrained by a seatbelt.
Yes, that’s right. So how would you assess this lady in the emergency department?
EXAMINER [interrupting]: Y es, all right, but what injuries would you expect to find? I would expect this lady to have intra-abdominal injuries due to the blunt trauma. With this mechanism, which is flexion distraction, I would suspect a transverse bicolumn injury that is either bony (Chance fracture) or soft -tissue type injury.
Tell me about Chance fractures (Figure 15.6b).
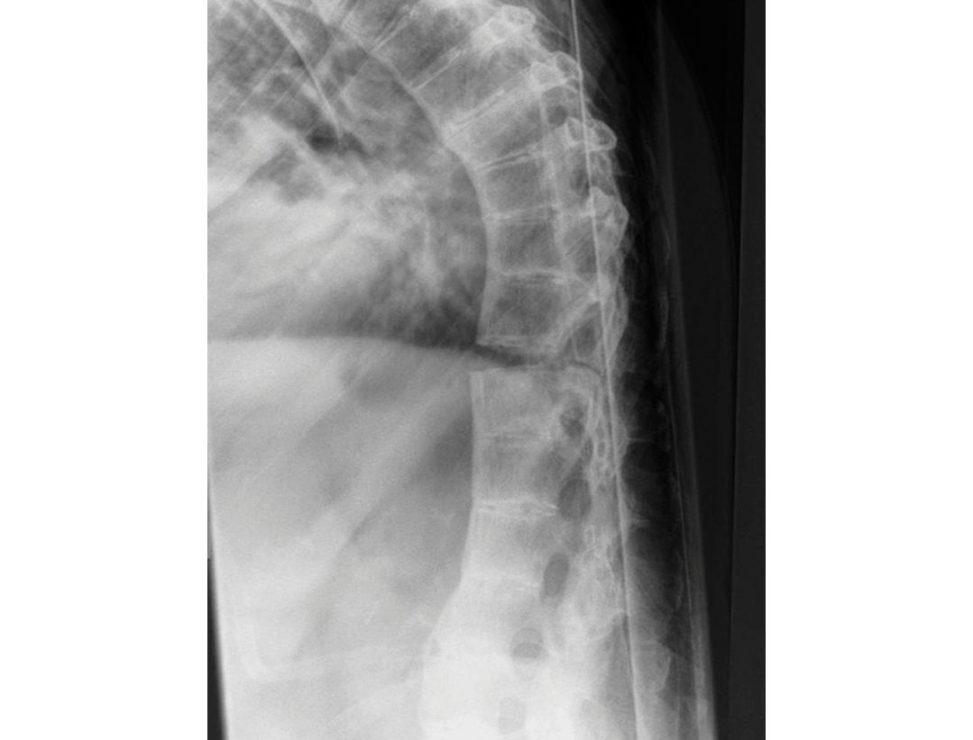
It involves an injury to both the anterior and posterior columns (B-type injury according to the AO classification system) [1]. It can be purely bony, which is a Chance fracture, purely ligamentous or mixed.
So how would you investigate this person in the Emergency department?
The patient would often have a trauma CT scan that will include the injured spine.
What would you expect to see?
If there was a bony injury then you could see the pattern of the fracture running through the vertebral body and the posterior elements.
Would you do any further investigations?
If there was no bony injury and I suspected a flexion–distraction type injury (or AO B-type injury) then.
How would you manage these injuries?
These fractures are often managed operatively to prevent progressive displacement and deformity and to allow the patient to return to normal function faster.
What if this was a soft -tissue Chance, i.e. a ligamentous flexion–distraction injury?
These healless reliably so would require surgical management with a posterior construct to recreate the tension band [4].
What if they were to have a complete injury? Is there a role for surgery then?
The role of surgery in a complete spinal cord injury is to facilitate rehabilitation by providing a stable and pain-free spine.
Would you use steroids?
There is no convincing evidence that steroids make any difference to the outcome of spinal cord injury.
OK, let’s move on. Spinal injuries can be classified by a number of different systems. The AO system identifies two columns. The anterior column includes the vertebral bodies, intervertebral discs and the anterior and posterior longitudinal ligaments, while the posterior column includes the neural arch and the posterior elements. There are three different mechanisms of injury. A-type injuries (compression) may be unstable, B-type injuries (flexion–distraction or hyperextension) are often unstable and C-type injuries (translation or rotation) are always unstable.
Figure 15.6a Clinical photograph demonstrating gross abdominal bruising.
Figure 15.6b Lateral radiograph of thoracic spine demonstrating Chance fracture.
Associated injuries
They have been seen on 40% of scans in a recent study and must be actively sought out at the time of presentation. It could also be shown as a treated Chance fracture with a delayed deterioration from a perforated viscus Alternatively, the surgeons may have identified the intra-abdominal injury but failed to recognize the association with spinal injuries.
Any neurological deficit or worsening neurological function is an indication for surgery.
Management
If we treat the spinal injury in isolation, worsening neurological function requires stabilization and decompression. Those which have soft -tissue injuries alone are unlikely to heal without stabilization procedures due to the poor healing potential of ligamentous structures.
There are, however, advocates of operating on all Chance fractures due to the unstable nature of the fracture and the vast improvements in surgical instrumentation.
References#
1. Chapman JR, Agel J, Jurkovich GJ, Bellabarba C. Thoracolumbar flexion–distraction injuries: associated morbidity and neurological outcomes. Spine. 2008;33(6):648–657.
2. Groves CJ, Cassar-Pullicino VN, Tins BJ, Tyrrell PN, McCall IW. Chance-type flexion–distraction injuries in the thoracolumbar spine: MR imaging characteristics . Radiology. 2005;236(2):601–608.
3. Bernstein MP, Mirvis SE, Shanmuganathan K. Chance-type fractures of the thoracolumbar spine:
imaging analysis in 53 patients. AJR Am J Roentgenol. 2006;187(4):859–868.
4. Ramie riA, Domenicucci M, Cellocco P, Raco A, Costanzo G. Effectiveness of posterior tension band fixation in the thoracolumbar seat-belt type injuries of the young population . Eur Spine J. 2009;18(Suppl 1):89–94.
Structured oral examination question 7#
Incomplete spinal injury
We have a young girl who was paragliding and fell down around 20 meters sustaining a high- energy injury. This is her vertebral fracture at the thoracolumbar junction. No other injuries, isolated unstable injury. Physical examination is ASIA C.
A person is ASIA C if they have any preserved motor function below the neurological level, but more than half of the key muscles have a muscle grade of 3 orless.
How will you manage this injury?
Perfuse the spine; prevent secondary cord injury, urinary catheterization, IV fluids, etc. Thorough inspection of the spine should be performed after a careful log-roll manoeuvre to look for abrasions, tenderness, local kyphosis and a palpable gap in between spinous processes. An MRI will be needed, but the patient needs to be first evaluated following the basic principles of trauma assessment. Candidates will score 4 (poor fail), as they need to resuscitate and stabilize the patient first and before thinking about obtaining scans.
How do you classify these thoracolumbar fractures?
There are some stable fractures and some that are unstable. It is a composite scoring system based on three injury components: (1) integrity of the posterior ligamentous complex, (2) radiographic injury morphology, and (3) neurological status of the patient. Type C: Displacement or dislocation.
What are the goals of surgery. What are you trying to achieve?
You would want to stabilize the fracture and decompress the neural elements either directly or indirectly, usually indirectly.
Regarding medical treatment, do you think these patients would benefit from using steroids?
Yes, I would give steroids.
Do you think there is clear evidence, literature evidence? Where is the controversy?
[... Silence]
You don’t know. Where is the controversy? Do you think there is a controversy (leading question)? Are you using steroids in your place (institution)?
Yes [... long silence]
OK. This is a 37-year-old woman who ... [Candidate debrief]
Where can we begin? The candidate was having a bad viva for whatever reason and would have scored a 4. If you cannot answer this, you are down to a 6.
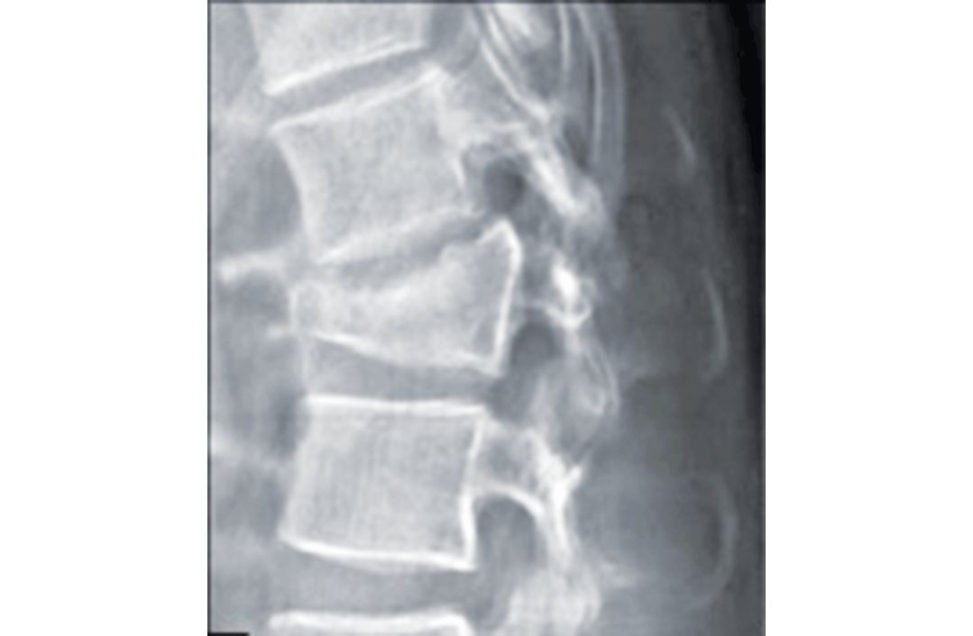
Figure 15.7 Thoracolumbar injury.
Key Points
A lumbar burst fracture is a single-column injury (lamina split if present not considered significant) and may be unstable, requiring fixation. An undisplaced Chance fracture
(two-column injury) may be treated conservatively if felt to be suitably stable.
Is my posterior tension band intact? If not, I need to address this.
Reference#
Sethi MK, Schoenfeld AJ, Bono CM, Harris MB. The evolution of thoracolumbar injury classification systems. Spine J. 2009;9(9):780–788.
Structured oral examination question 8#
Application of a halo
How do you apply a halo?
My indications for applying a halo would be: Temporary; Paediatric trauma patient [1].
I asked how you apply a halo, not indications. 4
The halo ring must provide 1–2 cm clearance circumference around the head. After antiseptic preparation and using local anaesthetic infiltration to the scalp, four pins are applied to the adult skull (eight in the paediatric population) and tightened with a torque-limiter (8 inch-pounds; 2–4 inch-pounds in the paediatric skull). The pins are placed equidistant and symmetrically in order to allow for stability of the construct. The anterior pins are placed 1 cm above the lateral one-third of the eyebrow (supraorbital ridge) with the eyes tightly closed. This is lateral to the supraorbital nerve [2].
Why should the patient close their eyes?
The posterior pins are placed 1 cm above the ear. A radiograph is obtained to ensure correct reduction Radiographs are required at regular intervals to ensure reduction is maintained. The patient should be instructed to return at 24–48 hours to have the pins re tightened and should be educated on pin hygiene.
How do you ensure correct pin placement and why is it important?
Correct pin placement is important to minimize the risks of direct neural or vascular injury, inner calvarial penetration and pin migration while providing adequate strength of fixation [ 3].
What are the potential complications?
Loss of position or reduction, pin-sit e infection and loosening , pain, nerve (sixth cranial nerve5) or vessel injury. One-fitih of patients also complain of pain, which can be managed by loosening. Restricted ventilation and pneumonia (elderly). Rarely there is a complication of dural puncture (1%). Protocols have been developed for managing pin-site infections.
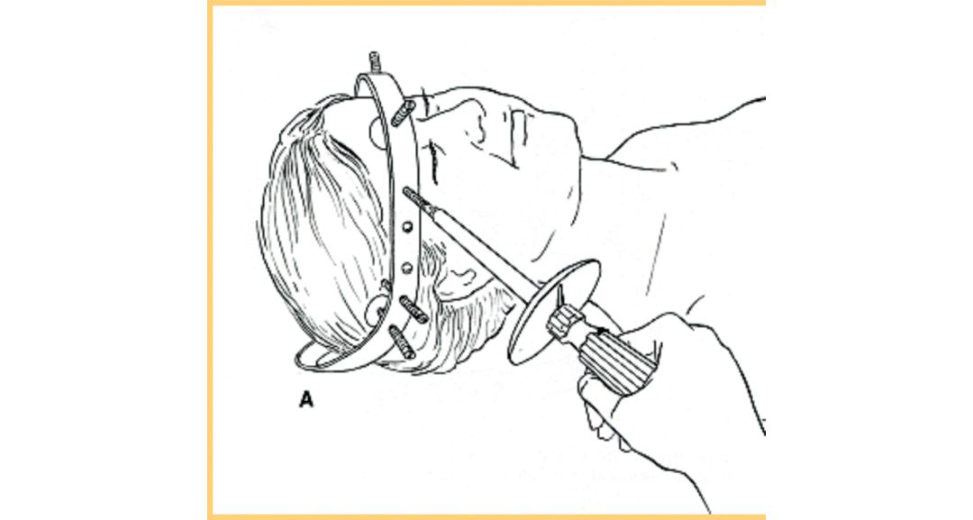
Figure 15.8 Halo traction.
References#
1. Bono CM. The halo fixator. J Am Acad Orthop Surg. 2007;15(12):728–737.
2. Boft e MJ, Byrne TP Abrams RA, et al. Halo skeletal fixation techniques of application and prevention of complications . J Am Acad Orthop Surg. 1996;4:44–53.
3. Garfin SR, Boft e MJ, Waters RLe tal. Complications in the use of the halo fixation device. J Bone Joint
Surg Am. 1986;68:320–325.
Structured oral examination question 9#
Caudae quina syndrome
You review a 42-year-old lady in your elective spinal clinic. She attends with her three children. She was referred by her own GP with troublesome unilateral L5 radicular symptoms. She briefly mentioned that she had a single episode of urinary incontinence. Does this worry you?
I would beworried with her presentation of a single episode of urinary incontinence with unilateral L5 radicular symptoms. I would like to know the chronicity of the unilateral leg pain, its distribution treatment and medications to date, any previous imaging, aggravating and relieving factors. Clinical examination would involve palpating the abdomen for a distended bladder and would include a per rectum examination testing for perianal sensation and the presence of voluntary sphincter contraction.
This does not sound like a dramatic presentation, but what is your concern?
I am concerned about caudae quina syndrome based on her clinical presentation. I would have a low threshold to arrange for an urgent MRI for this patient if the history is potentially consistent with caudae quina syndrome provided she has no contraindications for MRI scan.
I had an MRI scan report on my desk yesterday reporting caudae quina compression in a patient who is 75 years old with spinal stenosis. Do I need to act urgently?
Spinal claudication duet o spinal stenosis is a slowly progressive compression of the caudae quina over a long period of time. The pathology is different, and the sacral roots usually accommodate so the patients have caudae quina compression but not caudae quina syndrome.
Tell me more of caudae quina syndrome (CES).
Caudae quina syndrome is typically bilateral radiculopathy with reduced perineal sensation (S3–S5 dermatomes disturbance of bladder and/or bowel and/or sexual function. It often presents on a spectrum between simple radiculopathy with no bladder, bowel or perineal sensory symptoms and CE Swith the full complement of symptoms.
The pathophysiology of CES includes compression of the caudae quina within the lumbosacral region [1].
Traumatic: disc herniation, epidural haematoma, retropulsion from bony fragment.
Tumours: intramedullary or extramedullary.
Infective epidural abscess.
Degenerative spinal stenosis.
Do you know the subtypes of CES?
Subtypes of CES include: CES incomplete (CESI): patient has objective evidence of CES – commonly impaired perineal sensation; They have preserved voluntary control of initiating; stopping micturition; bowel emptying but may exhibit some degree of disturbance (for example; it is important to note that there may not be complete loss of caudae quina function.
You managed to arrange an urgent MR Iof lumbosacral spine after discussing with the radiologist on call. The radiologist phoned you at 5 pm and reported that the MRI scan showed radiological evidence of caudal equina syndrome. What would you do now?
I would explain to her that this requires emergent decompression; this is conventionally with agene rous midline decompression and discectomy. The operation should be carried out on an emergency basis within 48 hours of symptom onset [2]. Meta-analysis has shown that the patient has better outcome in terms of bladder and bowel function if decompression surgery is performed within 48 hours of symptom onset.
How would you perform a decompression for caudae quina syndrome?
I would approach the lumbar spine through posterior midline approach utilizing the inter nervous plane between two paraspinal muscles (erector spinae). Deep dissection involves performing a laminotomy of the proximal lamina until lamina has been resected above the ligamentum flavum insertion on its under side. The ligamentum flavum is then resected from proximal to distal before the laminotomy of the distal lamina is performed by undercuting it. When the decompression is full width the lateral edge of the dura is identified, and the nerveroot can be retracted to access the disc and remove it.
The strategy is to ensure adequate decompression of the caudae quina at the end of the operation.
What are the complications of the operation?
Local complications: damage to dura nerveroots and incomplete decompression. General complications: deep vein thrombosis, pulmonary embolism, loss of airway during operations troke and myocardial infarction.
References#
1. Ah nUM, Ahn NU, Buchowski JM, Garrett ESSie ber AN, Kostuik JP. Caudae quina syndrome secondary to lumbar disc herniation – a meta-analysis of surgical outcomes. Spine. 2000;25(12):1515–1522.
2. Gleave JRW, Macfarlane R. Caudae quina syndrome: what is the relationship between timing of surgery and outcome? Br J Neurosurg. 2002;16(4):325–328.
Structured oral examination question 10#
Spinal trauma assessment
You are asked to review apa tien t with suspected spinal injury after a high-speed road traffic accident. The patient was stabilized in the Emergency department resuscitation bay but has persistent hypotension. What are your thoughts?
The hypotension is likely hypovolaemic shock secondary to blood loss, which is the most common after such an injury. I would assess the pa tientas with any other patient using the Advanced Trauma Life Support (ATLS) principles. The ATLS principles would then move on to breathing, circulation, disability and exposure.
You suspected spinal injury in this patient How are you going to assess this patient?
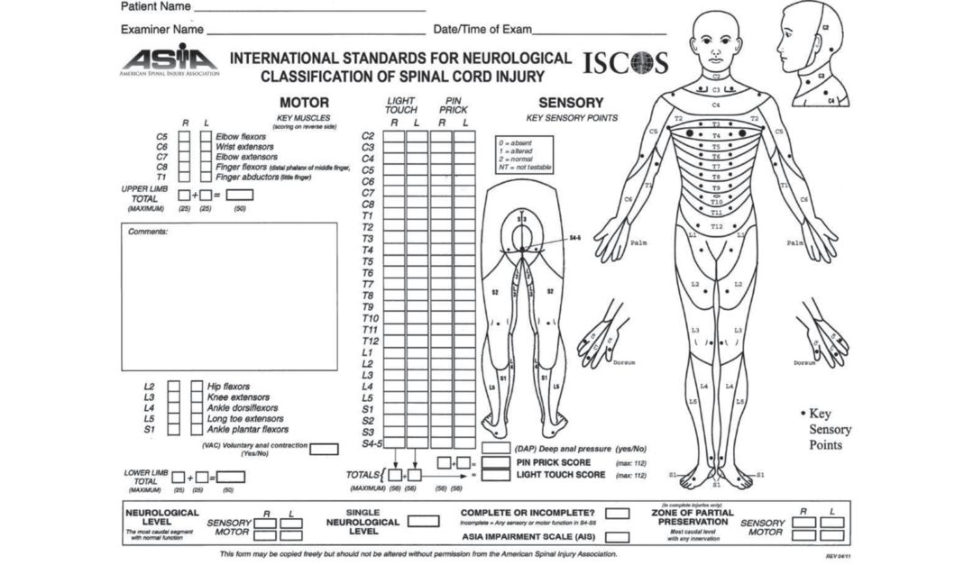
Assuming ATLS principles have been applied in the initial management of this patient and life-threatening injuries have been excluded, I would proceed to assess the cervical, thoracic and lumbar spine. The patient needs to be log-rolled with full protection of the cervical spine during clinical examination of the thoracolumbar spine looking for swelling, bruising, deformity and focal pain on palpation of the thoracolumbar spine, which may indicate posterior spinal column injury. I would complete the examination by performing a complete neurological examination of each dermatome and myotome using the American Spinal Injury Association (ASIA) chart ( Figure 15.9) [1].
What investigations would you request?
Reformat in three planes of the cervical, thoracic and lumbar spine would be available for viewing as part of the whole-body CT scan and early report by the duty radiologist would influence the initial management of this patient This is now a routine practice in all major trauma centres int heUK.
What do you understand by the term neurogenic shock?
Neurogenic shock occurs due to disruption of the sympathetic pathways in the spinal cord with resultant peripheral vasodilation, a decrease in peripheral vascular resistance and drop in blood pressure. Depending on the level of the spinal cord injury there may also be bradycardia present due to loss of sympathetic cardiac innervation.
What do you understand by the term spinal shock?
Spinal shock is a neurological phenomenon. It is a temporary loss of spinal cord function and reflex activity below the level of the injury.
What is the importance of spinal shock and how do you know when it’s over?
The importance of spinal shock is that one cannot evaluate the neurologic deficit until the spinal shock phase has resolved.
So, what are you going to do with this spinal problem?
If the spine is sufficiently stable under physiological load to resist deformity, with no significant pain and neurological deficit, the injury is considered stable and can be managed conservatively; 10% of spinal fractures will have non- contiguous injuries elsewhere, so these need to be excluded with imaging.
How will you decide if it is stable?
This is decided by recognizing patterns of injury. Those insignificant, e.g. isolated transverse process, fractures require no further treatment. Clearly unstable fractures, e.g. rotational or translation injuries, are likely to require surgical management.
Figure 15.9 ASIA chart.
Reference#
1. Dodwad SN, Dodwad SJ, Wisneski R, Khan SN. Retrospective analysis of thoracolumbar junction injuries using the thoracolumbar injury severity and classification sc ore, American Spinal Injury Association class, injury severity score, age, sex, and length of hospitalization . Clin Spine Surg. 2015;28(7):E410–416.
Notes
1. The candidate is stuck in the A&E department and can’t get to theatre for the surgery.
2. Haematomyelia–haemorrhage centrally causing mass effect on MRI imaging.
3. Vaccaro AR, Kim DH, Brod keDS, et al. Diagnosis and management of thoracolumbar spine fractures. J Bone Joint Surg. 2003;85(12):2456–2470.
4. There are no absolutes and we think it is at least worth trying to sneak these in.
5. Abducens nerve responsible for causing contraction of the lateral rectus muscle to abduct (i.e. turnout) the eye.