Chapter 18 Children’s orthopaedics
Introduction#
The paediatric viva section seems to contain the followings three areas:
1. One of the big paediatric topics such as DDH, septic hip, SUFE, clubfoot or knee deformities, during which in-depth knowledge is expected from candidates.
2. A common significant paediatric trauma such as elbow/supracondylar fracture, forearm fractures, femur fractures, NAI or paediatric ankle fractures. Again, the candidate is expected to have a solid knowledge about these subjects.
3. The last area is about common conditions that could face orthopaedic surgeons in any subspecialty such as bone cyst, multiple hereditary exostosis, tarsal coalition, pes cavus, osteochondritis dissec ans.
In this secft on, we follow the exam format with a simple question around a clinical picture, X-ray or a video clip, followed by increasingly difficult questions to explore candidate depth and breadth of knowledge. The online version of this book will have more cases, videos and discussion. This section complements the first edition of this book, the postgraduate paediatric orthopaedic book (the green book) [1] and the third edition of the parent book.
Candidate 1#
This is a clinical photograph of a child (Figure 18.1) who tripped and fell, hurting his knee. He was seen in the A&E department and referred to your fracture clinic. Describe what you see. How would you approach him?
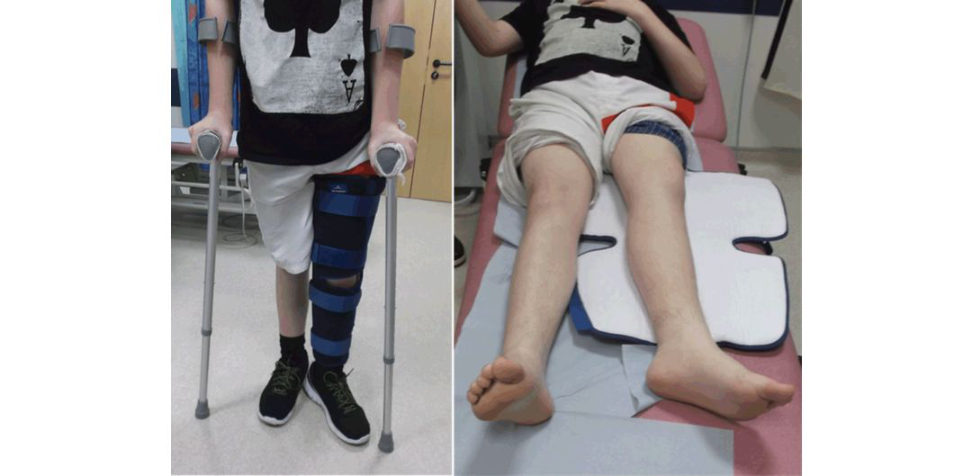
My approach is to take a detailed history, perform a thorough examination and or der the appropriate investigations guided by my examination and provisional diagnosis. The left leg is externally rotated and may be short.
How can you confirm your diagnosis?
History, examination and radiological tests to confirm my diagnosis. Hip examination may reveal limited internal rotation or even obligatory external rotation on flexing the hip (Drehmann sign). I also request pelvis X-ray (AP and cross-table lateral views of both hips).
This is his pelvis X-ray (Figure 18.2). What can you see?
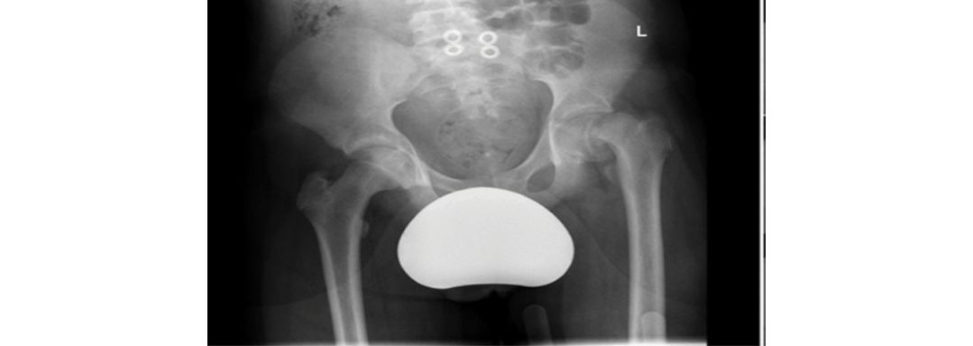
This is a plain X-ray of the pelvis (AP view only) showing both hips. The head remained in the socket while the neck moves anteriorly and superiorly. Trethowan’s sign is positive; a line (often referred to as Klein’s line) drawn on the superior border of the femoral neck on the AP view should pass through the femoral head. In SUFE, the line passes over the head rather than through the head.
What other radiological signs might you see in SUFE?
Several radiological signs are described to aid diagnosing SUFE (particularly subtle ones). These are not present in every case of SUFE, such as Trethowan’s sign that I just mentioned; widening and irregularity of the growth plate (early sign); decreased epiphyseal height as the head slipped posteriorly behind the neck; remodelling changes of the neck and increased distance between the teardrop and the femoral neck metaphysis.
What if this child’s X-ray was normal?
Normal X-ray does not exclude SUFE (it may be in the preslip stage); therefore,
Can you grade the severity?
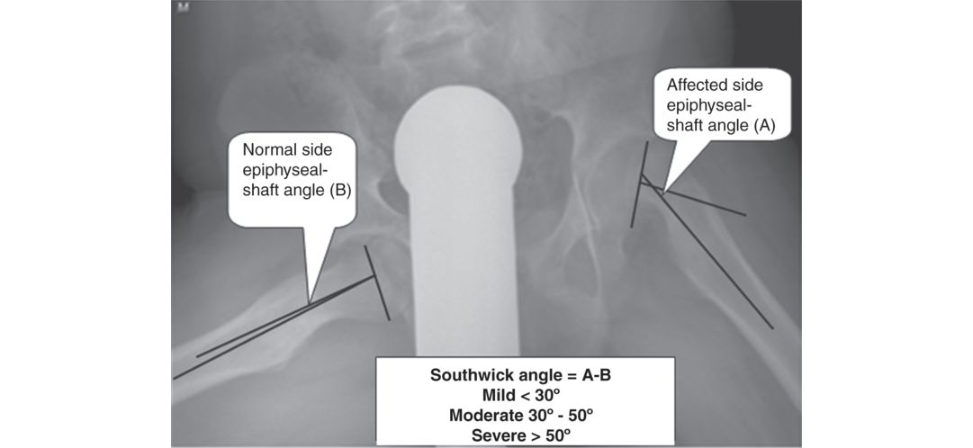
I measure the severity using either Wilson grading on the AP views or the Southwick angle on the lateral views.
Can you draw for me how these two classifications measure the severity of the slip?
Southwick graded the severity on the frog lateral view by measuring the Southwick angle, which is the difference between the lateral epiphyseal shaft angle of the slipped and the non-slipped sides (Figure 18.4). Mild slip (grade I) has an angle difference of less than 30°, moderate slip (grade II) has an angle difference of between 30° and 50° and severe slip has a difference of over 50°. If both sides slipped, Southwick angle is calculated by subtracting 12° from the corresponding lateral epiphyseal shaft angle.
You mentioned that the slip is stable. Why?
Randall Loder [2] classified SUFE into two types: Unstable slip: child is notable to weight bear on the affected side even with crutches; The risk of AVN is high in an unstable SUFE; In Loder’s original paper the AVN rate was 47% in unstable SUFE; 0% instable ones; Similar findings were shown in other centres [3; There has been some confusion about the exact meaning of ‘able to weight bear’ in Loder’s original paper; there must be enough stability to allow him to stand.
Figure 18.1 Twelve-year-old boy who tripped and fell.
Figure 18.2 Pelvis X-ray of 12-year-old child with knee pain shown in Figure 18.1.
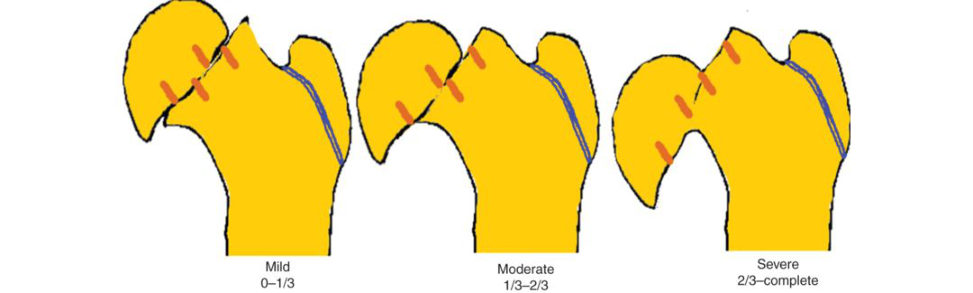
Figure 18.3 SUFE radiological grading.
Figure 18.4 Southwick angle.
How would you treat this child?
This child has grade III stable slip. My options are: 1. Pinning in situ to stabilize the slip and prevent further progression until physis closure. 2. Primary open reduction and internal fixation Several techniques have been described and currently the Ganz surgical dislocation is the preferred option.
Do you think you can pin this SUFE?
Yes, although it will not be easy and the worse the deformity is the more difficult the pinning in situ will be.
Take me though how you would pin it.
Before I perform any operation, I will make sure that my patient is as fit as can be for surgery. I review their health records investigations and obtain an informed consent for surgery. The operation is done undergeneral anaesthetic (GA Intravenous antibiotic is given at induction. The patient is positioned supine on a fracture table (without traction). (In bilateral stable slip, a radiolucent table is preferred over the fracture table because it reduces the chance of worsening the contralateral slip by overenthusiastic positioning.
The trajectory of my screw is identified and marked using a free guide wire placed on the skin overlying the proximal part.
The entry point is usually quite anterior. It is essential to screen the hip to ensure there is no protrusion of the guide pin in the joint; particularly in the blind spot ( Figure 18.6). For unstable slips, a second guide wire is useful to provide some rotational stability and can be used for the insertion of a second cannulated screw if desired.
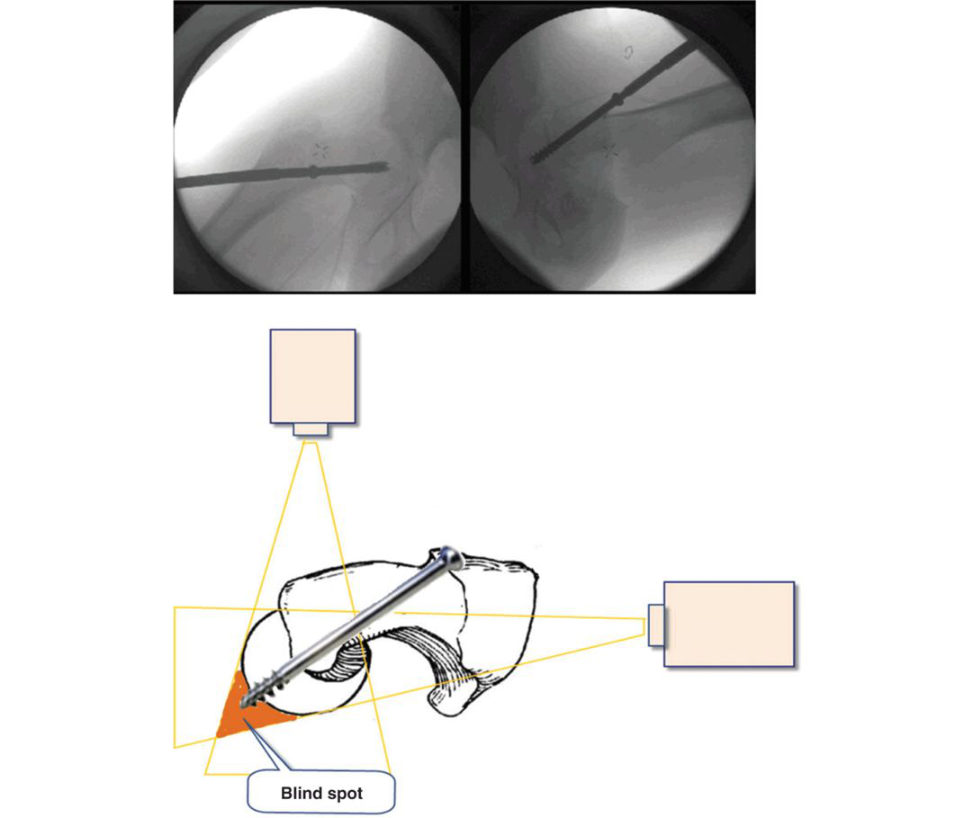
After the appropriate screw length has been determined, the femoral neck and epiphysis is drilled using the cannulated.
I prefer to use a 7.3- or 6.5-mm fully threaded, reversed cuting cannulated screw. If available, 3D C-arm is valuable for this purpose.
Follow-up is until ph yseal closure.
Would you pin the other side?
Age of the child (< 10 years is associated with a higher risk of bilaterality). 2. Slips associated with renal osteodystrophy and endocrine disorders (a high incidence of bilaterality approaching 95%). The quoted risk of contralateral slip varies from 18% to 60%. The proponents and opponents have some evidence to support their views [5]. Both of these markers are not perfect and do not have 100% positive or negative predictive value. I would have a low threshold to prophylactically pin the other side if the posterior sloping angle is more than 14° as research has shown that the risk of contralateral slip would be around 83%.
Can you draw the posterior slip angle?
The above scenario is typical; however, the examiners may wish to explore the following (this is a good sign indicating that you have done well to reach these areas): 1. Single or double screws for unstable severe slips: double screws offer 66% stiffer construct than single screws, but the risk of intra-articular penetration increases from 4% to 20% with double screws. c. 2. Management of grade III slips; open reduction with or without surgical dislocation: both can be used as longas there is no undue pressure on the retanicular blood vessles. Parsch [8] reported 4.7% AVN with open reduction without surgical dislocation while Ganz [ 9] reported no AVN with surgical dislocation. In a systematic review and meta-analysis we compared all treatment options and risk of AVN, and surgical dislocation has 3% A VN rate but better patient satisfaction rates whereas PIS has 1.5% AVN rate and lower satisfaction rates [3,10].
This is a clinical photograph of the elbow of a 5-year-old child who fell off a monkey bar (Figure 18.8). How would you manage this child?
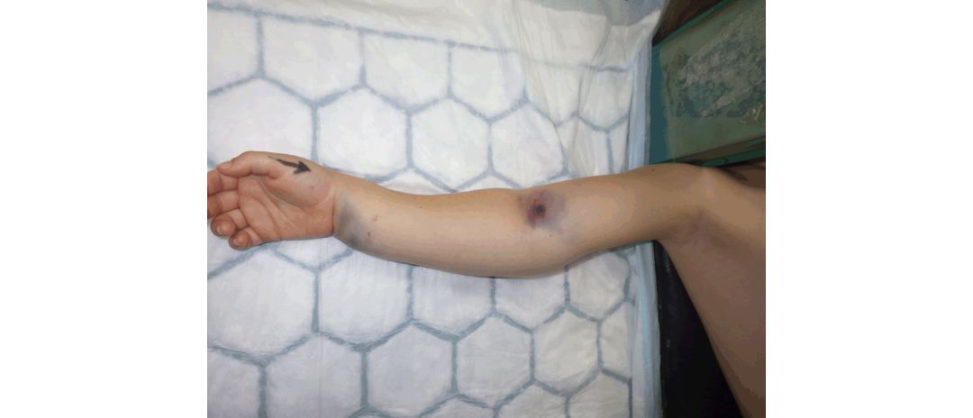
The photograph shows wrist and elbow swelling, deformity and bruises. This child most likely has wrist and supracondylar fractures of the humerus (SCH#). I always follow the ATLS protocols in assessing and managing traumatic injuries in children.
You perform primary and secondary surveys and find that this is an isolated upper limb injury.
I assess the movement of the joints that are not involved to ensure that there are no unexpected problems. I would not move the elbow joint at this stage as it is expected to be painful. I assess the neurovascular status of the limb using special tests to test for nerve injuries.
You find the hand warm and relatively well perfused but there was no radial pulse.
What about the neurological status?
The child was not cooperative and you could not assess him optimally despite your best effort.
This is not an uncommon scenario. I would like to confirm the diagnosis by requesting an X -ray.
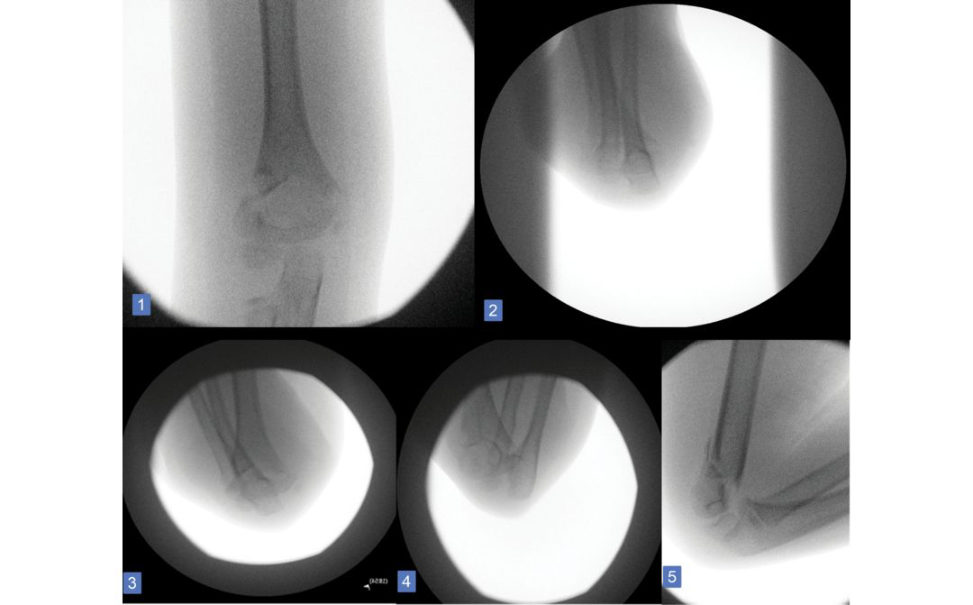
This was his X-ray.
The radiograph confirms my thoughts that this child has supracondylar humeral and distal radius fractures. The supracondylar humerus fracture is an extension type (Gartland type III) injury with the distal fragment displaced posteriorly and rotated externally. I would like to take the patient to theatre to reduce and stabilize the fracture.
How did Gartland classify these fractures?
Gartland classified this fracture into three types: Type I (undisplaced); type II angulated.
How do you fix this fracture?
The fracture pattern is extension type (Gartland type III), there may be some comminution. There is a wrist fracture distally which complicates things further. I still think closed reduction and percutaneous pinning (using two or three 2-mm K-wires) will be successful; however, an open reduction may become necessary. I will gently check how easily I can reduce both fractures. I will use the mid-forearm part for applying the traction to avoid traction damage to the distal neurovascular structures crossing the wrist fracture. Traction usually takes between 1 and 3 minutes to allow for the muscle to relax and the soft tissue to stretch. Successful traction should allow the visibility of the fracture without overlapping of the proximal and the distal fragments on the AP screening. This makes reduction more stable because the main pull vector of the triceps muscle becomes the fracture compressor (or even flexor) rather than the extensor. Fluoroscopic assessment to confirm reduction using AP and two oblique views at 90° (lateral and medial oblique views). A lateral view can betaken either by carefully rotating the elbow if the fracture is stable enough or by rotating the X -ray machine if not. After flexing the elbow, there will be overlapping of the proximal ulna and radius over the fracture site Jone’s view) but it is still possible to assess the continuity of the medial and lateral columns and Baumann’s angle (see Figure 18.10). There are two methods that I use depending on the fracture stability and the experience of my assistant (Figure 18.11). If the fracture is stable and I do not have an experienced assistant, I would tape the limb (hand to shoulder as in Figure 18.11) to keep it reduced; otherwise, I will rely on my assistant to hold it reduced during the procedure.
Then I prepare the skin using antiseptic solution and dr ape the upper limbI use two smooth K-wires (size 2 mm unless the child is very small, when I use a smaller size).
(holding up to six cortices – this is not always possible depending on the site and direction of the fracture). Then I t est the fracture stability; if it is stable, I will do the wrist, but if not, I may supplement with a third wire or I may use the medial wire. The latter requires a small incision to visualize the ulnar nerve.
This is what has been done. Any thoughts?
The images showed a good reduction of the humeral fracture. There may be a slight lateral translation on the AP view. The positions of the wires are perfect. This gives good purchase to the bones as it passes through six cortices. On the lateral they are both in good position.
Was the second wire in the wrist necessary?
I think so, although it is not always possible to correctly judge the stability of a fracture from a static 2D picture Moreover, the risk of compartment syndrome is high in this patient and it is important to obtain a stable fixation in an ticipa tion of c ast splinting or even removal if compartment syndrome happens or if the vascular surgeon decides to explore and repair a blood vessel in this case.
Fair enough. You stabilized the fracture but the radial pulse did not return. What would you do?
However, if the upper limb remains ischaemic (pale, cold, delayed capillary refill and pulseless limb) after fracture reduction, a surgeon competent to perform small vessel vascular repair should explore the brachial artery and that is why I informed them before taking the child to surgery [11].
Authors’ note: 2
Fractures around the elbow are commonly featured in the exam as they have diagnostic,
Always practise with your colleagues and seniors the five ‘whys’ questions until you become confident to tackle any potential questions in these areas.
Candidates must also know the following topics inequivalent detail:
1. Gunstock deformity.
2. Lateral condyle fracture.
3. Medial condyle fracture.
This young boy presented with the above toe deformity. What is your thought?
The pictures show a typical overlapping fitih toe. It is a congenital deformity of the fitih toe which overlaps the fourth. The toe is usually adducted and externally rotated and the MTPJ is dorsiflexed. I usually advise non-operativ e treatment in the form of passive stretching, neighbour taping and shoe modifications.
How do you perform Butler’s procedure?
Then I close the skin (Y inV at the plantar aspect and V in Y at the dorsal aspect) (see Figure 18.14).
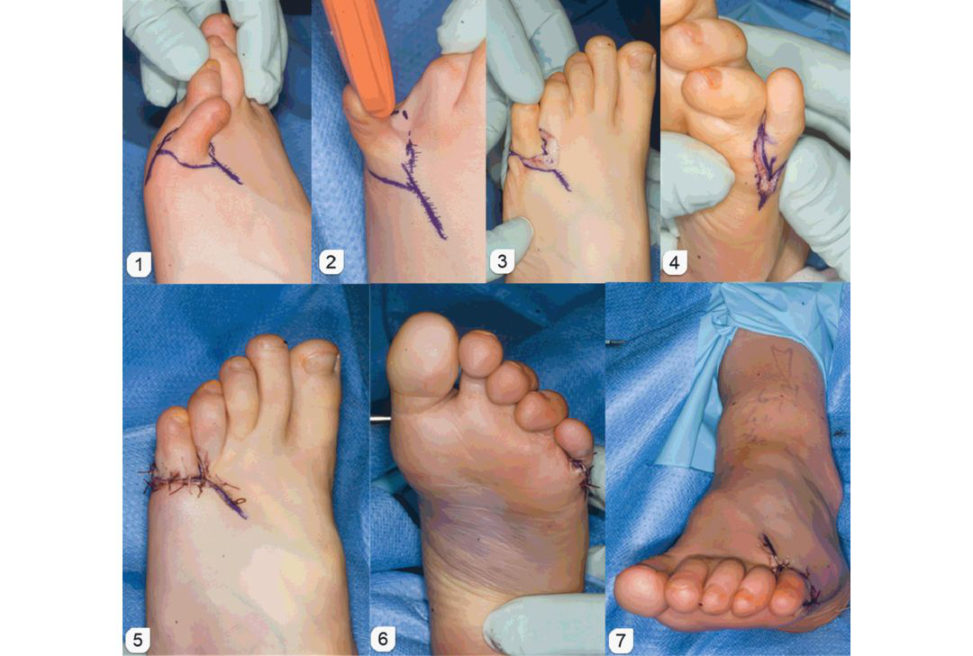
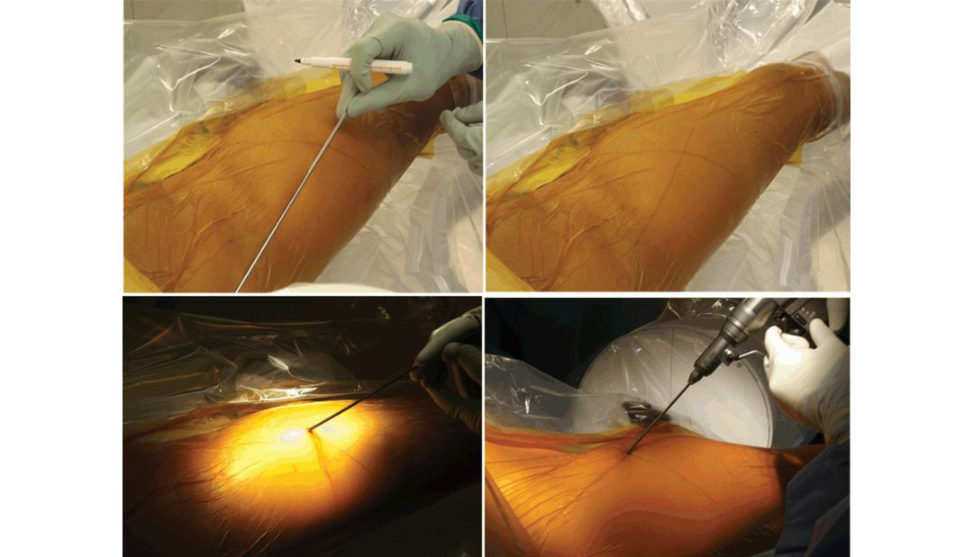
Figure 18.5 Pinning in situ.
Figure 18.6 Blind spot.
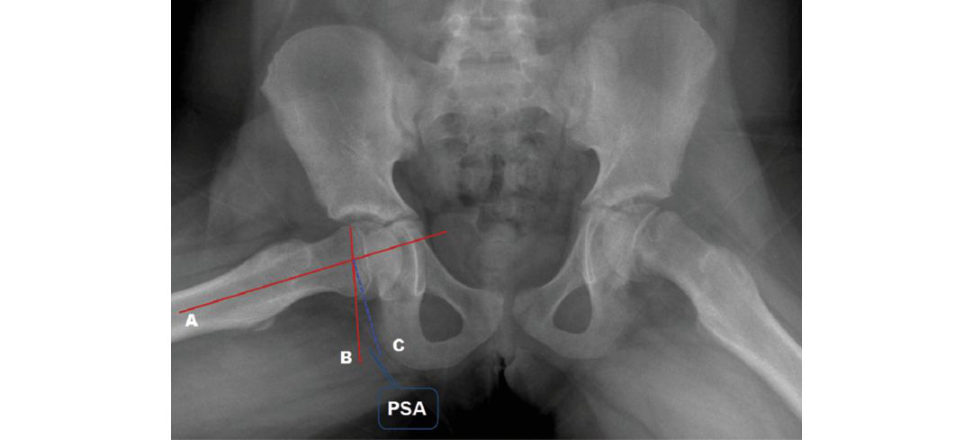
Figure 18.7 Posterior sloping angle.
Figure 18.8 A clinical photograph of a child who fell off a monkey bar.
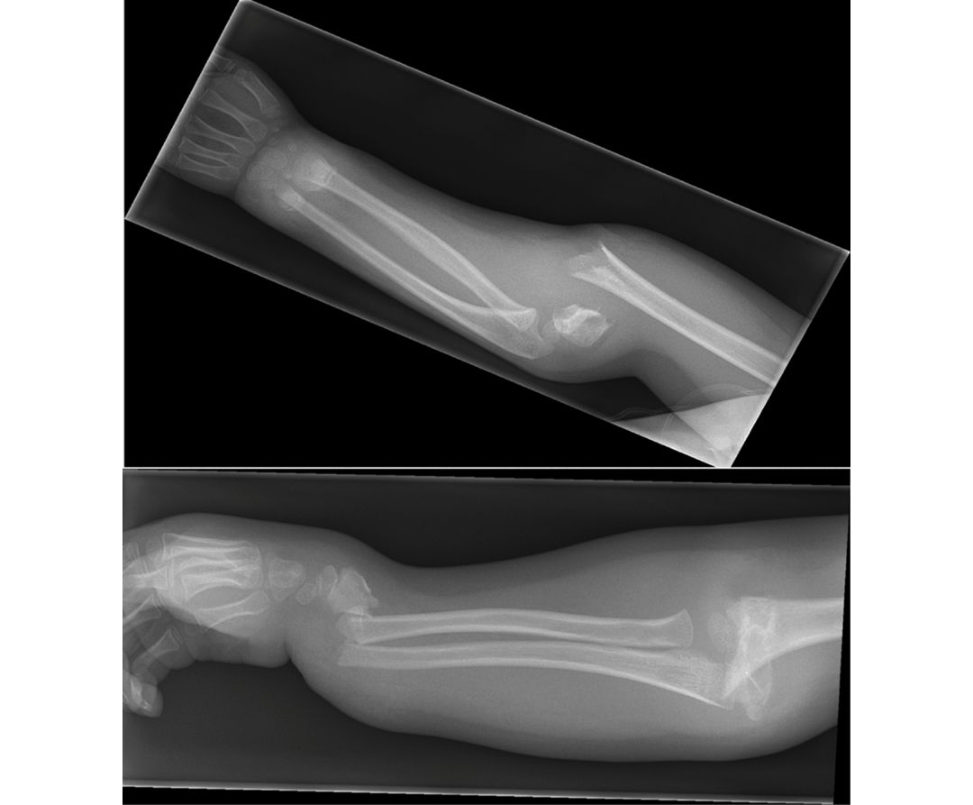
Figure 18.9 Plain radiograph of the child who fell off a monkey bar.
Figure 18.10 Reducing supracondylar humeral fracture.
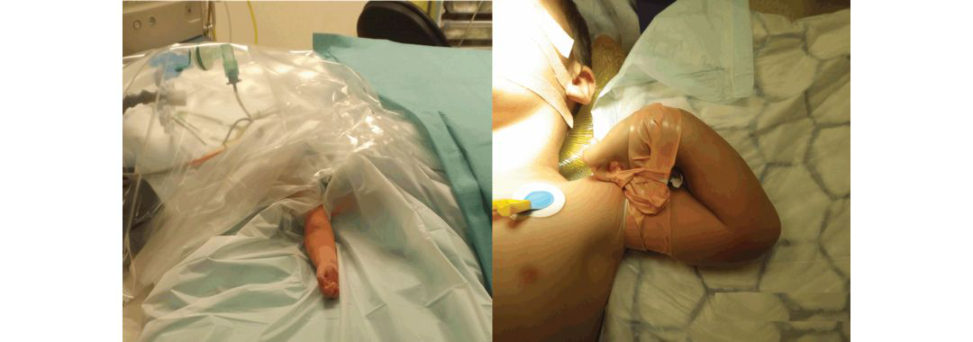
Figure 18.11 Supracondylar methods of fixation.
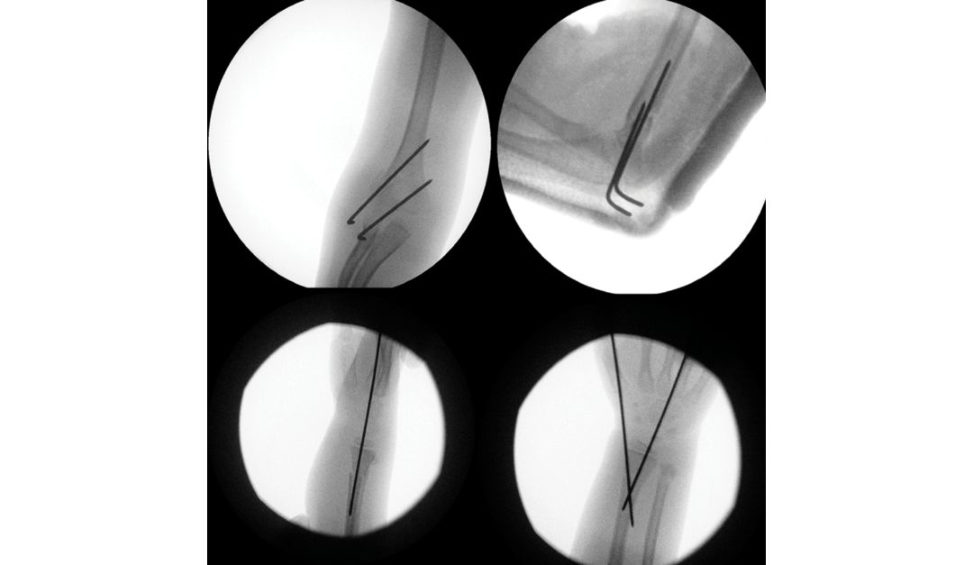
Figure 18.12 Intraoperative fluoroscopy images.
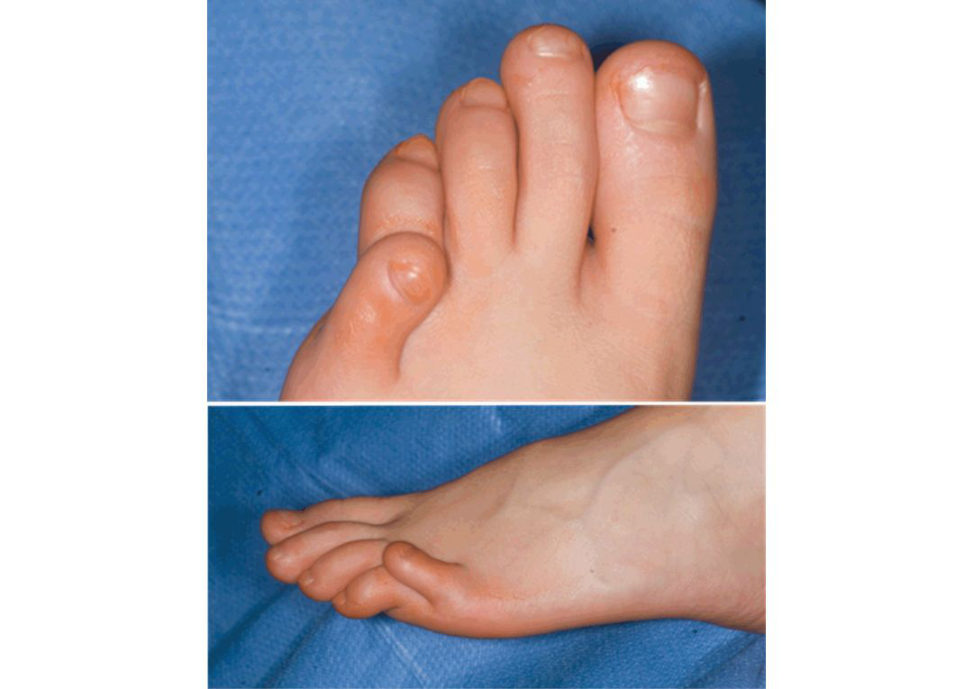
Figure 18.13 A child with the liti let oe deformity.
Figure 18.14 Butler’s procedure.
Table 18.1 Modified Gartland classification
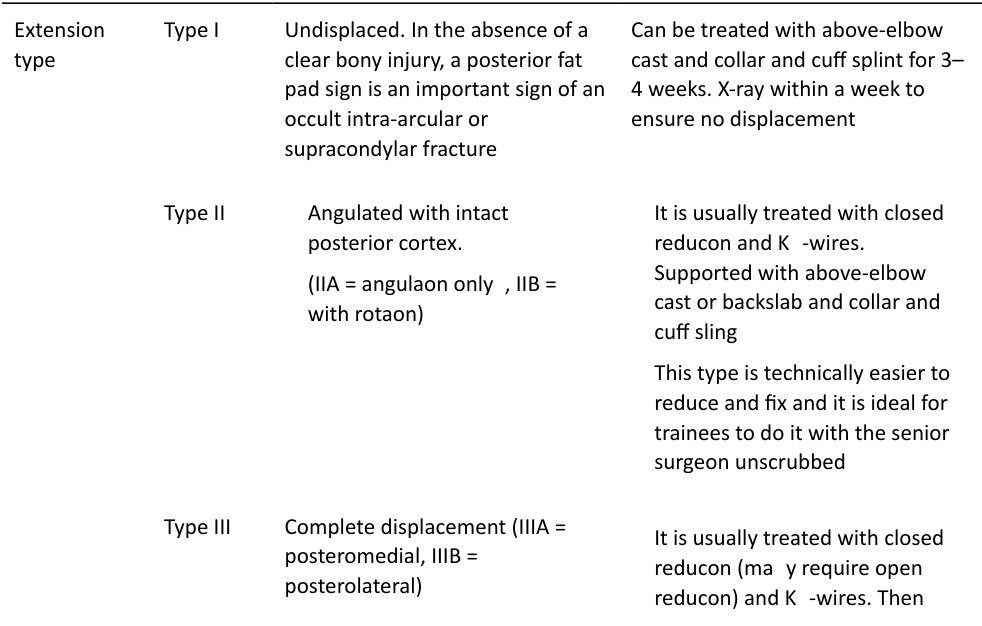
above-elbow back slab and collar and cuff sling
This type can be technically demanding and some experience is required
As in type III, but even with three wires this type can still be unstable
This indicates that the thin posterior periosteum has been disrupted rendering the fracture very unstable.
1. Low and high SCH fractures (below and above the olecranon fossa), flexion type and medial comminutions are radiological signs that predict technically difficult surgery – be prepared.
2. Collar and cuff is part of the stabilization and should beworn 24/7. It is not for comfort as in forearm or wrist fractures.
Candidate 2#
This is a clinical photograph of newly born foot (Figure 18.15). What can you see?
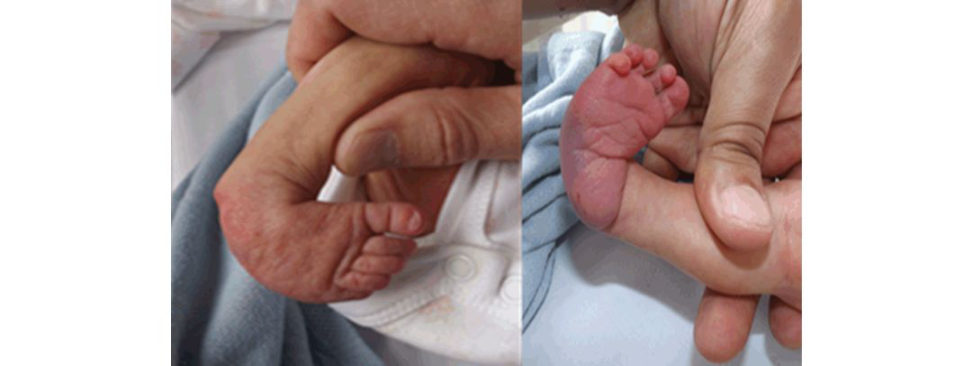
This photograph shows typical features of a clubfoot (congenital talipes equinovarus (CTEV)) deformity. It looks severe. There are two classifications in use to assess the severity: Pirani score and Dimeglio scoring system. The former is more popular int heUK.
How does Pirani score clubfeet?
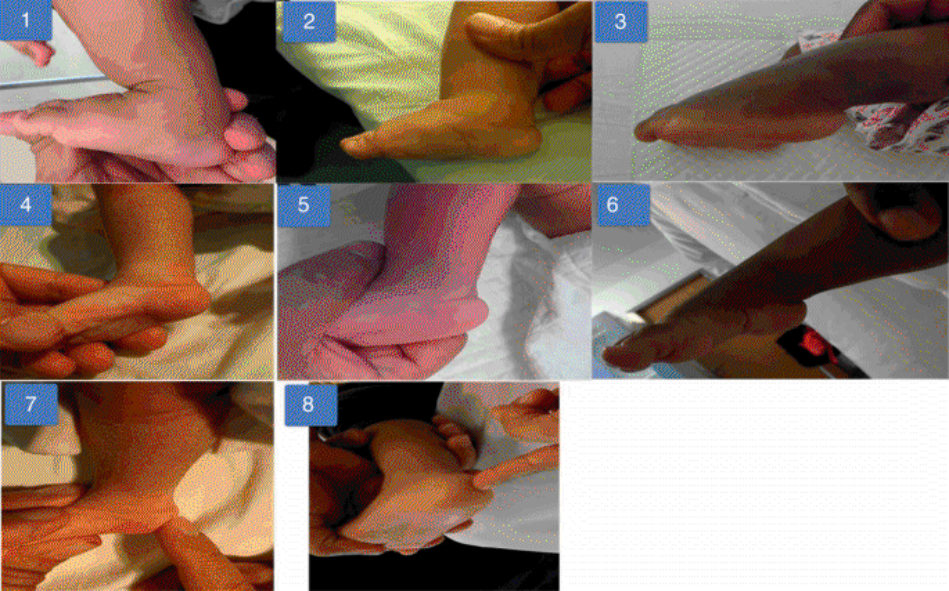
Each component is scored as 0 (normal), 0.5 (mildly abnormal) or 1 (severely abnormal) (Table 18.2). The six clinical signs are divided equally between the hind foot and midfoot as follows:
Hind Foot Contracture Score (HFCS) 0–3
1. Equinus.
2. Deep posterior crease.
3. Empty heel.
Midfoot Contracture Score (MFCS) 0–3
4. Curved lateral border.
5. Medial crease.
6. Lateral head of talus.
Figure 18.15 A newly born child with a foot deformity.
Table 18.2 Pirani score for clubfeet.
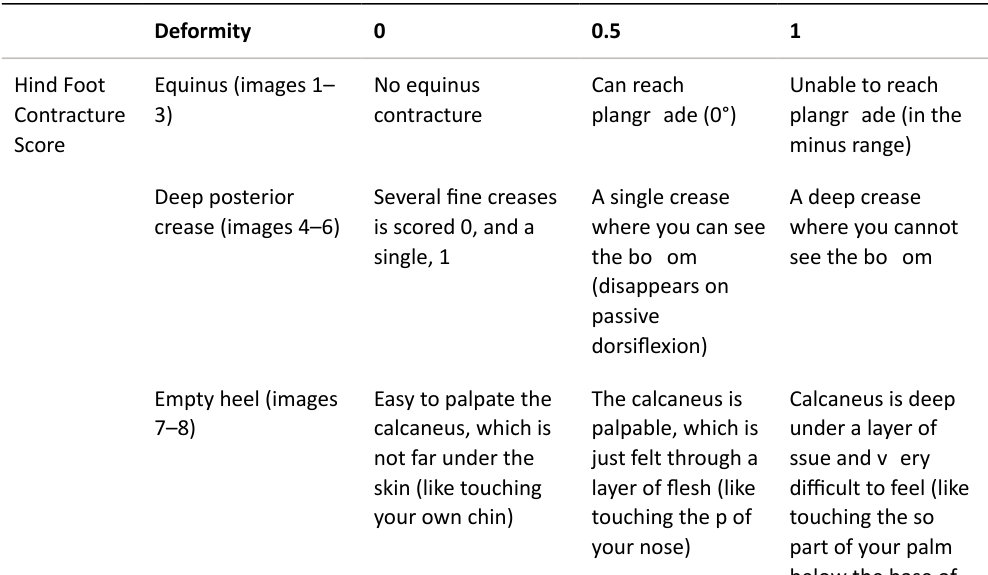
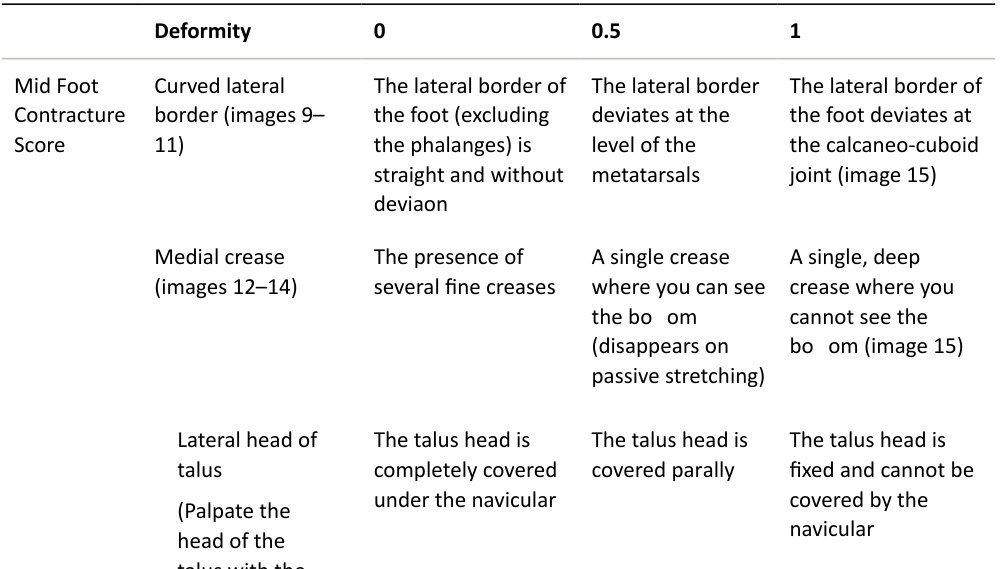
(Palpate the head of the talus with the foot uncorrected) (image 15)
Deformity 0 0.5 1
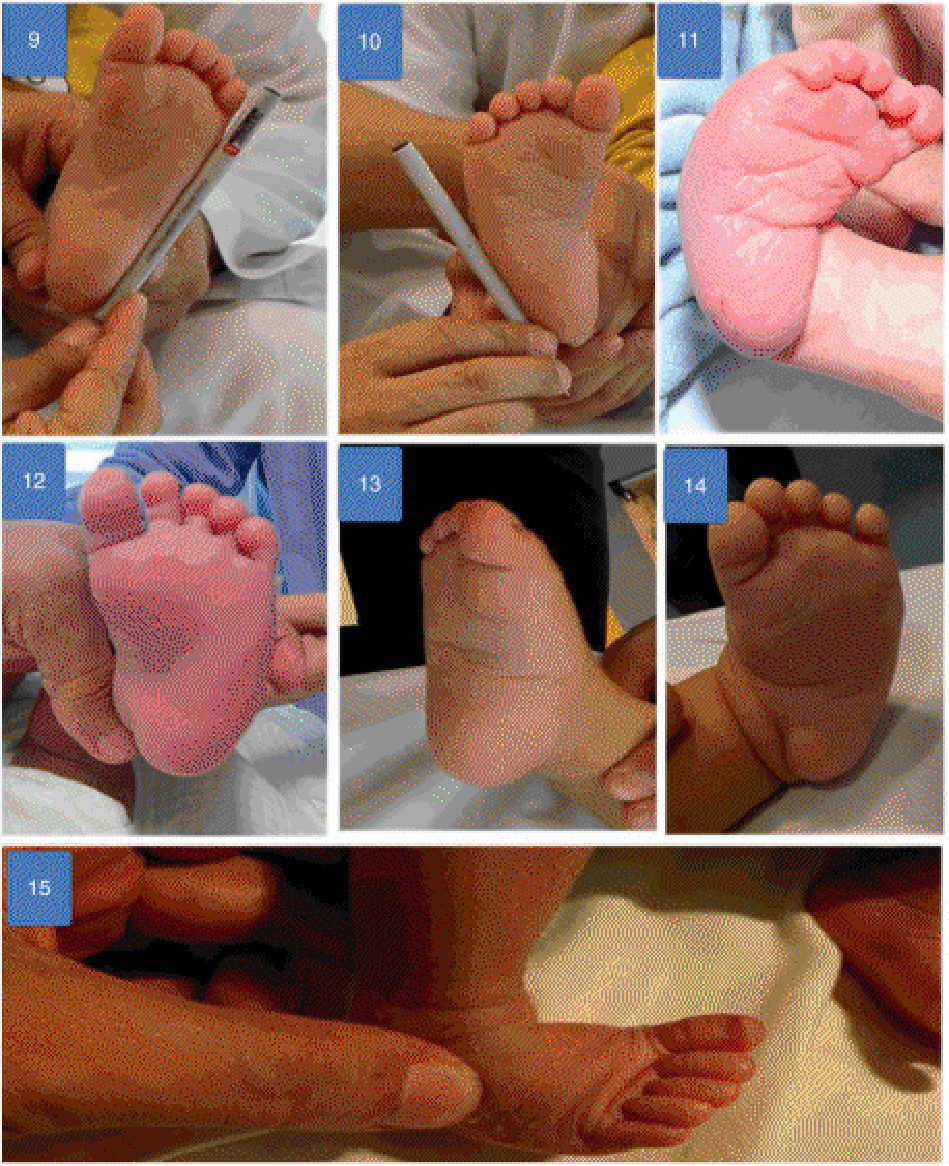
Pictures courtesy of Dr Sattar Alshryda.
Total Score (TS) 0–6
What causes clubfeet?
1. The neuropathic theory [12]: biopsies were taken from the posteromedial and peroneal muscle groups in 60 patients mostly under the age of 5 years. 2. The myopathic theory [13]: a histochemical analysis was made of 103 muscle biopsies taken from 62 patients with idiopathic clubfeet. Authors noticed the muscles in patients aged under 6 months contained 61% Type 1 fibres in the affected legs compared to 44.3% in normal legs. There is a 10% risk if a first-degree relative is affected; combination of en vironmental/genetic [ 14]. Recent link to PITX1, transcription factor critical for limb development. 5. Congenital constriction annular band. 6. Viral infection. 8. Multifactorial. a. 10% risk if a first-degree relative is affected: combination of en vironmental/genetic [ 14]. d. 25% have a family history.
7. Hand anomalies Streeter dysplasia/constriction band syndrome).
8. Diastrophic dwarfism.
9. Prune belly syndrome.
10. Opitz syndrome.
11. Larsen syndrome.
12. Anterior tibial artery hypoplasia or absence is common.
13. Tibial hemimelia.
How would you manage this child?
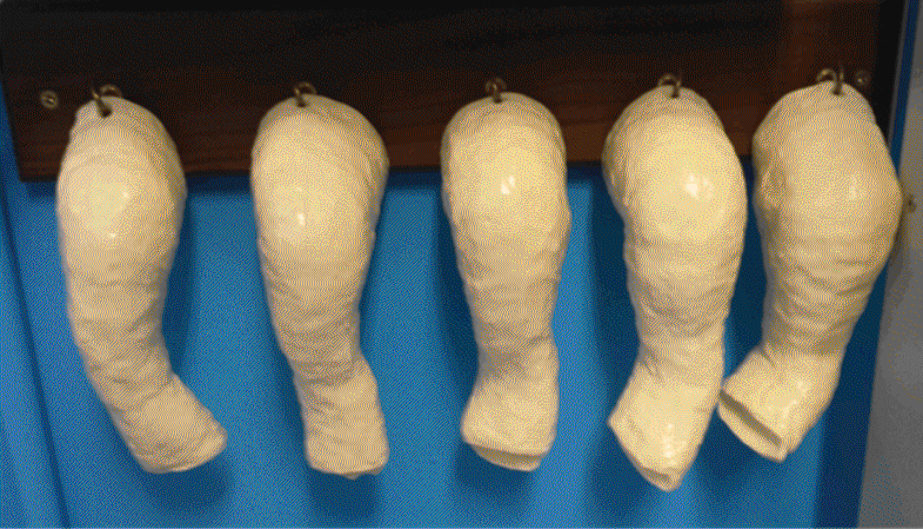
Most clubfeet are diagnosed prenatally in the 20-week scan and management and counselling starts before birth. Prenatal counselling is usually focused on the accuracy of diagnosis (65–90%) [15], potential associated conditions (see above) and treatments. Having established the diagnosis of idiopathic clubfeet, I recommend the Ponseft serial casting [16,17] (Figure 18.16). The treatment should be started as early as possible; the severity of the deformity is quantified using the Pir ani score, then serial casting weekly for an average of 4–6 cast changes. This usually corrects all deformities (CA V) with the exception of equinus, which requires a tendoachillis tenotomy in more than 90% of the cases. 3. Equinus of the heel corrections tarts in the serial casting stage, but often requires tendoachillis tenotomy for full correction in 90% of patients. Three signs indicate the right timet o start equinus correction: i. Forefoot abduction of approximately 60° in relationship to the frontal plane of the tibia. iii.
Tendoachillis tenotomy is performed when the residual equinus is about 0–5°.
Successful correction is followed by a regime of using Denis Browne (DB) splint (Figure 18.17) on a.
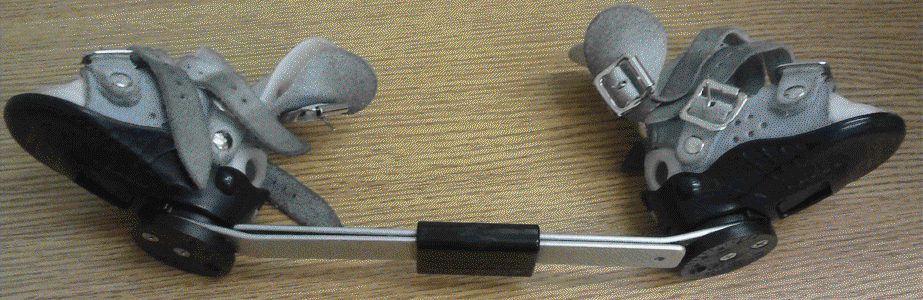
The bar should be bent 5–10° to hold the feet in dorsiflexion. For unilateral cases, the brace is set at 60–70°of external rotation on the clubfoot side and 30–40° of external rotation on the normal side. In bilateral cases, it is set at 70° of external rotation on each side.
This is another child who was referred to you with a clubfoot (Figure 18.18). Have a look at the picture and tellus what your thoughts are.
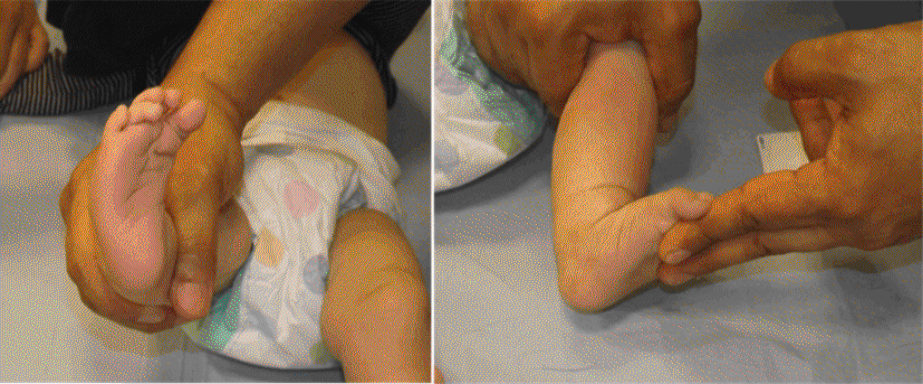
My thoughts are that the child has a metatarsus adductus and not a clubfoot. I need to examine the child to confirm my thoughts.
Tell me more about metatarsus adductus (MA)?
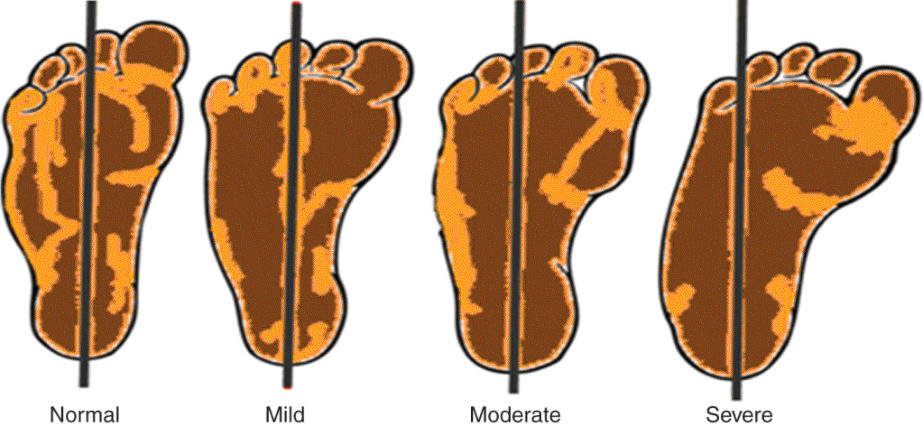
As the name implies, the metatarsus (forefoot) is adducted in relation to the hind foot. It is as common as clubfeet (1 in 1000 births), no sex predominance and bilateral in approximately 50% of cases. For the same reasons, MA is linked to DDH (15–20%), torticollis and plagiocephaly. It can bepart of a more complex foot deformity such as clubfoot and skew foot. Bleck classified the severity using the heel bisector line into mild, moderate and severe (Figure 18.19).
How would you treat metatarsus adductus?
Isolated MA is a benign condition that resolves by the age of 5 years (or even earlier). Surgery is rarely indicated (and often unnecessary) before the age of 5. Lateral column shortening is done with cuboid closing wedge osteotomy. Medial column lengthening includes a cuneiform opening wedge osteotomy with medial capsular release and abductor hallucis longus recession.
How do you know whether the foot is long or short?
By comparing it to the standard growth charts.
Authors’ note: 3
Clubfoot is another A-list topic in the paediatric section. It should be an area where you get a full mark. The above scenario is a typical example for a straighfoorward pass performance.
Our advice is that you should aim for more than a pass by considering the following:
1. The Ponseft vs. the French method.
2. Complications of treatments.
3. Relapse and its treatment.
4. Potential operative intervention:
a. Posteromedial soft -tissue release and tendon lengthening.
b. Medial column lengthening or lateral column-shortening osteotomies.
c. Talectomy (in severe, rigid recurrent clubfoot in children with arthrogryposis).
d. Gradual correction using a circular frame.
Figure 18.16 The classic shapes of casts in Ponseft weekly serial casting.
Figure 18.17 Denis Browne boots.
Figure 18.19 Bleck classification of metatarsus adductus severity.
Figure 18.18 A child with right foot deformity.
Clubfoot, metatarsus adductus and congenital vertical talus are completely different conditions.
Make sure that you do not confuse them in the exam (and real life!).
The below is a photograph of a child with a thumb deformity (Figure 18.20). What is the diagnosis?
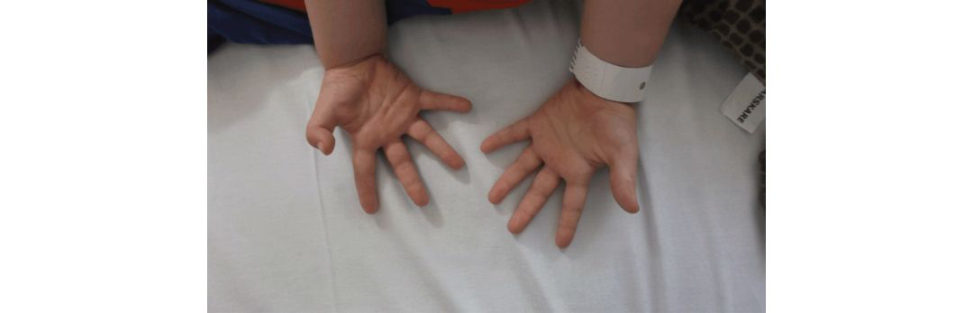
The right thumb IPJ looks in a fixed flexion deformity; the likely diagnosis is a congenital trigger thumb; however, without a proper examination, I cannot be certain.
You are correct. This is a trigger thumb. What would you tell the parents?
I will explain the management options including conservative (observation exercises, splinting) and surgical (open A1 pulley release or percutaneous A1 pulley release). In my practice, if conservative treatment fails, I would offer the child open A1 pulley release. Many of the study interpretations are vulnerable tobias [18].
Figure 18.20 A child with a thumb deformity.
Candidate 3#
You have been called to see an 8-year-old boy who presented to the A&E with limping on the right leg. How would you approach this child?
The list of causes for a limping child is long and ranges from trivial conditions that require just reassurance such as minor trauma to the most serious conditions that require admission investigations and urgent surgery, such as infections and tumours.
What do you want to know in the history?
I would like to know whether there is a history of trauma (trauma or SCFE), temperature (infection), upper respiratory tract infection or earache (transient synovitis constitutional symptoms and weight loss (tumour or infection).
There was no history of trauma, no temperature and no recent URTI or contact with an unwell child. He has never had this problem before and there are no swollen joints.
I will proceed with my examination, I would start with general signs and walking, then I examine his lower limbs, back and upper limbs.
You examined him and he was walking with obvious limp, he was holding his leg in a position of rest and there was a reluctance to move the right hip.
This is important information to know as I can now focus on hip causes of limping and I can investigate accordingly.
Your junior has already requested these as well as rheumatoid factor (RF) and serum uric acid (UA).
That is OK. I would not recommend checking RF and UA at this stage. When I want to find the diagnosis ASAP, I do not want to miss or delay important diagnosis such as infection Therefore, I requested the above bloodtests to estimate the probability of infection in this child using K ocher’s criteria.
What are Kocher’s criteria?
The criteria include: 1. Fever (> 38.5°C). InKo cher’s original paper, the predicted probability of septic arthritis with one positive predictor was 3%, two predictors 40%, three predictors 93% and four predictors 99.6%.
What about the CRP that you requested?
CR Pis more sensitive to infection thanE SR (although it was not mentioned in the K ocher criteria). It usually rises within 6 hours after an insult (whether infection or injury Caird and colleagues [19] noted that CRP (> 20 mg/l) was a further independent predictor of septic arthritis. It is s till expensive and not widely available [20,21].
Authors’ note: 4
The FRCS exam is about safe and high-standard practice. The above candidate scored high by quoting a well-recognized paper and showed that he kept updated with recent advances in the field (the PCT value in diagnosing septic arthritis). He could have emphasized the limitation of the evidence that he quoted, for example by saying, ‘It is important to appreciate that even when all Kocher’s criteria are negative the risk of infection is still present ranging from
0.3% to 17%’.
As this area is extremely important, we summarize the evidence below.
Kocher and colleagues [22] identified the above four independent predictors to differentiate between transient synovitis and septic arthritis:
The diagnosis of true septic arthritis which occurred in 38.
1. A positive finding on culture of joint fluid.
2. WCC ≥ 50,000 cells per cubic millimeter with positive findings on blood culture.
The diagnosis of presumed septic arthritis (44 patients was assigned when apa tien t had
WCC ≥ 50,000 cell per cubic millimeter in the joint fluid.
The diagnosis of transient synovitis (86 patients was assigned when the patient had WCC
< 50,000 cells per cubic millimetre in the joint with negative findings on culture,
Predicted probability of septic arthritis with one predictor was 3%, two predictors 40%, three predictors 93% and four predictors 99.6%.
Kocher validated his criteria prospectively in another study of 154 patients [23]: 24 had true septic arthritis, 27 were presumed to have septic arthritis, 103 had transient synovitis.
Table 18.3 Predictors for septic arthritis.
No. of predictors Predicted probability of septic arthritis (%)
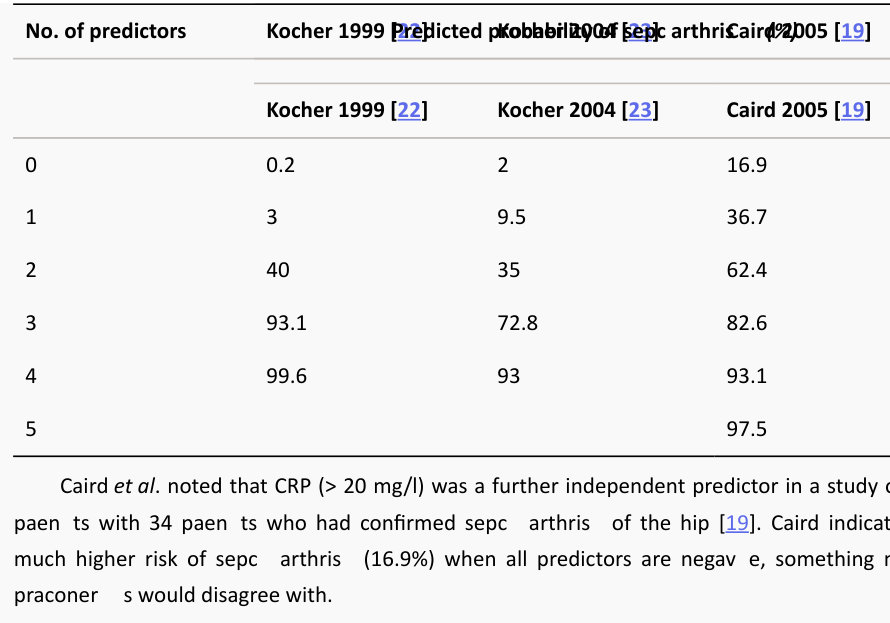
The CRP did not perform as well as PCT in a systematic review and meta-analysis by Zhao
[21]. The review included 10 studies (838 patients and found that the overall sensitivity of serum
PCT levels for the diagnosis of septic arthritis was 0.54 (95% CI, 0.41–0.66), and the specificity was
0.95 (95% CI, 0.87–0.98). The sensitivity and specificity of CRP were 0.45 (95% CI, 0.35–0.55) and
0.079 (95% CI, 0.0.021–0.25), respectively.
The bloodtests that you requested came all within normal. This is the X-ray that you requested.
On the top of my list isL egg Calves Perthes disease (LCPD), but there are others such as: 1. Infections (normal blood does not exclude septic arthritis or osteomyelitis ). 2. Multiple epiphyseal dysplasia (MED: as the name implies, there will be involvement of the other side and other joints). 3. Spondyloepiphyseal dysplasia (similar to the MED but with spinal involvement).
7. Hypothyroidism.
8. Meyer’s dysplasia.
How do you confirm your diagnosis?
Joint aspiration and MRI sc an could largely exclude joint and bone infection Thyroid function t est to rule out hypothyroidism, sickling testor HB electrophoresis to rule out sickle cell diseases, etc. Every test that I may use to confirm my top diagnosis (LCPD) has some limitation and the eventual diagnosis will have some uncertainty.
You did all these tests and you are convinced that this child has LCPD. How would you treat him?
My first line of treatment for all children with LCPD is to treat their symptoms and educate them and their parents about the disease itself.
How would you educate them?
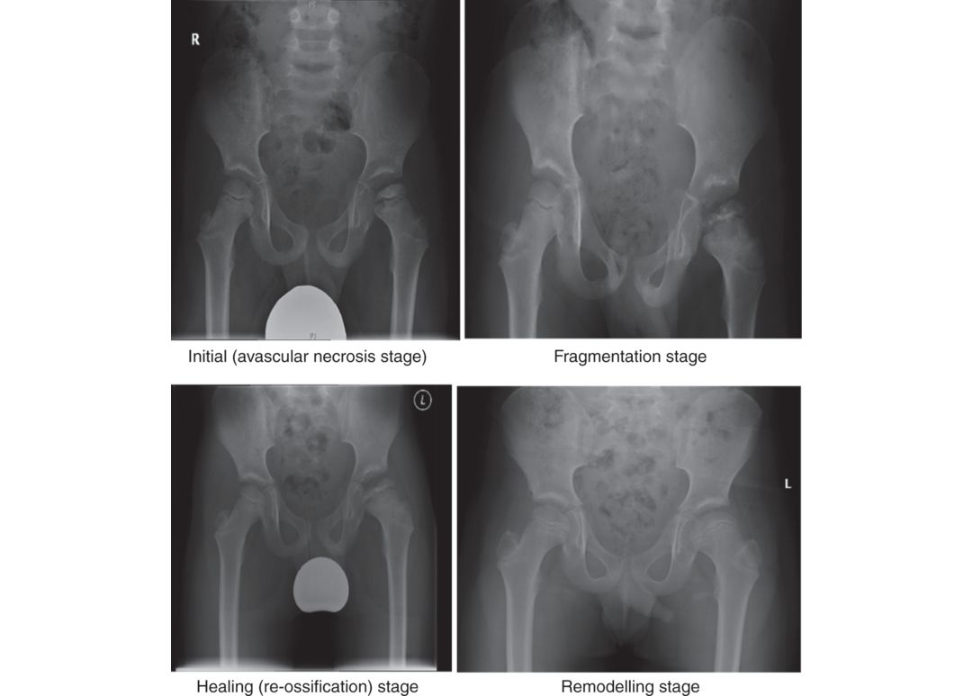
The disease is caused by interruption of blood supply to the femoral head. The blood supply is restored spontaneously over a period of 2–4 years. During this period the femoral head passes through distinctive stages (Figure 18.22): 1. Initial (also called necrotic or a vascular necrosis stage). 2. Fragmentation (or resorption stage). 3. Healing (re-ossification or reconstitution stage). 4. Remodelling stage. Each stage lasts 6 months on average (range 3–18 months). The classification depicts that the femoral head is made of three equal pillars (medial, middle and lateral). The severity is divided into four groups based on the height of the lateral pillar or third on the AP film at the beginning of the fragmentation stage (Figure 18.23).
Group A: Normal height of the lateral third of the head is maintained.
Group B: More than 50% of the original lateral pillar height is maintained.
Group C: Less than 50% of the original lateral pillar height is maintained.
Group B/C: Less than 50% of the original lateral pillar height is.
I would also explain that when LCPD is fully healed, there are other classification systems that can help us predict how well the child’s hip would do in the future.
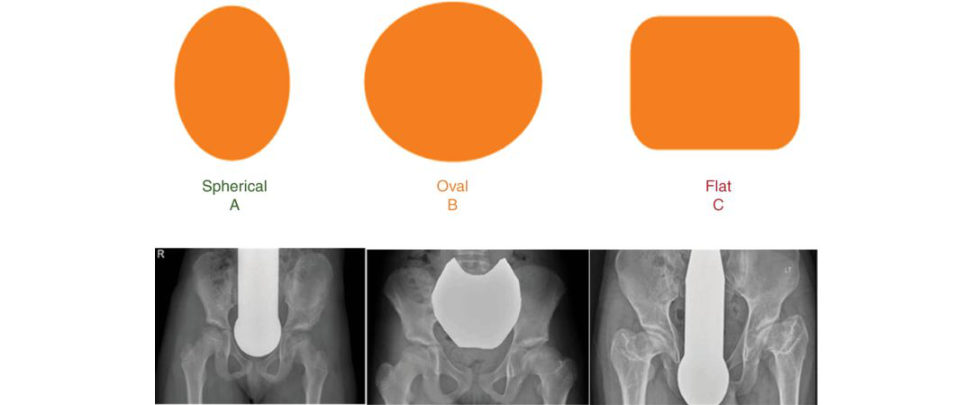
Stulberg classification ( Figure 18.24). It consists of three groups: Group A hips have a spherical femoral head, group B have an ovoid (or mushroom-shaped) femoral head and group C have a flat femoral head.
The following are not good signs (often referred to as the FOOBS):
1. Females.
2. Older children (older than 6 years).
3. Overweight.
4. Bilateral hip involvement.
5. Stiffness of the involved hip.
So which Herring group would you think this child belongs to?
I would classify this as group B. The lateral pillar is more than 50% (compared to the other side).
Would you consider surgery?
The evidence shows that containment surgery is beneficial inpatients with lateral pillar B and B/C stages who are 8 years or older [24,25]. It increases the number of patients with Stulberg A by 30%.
Have you done or seen femoral varus osteotomy for LCPD? Can you take me through it?
Yes. Preoperative planning is essential. It is important to ensure that there is a good hip abduction to compensate for the varisation of the femur. This step can be done in theatre using fluoroscopy.
The lower limbs are prepared and draped free. Adductors release may be required if there is significant tightness.
I use the lateral subvastus approach. The periosteum is incised and elevated with a Cobb elevator.
(3.5 mm for those under 35 kg and 5 mm for those above).
Jig angle = plate angle + the desired amount of varisation
So, if I want a varisation of 30°, I will use 110° plate and I set my jig to 140°.
It is important to mark rotation before performing the femoral osteotomy.
I use two K-wires; one above and one below the osteotomy, using the hockey stick (a small curved spanner on the paediatric locking plate that looks like a hockey stick) to identify the level of the femoral osteotomy.
I perform femoral osteotomy using an oscillating saw. Gentle soft -tissue releases around the osteotomy site to aid varisation. I fix the plate proximally then distally.
Would you do the same if this child has lateral pillar type C?
However, I may consider other options such as r est, traction, adductor release and Petri if there are significant stiffness and lateral extrusion.
Would you do the same if this child has lateral pillar type A?
If all children older than 8 years were to be offered surgical treatment, the group A and C hips would not likely benefit. These groups combined represent only 13% of hips presenting a t age older than 8, and this approach may be justified [ 26].
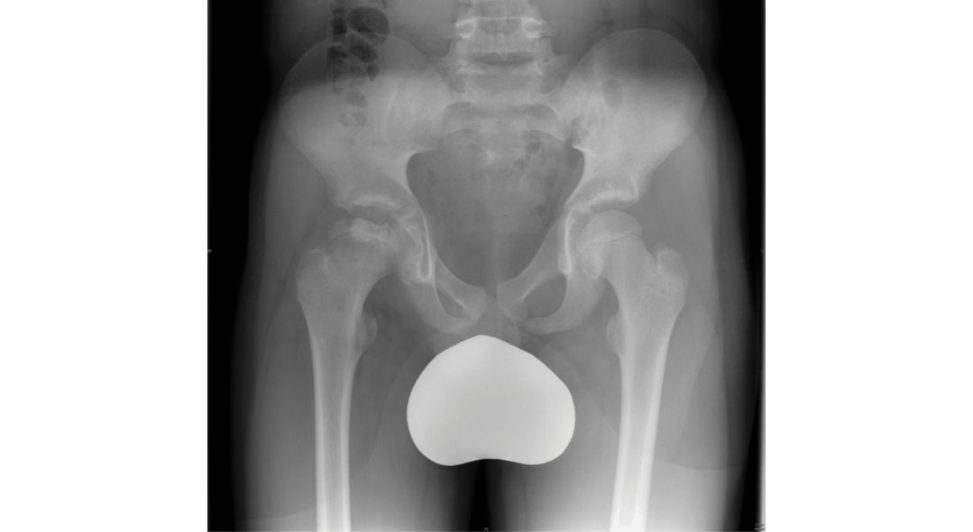
Figure 18.21 Pelvis X-ray of a child with right hip pain and limping.
Figure 18.22 LCPD stages.
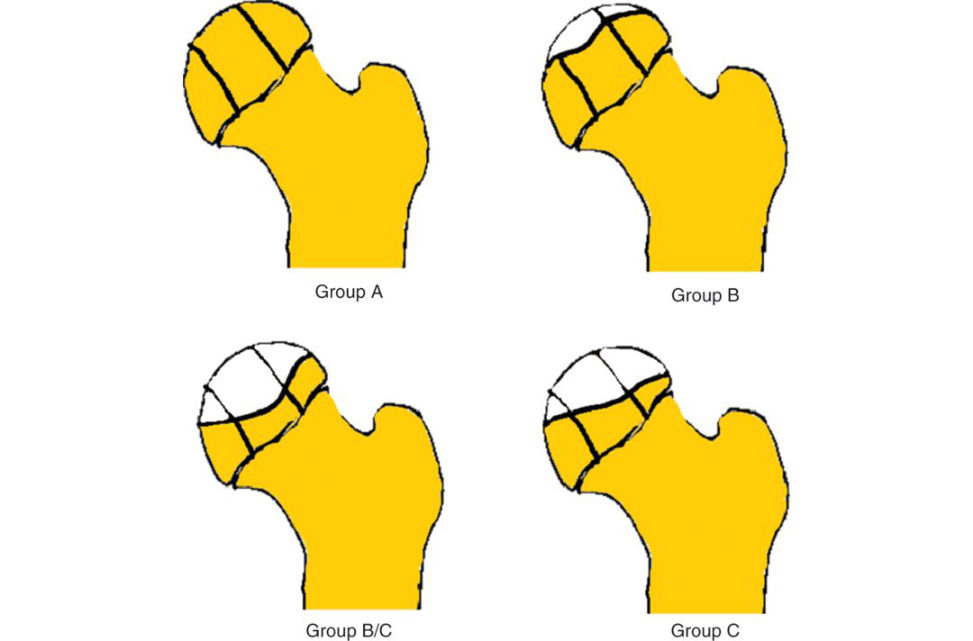
Figure 18.23 Herring classification.
Figure 18.24 Modified Stulberg classification.
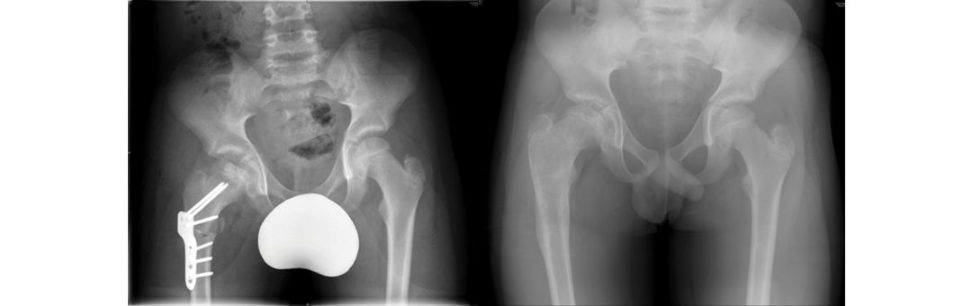
Figure 18.25 Varus osteotomy of patient with LCPD and a few years later.
Authors’ note: 5
LCPD is another A-list topic. The ability to discuss the findings and differential diagnosis is a must topass the exam.
Herring et al. [24] reported on the results of the Legg Perthes Study Group. Thirty-nine surgeons from 28 centres took part in a prospective study.
12 years of age at the onset of the disease, and none had had prior treatment.
The study showed that age, lateral pillar grading and treatment methods were significantly related to outcome.
In group B hips with an age at onset of more than 8 years, 73% of the operated hips had a
Stulberg I or II result compared with 44% of the non-operated hips (P = 0.02).
The group C hips were not shown to benefit from surgical or non-surgical treatments.
Twenty-eight hospitals in Norway were instructed to report all new cases of LCPD over a period of 5 years.
A total number of 368 with unilateral disease were included in the study. For patients over
6 years of age at diagnosis with more than 50% necrosis of the femoral head (152 patients the surgeons.
(55 patients the Scotish Rite abduction orthosis (26) and proximal femoral varus osteotomy (71).
In children over 6 years at diagnosis with more than 50% of femoral head necrosis, proximal femoral varus osteotomy gave a significantly better outcome than orthosis or physiotherapy. There was no difference in outcome after any of the treatments in children under
6 years.
It is worth knowing more details about Stulberg classification and its modification.
A modified version of the Stulberg classification is becoming more popular.
have an ovoid femoral head and group C (Stulberg IV and V) have a flat femoral head.
valgus osteotomy in hinged abduction [29]; and trochanteric growth arrestor advancement when there is overgrowth.
Soft -tissue release and articulated hip distractor intreating late-onset LCPD (even severe ones) have shown promising results [30,31]. Segev and colleagues studied 16 children with late-onset and type CL CPD.
Table 18.4 Stulberg grading.
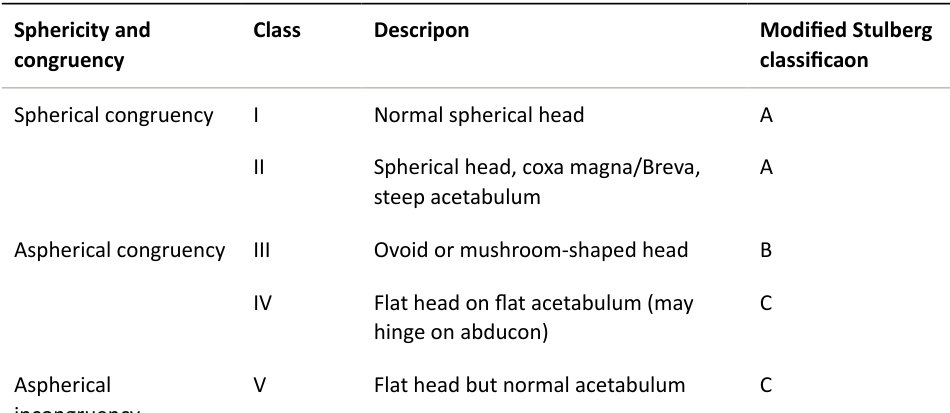
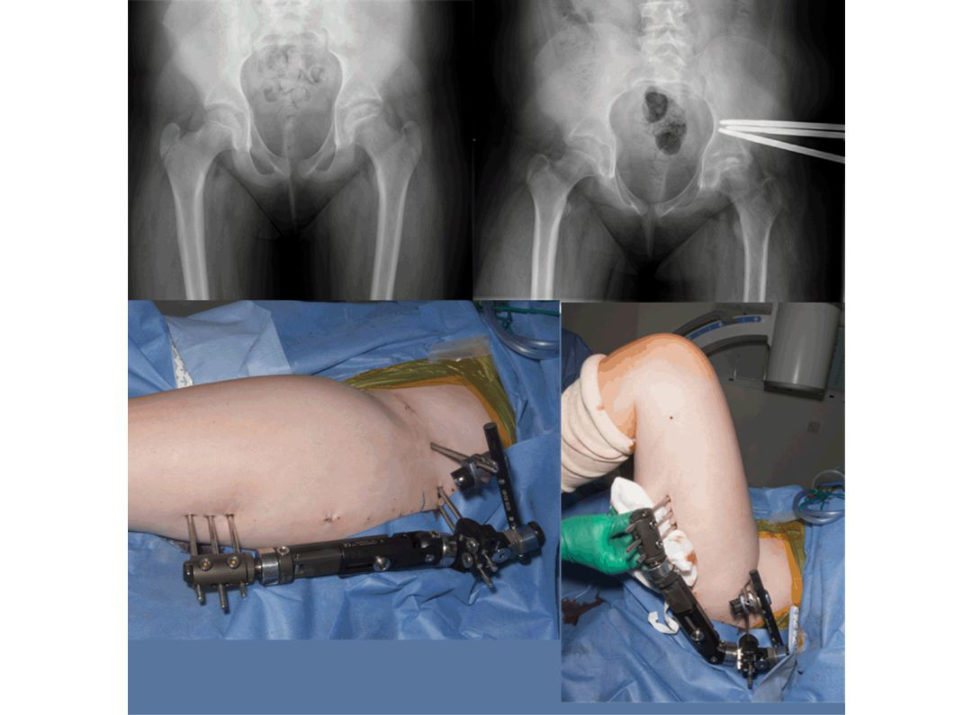
Figure 18.26 Articulated hip distractor in LCPD.
Candidate 4#
This is a clinical photograph of a 2-year, 8-months-old girl who was brought to you by her parents because they are concerned about the bent legs that she has (Figure 18.27). What are your thoughts?
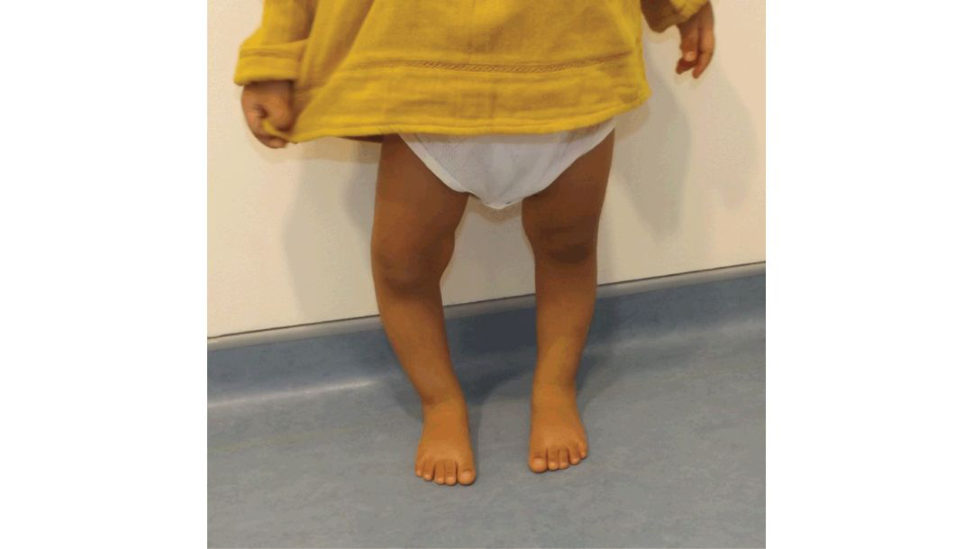
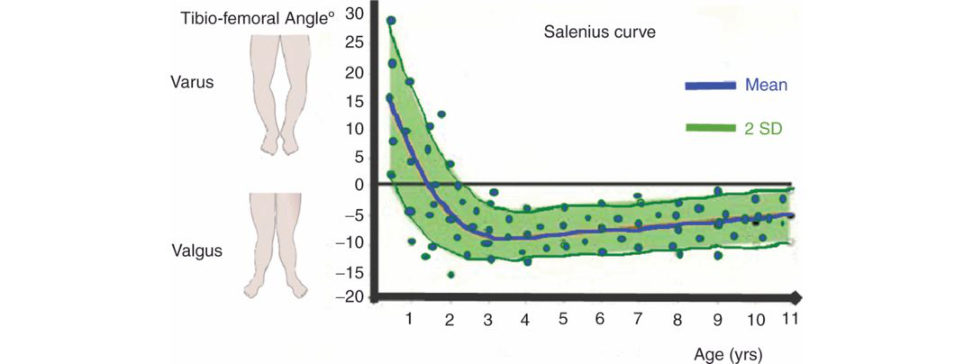
This is a clinical photograph of a standing child. I anticipate a child of this age has almost straight knees (or slight valgus) as depicted by the Salenius curve.
Tell me more about the Salenius curve.
Newborn babies were born with an average knee varus of 10–15°. As children started standing and walking, the knee became straight at around 18 months of age. This was followed by a progression into valgus of an average of 10° around the age of 4. Thereafter, knee valgus gradually reduced to the adult valgus of about 6° over the next several years (Figure 18.28).
How would you approach this patient?
I want to know when they noticed the deformity, is it geting worse or better, are there any symptoms, did they have any treatment? I want to know whether there is any history of trauma or previous infection ( growth arrest). Any family history of similar conditions, joint diseases, congenital or genetic disorders. I would perform a general examination looking for any signs to explain the deformity. I will look for any obvious abnormalities, f eel for swellings, tenderness or abnormal sounds (clicking, clunking or crepitus), I will check joint movements (active and passive) then I will do relevant special tests. A positive cover-up test has a high sensitivity; a negative cover-up test has a high specificity and negative predictive value [32].
The below clinical photograph (Figure 18.29) shows the cover-up test. What do you think?
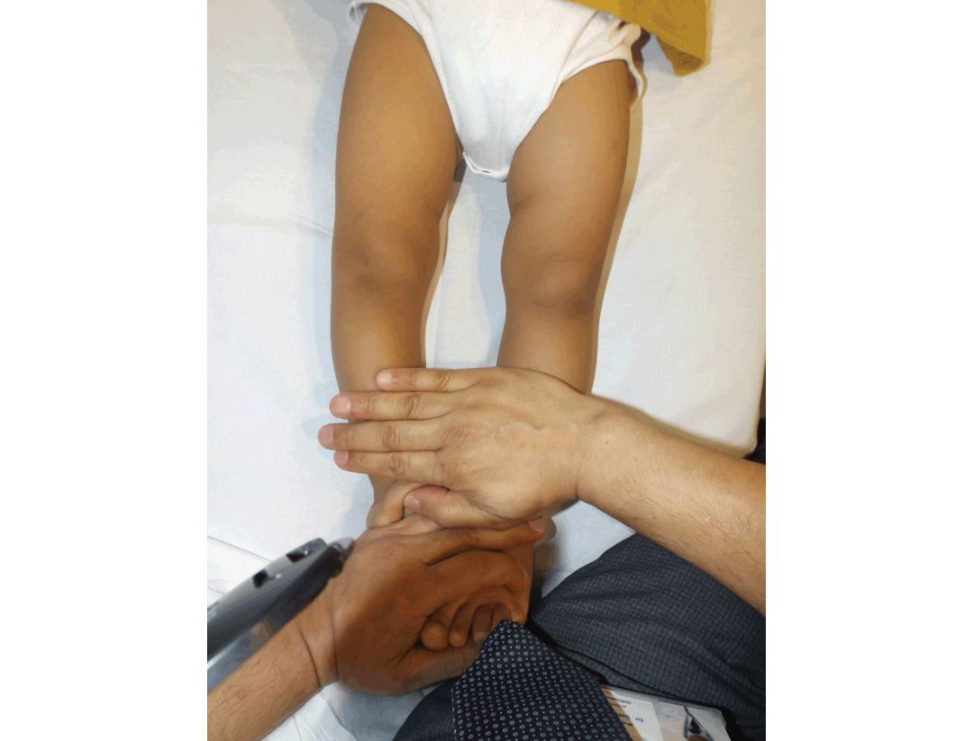
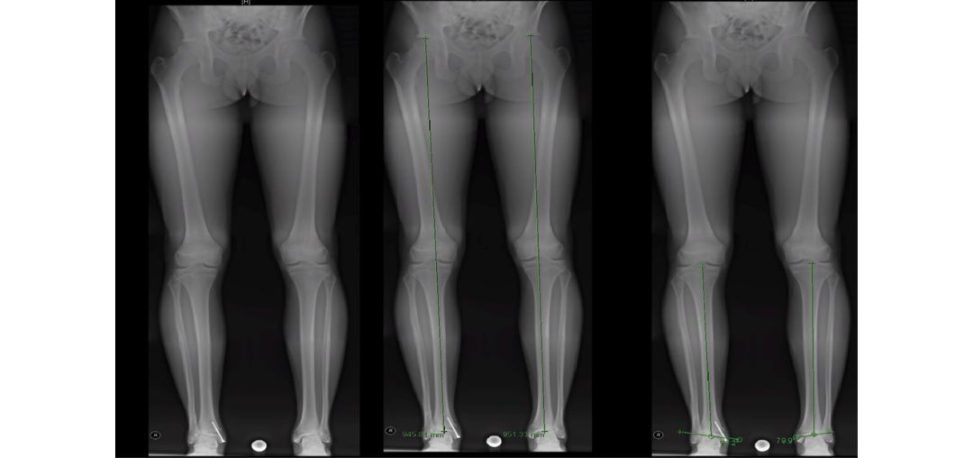
I think the child has a positive cover-up teston the right and neutral on the left and I would request a longlegs alignment view.
This is the X-ray that you have requested (Figure 18.30). Tell me what you can see.
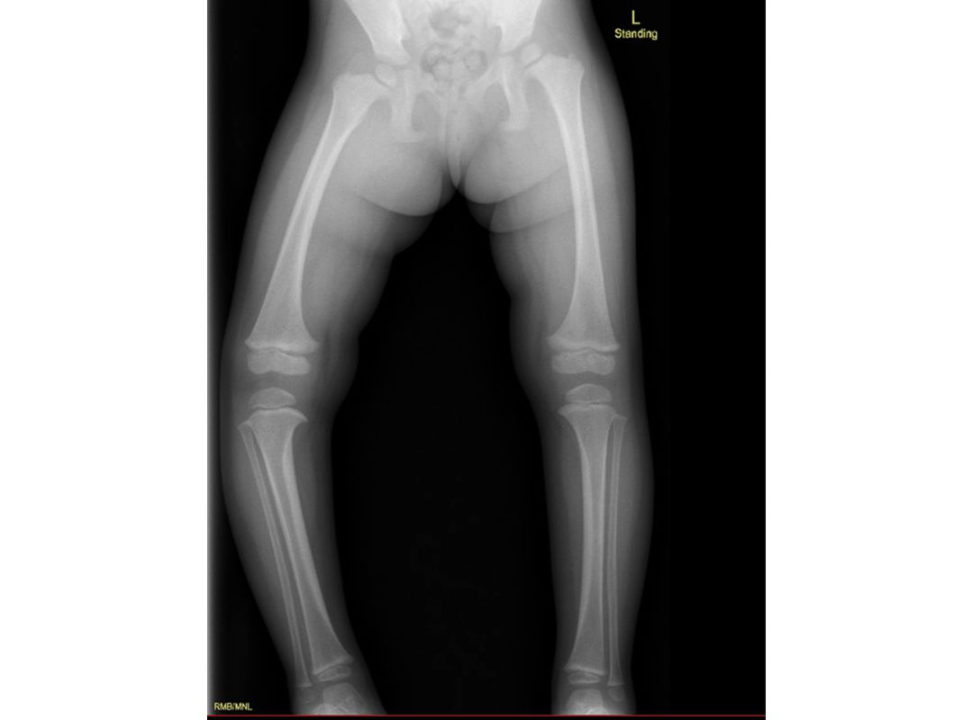
The X-ray shows most of the lower limbs. I also noted the X-rays are not fully labelled (names, dates, time, etc.) so I have to bear this in my mind when I make my decision. There are features that are suggestive of Blount’s disease (stage I) with a varus deformity of the knee and medial beaking of the metaphysis.
OK; go ahead. Show us what angles you measure and how.
I usually measure the tibiofemoral angle (TFA), mechanical axis deviation (MAD), metaphyseal–diaphyseal angle of Levine and Drennan (MDA)[33], epiphyseal–metaphyseal angle (EMA),
Figure 18.27 A child with bent legs.
Figure 18.28 Salenius curve of tibiofemoral angle.
Figure 18.29 Cover-up test (positive on the right and neutral on the left – both are indication for X-ray).
Figure 18.30 A longlegs alignment view in a child.
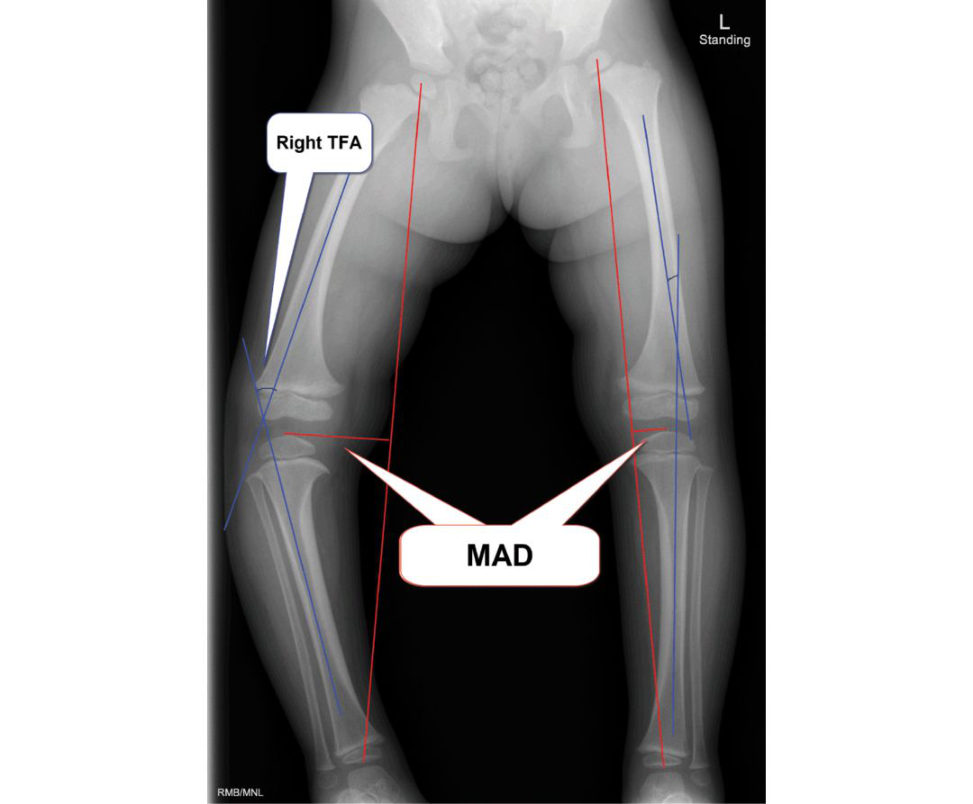
Figure 18.31 Tibiofemoral angle and mechanical axis deviation. The TF A is the angle the femoral and tibial mid-diaph yseal. MAD is the distance between the mechanical axis and the centre of the knee.
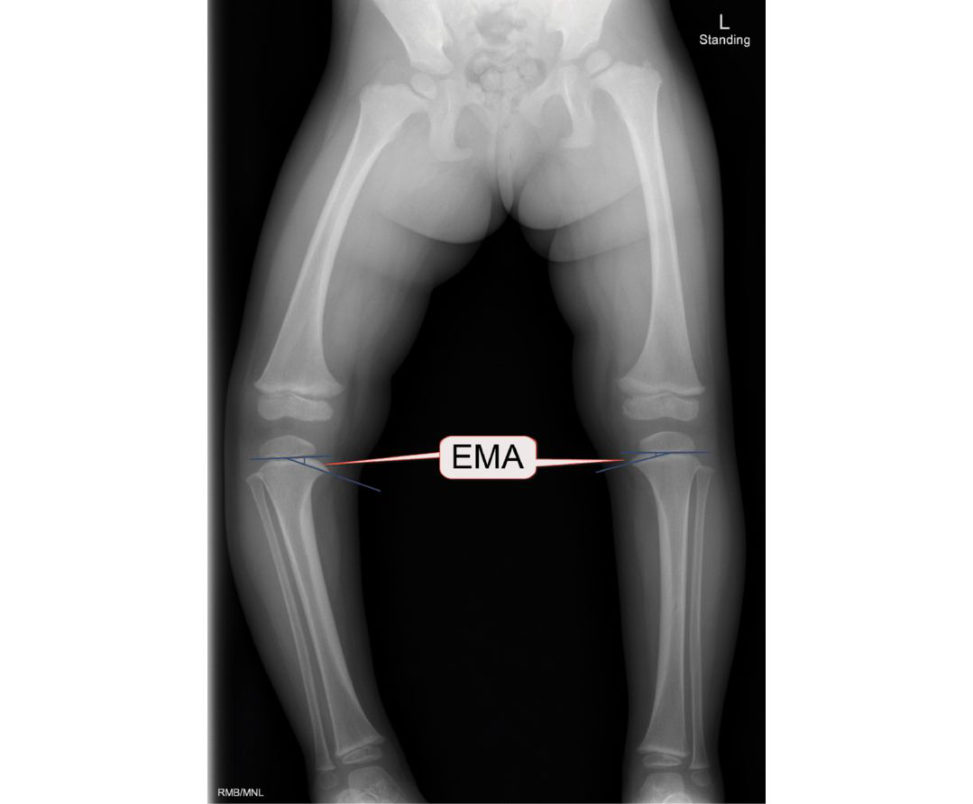
Figure 18.32 Epiphyseal–metaphyseal angle (EMA). The EM Ais the angle formed by the epiphyseal line (a line through the proximal tibial physis parallel to the base of the epiphyseal ossification centre) and a line connecting the midpoint of the base of the epiphyseal ossification centre with the most distal point on the medial beak of the proximal tibial physis.
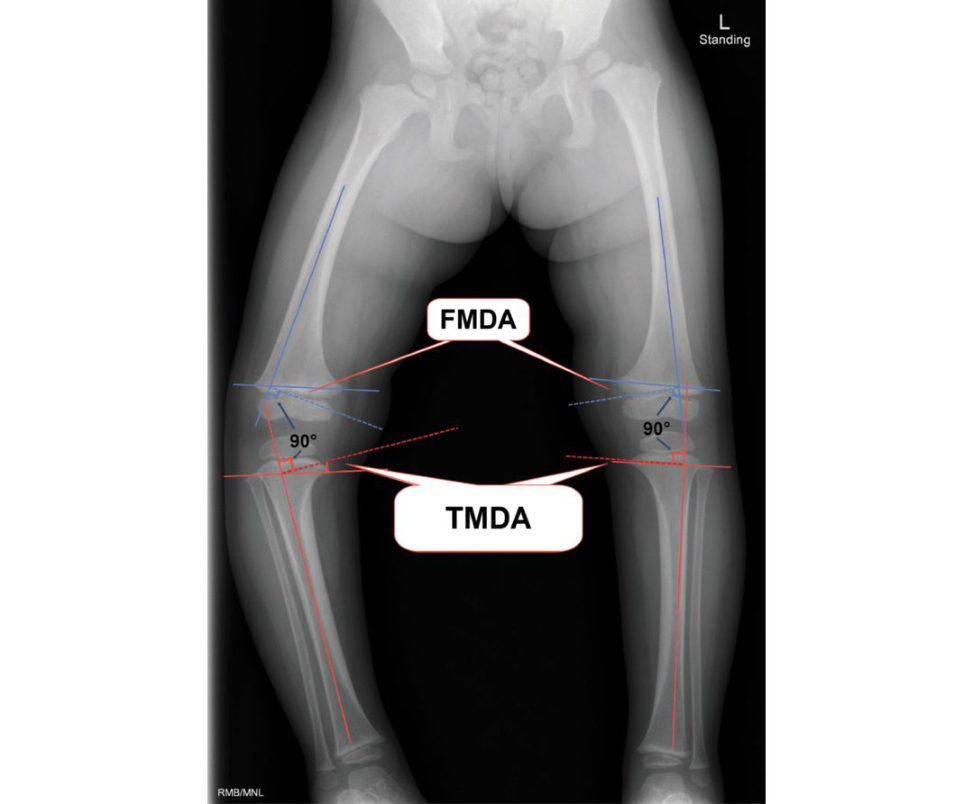
Figure 18.33 Metaphyseal–diaphyseal angles. Th eMDA is the angle formed by a line connecting the most distal point on the medial and lateral beaks of the metaphysis (distal femur in FMDA and proximal tibia in the TMD A) and a line perpendicular to the anatomic axis (or lateral cortex) of the bone. The femoral-tibial ratio (FTR) is defined as the FMDA divided by the TMDA.
Table 18.5 Angle measurements around the knee.
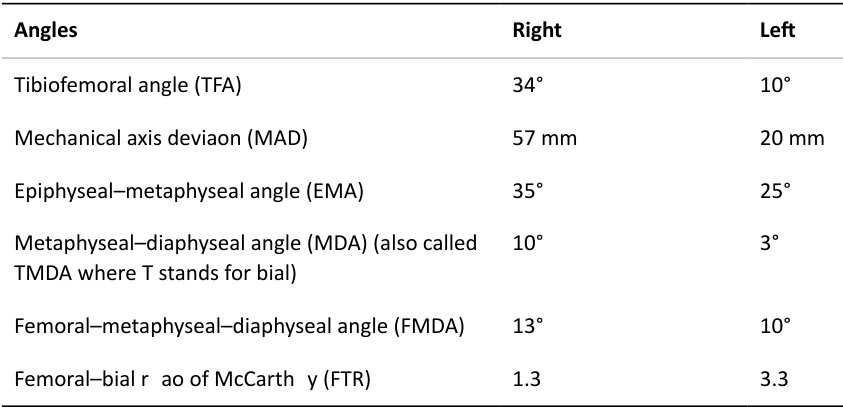
The TFAs show bilateral varus with the right side worse. This is also reflected by the MAD, which is more than the normal value (0 ± 3 mm from the centre of the knee).
MAD is valuable to monitor progression of the disease.
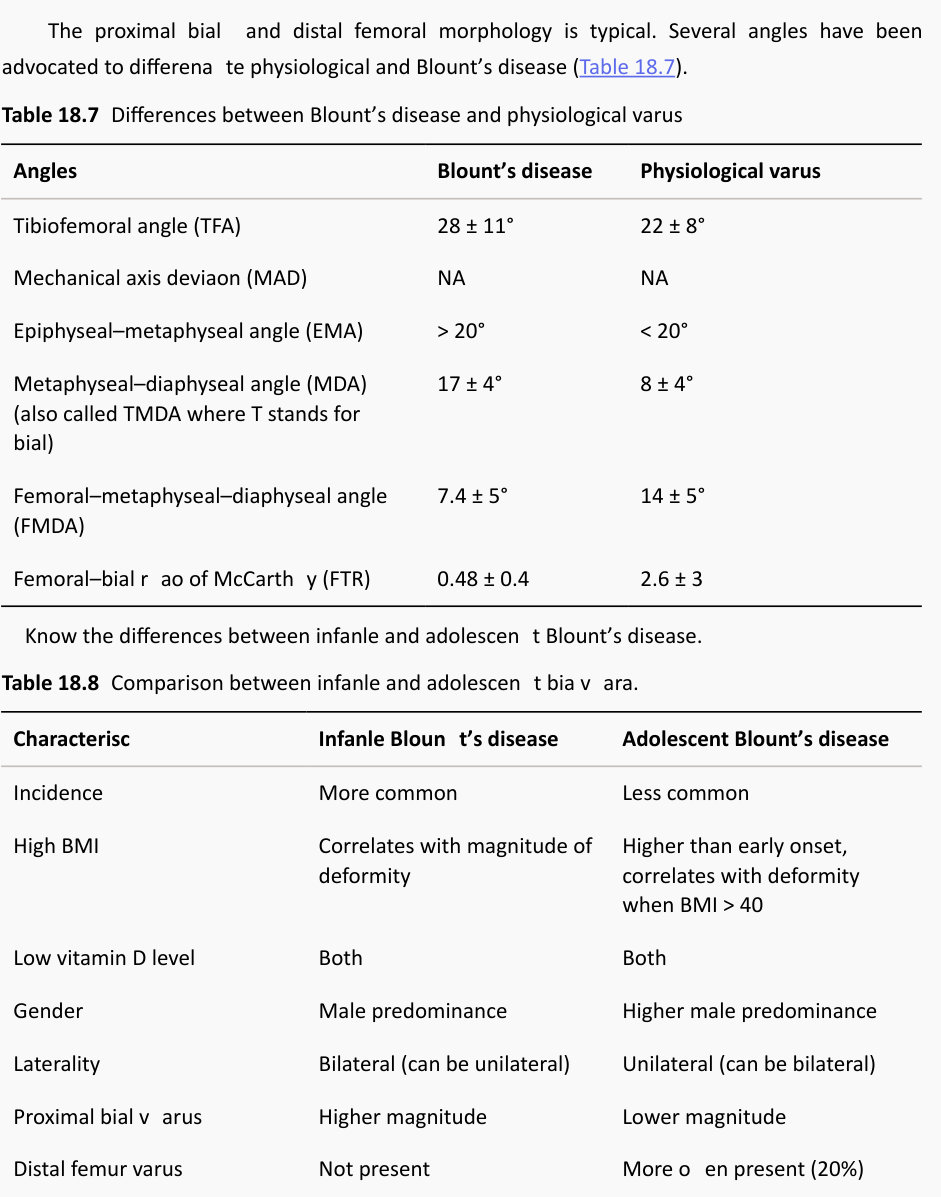
The other angles help to differentiate between physiological and pathological genu varu mAs with any test, they are not 100% sensitive or specific and clinical judgement is often required when the values fall in the grey zone.
So, what is Blount’s disease?
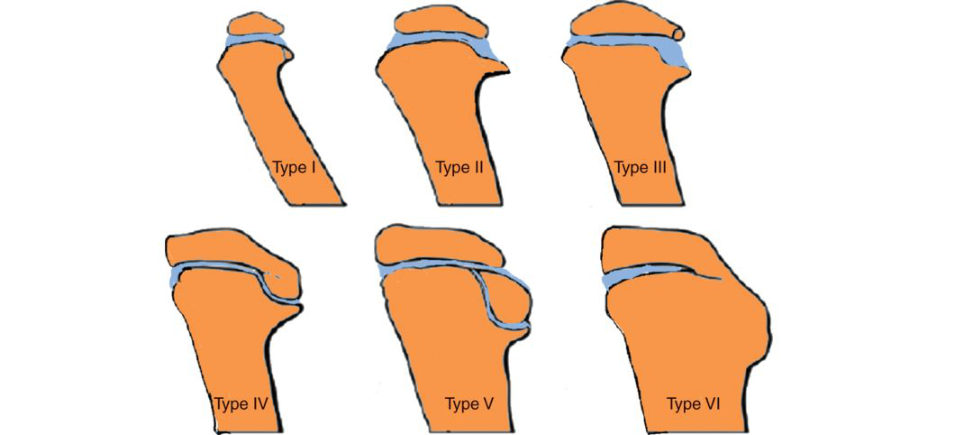
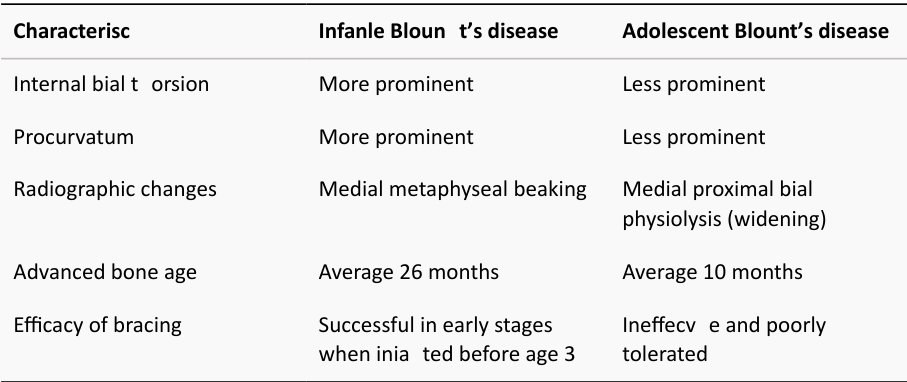
There are two recognized types: 1. 2. Adolescent (> 10 years). In the infantile tibia v ara, patients generally start to walk early (9–10 months; it is more prevalent in females, blacks and those with marked obesity. It is bilateral in approximately 80% of cases and associated with a prominent metaphyseal beak, internal tibial torsion and LLD. These patients are normally similar to the SUFE type of patient with more incidences in overweight Afro-Caribbean males and unilateral involvement in 80% of cases. Langenskiold recognized six radiological stages of the disease (Figure 18.34).
So, what do you advise parents?
My advice is that bowed legs are common (in fact, the norm) before the age of 2 years. My options are either start treatment now or observe it for another 4–6 months. If things improve, observation will continue; otherwise, I will treat with a brace.
Do you think the brace will help?
There is evidence that braces can improve deformity in younger thanage 3 or prior to Langenskiold stage II. An elastic Bloun t brace provides valgus force in conjunction with a medial upright, with drop locks to increase corrective force during weight-bearing [36]. Bracing failure was more likely with ligamentous instability, bodyweight exceeding the 90th percentile, or late initiation [ 37]. Another study demonstrated 70% success in Langenskiold stage II disease, although this was mainly in unilateral disease.
Figure 18.34 Langenskiold classification of Bloun t’s disease.
Table 18.6 Langenskiold classification of Bloun t’s disease.

Stages Descriptions Treatment
Stage 6 Medial physeal closure
Authors’ note: 6
The former is very common in clinical practice (and exams) and the latter, although rare, is closely related to the genu varu mand it has become the favourite linked topic to genu varum.
Please master these topics. They are easy, and you can score high marks!
Candidate 5#
The clinical photograph (Figure 18.35) is for a newborn child who was referred to you with a left foot deformity; the referrer thinks the baby may have a congenital vertical talus (CVT)? What do you think?
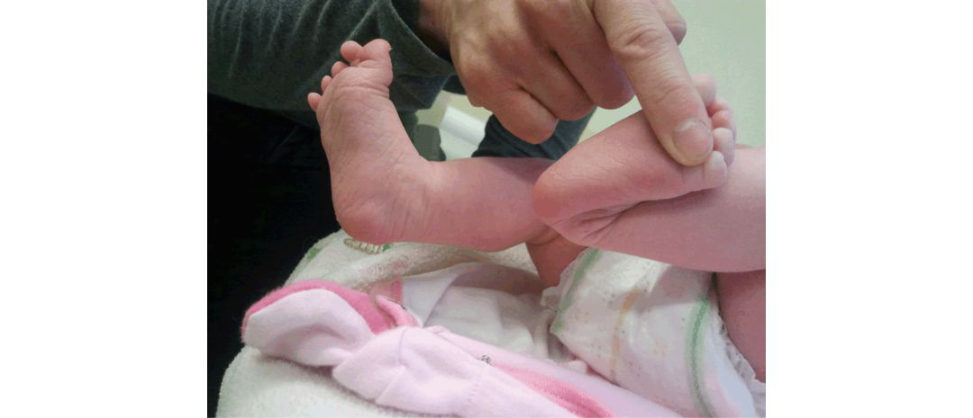
There is an excessive dorsiflexion of the foot to the extent that the dorsum of the foot touches the frontal aspect of the leg. Although it may look similar to CVT for the inexperienced, the differences are clear: in CVT the hindfoot is a rigid equinus/valgus (not a flexible calcaneovalgus) (see Figure 18.36).
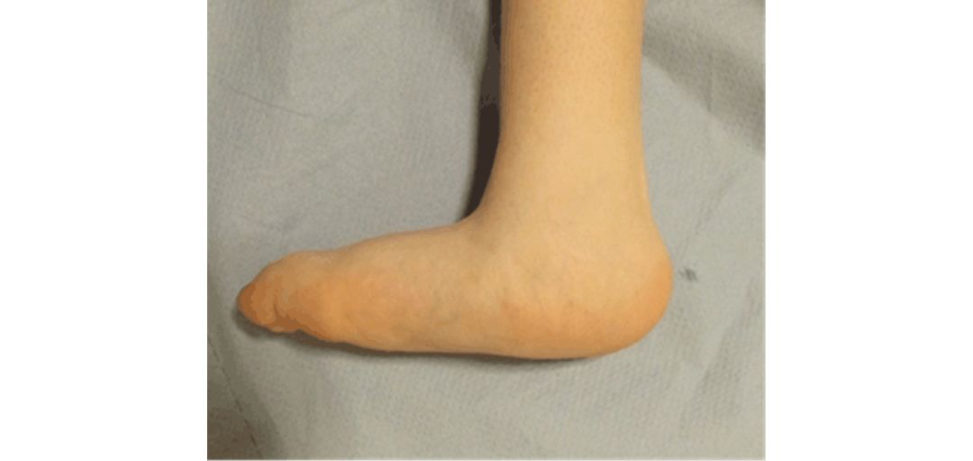
How would you manage it?
However, radiographs can be useful to exclude CVT and posteromedial bowing, and US to exclude DDH. I usually reassure parents and advise them on simple stretching manoeuvres and it usually resolves over 6 months. In resistant cases serial casting may be used to expedite correction (particularly if the foot cannot be plantar flexed beyond neutral).
This is a radiograph of another child with the same condition ( Figure 18.37). Any comments?
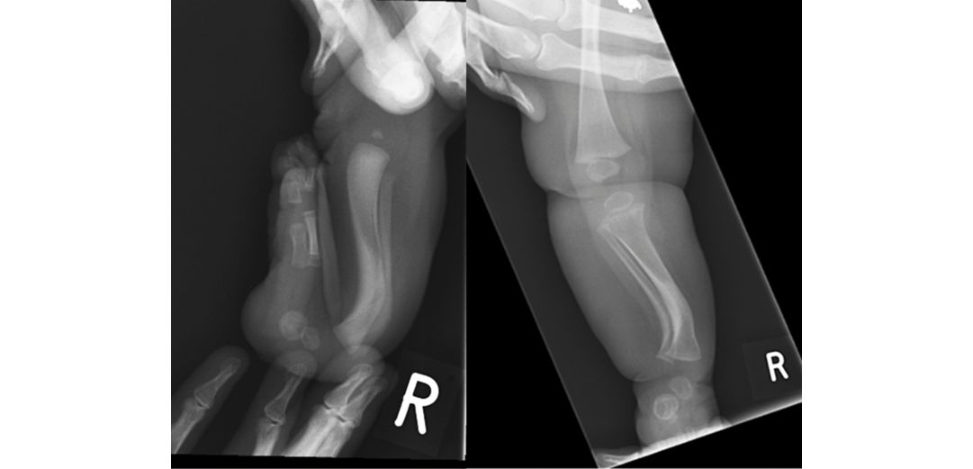
This clinical photograph shows a posteromedial bowing of the tibia (the apex of the deformity is pointing posterior and medial). It is often associated with congenital calcaneovalgus foot. In most cases the bowing resolves spontaneously over 3–5 years (Figure 18.38).
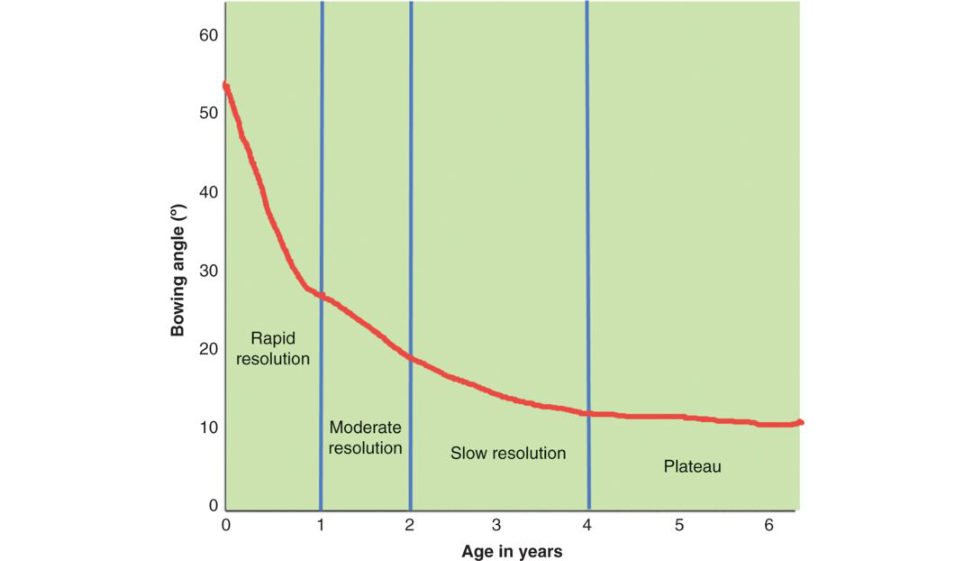
You followed-up this patient and these are his X-rays over the last 3 years (Figure 18.39– 18.41) (see also Table 18.9).
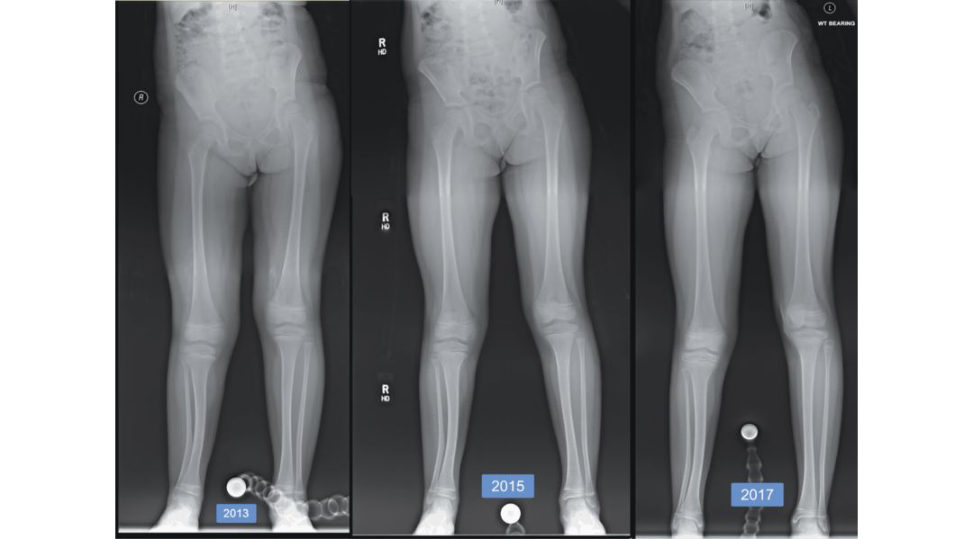
The X-rays show gradual improvement of the deformity (as expected), but there is still residual deformity and LL Das evident by the pelvic tilt.
Show me how you would do your measurement.
My measurements indicate that there is a LLD of 4 cm (mainly from tibia 3.4 cm) and a coronal angular deformity (valgus) of 15° at the junction between the distal and middle third of the tibia. I also need to check her skeletal age.
She was 8 years and 10 months when she had the X-ray in 2017, her height was 134 cm, she is fit and healthy. She and her parents will be guided by your advice.
OK, I need to estimate her height and the LL Dat maturity, then plan my management. So, her estimated height at maturity would be 166 cm, which is just above the 50th centile. The estimated full LLD would be 5.1 cm, whereas the tibia LLD would be 4.3 cm. There is an increase in the full LLD of 6 mm and tibial LLD of 5 mm e very 2 years from the table above or 3 and 2.5 mm every year. On average, girls finish growth at 14 years of age, so she has 5 years and 2 months of growth.
What will be your management plan?
As for the LLD, I want to achieve equal leg lengths at skeletal maturity without excessive risk, morbidity or height reduction. 2. Epiphysiodesis of the long side. Given the significant LL Dand the deformity of the distal tibia (15° of valgus), my preferred option will be lengthening of the short leg with gradual correction of the leg deformity using a circular frame.
What is your rationale for this? Why not correct and lengthen at the deformity site?
I could but the bone healing at the site of deformity in this condition is.
The radiograph below shows what has been done (Figure 18.44). Any criticism?
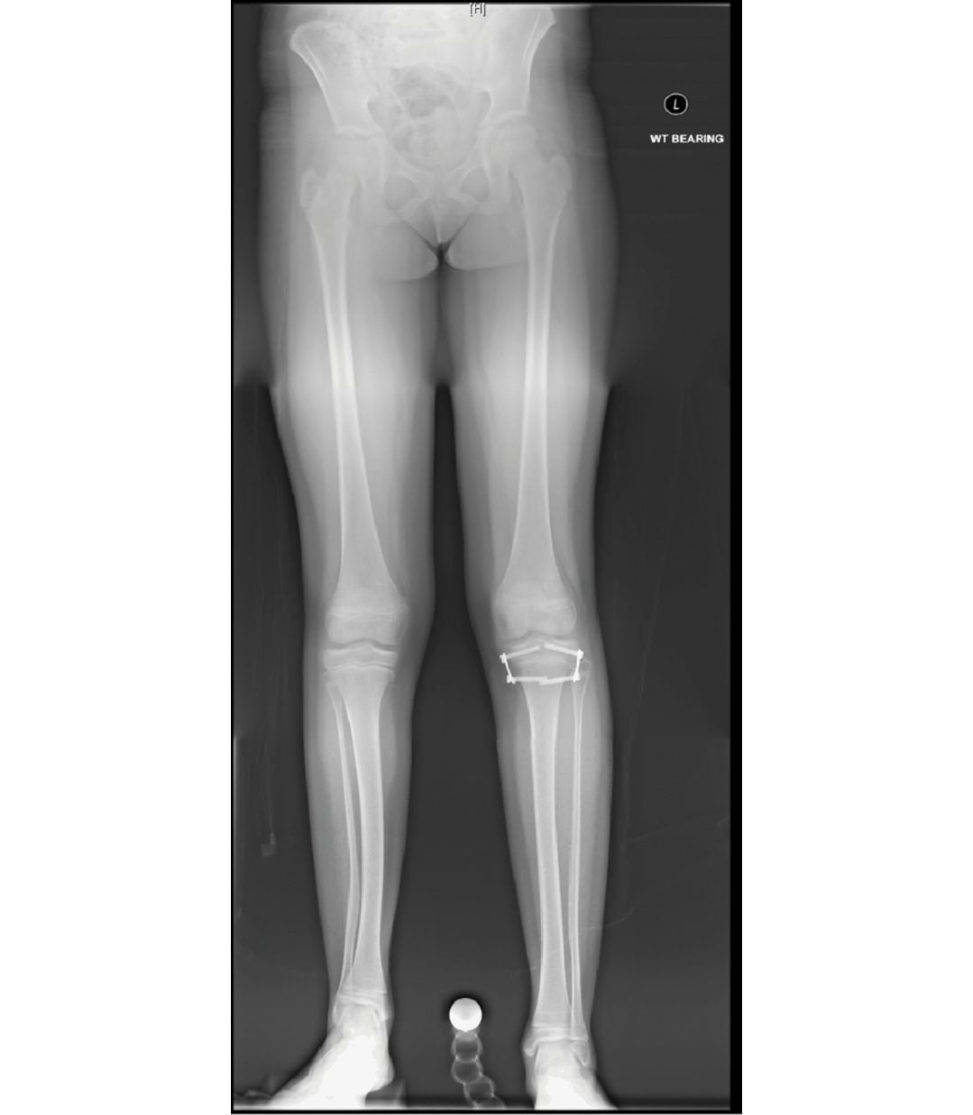
The surgeon chose to slow the growth of the left leg. It is a small operation, revisable and given the remaining few years of growth, it is potentially ablet o equalize the leg.
Figure 18.35 A newborn with left foot deformity.
Figure 18.36 Rocker boft om foot in congenital vertical talus.
Figure 18.37 Lower limb radiograph.
Figure 18.38 Resolution of posteromedial bowing.
Figure 18.39 Followup X-rays.
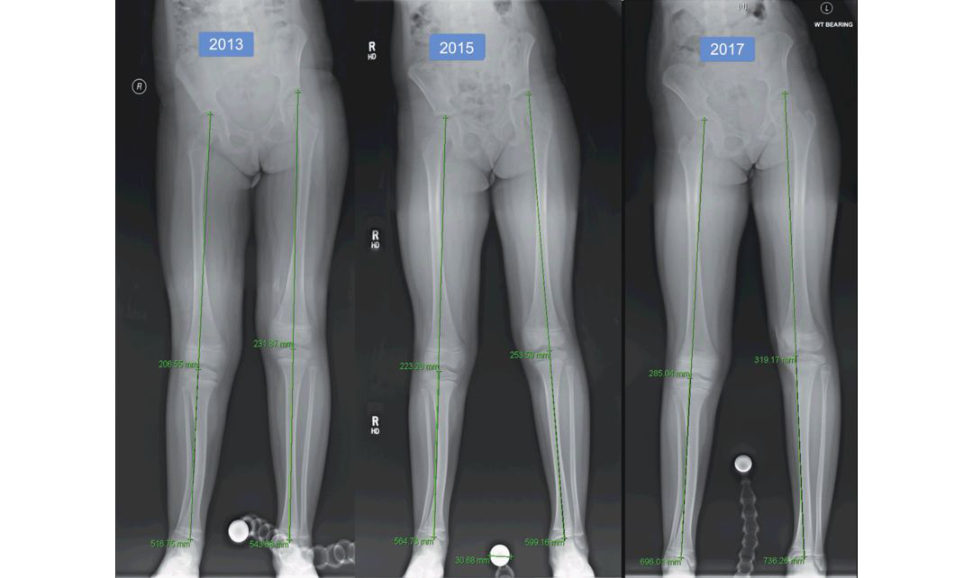
Figure 18.40 LLD following posteromedial bowing.
Table 18.9 Leg length discrepancy table.
Dates Segments Right Left Δ
2013 Total 51.7 54.4 2.7
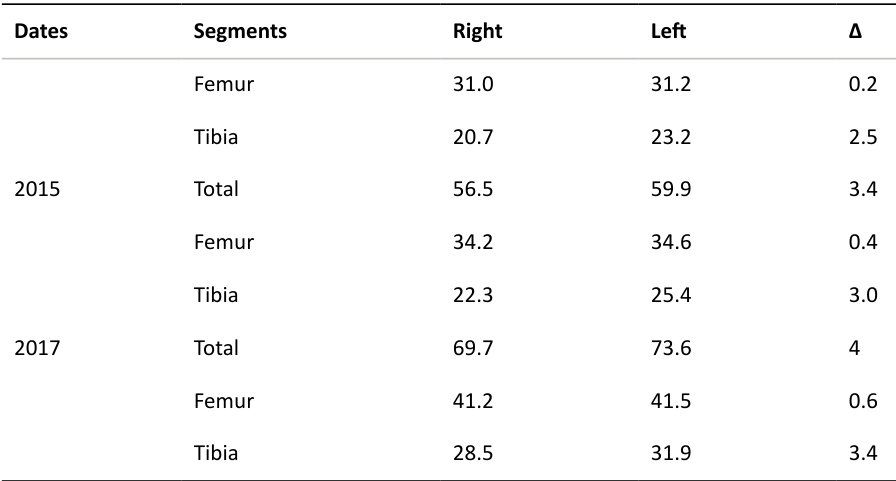
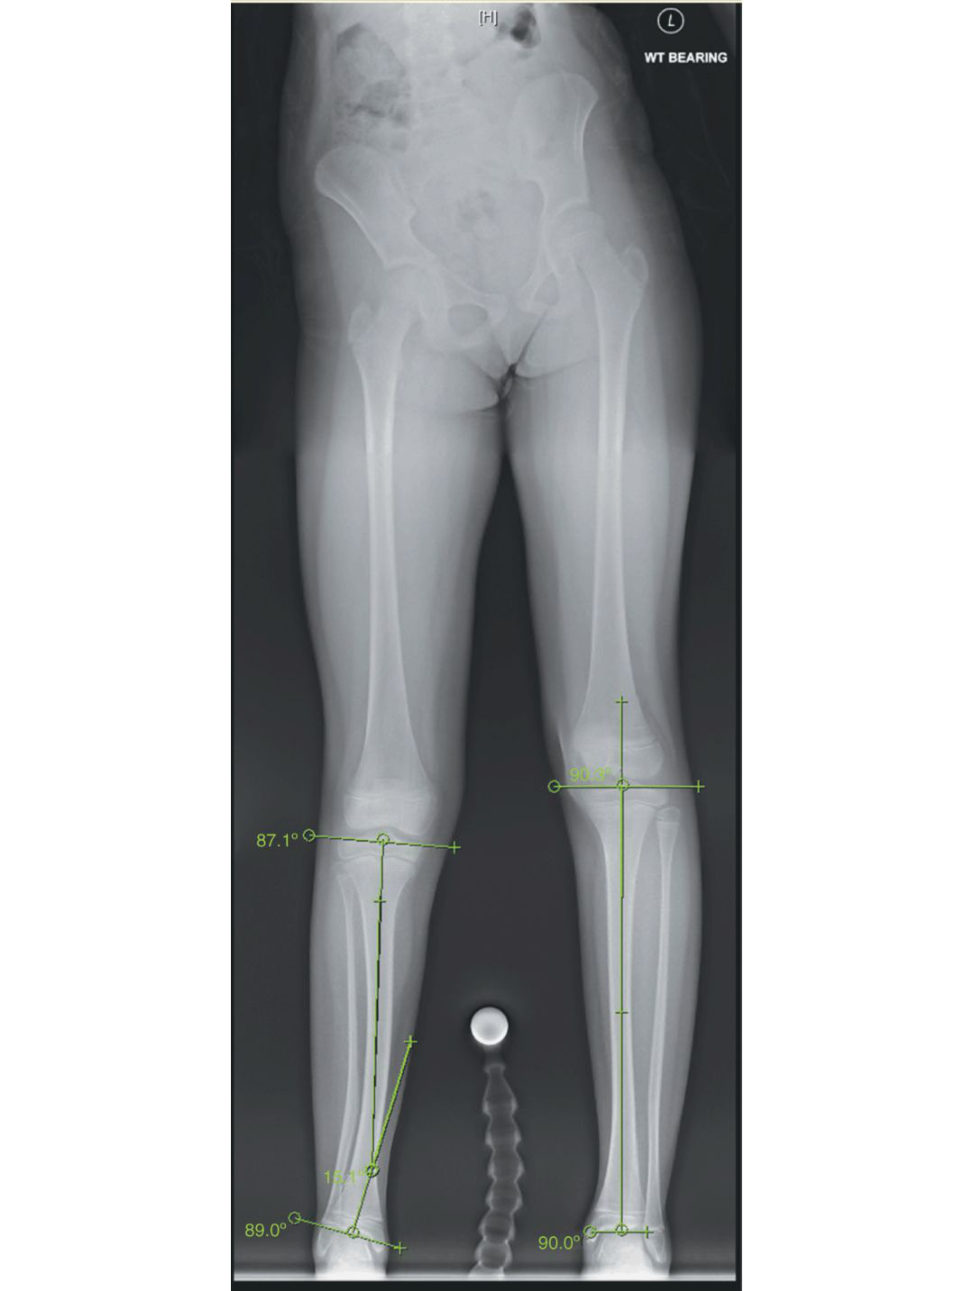
Figure 18.41 Tibial alignment measurements.
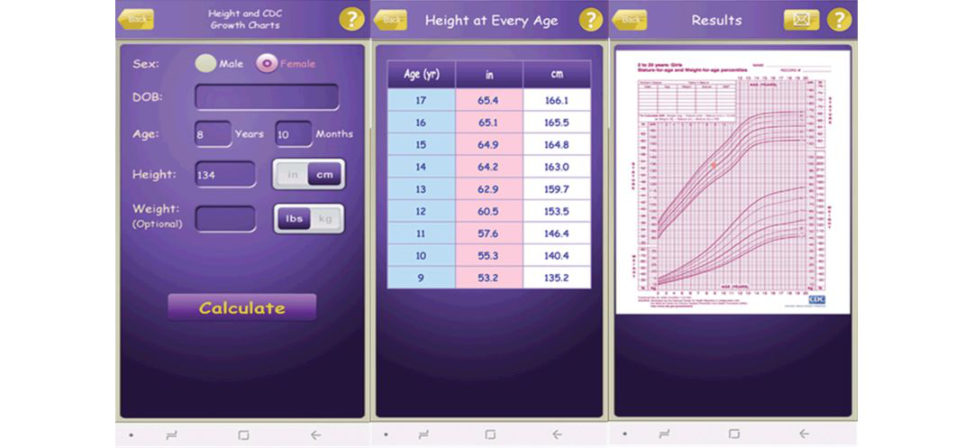
Figure 18.42 Estimation of height at maturity using the multiplier app.
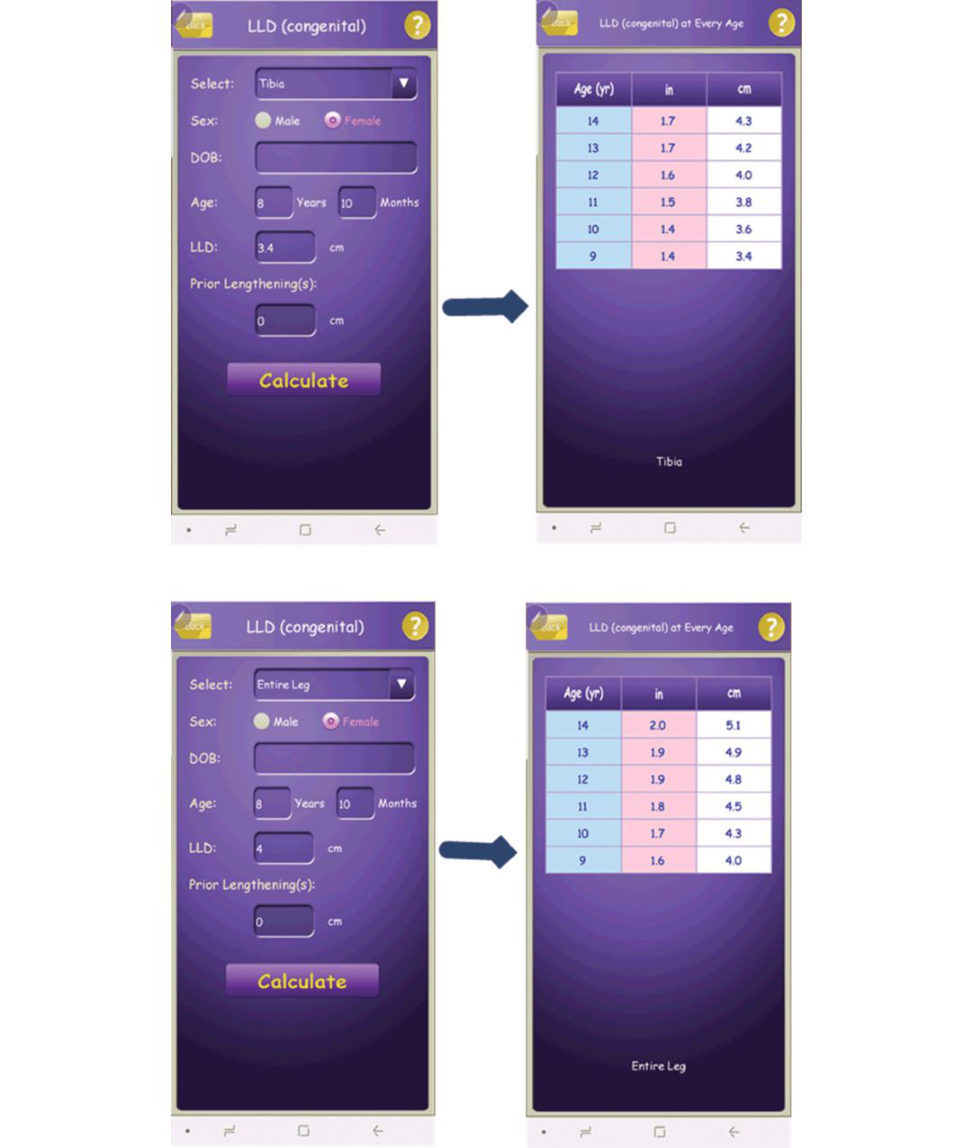
Figure 18.43 Estimation of LL Dat maturity using the multiplier method.
Authors’ note: 7
Limb reconstruction in general and lengthening in particular is an important topic not only in the paediatric section but in the adult section aswell. The viva started with a simple case of congenital calcaneovalgus foot, which all candidates must recognize and come with a sensible plan.
He was not derailed when he realized that the patient did not have what he had suggested.
He pointed out the pros and cons of what had been done and explained why he would have chosen a different plan.
Please be objective and sensitive when you criticize other people’s operation and do not be.
We recommend you familiarize yourself with the multiplier app You can download it from:
htip s://itunes.apple.com/us/app/multiplier/id460335161?m t=8
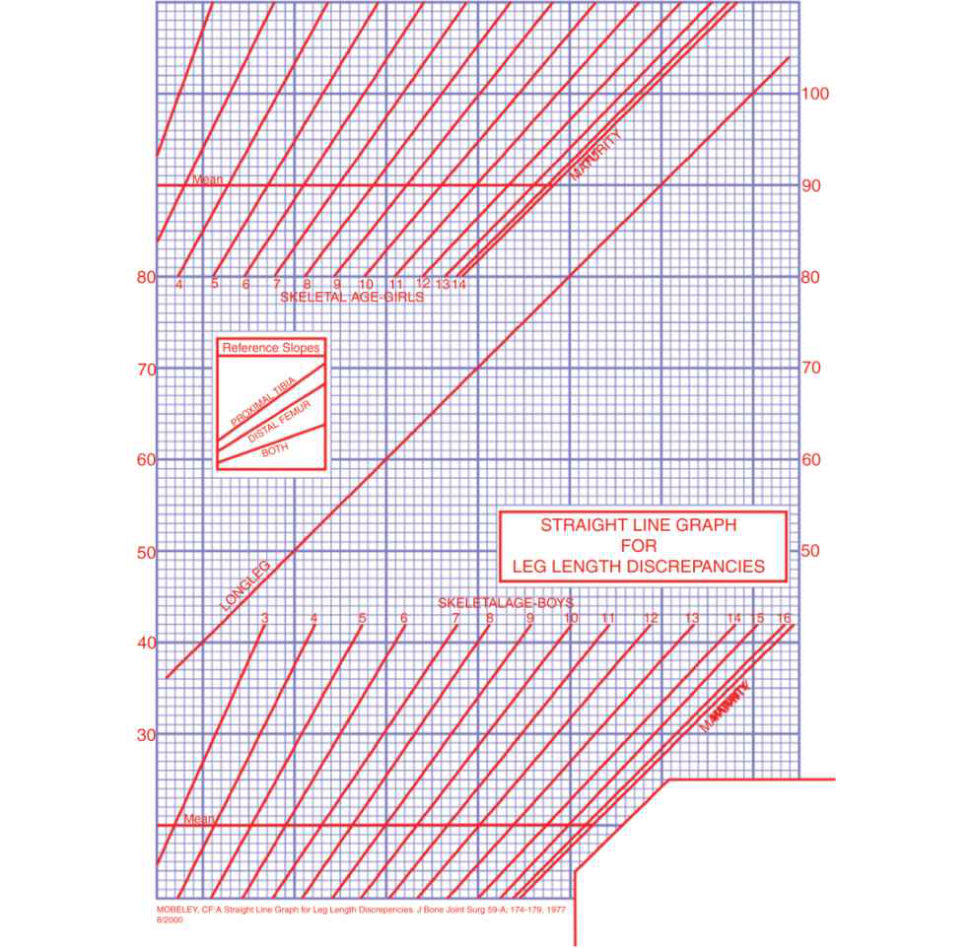
Try to practise using the Mosley chart method (Figure 18.45) to do the calculation for the above patient.
More information is available on the following website:
www.pedipod.com/Chapters/StepByStep.asp#
Figure 18.44 Proximal tibia epiph ysiodesis using eight plates.
Figure 18.45 Blank Mosley chart.
Candidate 6#
These are AP and lateral views of a 13-year-old child (Figure 18.46) who was brought in after a football injury. How would you manage such an injury?
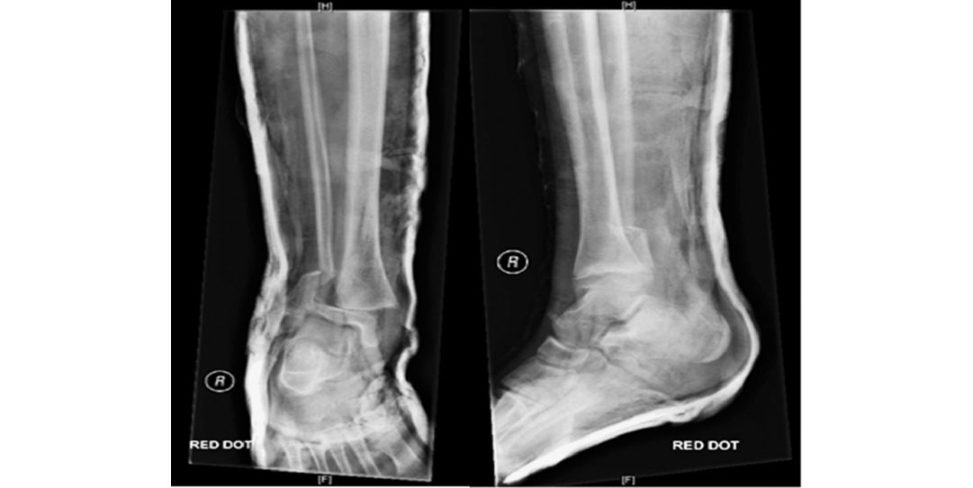
Figure 18.46 Ankle injury.
It is very tempting to start with the ankle fracture or the deformed limb and it is important to resist this temptation.
You did your primary and secondary survey, and this is the only injury that this child has.
The X-ray indicates the skin on the medial side of the ankle might be overstretched and there may be impending skin breakdown that requires immediate fracture reduction. I assess the movement of the joints that are not involved to ensure that there are no unexpected problems. I would not move the ankle joint at this stage as it is expected to be painful.
Indeed, you have found the skin over the medial malleolus is overstretched, white and about to tear.
Then we need to reduce the fracture immediately to prevent this fracture from becoming an open fracture, which has more comorbidity.
Theatre is available, but the patient had food an hour ago.
I think this a limb-threatening condition and justifies a rapid sequence induction anaesthesia (to prevent aspiration). These physeal injuries are usually stable after reduction and the y need closed reduction and a well-moulded cast application.
This is what has been done (Figure 18.47), any thoughts?
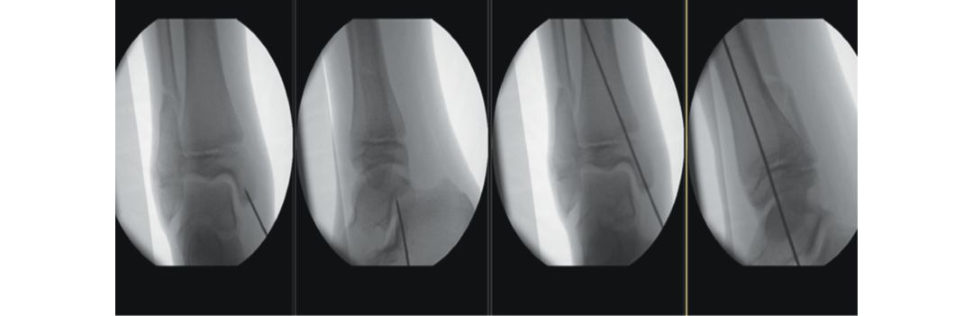
Figure 18.47 Ankle facture fixation.
The surgeon reduced the fracture nicely and stabilized with a single K-wire crossing the physis. The concern is that the K-wire may cause physeal damage.
What would you do next?
If everything is satisfactory, I will plan to remove the K-wire in 6 weeks’ time. As the risk of growth plate disturbance is high in these fractures, I would like to follow this patient until I am sure that there is no growth arrest.
This is the ankle X-ray after 8 months (Figure 18.48).
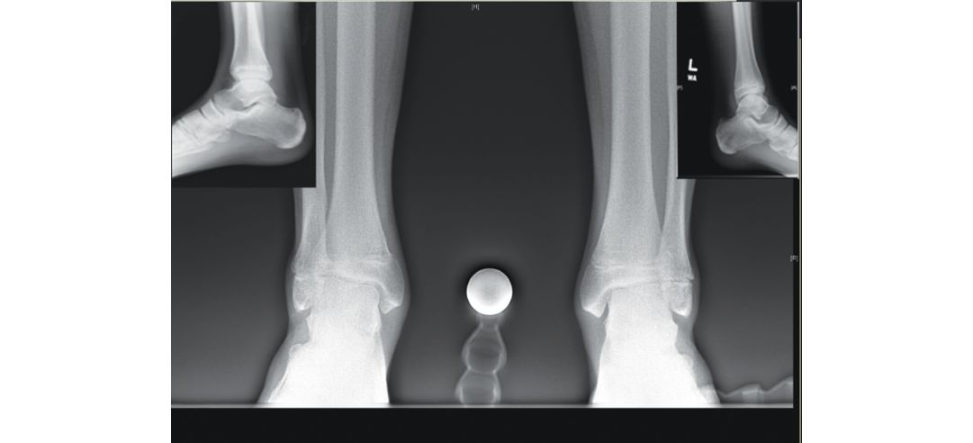
Figure 18.48 Eight months postoperative.
I would like to get more imaging (CT scan or MRI scan).
There was no CT scan or MRI scan but there are longlegs alignment views and some measurements (Figure 18.49).
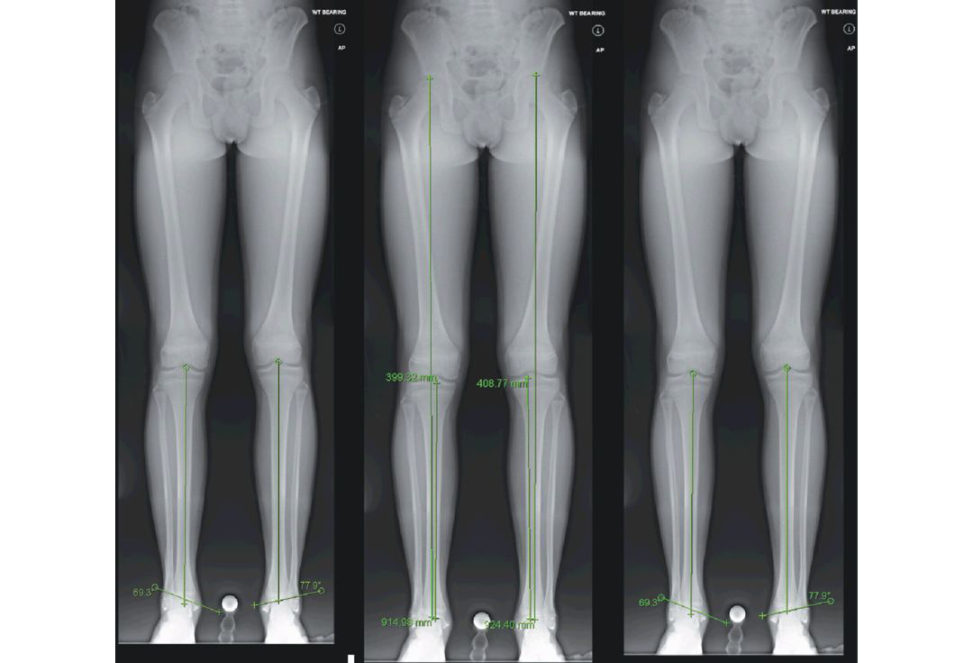
The longleg alignment views confirm my initial suspicions that there is a growth arrest which led to a shortening of almost 1 cm and distal tibial valgus deformity of at least 10°.
Figure 18.49 Longleg views measurements.
15 years old.
So, he still has two years or more to go. A hand X-ray to establish his skeletal age will be valuable.
Would you consider correcting the distal tibial deformity?
If he is asymptomatic and the reis a good subtalar join movement I probably would not; however,
The patient underwent left distal tibia and fibular epiph ysiodesis and right distal tibial medial hemiepiphysiodesis. These are his pictures a year after (Figure 18.50), any thoughts?
I thought about it; however, I was not sure whether the right distal tibia physis is still reliable to correct deformity.
Figure 18.50 Postoperative left distal tibia and fibula hemiepiph ysiodesis and right distal tibia medial hemiepiphysiodesis.
Authors’ note: 8
Physeal injuries are common in children. They are relatively stable after reduction; however, this is not always true. The above fracture was unstable and using a smooth K-wire to stabilize was the right thing to do. K-wire rarely causes growth arrest (take the supracondylar fracture as an example).
These clinical photographs (Figure 18.51) are for an 18-month-old child who is about to have surgery. Could you tell me what the pictures show and what the surgery involves?
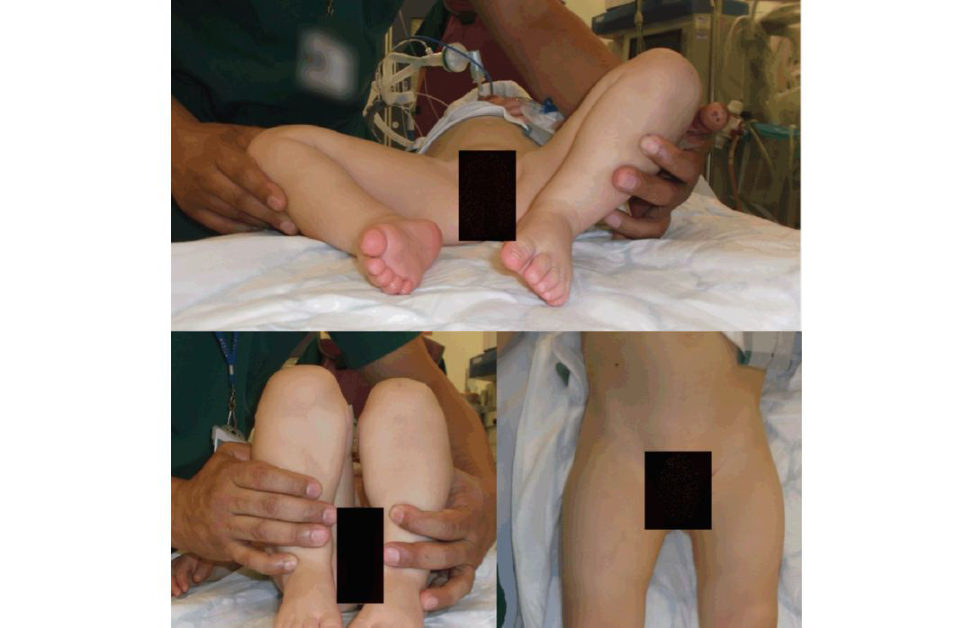
Figure 18.51 Clinical photographs of 18-month-old child.
All are signs of hip dislocation. In an 18-month-old child, I anticipate the surgery will be hip adductors release, open reduction, pelvic osteotomy (with or without femoral osteotomy) and application of hip spic a.
This is a plain pelvis X-ray of the above baby (Figure 18.52). What can you say about the X- ray?
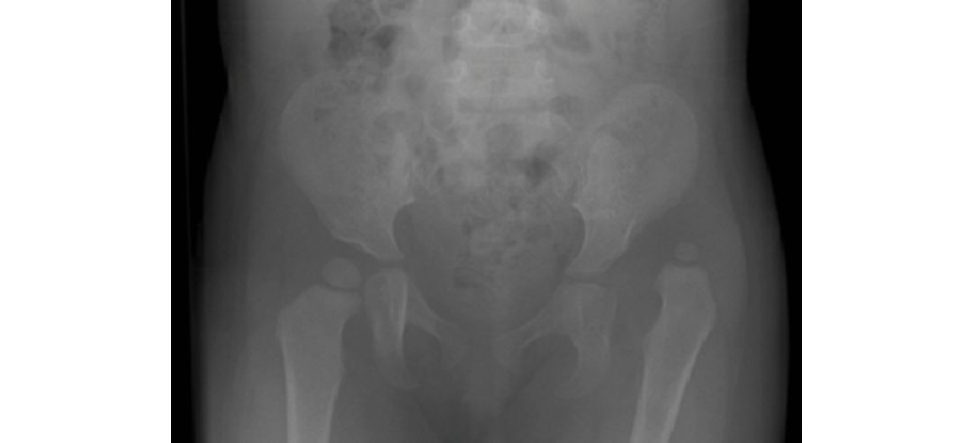
Figure 18.52 Plain pelvic X-ray.
The radiograph confirms my initial thought that the baby has a left hip dislocation. The femoral nucleus is smaller on the left side and has created a false acetabulum. There is a break in the inferior and lateral Shent onlines (Figure 18.53).
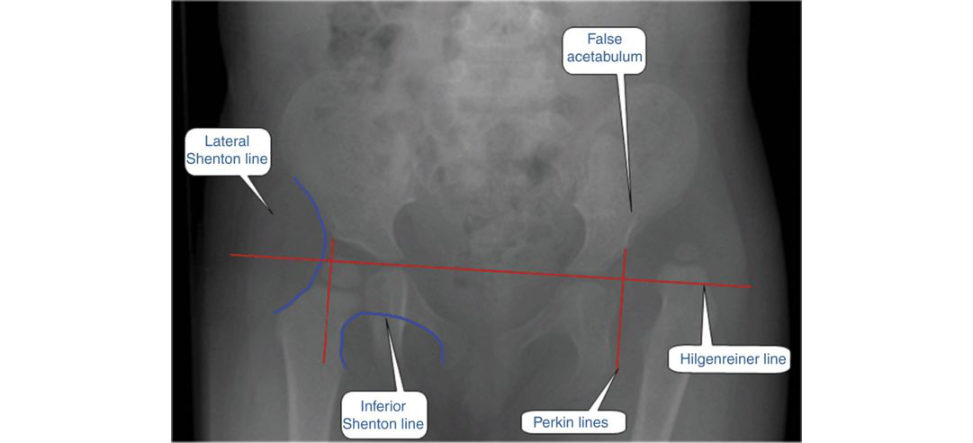
Figure 18.53 Plain pelvis X-ray of the hip of an 18-month-old child.
What would you do if you were the surgeon?
He is 19 months old. However, there is always apa tien t who does not follow the rule. So, I would perform EUA and trial of closed reduction.
Tell me what you mean by zone of safety?
The average movement of the hip in a hip spica is 15°; so, it is important to keep the hip away from the line of dislocation by about 20° to reduce the risk of dislocation inside the spica. 2. The risk of AVN increases with the hip put at the maximum range of motion so it is safe to be 20° inside the maximum range of motion. So, the safety zone is the range of motion (c one of motion) within 15 –20° of the maximum range of motion and dislocation range.
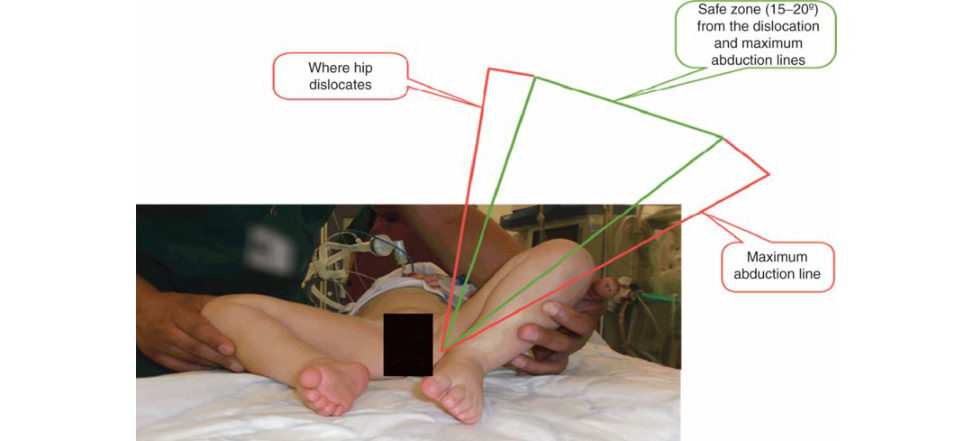
Figure 18.54 Coronal safe zone.
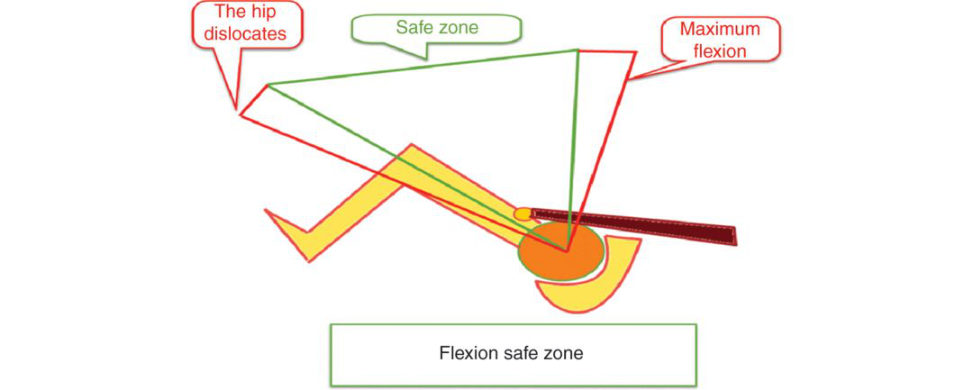
Figure 18.55 Sagift al safe zone.
You tried to reduce it closed and did a hip arthrogram. Figure 18.56 shows the arthrogram. Do you want to comment on the findings?
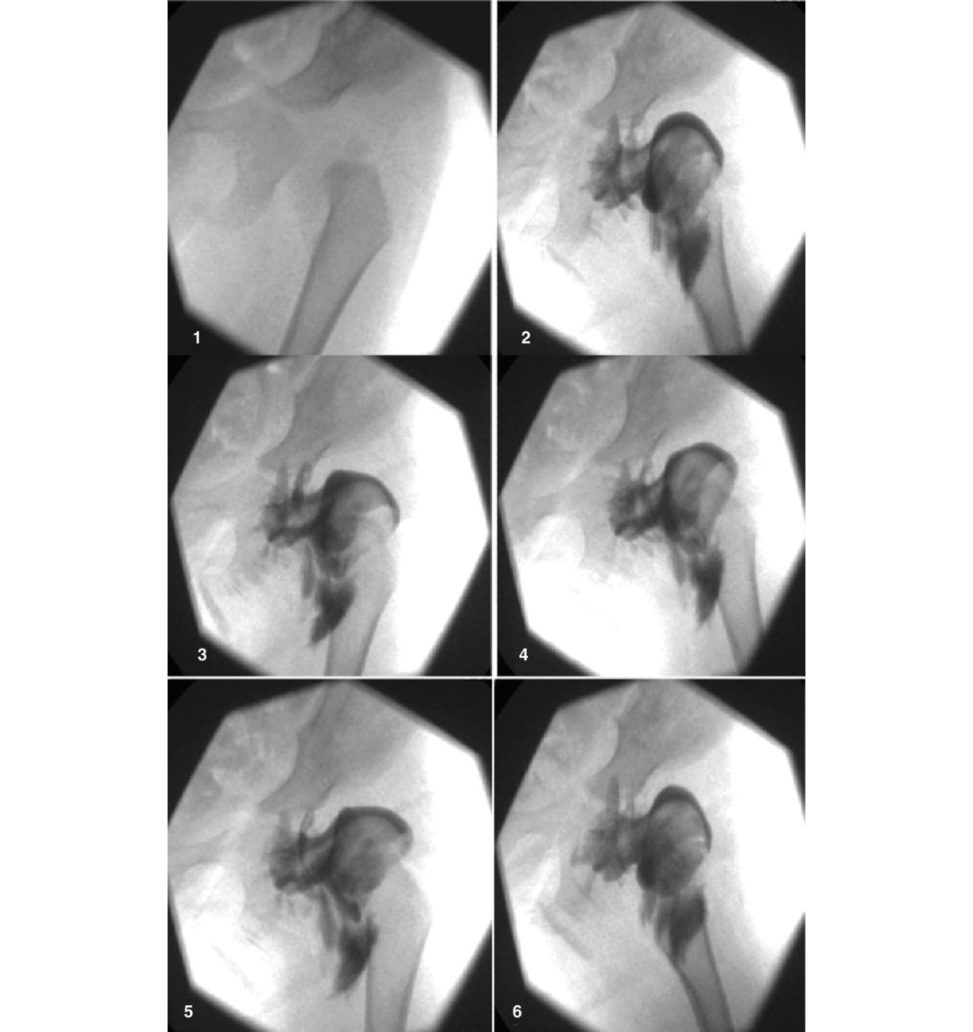
The arthrogram nicely shows the full size of the femoral head, which is much bigger than the ossified nucleus. The isthmus is further constricted by the Chinese trap effect as well as by pressure from the iliopsoas tendon (visible in pictures 2 and 6). The ligamentum teres is thickened and elongated (pictures 2–6). None of the pictures demonstrate a reduced hip and there is significant medial dye pool.
Figure 18.56 Hip arthrogram of a 19-month-old child.
What prevents reduction?
Extra-articular structures: 1. 2. Capsular constriction. B. Intra-articular (2 ligaments + 2 pathological structures):
1. Elongated ligamentum teres.
2. Thickened transverse acetabular ligament giving the acetabular cartilage the classic horse-shoe structure.
3. Pulvinar (fibro-fatiy tissues filled the acetabulum ).
4. Inverted limbus.
What is the limbus?
There is no anatomical structure called limbus (or neolimbus), but it is the name given to the deformed and moulded labrum.
So, what would you do in the above situation?
Pelvic osteotomy is often needed and femoral osteotomy may be needed as well.
Take me through how would you do open reduction throu ghan anterior hip approach? Authors’ note: 9 DD His one of the commonest paediatric topics that have been featured in the exam. It is not the candidates’ favourite, particularly if they have not done a paediatric orthopaedic job. The topic is nicely covered in the postgraduate paediatric orthopaedic book and the relevant section in the third edition. You do not need to know all the ins and outs of the topic as longas you know the principles. Treatment options depend on the age of child at presentation, reducibility of hip, stability after reduction anda mount of acetabular dysplasia. Authors’ note: 10 The FRCS (Trauma and Orthopaedic) exam is easy topass, but ironically it is also easy to fail. Having helped hundreds of candidates topass their exam, we find it is all about preparation: ‘If you fail to prepare, then prepare to fail’. Core knowledge and skills are important, but what is most important is how to present them clearly and confidently. This will come with practice. The Postgraduate Orthopaedic faculty wish you all the best for your exam. Table 18.10 Dislocated hip management. Age groups Treatment
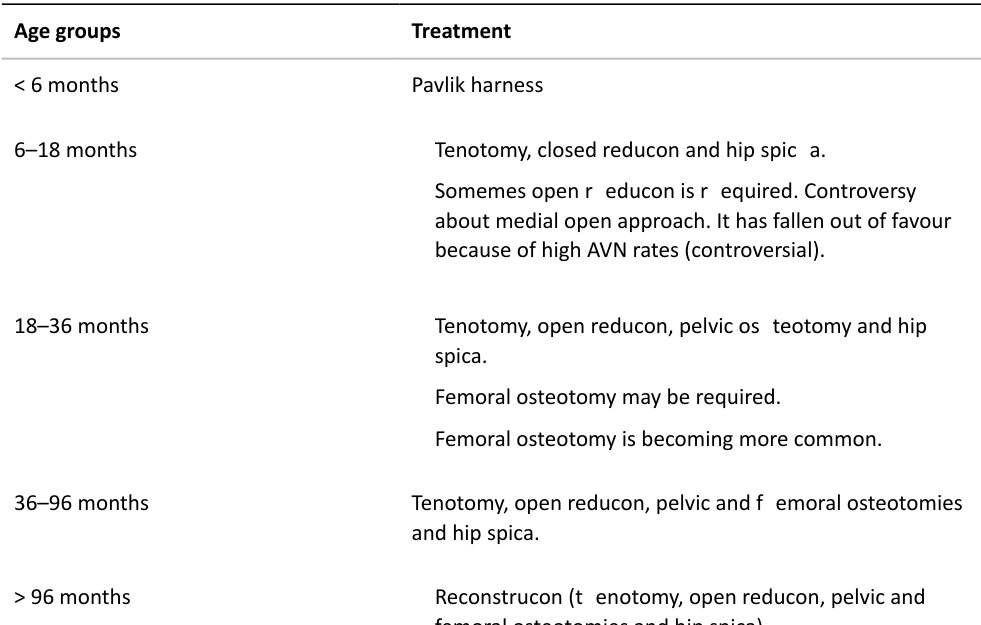
vs.
Leave it unreduced.
Have some answers about controversial points, including:
- Routine screening: only patient sat risk/with abnormal exam will have an ultrasound scan.
- Traction before closed reduction: Supporters suggested that traction reduces the need for open reduction; without traction mainly duet o better understanding of treatment principles; which encourage gentle reduction; the use of the human position to maintain reduction.
- Medial vs. anterior approach for open reduction.
- Pelvic osteotomy types and indications.
- Reconstructive must have concentric reduction.
ARe directional: Salter, Pemberton, double (Sutherland), triple (Steel) and periacetabular (Ganz/PAO).
B. Reshaping Dega and Pemberton (Pemberton osteotomy mainly directional but can change the shape as well).
- Salvage: Shelf and Chiari.
References
1. Alshryda S, JonesS, Banaszkiewicz P. Postgraduate Paediatric Orthopaedics: The Candidate’s Guide to the FRCS (Tr and Orth) Examination . Cambridge: Cambridge University Press; 2014.
2. Loder RT Richards BS, Shapiro PS, Reznick LR, Aronson DD. Acute slipped capital femoral epiphysis: the importance of physeal stability. J Bone Joint Surg Am. 1993;75(8):1134–1140.
3. Alshryda ST sang K, Chytas A, et al. Evidence based treatment for unstable slipped upper femoral epiphysis: systematic review and exploratory patient level analysis. The Surgeon. 2018;16(1):46–54.
4. Alshryda ST sang K, Ahmed M, Adepapo A, Montgomery R. Severe slipped upper femoral epiphysis;
fish osteotomy versus pinning-in-situ: an eleven year perspective The Surgeon. 2014;12(5):244–248.
5. Jerre R, Billing L, Hans sonG, Wallin J. The contralateral hip inpatients primarily treated for unilateral slipped upper femoral epiphysis. Long-term follow-up of 61 hips. J Bone Joint Surg Br. 1994;76(4):563–567.
6. Phillips PM, Phadnis J, Willoughby R, Hunt L. Posterior sloping angle as a predictor of contralateral slip in slipped capital femoral epiphysis. J Bone Joint Surg Am. 2013;95(2):146–150.
7. Stasikelis PJ, Sullivan CM Phillips WA, Polard JA. Slipped capital femoral epiphysis. Prediction of contralateral involvement. J Bone Joint Surg Am. 1996; 78(8):1149–1155.
8. Parsch K, WellerS, Parsch D. Open reduction and smooth Kir schner wire fixation for unstable slipped capital femoral epiphysis. J Pediatr Orthop. 2009;29(1):1–8.
9. Ziebarth K, Zilkens C, SpencerS, Leunig M, Ganz R, Kim Y-J. Capital realignment for moderate and severe SCFE using a modified Dunn procedure. Clin Orthop Relat Res. 2009;467(3):704–716.
10. Naseem H, Chatterji ST sang K, Hakimi M, Chytas A, Alshryda S. Treatment of stable slipped capital femoral epiphysis: systematic review and exploratory patient level analysis. J Orthop Traumatol.
2017;18:469.
11. British Orthopaedic Association . BOAST11. Supracondylar fractures of the humerus in children. 2014.
12. Isaacs H, Handelsman JE, Badenhorst M, Pickering A. The muscles in clubfoot – a histological histochemical and electron microscopic study. J Bone Joint Surg Br. 1977;59B(4):465–472.
13. Gray DH, Katz JM. A histochemical study of muscle in clubfoot. J Bone Joint Surg Br. 1981;63B(3):417–423.
14. Wynne-Davies R. Genetic and environmental factors in the etiology of talipes equinovarus. Clin Orthop
Relat Res. 1972;84:9–13.
15. Sharon-Weiner M, Sukenik-Halevy R, Tepper R, Fishman A, Biron-Shental T, Markovitch O. Diagnostic accuracy, work-up, and outcomes of pregnancies with clubfoot detected by prenatal sonography. Prenat
Diagn. 2017;37(8):754–763.
16. Ponseti IV, Morcuende JA. Current management of idiopathic clubfoot questionnaire: a multic enter study. J Pediatr Orthop. 2004;24(4):448.
17. Ponseti IV, Smoley EN. Congenital clubfoot: the result of treatment. J Bone Joint Surg Am.
1963;45(A(2)):261–344.
18. Huntley JS. What is the best treatment for paediatric trigger thumb (acquired thumb flexion contracture)? InS Alshryda, JS Huntley, P Banaszkiewicz (Eds.), Paediatric Orthopaedics: An Evidence-Based Approach to Clinical Questions . Cham: Springer; 2016.
19. Caird MS, Flynn JM, Leung YL, Millman JE, D’Italia JG, Dormans JP. Factors distinguishing septic arthritis from transient synovitis of the hip in children. A prospective study. J Bone Joint Surg Am.
2006;88(6):1251–1257.
20. Maharajan K, Patro DK, Menon J, et al. Serum procalcitonin is a sensitive and specific marker in the diagnosis of septic arthritis anda cute osteomyelitis . J Orthop Surg Res. 2013;8:19.
21. Zhao J, Zhang S, Zhang L, et al. Serum procalcitonin levels as a diagnostic marker for septic arthritis: a meta-analysis. Am JEm erg Med. 2017;35(8):1166–1171.
22. Kocher MS, Zurakowski D, Kasser JR. Differentiating between septic arthritis and transient synovitis of the hip in children: an evidence-based clinical prediction algorithm. J Bone Joint Surg Am.
1999;81(12):1662–1670.
23. Kocher MS, Mandi gaR, Zurakowski D, Barnewolt C, Kasser JR. Validation of a clinical prediction rule for the differentiation between septic arthritis and transient synovitis of the hip in children. J Bone Joint Surg
Am. 2004;86A(8):1629–1635.
24. Herring JA, Kim HT, BrowneR. Legg–Calve–Perthes disease. Part II: Prospective multic enter study of the effect of treatment on outcome. J Bone Joint Surg Am. 2004;86A(10):2121–2134.
25. Wiig O, Terjesen T, Svenningsen S. Prognostic factors and outcome of treatment in Perthes’ disease: a prospective study of 368 patients with five-year follow-up. J Bone Joint Surg Br. 2008;90(10):1364–1371.
26. Wright JG. Evidence-Based Orthopaedics. The Best Answers to Clinical Questions , ed. J. Wright. Philadelphia: Saunders; 2009.
27. Daly K, Bruce C, Catterall A. Lateral shelf acetabuloplasty in Perthes’ disease. A review of the end of growth. J Bone Joint Surg Br. 1999;81(3):380–384.
28. Domzalski MEG luting J, Bowen JR, Litile ton AG. Lateral acetabular growth stimulation following a labral support procedure in Legg–Calve–Perthes disease. J Bone Joint Surg Am. 2006;88(7):1458–1466.
29. Bankes MJ, Catterall A, Hashemi-Nejad A. Valgus extension osteotomy for ‘hinge abduction ’ in
Perthes’ disease. Results at maturity and factors influencing the radiological outcome. J Bone Joint Surg
Br. 2000;82(4):548–554.
30. Seg evE, Ezra E, Wientraub S, Yaniv M, Hayek S, He moY. Treatment of severe late-onset Perthes’
disease with soft tissue release and articulated hip distraction revisited at skeletal maturity. J Child
Orthop. 2007;1(4):229–235.
31. Laklouk MA, Hosny GA. Hinged distraction of the hip joint in the treatment of Perthes disease:
evaluation a t skeletal maturity. J Pediatr Orthop B. 2012;21(5):386–393.
32. Davids JR, Blackhurst DW, Allen Jr BL. Clinical evaluation of bo wed legs in children. J Pediatr Orthop B.
2000;9(4):278–284.
33. Levin eAM, Drennan JC. Physiological bowing and tibia v ara. The metaphyseal–diaphyseal angle in the measurement of bowleg deformities . J Bone Joint Surg Am. 1982;64(8):1158–1163.
34. O’Neill DA, MacEwen GD. Early roentgenographic evaluation of bowlegged children. J Pediatr Orthop.
1982;2(5):547–553.
35. McCarthy JJ, Betz RR, Kim AD avids JR, Davidson RS. Early radiographic differentiation of infantile tibia vara from physiologic bowing using the femoral–tibial ratio . J Pediatr Orthop. 2001;21(4):545–548.
36. Herring JA (Ed.). Tachdjians Pediatric Orthopaedics, Vol. 1. Philadelphia: Saunders Elsevier; 2008.
37. Raney EM, Topoleski TA, Yaghoubian R, Guidera KJ, Marshall JG. Orthotic treatment of infantile tibia vara. J Pediatr Orthop. 1998;18(5):670–674.
38. Richards BS, Katz DE, Sims JB. Effectiveness of brace treatment in early infantile Bloun t’s disease. J Ped
Orthopaed. 1998;18(3):374–380.
39. Ramsey PL, Lass erS, MacEwen GD. Congenital dislocation of the hip: use of the P avlik harness in the child during the first six months of life. 1976. J Bone Joint Surg Am. 2002;84A(8):1478; discussion 1478.
Section 5