Chapter 20 Structure and function of connective tissue
Paul A. Banaszkiewicz
Introduction#
Section 2 of the basic science (Tr & Orth) syllabus is a large topic, difficult to grasp at face value as it appears quite removed from the average orthopaedic surgeon’s practice.
It contains large sections of A-list topics that just need to be learnt as well as possible, otherwise marks will be thrown away.
Candidates may be asked very general questions or questions in more detail, so you need to cover both bases.
Candidates will need to double time on this section to both understand the topics.
This section was generally well received in the first edition viva book and we have kept and updated the majority of previous viva questions.
1. Bone structure and function#
This is an A-list topic.
Structured oral examination question 1#
What is bone?
Bone is a dynamic composite form of specialized connective tissue composed of cells (10%) and matrix (90%). The matrix has inorganic (60%) and organic (40%) components ... Or Bone is an organ.
What is an organ?
Make sure you know the definition of an or gan.1 Try to avoid giving an answer that will lead you up a blind alley. An organ is composed of multiple tissue types.
What are the functions of bone?
The three main functions of bone are: 1. 3. A mechanical role in supporting the bodys tissues providing attachment for muscles and protecting internal organs.
Describe the structure of bone.
There are two main macroscopic types of bone, either (1) lamellar or (2) woven. The structure of lamellar bone can be either cortical compactor cancellous trabecular bone. Woven bone can be either immature (fracture callus) or pathological. Candidates may be pressed in a bit more detail about the differences between woven and lamellar bone, especially at the beginning of a viva, because it is basic information candidates would be expected to know. Woven bone Has a random arrangement of collagen, there are no lamellae, it is weaker and more flexible than lamellar bone. More cellular (×8 lamellar bone). Table 20.1 Lamellar bone versus woven bone.

Found in Immature (embryonic/neonatal skeleton, metaphyseal region fracture healing)

High-yield orthopaedics: Differentiating features of woven vs. lamellar bone.
No lamellae, isotropic.
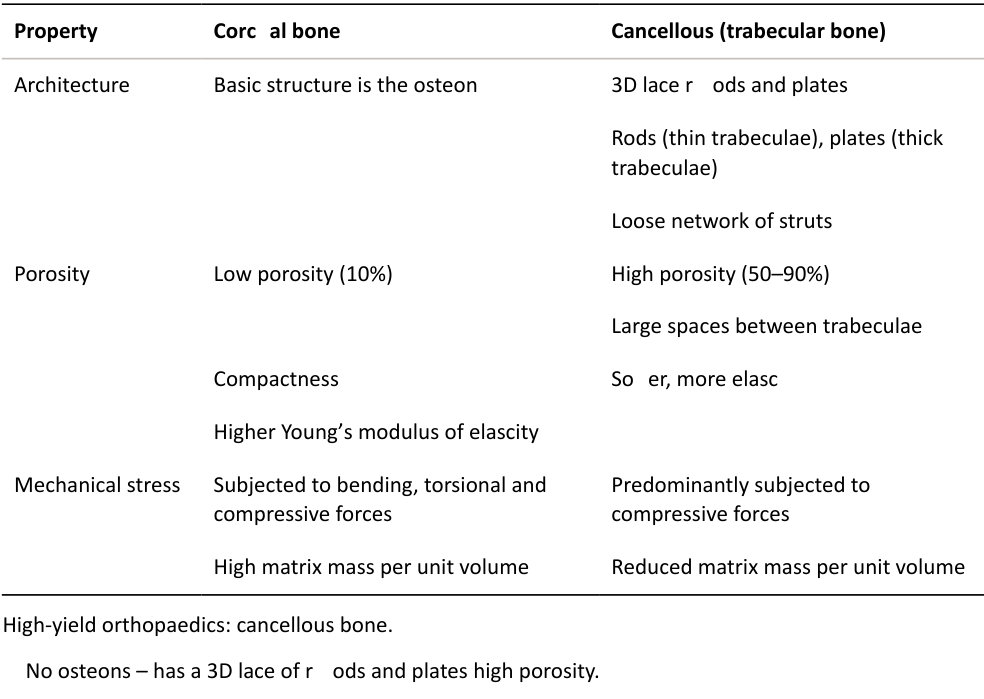
What is the difference between cortical and cancellous bone (Table 20.2)?
It is usually found in the diaphysis of long bones. It has an architecture of 3D latice rods and plates, high porosity with large spaces between trabeculae and predominantly subjected to compressive loads.
What do we mean by the term isotropic?
Isotropic refers to uniform properties in all directions, independent of the direction of load application.
So, which type of bone is isotropic?
Woven.
So, what about lamellar bone. Is this isotropic?
No.
Why?
These are fairly straighfoorward questions but may catch the unprepared candidate out. Lamellar bone has stress-orientated collagen fibres and has anisotropic features.
What is the structure of bone?
The main structural unit within cortical bone is the Haversian system osteon) with its central neurovascular channels enclosed within concentric lamellae. Each osteon or Haversian system consists of five to seven concentric layers (lamellae) of bone matrix. Volkmann’s canals run perpendicular to the long bone axis carrying blood vessels to and from the Haversian systems to the outer surfaces of the bone. Bone compromises cells (10%) and extracellular matrix (90%). The matrix has organic (collagens, mainly type 1) and inorganic (calcium phosphate, osteocalcium phosphate) constituents.
What are the main types of bone cells and what are their functions?
The main types of bones cells, and their function, areas follows: 1. 2. Osteoclast: bone-resorbing cells, multinuclear irregular giant cells. 4. Osteoprogenitor cell: precursors to osteoblasts that line the Haversian system and can be stimulated to differentiate into osteoblasts and form new bone.
The osteoprogenitor cells originate from mesenchymal stem cells and line the Haversian canals, endosteum and periosteum.
How do osteoblasts and osteoclasts differ?
Osteoblasts are derived from undifferentiated mesenchymal cells; they are bone-forming and laydown osteoid (type 1 collagen) as well as activating osteoclasts to resorb bone via the receptor activator of nuclear factor κβ (RANK) and its ligand (RANKL) system. RANK Lis expressed by macrophages and osteoblasts, and functions as an activator of RANK. RANK, expressed on osteoclast precursors, is a key regulator of osteoclastogenesis. They can sit in small pits called Howship’s lacunae, on the bone surface, or lead cuting c ones that tunnel through the bone. This process is controlled via the RANKL system (inhibited by osteoprotegerin) of activated osteoblasts. Osteocytes are osteoblasts that have become trapped in bone matrix (comprising up to 90% of the cells in bone).
What is Wolf flaw?
Wolf flaw states that bone will adapt to the loads placed through or across it. It is the result of the close coupling within bone remodelling units consisting of osteoblasts, osteoclasts and supporting stromal tissues.
Can you give me an example of Wolf flaw?
The racket-holding arms of tennis players are stronger than the other arm. There is thicker cortical bone alongside hypertrophy of the muscle attachment sites. The arm is about a third bigger in size (35%).
if loading on a bone decreases, the bone will become less dense, weaker due to the lack of stimulus required for continued remodelling.
What is the Hueter–Volkman law?
This law suggests mechanical factors influence longitudinal growth, bone remodelling and fracture repair. The underlying mechanisms remain unclear.
What controls the differentiation of osteoblasts?
Two transcription factors are important for osteoblastic differentiation. 1. Osterix (Os xis an osteoblast-specific transcription factor essential for osteoblast differentiation and bone formation.
What are transcription factors?
Transcription factors are proteins involved in the process of converting , or transcribing, DN Aint oRNA.
What is this cell line?
A picture was shown of an osteoclast in Howship’s lacuna (Figure 20.1).
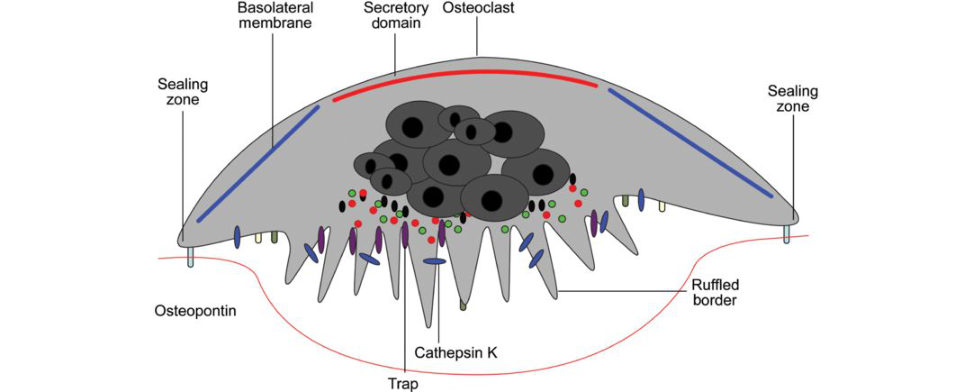
Figure 20.1 Activated osteoclast. The osteoclast plasma membrane is divided into multiple domains. A t the ruffled border, the osteoclast secretes acid and lysosomal enzymes that digest the mineral and protein components of the underlying bone. The degradation products of collagen and other matrix components are endocytosed, transported through the cell and exocytosed through a functional secretory domain.
This is an activated osteoclast.
How do osteoclasts resorb bone?
Osteoclasts resorb bone by binding to the bone surface using integrin anchor proteins and secreting hydrogen ions into the sealed area produced with a carbonic anhydrase system allowing dissolution of hydroxyapatite mineral matrix.
What do you understand by the term remodelling? Describe the process.
Remodelling is the process whereby the structure of bone is transformed from disorganized, haphazard immature bone to organized lamellar bone by osteoclast cuting c ones.
Can you please draw an osteoclastic cuting c one for me?
Learn to draw a cuting c one and be able to describe how this functions to remodel bone as you go along (Figures 20.2 and 20.3).
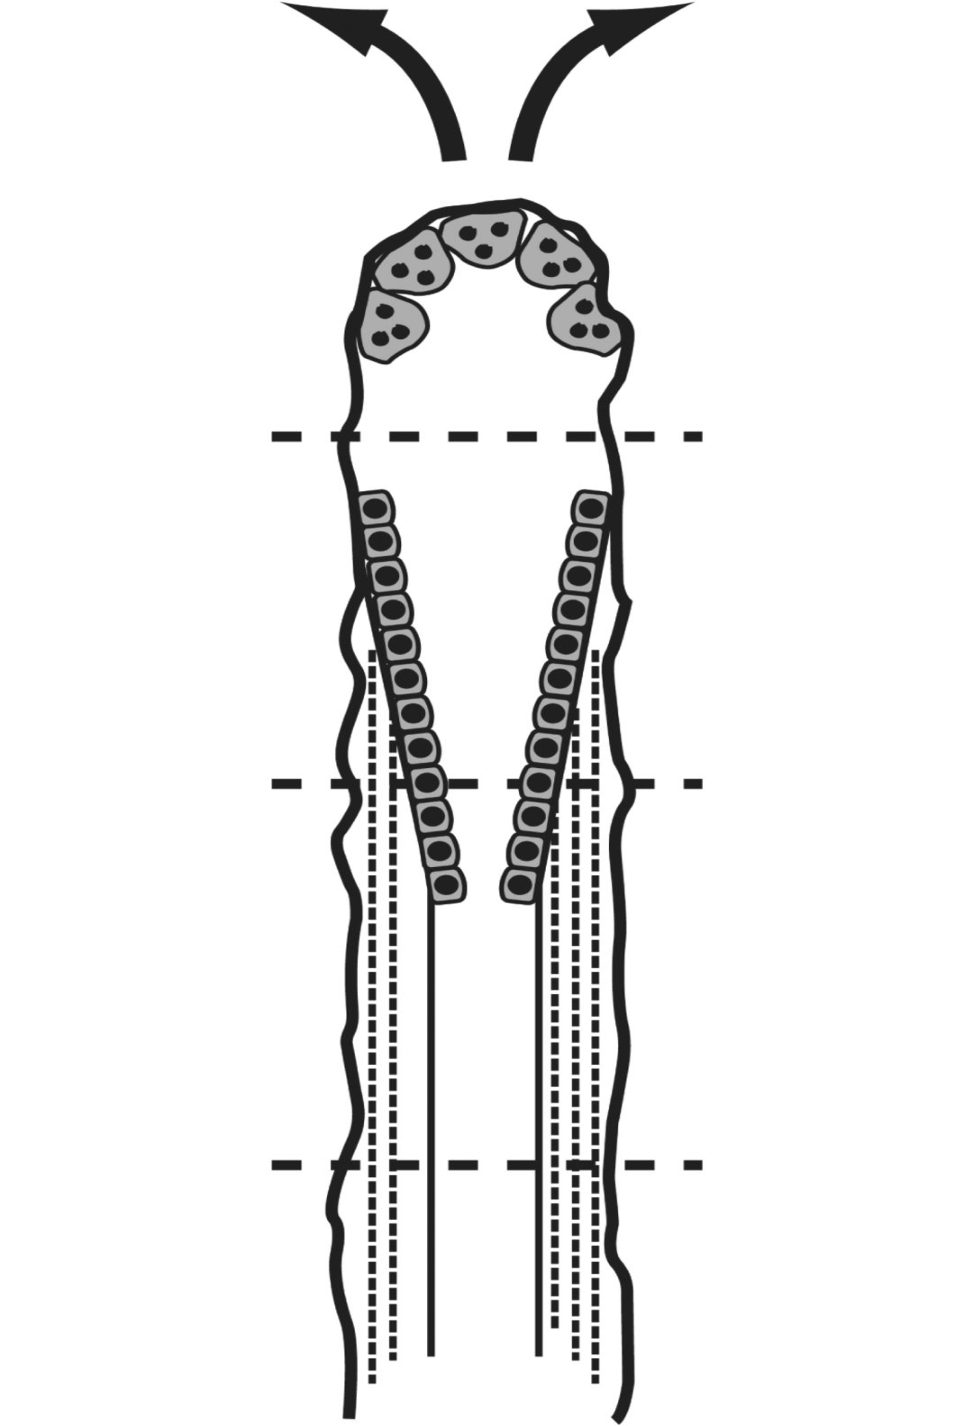
Figure 20.2 Osteoclastic cuting c one. Candidate drawing. The cuting filling c one has a head of osteoclasts that cut through the bone, and a tail of osteoblasts that form a new secondary osteon.
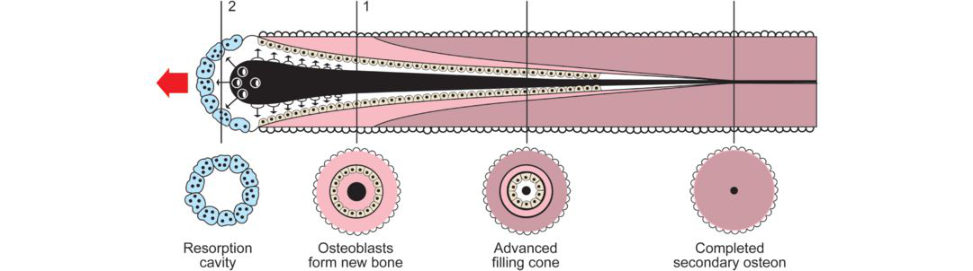
Figure 20.3 Osteoclastic cuting c one. At its tip osteoclastic resorption takes place while in the latter parts of the cone osteoblasts deposit osteoid with subsequent mineralization Reversal refers to a 1- to 2-week interval between completion of resorption and initiation of bone matrix formation. The structure terminates as a closing zone in which osteoblasts close the newly excavated osteon by adding centripetal layers of lamellar bone inward from the cement line boundary.
How and from where does bone derive its blood supply?
(a) High-pressure nutrient artery system. The nutrient arteries are branches of the systemic circulation and en ter the bony mid-diaphysis through the nutrient foramen passing to the medullary canal before branching into ascending and descending vessels and arteriolar branches supplying the inner two-thirds of the diaphyseal cortex (endosteal circulation). (c) Metaphyseal–epiphyseal system is the periarticular vascular complex that penetrates the cortex and supplies the metaphysis, physis and epiphysis with end arterioles.
What is the direction of blood flow within a long bone?
Arterial flow in mature bone is centrifugal (inside to outside), which is the net effect of the high-pressure nutrient artery system and the low-pressure periosteal system.
Venous flow in mature bone is centripetal.
Describe the structure of the periosteum.
The periosteum consists of an outer layer of fibroblasts and an inner layer of osteoblasts. With age, the periosteum thins and has less osteogenic capability.
What are the functions of the periosteum?
Functions of the periosteum include: Medium through which muscles, tendons and ligaments are attached. Can form bone when required.
What is the structure of collagen in bone?
Collagen is type 1 in bone. The structural unit of type 1 collagen is called tropocollagen and is a trimer composed of three polypeptide chains. T wo chains are α1 chains and the third chain is α2. Each polypeptide chain is a le ft-handed helix, but the triple helix is a right-handed superhelix (i.e. the opposite way around) (Figure 20.4). The triple helical structure is not the same as the α helix that is formed by a single polypeptide chain and is the defining feature of all collagen. It is a fibril-forming collagen.
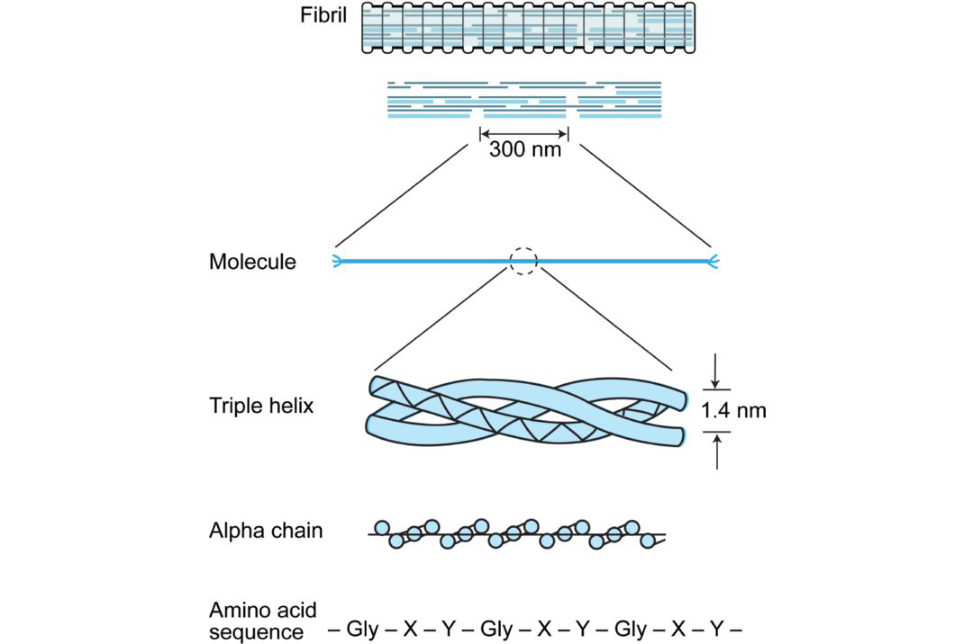
Figure 20.4 Several tropocollagen molecules are aggregated in an organized head-to-tail fashion into a structure called a collagen fibril. These collagen fibrils can beseen with an electron microscope and exhibit a 67-nm D-period banded appearance due to staggered gaps between the heads and tails of the molecules in each row.
How is collagen assembled?
Collagen biosynthesis and assembly is a complex process that involves several steps. Pro collagen is secreted out of the cell.
What do we mean by osteoclastogenesis?
Osteoblasts secrete receptor activator of nuclear factor κβ ligand (RANK Land macrophage colony- stimulating factor (M-CSF) to activate osteoclasts. With RANK activation, specific genes are switched on and the osteoclast becomes programmed to resorb bone. OPG acts as a decoy receptor, blocking RANKL binding and subsequent activation of the
RANK system, thus inhibiting osteoclast differentiation and bone resorption.
What are osteotropic factors?
They induce the formation of osteoclasts by upregulating RANKL expression on the surface of marrow stromal cells and immature osteoblasts (see Figure 20.5).
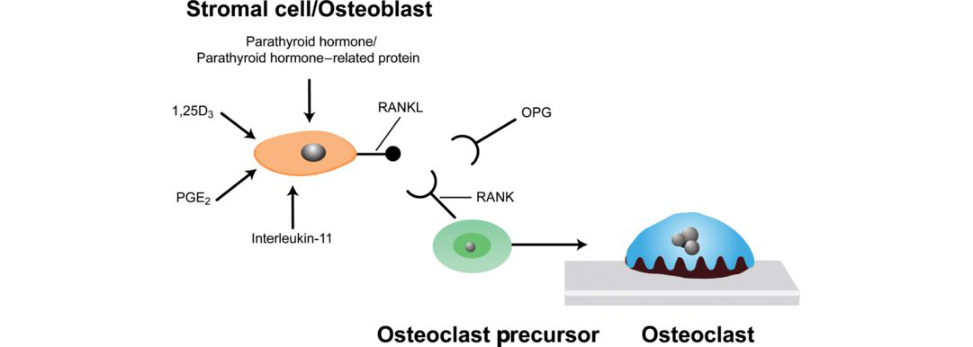
What is an osteoclastic cuting c one?
Figure 20.5 Osteoblast/osteoclast coupling.
Osteoclasts at the front of the cuting c one remove bone and are followed by layering of osteoblasts and successive deposition of layers of lamellae after the cement line has been laid down. The head of the cuting c one is made up of osteoclasts (which boreholes through hard cortical bone).
Can you draw a cuting c one out?
[Figure 20.3] Remember to keep the diagram simple.
Draw me the structure of bone.
Candidates should discuss the structure of bone as they draw paying particular attention to Haversian systems (Figure 20.6).
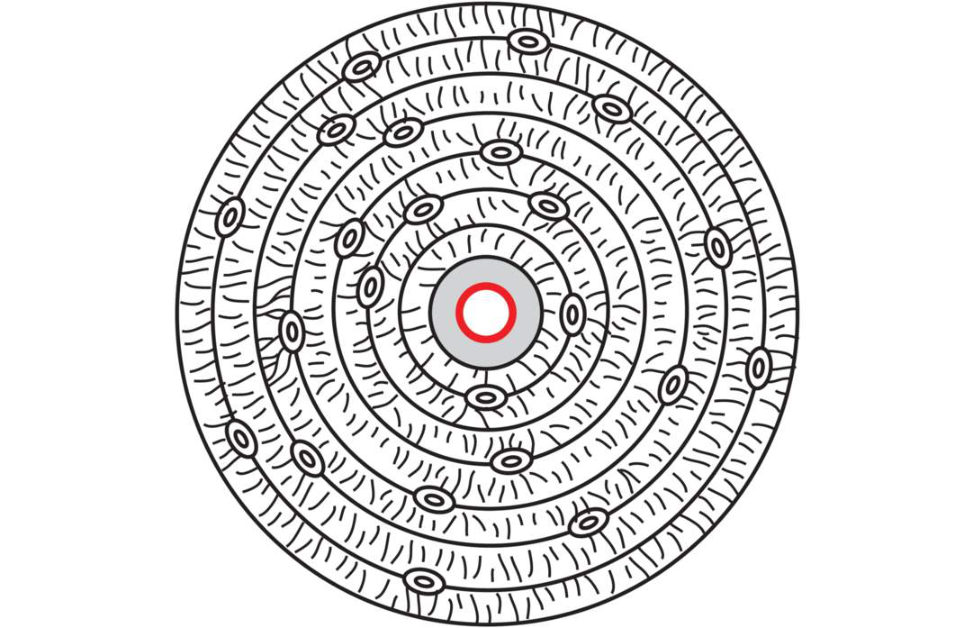
Figure 20.6 Structure of bone. Candidate drawing.
What is bone composed of?
Bone consists of cells (10%) and extracellular matrix (90%). Organic (40%). Collagen (type I) 90%.
- ▪ Osteocalcin, osteonectin, os teopontin. ·
Growth factors and cytokines.
Inorganic (60%).
Primarily hydroxyapatite Ca5(PO4)3(OH)2.
What type of collagen is present in bone?
Type 1 [Remember – BONE].
Draw me some collagen.
Figure 20.7(b) is more complicated, but allows candidates more opportunity to focus on the hierarchical collagen arrangement.
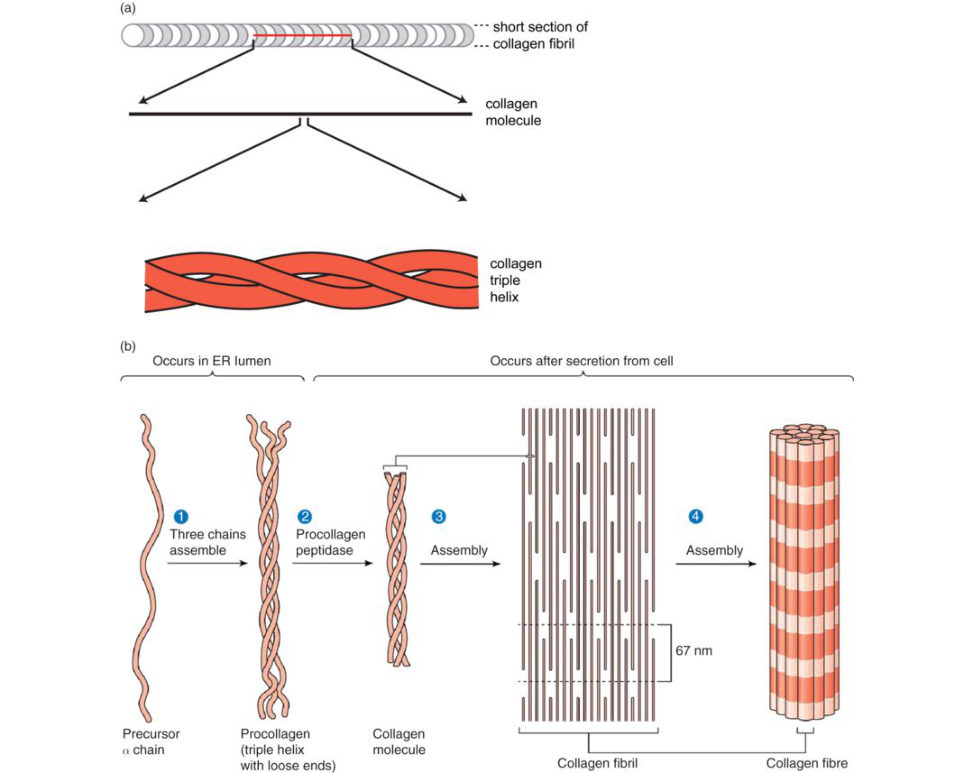
Figure 20. 7 (a) Candidate drawing. Structure of collagen. (b) More complex drawing of collagen assembly.
What do you know about the collagen structure in osteogenesis imperfecta (OI)?
Collagen is type 1 in bone. The structural unit of type 1 collagen is called tropocollagen and is a trimer composed of three polypeptide chains. The collagen triple helix forms because both the α1 and α2 chains contain repeat sequences of amino acids (-gly-X-Y), where gl yis glycine, X is proline andY is usually hydroxyproline.
Wit hOI the majority of identified mutations are single nucleotide substitutions that result in alteration of glycine codons within the triple helical domain of either of the chains of type I procollagen (Figure 20.8).
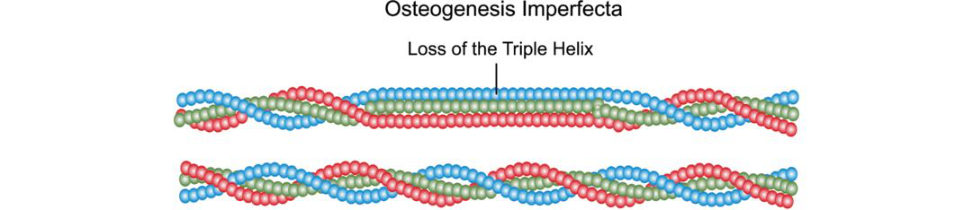
Figure 20.8 Collagen structure in osteogenesis imperfecta. Triple helix steric hindrance.
What is the gene coding fo rOI?
COL1A1 and COL1A2 are the genes that encode the two chains pro α1(I) and pro α2(I), respectively, of type I procollagen.
What about qualitative versus quantitative collagen deficiencies in osteogenesis imperfecta (OI)?
OI is a group of disorders with broad variations in clinical severity. Quantitative defects are often heterozygous, with one copy not producing any collagen.
What about compression and tension of bone?
An eccentrically loaded bone has a compression and tension side. Whenever feasible, any internal or external fixation device should be applied to the tension side to provide maximum stability.
Draw me a longitudinal cross section of a long bone and t ell me the areas (Figure 20.9).
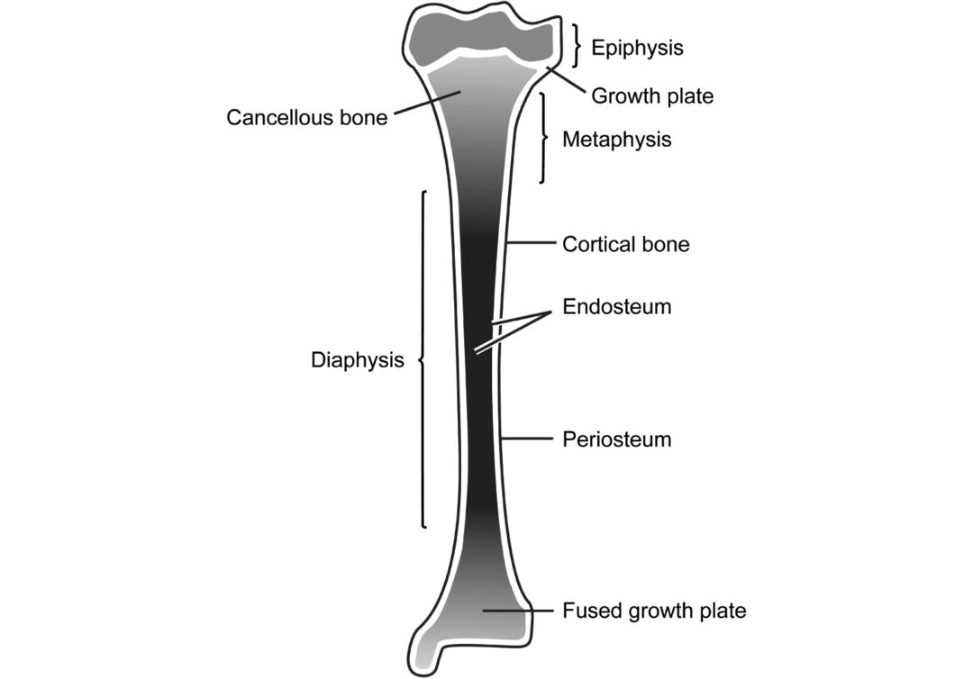
Figure 20.9 Drawing of a typical long bone.
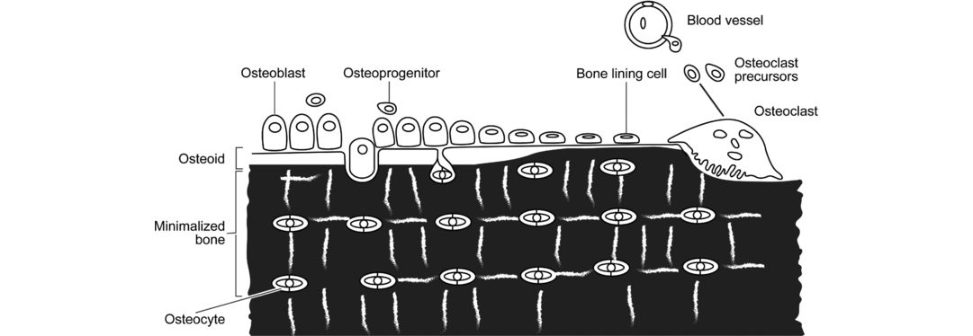
Where are the cells? Where are the osteoblasts? Where are the osteocytes?
Osteocytes are derived from osteoblasts and are essentially osteoblasts surrounded by the products they secrete (Figure 20.10).
What do you know about skeletal dysplasias?
Rubin’s classification of bone dysplasia is based on the type of abnormality (hypo-/hyperplasia) and the site involved in the bone: (1) epiphyseal, (2) physeal, (3) metaphyseal, (4) diaphyseal location.

Structured oral examination question 2#
Draw me the structure of cortical bone (Figure 20.11a and 20.11b).
The cross-section of a long bone was quickly drawn, but we then almost immediately moved on to discussing the structure of compact bone.
What runs in a Haversian canal?
Haversian canals contain blood vessels lymphatics and nerves and are enclosed by closely packed concentric lamellae of bone.
What is the Haversian system?
The Haversian system, or osteon, is the basic structural unit of cortical bone and lies parallel to the long axis of the bone. Volkmann’s canals run transversely to the bone’s long axis and permit communication between the outer vessels of the periosteum and the Haversian canals.
Where do osteocytes originate from?
Osteocytes are trapped osteoblasts located within lacunae between lamellae.
What do canaliculi do?
Canaliculi are the spaces or ‘canals’ occupied by osteocyte cell processes. They connect the lacunae together within the cortical bone.
How do bisphosphonates work?
Bisphosphonates are a class of anft-r esorptiv e agents used to treat diseases characterized by osteoclast-mediated bone resorption.
They act differently to diminish bone resorption.
Non-nitrogen-containing BPNs are metabolized into non-functioning ATP analogues, which cause eventual osteoclast apoptosis.
These small GTPases are signalling proteins that regulate a number of cell processes such as membrane ruffling, cytoskeletal organization and trafficking of vesicles, which are required for osteoclast function.
Can you tell me some clinical uses of bisphosphonates?
Clinical uses would include osteoporosis, hypercalcaemia of malignancy, Paget’s disease, solid tumours and metastatic bone disease AVN and stress fracture.
Structured oral examination question 3#
Bone healing, primary vs. secondary. Including cellular signalling pathways. Draw an osteonal cuting cone.
What do we mean by primary bone healing?
Primary bone healing is led by osteonal cuting c ones that consist of osteoclasts at the front of the cone that ream out a tunnel in the bone into which a blood vessel grows. Primary bone healing occurs only under low interfragmentary movement (rigid fixation). Primary bone healing can be further divided into gap and contact healing.
What is contact healing?
Contact healing occurs if bone fragments have direct appositional contact and the gap between bone ends isless than 0.01 mm with an interfragmentary strain of less than 2%.
And gap healing?
Gap healing occurs when a small stable fracture gapless than 1 mm is present between bony fragments. The fracture site is initially filled with transverse lamellar bone without intermediate fibrous or cartilage precursors. Gap healing – small stable fracture gap.
What is secondary bone healing?
Secondary bone healing involves the formation of fracture callus. There is: 1. 2. An inflammatory phase with local accumulation of macrophages, MSC, cytokines.
3. Primary soft callus formation. Granulation tissue gradually differentiates into fibrous tissue and afterwards fibrocartilage.
4. Callus mineralization (hard callus). Osteoblasts laydown woven bone at the periphery
(intramembranous ossification), new woven bone is laid down (endochondral ossification).
Cartilage is found during the early stages of healing replaced by woven bone laid downby osteoblasts.
Primary and secondary bone healing comes up repeatedly in the viva exam and candidates need to be very clear about the distinction between them. Key points are as follows: Primary bone healing Requires anatomical reduction and inter fragmentary compression. Fibrocartilage develops at the bone ends and this is subsequently calcified and replaced by woven bone or osteoid.
What is Perren’s strain theory?
Cortical bone can only tolerate 2% strain. Rigid internal compression fixation, which minimizes strain, will lead to primary fracture healing. Lamellar bone can tolerate up to 10% strain, and when this relative stability is present, the fracture heals with callus or secondary fracture healing. Fracture healing will not occur when the strain at a fracture gap exceeds 10%.
[At the very end of the topic after discussing primary and secondary bone healing, Perren’s strain theory] There was a very well-wrift en important paper published recently that discussed fracture healing.
Which paper is that?
It was a paper published in the JBJS.2
What did the paper say?
Candidates should refrain from mentioning a paper they haven’t fully read and struggle to say anything sensible about.3 Ellioft et al. consider the whole fracture to be a ‘bone-healing organ’ that works as a functional unit and responds to biological and mechanical stimuli. In BHN, the bone is in homeostasis when under tolerable strain (much less than 2%). For strains greater than 2% and less than 100%, a fracture occurs and is considered to be the beginning of the ‘bone-healing organ’. Finally, for strains above 100%, the ‘bone-healing organ’ stops and fails to heal, leading to non-union.
Structured oral examination question 4#
Which cells reside in bone?
Osteoblasts, osteoclasts, osteocytes, bone lining cells and osteoprogenitor cells.
Figure 20.10 Bone remodelling. The origins and locations of bone cells.
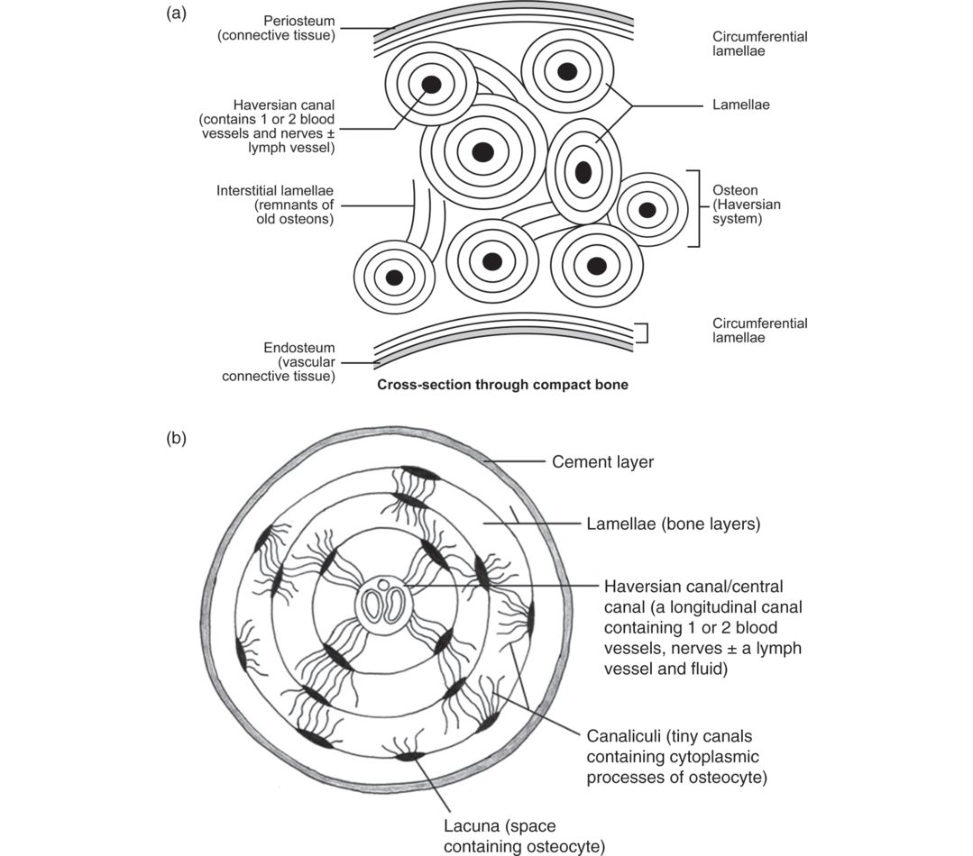
Figure 20.11 Candidate drawing. Cross-section of (a) long bone and (bos teon.
What do they all do?
Osteoblasts are large cells responsible for the synthesis and mineralization of bone during both initial bone formation and la ter bone remodelling. Osteoblasts form a closely packed sheet on the surface of the bone, from which cellular processes extend through the developing bone. Osteocytes lie within the substance of fully formed bone. They lie within a small space called a lacuna, which is contained in the calcified matrix of bone.
Where are osteoclasts derived from?
RANK Lis produced by osteoblasts, binds to immature osteoclasts and stimulates differentiation in to active mature osteoclasts and macrophage colony stimulating factor (M-CSF). Osteoprotegerin inhibits bone resorption by binding and inactivating RANKL.
Tell me about mesenchymal stem cells.
MSCs are multipotent stem cells that can differentiate into a variety of cell types.
What types of cartilage do you know about?
There are three types of cartilage hyaline cartilage, fibrocartilage and elastic cartilage.
Draw a cross-section of articular cartilage (Figure 20.12).
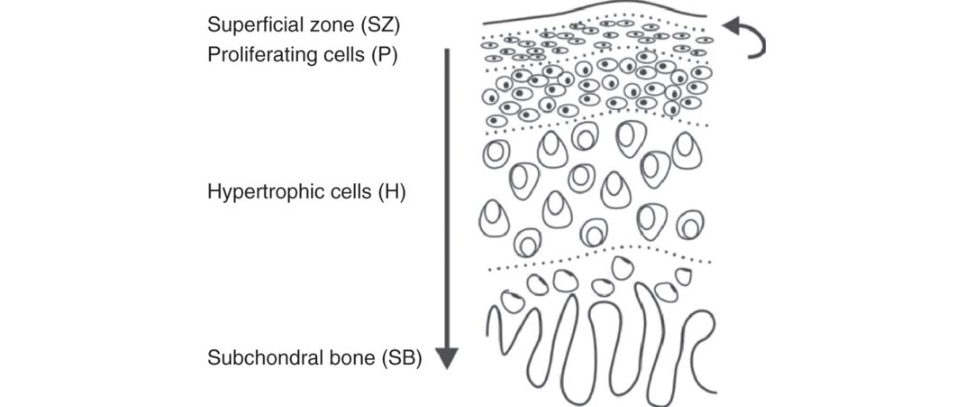
Figure 20.12 Articular cartilage layers.
Draw and talk about the different layers. Practise the drawing and discussion of it at least 10 times.
What are the differences between articular cartilage and meniscus?
Articular cartilage is 68–85% water, 10–20% (type II) collagen and 5–10% proteoglycans.
Can you draw a picture of collagen and proteoglycans?
Draw the standard picture seen in many textbooks (Figure 20.13).
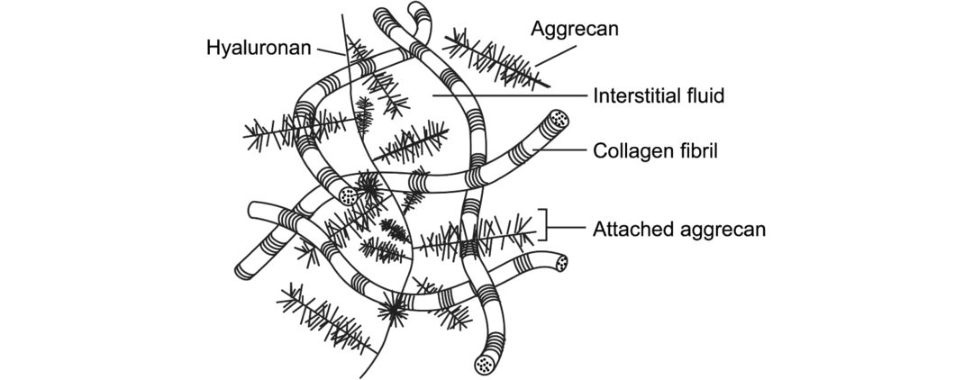
Figure 20.13 Collagen and proteoglycan arrangement in articular cartilage.
What’s the importance of water?
30% of the total water exists between the collagen fibres and this is determined by the negative charge of the proteoglycans which lie within the collagen matrix. Because the proteoglycans are bound closely, the closeness of the negative charges creates a repulsion force that must be neutralized by positive ions in the surrounding fluid. If the collagen network is degraded, as in the case of OA, the amount of water in the cartilage increases because more negative ions are exposed to draw in fluid.
Bearing in mind what we have discussed, what do you want to talk about next?
Growth plates.
Correct answer! Tell me about any classifications you know of specific to the growth plate.
Salter–Harris Type II fractures are the most common. When all types of Salter–Harris fractures are considered, the rate of growth disturbance is approximately 30%. However, only 2% of Salter–Harris fractures result in a significant functional disturbance.
The fracture types described later, also less common, include:
Type VI (injury to the perichondral structures – rare).
Type VII (isolated injury to the epiphysis only).
Type VIII (isolated injury to the metaphysis).
Type IX (an injury to the periosteum which could interfere with membranous growth).
I would not mention an y of this unless you get asked. You may end up speaking to an orthopaedic paediatric professor!
Draw me a growth plate.
[I drew a simple schematic like Figure 20.14] Zone I is the reserve or resting z one with low rates of proliferation, pr oteoglycan synthesis and typeIIB collagen. The zone is the truegerminal layer of the growth plate and Type IIcollagen synthesis is increased. Metabolic activity is high, with matrix synthesis approximately threefold compared to the proliferative zone; the main matrix componentssynthesized are types II and X collagenand aggrecan. [I got stopped at this point but will continue for completeness] Zone V is the zone of the matrix calcification as this calcified matrix becomes the scaffolding forbone deposition in the metaphysis. Zone VI is the junction of the growth plate with the metaphysis, the region where the transition from cartilage to bone occurs.
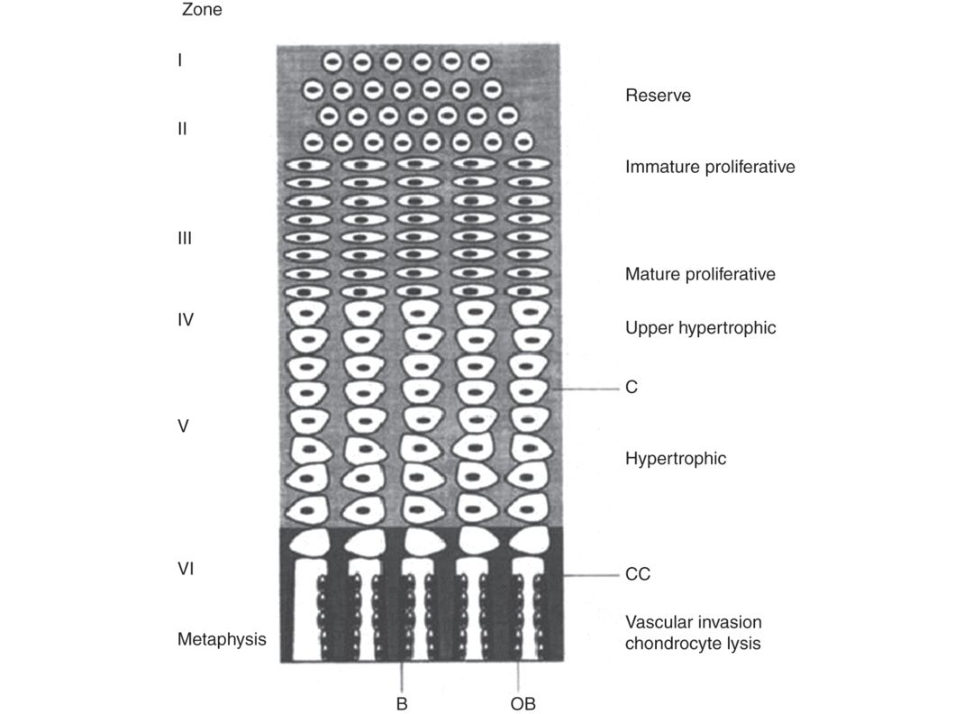
Figure 20.14 Diagram of a growth plate. B, bone; OB, osteoblast; CC, calcified cartilage; C, cartilage matrix.
A non-controversial standard textbook zone description would be: (1) reserve zone, (2) proliferating z one, (3) hypertrophic zone which can be subdivided into (a) maturation z one, (b) degenerative zone, (c) zone of provisional calcification, (4) metaphysis subdivided into (a) primary spongiosa and (b) secondary spongiosa.
How is the growth plate regulated?
The growth plate is regulated by growth factors, hormones and vitamins. They have significant effects on the growth plate chondrocytes, and IGFs retained in bone matrix are important in the regulation of bone remodelling.
Transforming growth factors (TGFs) have an important role in skeletal tissue, particularly certain members of the TGF-b gene family which includes the bone morphogenetic proteins involved in morphogenesis and regulation of endochondral ossification and in bone remodelling.
Key message5 Over 50 years ago, Urist made the key discovery that demineralized bone fragments implanted either subcutaneously or intramuscularly in animals induced bone formation. The extracellular matrix of bone contains substances that can stimulate new bone formation when implanted into extraskeletal sites in a host. Both BMP2 and BMP7 are approved for use in acute tibial fractures and complex non-unions. Both BMP2 and BMP7 have been shown to induce ectopic bone formation. At present, the use of BMP2 is preferred as studies suggest it may be more effective than BMP7 at promoting healing and it is also less costly. Platelet-derived growth factor plays a role in bone development and growth, being important in the regulation of bone and cartilage cells, although liti leis currently known of their role in normal endochondral ossification.
2. Structure and function of cartilage: (a) articular#
Introduction#
In practical terms this means a candidate has a 1 in 4 or 25% chance of being asked this topic.
As such the challenge for the Intercollegiate Board is to avoid asking the same questions each and every exam siting.
To make the subjectless predictable the topic focus can be changed mid viva onto different more detailed areas within this large topic such as proteoglycan structure.
The flip side is that regular examiners become more familiar with the topic and on occasion may ask esoteric questions to stretch you out to see if you are a possible score 7/8 candidate.
One word of caution with A -list topics is that candidates can continue to read further and further into a subject and end up concentrating on unfocused minutia details that have no relevance to any possible viva question likely to be asked.6 This is very different to reading extra details, but being able to apply these details into higher-order thinking to better answer a question.
Props#
Candidates may immediately be handed a laminated photograph of articular cartilage at the start of the viva or be asked a couple.
Structured oral examination question 1#
What are the functions of articular cartilage?
It reduces the coefficient of friction down to 0.0020, which is 30 times superior to the best performing artificial joint. These are the two main functions of articular cartilage, although some textbooks mention other minor roles.7 There is some controversy as to the relative importance of articular cartilage as a shock absorber. Again, we suggest stay simple and don’t mention this standpoint unless it comes up in discussion (very unlikely).8
Can you draw the histological appearance of articular cartilage? [Draw the structure of articular c artilag e.9] What are the articular cartilage layers?
Candidates should be able to draw the various layers of articular cartilage without hesitation Candidates may then be asked to explain why the layers appear like this, with reference to the three-dimensional ultrastructure.10 The histological appearance of articular cartilage is structured into zones ...: Take the examiner sequentially through the layers. Focus your discussion on (1) the differing orientation of type II collagen fibrils, (2) orientation and cellular features of the chondrocytes. 1. Superficial (tangential/ gliding) zone: 10–20% of thickness.
Collagen fibres are arranged parallel to the joint surface, forming a dense mat.
The most superficial partis called the lamina splendens,13 providing a very low-friction lubrication surface.
This dense collagen arrangement reduces leakage of proteoglycans from the articular surface and protects it from the effects of harmful enzymes.
Below this is a cellular layer with chondrocytes parallel to surface, flat-shaped, high density, many cells 1–3 thick.
This layer provides good resistance to shear forces due to tangential arrangement of collagen and provides the greatest tensile strength.
Low metabolic activity , hence low healing potential.
Thinnest layer with the highest concentration of collagen and water and the lowest concentration of pr oteoglycan.
Water can be squeezed out of the layer to help create lubrication.
May function as a barrier to the passage of large molecules from the synovial fluid.
2. Middle (transitional) z one: 40–60% of thickness.
Collagen fibres arranged obliquely at right angles to each other.
Plentiful concentration of pr oteoglycan.
Chondrocytes arranged in random orientation round shape, progressively lower density and fewer cells.
Transitional z one between the shearing forces of the surface layer and resistance to compression in the deep layer.
3. Deep (radial) zone: 30% of thickness.
Provides resistance to compression.
Collagen fibres vertically arranged (perpendicular to articular cartilage) cross the tidemark and are anchored to subchondral bone.
Highest concentration of pr oteoglycans.
Chondrocytes spherically arranged in vertical columns.
Collagen fibres largest diameter.
Lowest water content.
4. Calcified zone.
This separates the cartilage tissue from the underlying subchondral bone.
Anchor for the various layers.
Collagen type X and hydroxyapatite crystals anchor articular cartilage to subchondral bone.
Forms a barrier to blood vessels supplying subchondral bone.
Matrix mineralization in the calcified zone allows gradual transition of mechanical properties between cartilage and bone.
Tidemark
The junction between the deep and calcified zone is called the tidemark.
As a candidate is describing the histological structure of articular cartilage an examiner may start to probe/interrupt/take over14.
What is the tidemark? What attaches to the tidemark?
It is cell-free and represents a calcification fr ont. The collagen fibres in the deep zone penetrate through the tidemark in to the calcified cartilage to provide structural stability for articular cartilage on the subchondral bone.
What is the composition of articular cartilage (Table 20.3)?
The wet weight proportions of articular cartilage are water (65–80%), collagen (10–20%), proteoglycans (10–15%), chondrocytes (5%) and other matrix components such as adhesives and lipids. The fibres account for 10–20% and are almost exclusively Type II collagen. Or more simply, articular cartilage is mainly composed of chondrocytes, water, Type II collagen, proteoglycans and a variety of matrix proteins. If you have to talk about dry weight mention that collagen accounts for 40–70% of the dry weight and that approximately 90% of the dry mass of articular cartilage is made up of proteoglycan aggrecan, type II collagen and hyaluronan.
What are the contents of articular cartilage?
Chondrocytes16 Derived from mesenchymal stem cells, chondrocytes produce and maintain EC Mand are the main cell type of articular cartilage. Deeper cartilage zones contain no chondrocytes. There are distinct subpopulations of chondrocytes in the different zones of cartilage whose properties differ in terms of their morphology, metabolism, and their response to cytokines. Water Up to 80% of the extracellular matrix. Collagen About 10–20% wet weight, 60% dry weight. The main collagen in articular cartilage is type II accounting for 90–95% of the collagen. Types II, IX and XI form a mesh that serves to trap proteoglycans, providing for stiffness and strength. Type VI helps chondrocytes adhere to the matrix. Type XI constrains the proteoglycan matrix.
Type X is only found near the calcified zone.
Proteoglycans
Proteoglycans are complex macromolecules composed of a protein core to which many glycosaminoglycan side chains are attached.
Proteoglycans trap and hold water, providing the tissue with its turgid nature that resists compression.
They are secreted by chondrocytes.
The most common glycosaminoglycan in articular cartilage is chondroitin-sulpha te (two subtypes.
Chondroitin-4-sulpha te is the most abundant, decreases over the years, age.
Glycosaminoglycan can link to a protein core by sugar bonds to form a proteoglycan aggrecan (see
Figure 20.14).
A proteoglycan aggrecan has three globular domains, G1, G2 and G3.
Aggrecan molecules do not exist in isolation within the extracellular matrix.
Each aggregate is composed of a central filament of hyaluronic acid, up to 100 aggrecan molecules radiating from it.
PG aggregation promotes immobilization of the PG swithin the fine collagen meshwork.
PG shave an average lifespan of 3 months, elasticity to the tissue.
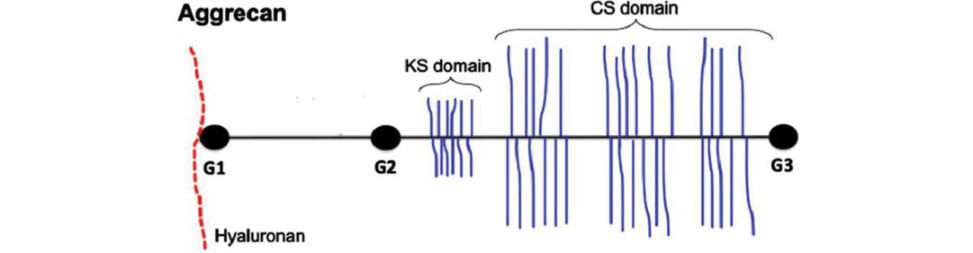
Figure 20.15 Proteoglycan aggrecan. A proteoglycan aggrecan has three globular domains, G1, G2 and G3.
What is the structure of a proteoglycan molecule?17,18
This involves differentiating between a proteoglycan aggregate and proteoglycan aggrecan molecule (Figure 20.14). As always, rehearse your drawing with dialogue as many times as needed to obtain a smooth, polished flow.
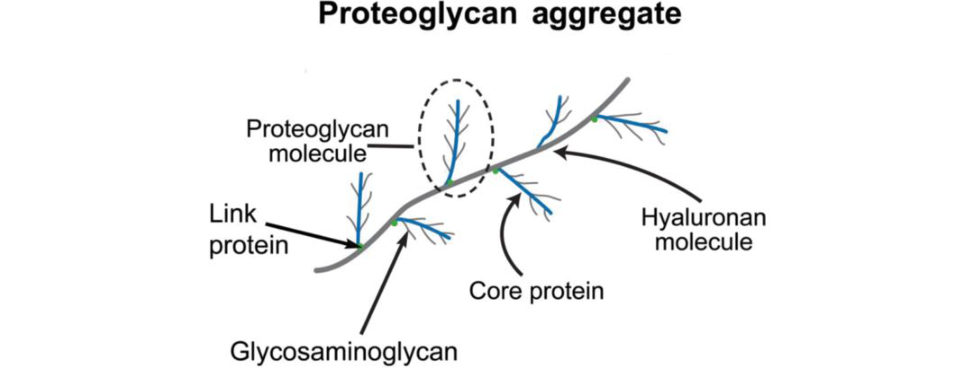
Figure 20.16 Candidate drawing of proteoglycan aggregate.
How does collagen synthesis take place? (Figure 20.17.)
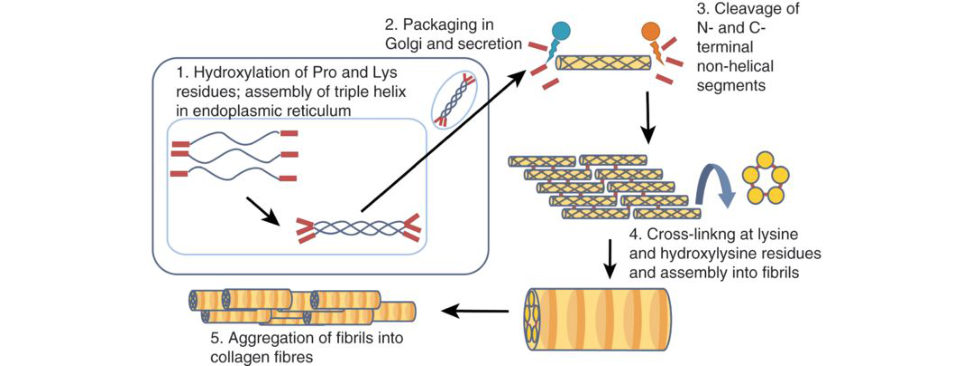
Figure 20.17 Collagen synthesis.
This question 19 may be asked as part of the main viva theme or as an add-on if a candidate has trail-blazed through previous viva questions and is on for a score 8. The secret is to try and simplify a complex process often poorly described in books. Procollagen is synthesized by a series of steps within the endoplasmic reticulum of cells such as fibroblasts.
Collagen monomers are then covalently cross-linked with each other after certain residues are oxidized by lysyl oxidase.
Table 20.3 Constituents of articular cartilage.
Cells (chondrocytes) (5%)
Extracellular matrix (95%) Fibres Collagen (10–20%) Type II, IX, XI
Almost exclusively Type II Type VI, X
Elastin
Ground substance Water (65–80%)
Proteoglycans and glycosaminoglycans (10–15%)
Glycoproteins
Degradative enzymes (matrix metalloproteinases)
Steps that occur INSIDE the cell
Synthesis of pro-alpha chain.
Hydroxylation of selected proline and lysine residues.
Glycosylation of selected hydroxylysine residues.
Self-assembly of three pro-alpha-chains into triple helix.
Procollagen triple helix formation.
Then extrusion of procollagen from the endoplasmic reticulum/Golgi compartment into secretory vesicles and then secretion in to extracellular matrix.
Steps that occur OUTSIDE the cell
Cleavage of propeptides. Once secreted, procollagen peptidases remove the N-terminal and C-terminal propeptides.
Self-assembly into fibril.
This enzyme allows hydroxyl groups on lysines and hydroxyl lysines to be converted into aldehyde groups that covalently bond between tropocollagen molecules to form a collagen fibril.
Closely related to synthesis is the structure of collagen and the line of questions may continue on with this subtopic.20
What is the structure of collagen (Figure 20.18)?
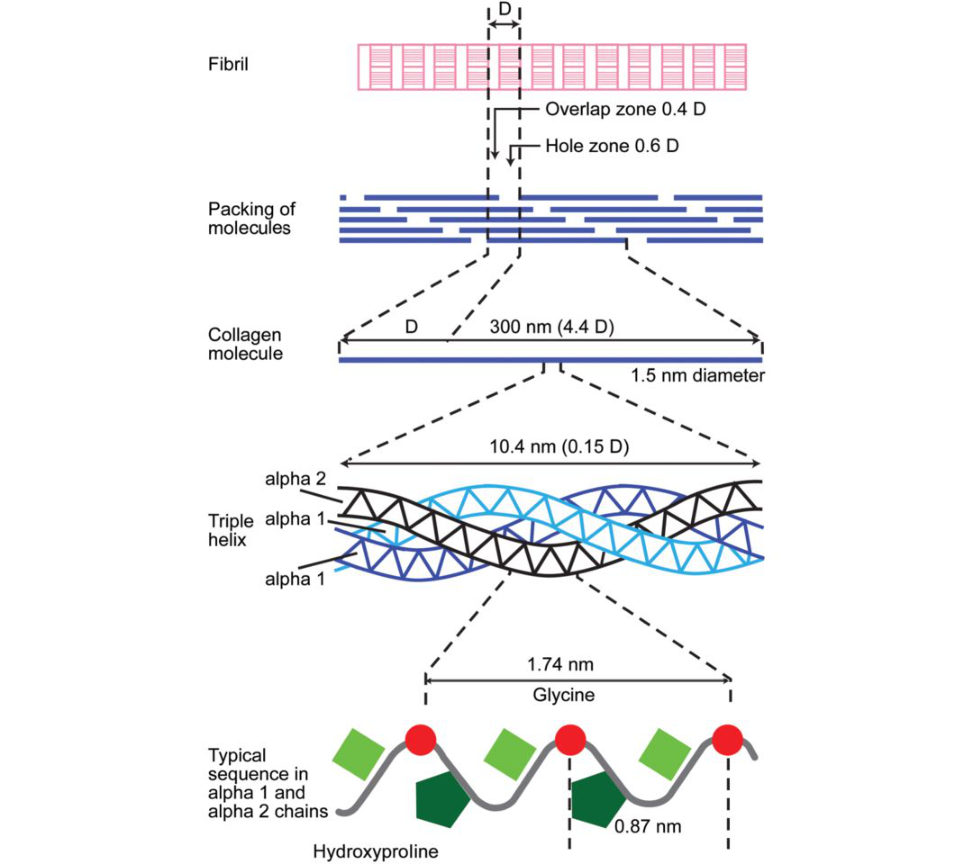
Figure 20.18 Hierarchical structure of collagen ranges from the amino acid sequence, tropocollagen molecules, collagen fibrils to collagen fibres.
In articular cartilage collagen is mainly type 2.
What is the function of matrix glycoproteins?
These interact with collagen fibrils and stabilize the matrix framework.
They help chondrocytes bind to the macromolecules of the matrix.
Matrix glycoproteins are much smaller than aggrecans.
More simply, they act as a tissue glue binding to various matrix components.
What about matrix metalloproteinases?
These degrade collagen and proteoglycan aggregates as part of the normal turnover of the matrix.
What do we mean by tensegrity architecture?
Water is atir acted and retained in articular cartilage by the ionic pressure created by the high level of negative charges on glycosaminoglycan (GAG) chains on proteoglycan molecules. The amount of water present in cartilage depends on the concentration of pr oteoglycans and the stiffness and strength of the collagen network. If the collagen network is degraded, as in the case of OA, the amount of water in the cartilage increases because more negative ions are exposed to draw in fluid. Candidates that do not understand this concept particularly well may become trapped quite easily by the examiners (just like water gets trapped by proteoglycans).
Tell me about matrix metabolism.
Chondrocyte regulators include hormones, cytokines and growth factors. Enzymes include aggracanase and metalloproteinases degrade the matrix. The chondrocytes also make inhibitors of these enzymes called tissue inhibitor of metalloproteinases (TIMP).
What do we mean by the term matrix region?
An alternative zonal classification is by the matrix regions.
Matrix regions differ in their collagen content, collagen fibril diameter.
There are three regions.
1. The pericellular matrix is a thin layer adjacent to the cell membrane, completely surrounding the chondrocyte.
The pericellular matrix region may play a functional r ole to initiate signal transduction within cartilage with load bearing.
2. The territorial matrix surrounds the pericellular matrix, it is composed mostly of fine collagen fibrils.
The territorial matrix may protect the cartilage cells against mechanical stresses.
3. The interterritorial region is the largest of the three matrix regions.
This region is characterized by randomly oriented bundles of large collagen fibrils and large amounts of proteoglycans.
Structured oral examination question 2#
Articular cartilage changes, ageing versus osteoarthritis is more of a section 3 (pathology) topic but there will be a large overlap, section 2 material (structure.
Describe the changes in articular cartilage with ageing.
Articular cartilage undergoes significant structural, matrix composition and mechanical changes with age. With increasing age there is an age-related decline in the ability of chondrocytes to maintain the tissue Chondrocytes become less responsive to the proliferative and anabolic effects of growth factors. There is a marked increase in the formation of advanced glycation end-pr oducts (AGEs).
Describe the changes in articular cartilage with osteoarthritis. What pathological processes are involved in the development of osteoarthritis?
The process can be divided into three overlapping stages: (1) cartilage matrix damage, (2) chondrocyte response to tissue damage (3) decline of the chondrocyte synthetic response with progressive loss of tissue. In the early stages of disease, loss of proteoglycan is reversible, whereas at later stages there is irreversible loss. The earliest visible change is loss of collagen integrity resulting in tissue fibrillation and increased water content. There may be areas of full-thickness cartilage loss with the subchondral bone exposed and often sclerotic.
Microscopic appearances include surface irregularities and erosions, deterioration of the tidemark, fissuring and damage to the cartilage structure.
Overall, the collagen content is maintained but the presence of collagenase disrupts its organization and orientation.
Have an answer rehearsed.
What are the management options for osteoarthritis?
Surgical management may include joint debridement, osteotomy, arthroplasty and arthrodesis.
What are the options for treating an articular cartilage defect?
There are three main types of cartilage injury: (1) superficial matrix disruption, (2) partial thickness defects and (3) full-thickness defects. These defects can elicit a repair response due to access to marrow cells; however, they are typically filled with fibrocartilage This type of repair tissue is much weaker than hyaline cartilage and displays poor long-term performance due to poor compressive strength and durability.
What are the options for treating a symptomatic focal articular cartilage defect in the medial femoral condyle of the knee of a young active patien t?21
Appropriate management of an articular cartilage defect in a younger patient is often very challenging. Current treatment options f all into three broad categories: 1. 2. Substitution options (osteochondral autograft transfer system [OATS], osteochondral allograft).
3. Cell-based, biological replacement options autologous chondrocyte implantation [A CIs tem cell therapy, tissue engineering).
Marrow stimulation techniques such as abrasion arthroplasty, causing bleeding within the cartilage defect that leads to fibrin clot formation.
Undifferentiated MSCs from the bone marrow migrate into the defect, proliferate and differentiate into fibrochondrocytes.
The repaired articular cartilage generally fails to replicate the structure, composition and function of normal articular cartilage.
OATS is recommended for smaller lesions, lesions in high-demand athletes, and lesions with associated bone loss.
Microfracture is suited for medium-size defects with litile or no bone loss in lo wer-demand older patients.
complications results, especially if in the adult pathology viva, aiming for score 8.
Structured oral examination question 3#
As viva question 1 initially, what are the functions of AC, describe the layers of AC.
What are the biomechanical properties of cartilage?
Cartilage is a biphasic, viscoelastic and anisotropic material demonstrating both creep and stress relaxation.
What do you mean by viscoelastic?
A viscoelastic material will exhibit a time-dependen t behaviour when subjected to a constant load or constant deformation.
What are the properties of a viscoelastic material?
A viscoelastic material demonstrates creep and stress relaxation. Creep is time-dependen t deformation of amate rial under constant load that is below its yield strength. Stress relaxation is the decrease in stress required to maintain constant strain over time. Viscoelastic materials display four characteristics: 1. 2. Stress relaxation. 3. Hysteresis. 4. Strain rate-dependent mechanical properties. It is due to the fact that materials do not perfectly obey Hooke’s law. A viscoelastic material is harder to deform when loading than unloading.
Viscoelastic materials are stiffer, tougher and stronger when loaded at a faster rate (higher strain rate) because there isless time for them to strain.
Can you drawout the graphs of creep and stress relaxation ( Figures 20.19 and 20.20)?
Yes, but my mind has gone blank.
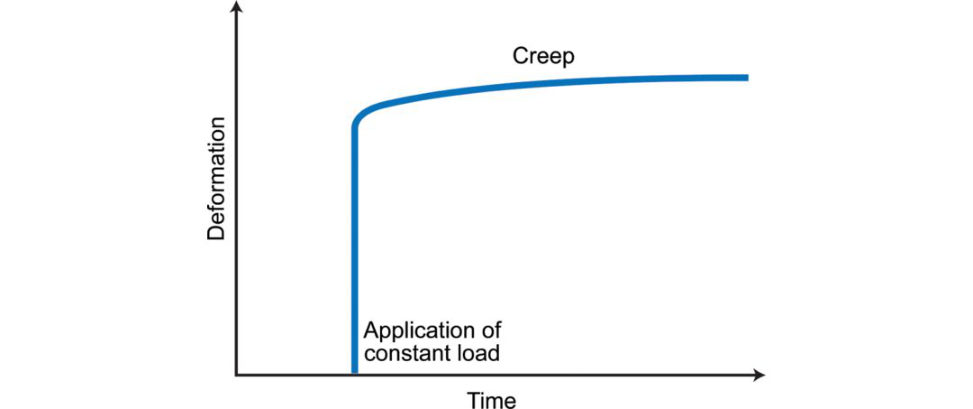
Figure 20.19 Creep. Continuous deformation overtime in response to constant load.
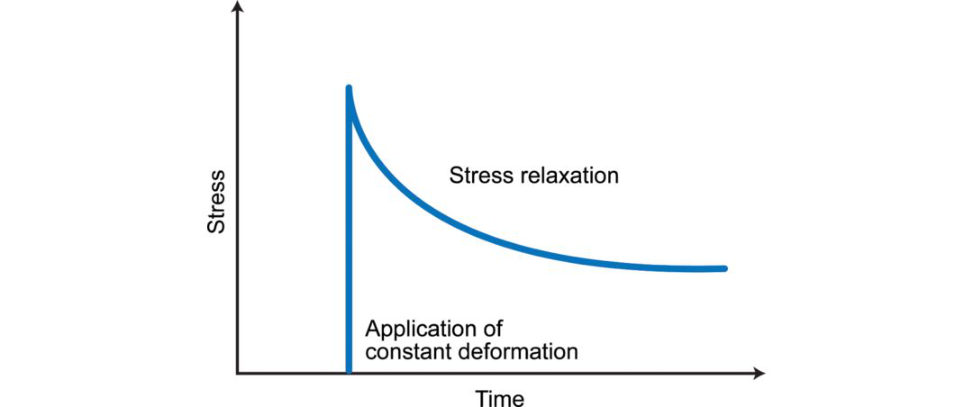
Figure 20.20 Stress relaxation. Time-dependen t decrease in stress required to maintain strain.
What about hysteresis and strain-dependent mechanical properties ( Figures 20.21 and 20.22)?
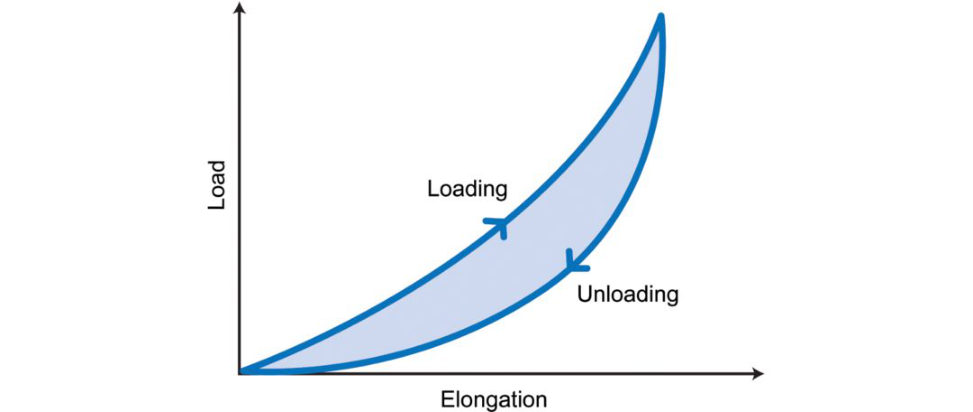
Figure 20.21 Hysteresis. Strain energy loss as heat due to internal friction between loading and unloading.
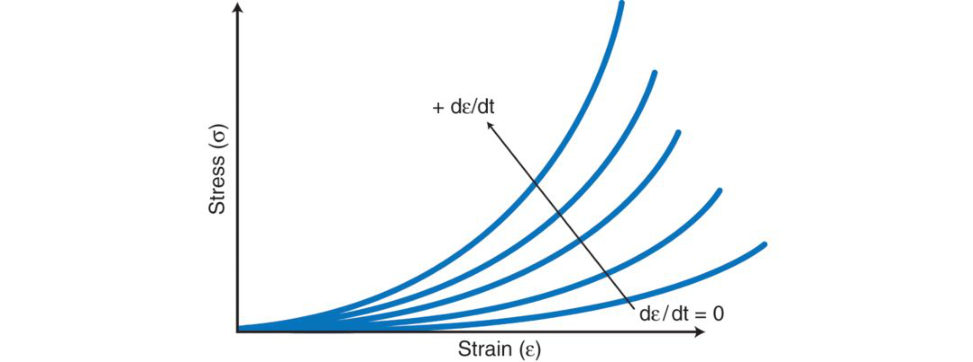
Figure 20.22 Time-dependent strain behaviour. Stress is proportional to strain rate.
No, sorry. These are predictable questions. The vi vais heading for a score 4 or at best 5.
What about articular cartilage permeability with compression?
Articular cartilage permeability decreases non-linearly with compression. There are two causes for this nonlinear effect. As the tissue is compressed: (1) The water content or porosity is reduced. (2) The density of the negative charges on the proteoglycans is increased.
There is a direct relationship between permeability and water content and an inverse relationship between permeability and proteoglycan content.
This is in the score 8 zone for candidates.
How does the internal architecture of articular cartilage relate to its biomechanical properties?
This fluid support is not uniform between the different zones of the tissue, with the superficial zone demonstrating the highest support (95%) compared to the deep zone (70% of applied load). However, dissolved electrolytes together with fixed charges of the solid matrix bring about mechanoelectrochemical phenomena adding to the load bearing of the tissue and described as a third phase. Rate of creep is governed by the rate at which fluid is forced out from the tissue, which, inturn, is governed by the permeability and stiffness of the por ous-permeable, collagen–proteoglycan solid matrix.
Structured oral examination question 4#
What are the properties of articular cartilage?
Cartilage is avascular, aneural anda lymphatic.
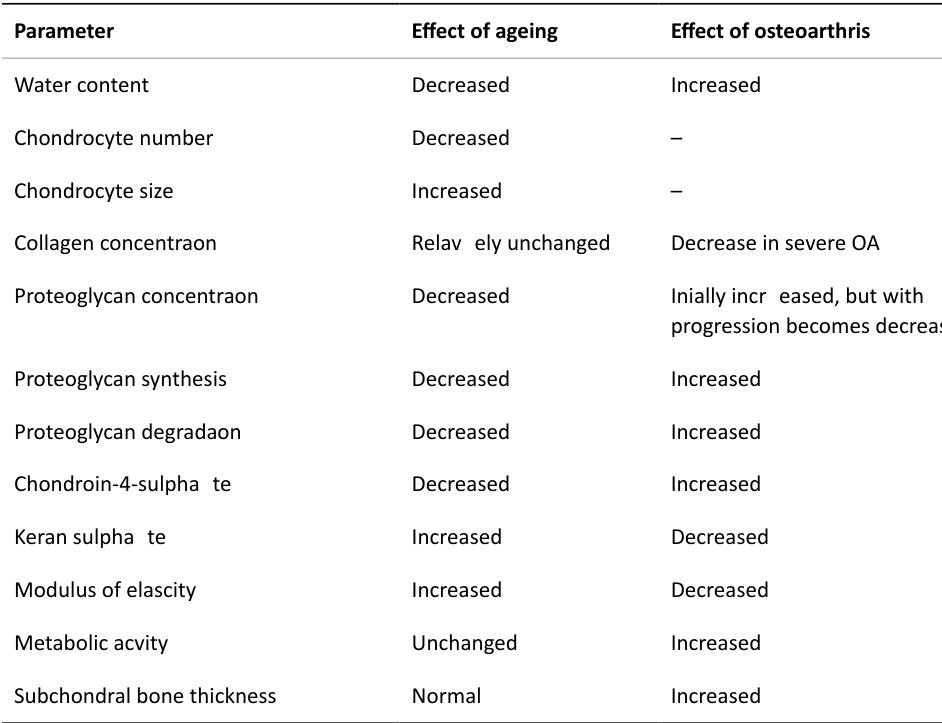
What are the articular cartilage changes that occur with ageing and osteoarthritis ( Table 20.4)?
Perhaps best remembered as changes occurring in the composition of articular cartilage, i.e. water, chondrocytes, collagen and proteoglycans.
What are the changes that occur with osteoarthritis?
There may be areas of full-thickness cartilage loss with the subchondral bone exposed and often sclerotic. The three main areas to consider with OA are (1) macroscopic changes, (2) microscopic changes and (3) synovial joint changes. Synovial joint changes include changes in periarticular musculature, and in articular and periarticular tendons and ligaments. There is synovial inflammation, joint capsule hypertrophy, meniscal degeneration thickening of subchondral bone and formation of osteophytes.
What is the relationship between ageing and osteoarthritis?
During ageing, an imbalance between the catabolic and anabolic processes occurs. Age-related loss of the ability of chondrocytes and tissues within the E CM to maintain a homeostasis between these pathways leads to a procatabolic state favouring matrix degradation.
Despite ageing being a significant risk factor for OA, not all aged joints develop the disease.
What are advanced glycation end products (AGEs)?
The effects of AGEs formation include: Modification of type II collagen by cross-linking of collagen molecules: increasing stiffness and britileness, increasing susceptibility to fatigue failure. The combination of changes in the mechanical properties of the cartilage tissue, the pro catabolic environment, and the innate low capacity for self-repair leads to a tissue that is unable to withstand normal joint loading, which gradually leads to total joint failure.
What about the use of hyaluronic acid? What is the evidence for its use in osteoarthritis?
HA is a macromolecule found naturally within cartilage with reduced levels found in joints where osteoarthritis is present. HA injection in to degenerative joints has been shown to improve function and to provide good pain relief in knees.
What about PRP. Does this work?
PRP can be defined as the volume of the plasma fraction from autologous blood with platelet concentration above baseline. There have been early encouraging clinical results shown inactive patients with early knee OA. NICE guidelines have suggested although there are no concerns regarding safety of PRP in knee osteoarthritis, the evidence for efficacy is weak.
What would you say to a colleague who has listed 10 patients with early knee osteoarthritis for PRP injections?
This is a delicate situation. I would discreetly suggest PRP injections are quite expensive to perform and can be problematic in blocking upo per ating list capacity. They perhaps should be used more selectively rather than as a first-line standard treatment for early OA as the evidence for efficacy is fairly weak. Table 20.4 Osteoarthritis versus ageing.
2. Structure and function of cartilage: (b) meniscus#
Introduction#
For a basic 6 the candidate should learn the usual core questions on meniscal structure, function, biomechanics and hoops tresses.
Candidates aiming to score a 7 or 8 will need to put in some detective work to uncover the higher-order thinking and judgement questions that follow on from this.
There are several possible routes into the topic.
Structured oral examination question 1#
1 . Can you talk me through this picture (Figure 20.23)?
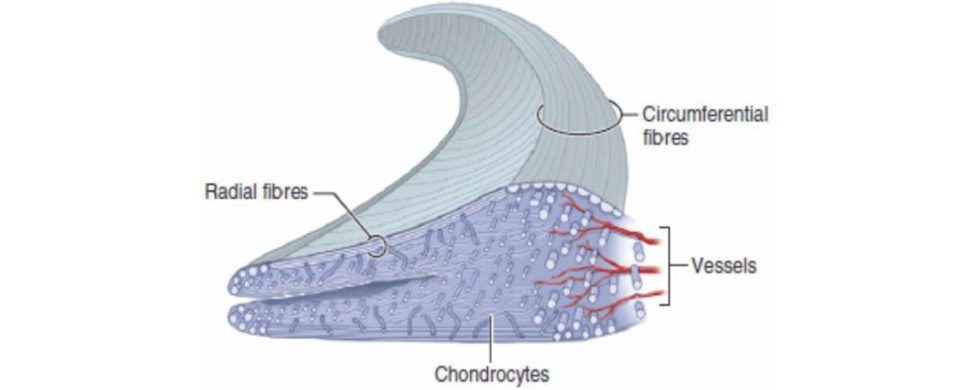
Figure 20.23 A cross-section of the meniscus showing the radial and circumferential collagen fibre orientation. Also shown are blood vessels penetrating the peripheral one-third of the tissue and location of chondrocytes.
No marks for recognizing the menisci as the examiners have already told you this. EXAMINER : Can you drawout a meniscus for me concentrating on the collagen arrangement within the menisci (Figure 20.24)?
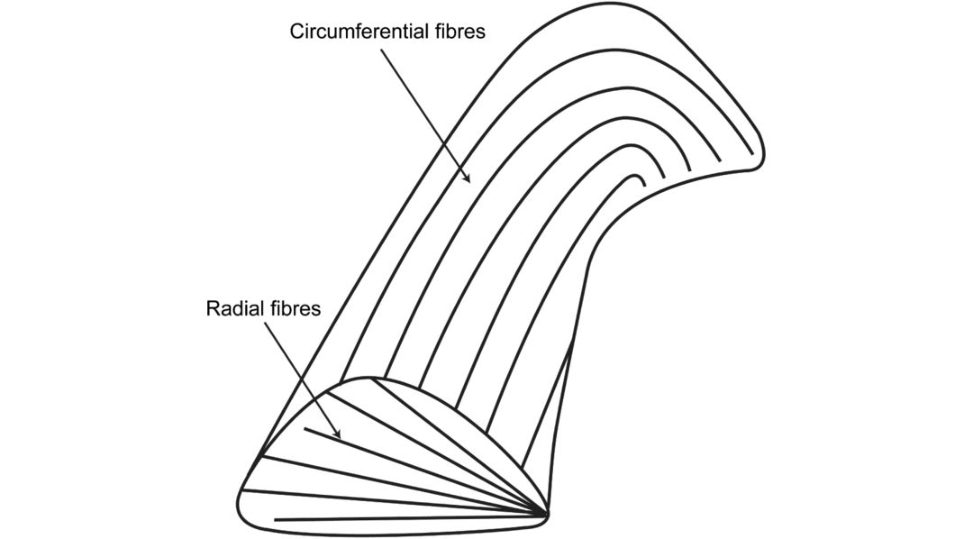
Figure 20.24 Candidate 20-second diagram of meniscal structure.
3 . EXAMINER : [Birdeye nest picture of the meniscus shown] Can you identify the unlabelled structures on the diagram (Figure 20.25)?
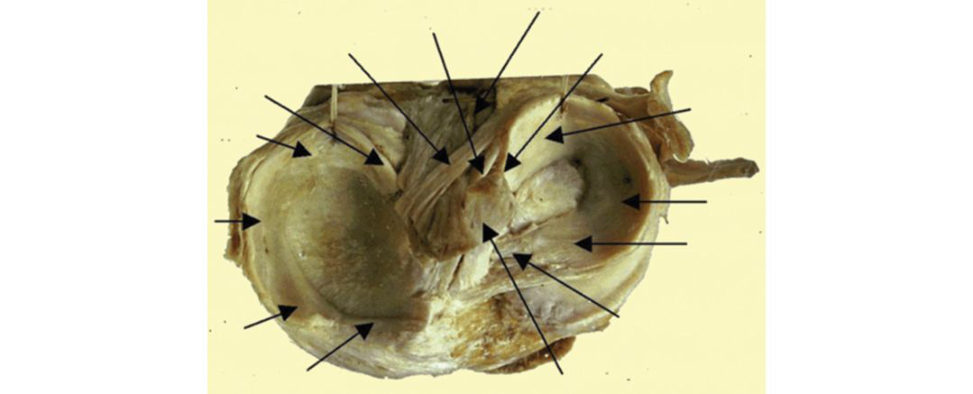
Figure 20.25 Unlabelled axial view of a right tibial plateau showing sections of the meniscus and their relationship to the cruciate ligaments.
This diagram could be shown either unlabelled (Figure 20.25) or labelled (Figure 20.26).
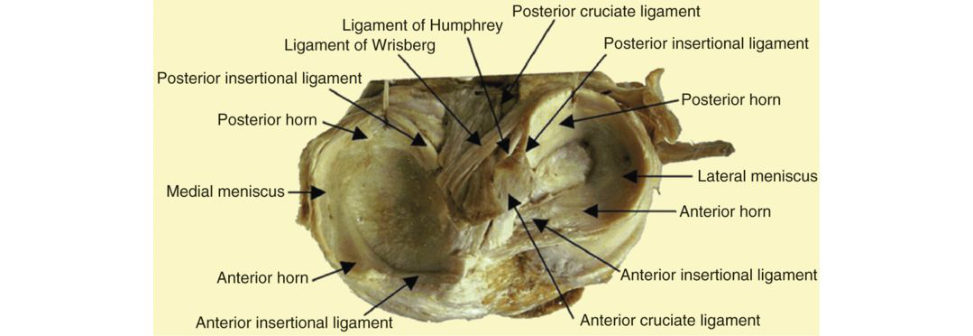
Figure 20.26 Labelled axial view of a knee showing sections of the meniscus and their relationship to the cruciate ligaments.
4 . EXAMINER : [Birdeye nest picture of the meniscus shown (Figure 20.26)] Describe what you see.
A birdeye nest picture of the meniscus generally leads to a more focused initial testing of meniscal anatomy.23 Candidates need to avoid stumbling around describing the diagram.
Describe the anatomy of the medial and lateral meniscus (Figure 20.27).
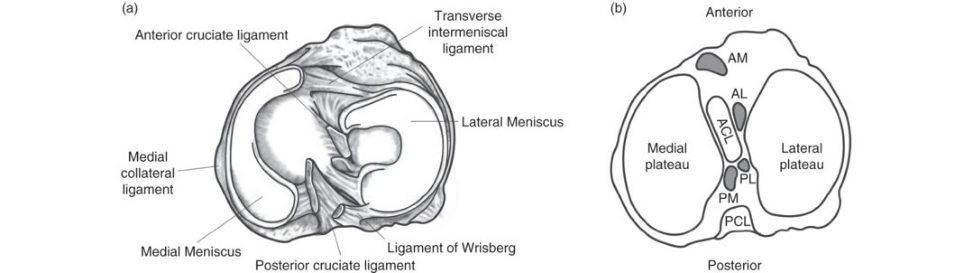
Figure 20.27 (a) Anatomy of the meniscus viewed from above. (b) Axial view of a right tibial plateau showing sections of the meniscus and their relationship to the cruciate ligamentAL, anterior horn lateral meniscus; AM, anterior horn medial meniscus; PCL, posterior cruciate ligament; PL, posterior horn lateral meniscus; PM, posterior horn medial meniscus.
They are triangular in cross-section, with an average thickness of 3–5 mm. The innermost border tapers to a thin free edge. The superior surfaces of menisci are concave, enabling effective articulation with their respective convex femoral condyles.
Lateral meniscus
The lateral meniscus is O-shaped and covers a larger area than the medial meniscus (80–85% of the lateral tibial plateau).
It is more constant in size between the anterior and posterior horns.
The anterior horn is attached to the tibia anterior to the intercondylar eminence.
The posterior horn is attached posteriorly to the intercondylar eminence of the tibia anterior to the posterior horn of the medial meniscus.
only a loose attachment to the joint capsule that is interrupted posteriorly by the popliteus tendon.
Occasionally a few fibres of the popliteus are attached to the posterior convexity of the LM.
Medial meniscus
The medial meniscus is C-shaped and covers 60–65% (~two-thirds) of the medial plateau.
The posterior horn is significantly wider than the anterior horn.
It has a larger anterior–posterior dimension than width.
The anterior attachment is approximately 7 mm anterior to the ACL attachment, inline with the medial tibial tubercle.
The posterior attachment to the posterior intercondylar fossa of the tibia anterior to the PCL attachment.
The MM attaches to the deep part of the MC Land to the capsule around its periphery via the coronary (meniscotibial) ligament.
What are the ligaments associated with the meniscus?
A number of important ligaments are associated with the menisci. Both menisci have firm attachments to the tibial surface at their anterior and posterior horns via the insertional ligaments, which are very strong and stiff. The anterior meniscofemoral ligament (ligament of Humphrey) passes in front of the PCL, the posterior meniscofemoral ligament (ligament of Wrisberg) passes behind the PCL.
What are the functions of the meniscus?
The function of the meniscus includes: Load transmission (bearing). Shock absorption. Lubrication. Distributes synovial fluid throughout the joint. Contributes to joint stability. Prevents hyperextension. Assists in gliding motion.
What are the biomechanical functions of the meniscus?
The meniscus serves several important biomechanical functions. The y contribute to load transmission, stability, nutrition, joint lubrication and proprioception. In most textbooks menisci are described as functioning as shock absorbers in the knee. However, recent evidence has suggested this might not actually be the case.24
What about the load transmission functions of the meniscus?
Inextension, the posterior menisci bear 50% of the compressive load compared to 85% at 90° flexion.
How does this lead to the development of osteoarthritis?
Medial meniscectomy results in a 50–70% reduction in femoral condyle contact area and a 100% increase in contact stress.
So why is lateral meniscectomy worse than medial meniscectomy?
The medial tibial plateau is slightly concave, giving some degree of congruency with the curved femoral condyle. However, with the lateral tibial plateau this is convex, causing a natural tendency to point loading.
How are menisci viscoelastic? What do you mean?
The elas tic quality or solid phase of the meniscus is due to its collagen–proteoglycan structure, whereas the viscous or fluid phase is due to its permeability and water content. Under compression, meniscal permeability determines the rate at which fluid is extruded. Articular cartilage, tendons and ligaments, intervertebral discs and menisci display viscoelastic properties.
How does the meniscus assist in lubrication?
The menisci serve to increase the congruity between the condyles of the femur and tibia; they contribute significantly to overall joint conformity. Like shock absorption, the reis no firm evidence of menisci involvement in knee joint lubrication.
What else?
There is fluid exudation across meniscal surfaces.
How does the meniscus function in proprioception?
The menisci provide a feedback mechanism for joint position sense. Neural elements have been identified within the meniscal tissue.
What are hoop stresses in the meniscus?
Candidates would be expected to know this to score a 6. The arrangement of collagen fibres in the meniscus convert compressive forces into a radially directed force, which is distributed and resisted as hoop stresses within the meniscus. The radial fibres act as intrasubstance tier ods to provide structural rigidity and resist against longitudinal spliting of the circumferential collagen bundles. The development of hoop stresses within the meniscus depends on intact anterior and posterior attachments. Hoop stress also relies on the conversion of axial load into tensile strain through intact longitudinal-orientated collagen fibres. No matter how many times I described hoops tresses in the meniscus, for some reason I never appeared very convinced that I knew what I was talking about.
What is the blood supply of the meniscus?
Branches from these vessels give rise to a perimeniscal capillary plexus within the synovial and capsular tissues of the knee joint. Approximately 10–30% of the periphery of the MM and 10–25% of the LM are relatively well vascularized. The remaining portion of each meniscus (65 –75%) receives nourishment from synovial fluid via diffusion or mechanical pumping (i.e. joint motion).
What factors influence your decision whether to repair a meniscal tear or resect?
Location oft ear
Red–white zonal tears have a reasonable chance of healing, whereas tears in the white zone (3–5 mm from the periphery) are unlikely to heal.
As a general rule, red–red should, white–white won’t and red–white might.
Age of tear
Fresh tears are more likely to heal than older tears.
Age of the patient
Meniscal repairs in older patients (> 30 years) have a significantly.
Tear pattern
Displaced bucket-handle tears should be repaired on an urgent basis whenever possible.
Repetiv e compression and abrasion in the displaced position will lead to macerated and damaged tissue and preclude repair.
Peripheral, vertical longitudinal tears are ideal for repair in the red–red or red–white zone.
Complex bucket-handle tears, flap tears, degenerative and radial tears often perform poorly with repair and are more often amenable to excision.
Horizontal cleavage tears are not repairable, and the unstable leaf should be excised, leaving up to
3 mm of the leaf.
Ligament stability
A meniscal tear should not be repaired in an unstable ACL-deficient knee.
What percentages of tears are amenable to repair?
This depends to a certain extent on the expertise of the surgeon, but a figure around 15% is generally accepted. If acute and/or a relatively well-preserved joint, consider repair.
How do radial and longitudinal tears differ?
A radial tear disrupts the continuity of the circumferential fibres interfering with the distribution of hoops tresses within the meniscus. This is the equivalent of a total meniscectomy. They occur due to fracture of the weak radial tie fibres.
If radial tears interfere so much biomechanically with hoop stress distribution, why do we not repair more of them?
There may be a case for attempting repair in a young active person, especially if the lateral meniscus is involved or if the tear extends to the periphery, but success rates can be unpredictable, and the patient needs to be partial w eight-bearing for at least 6 weeks following the repair.
What is a meniscal root tear?
A meniscal route tear is where the tear extends to either the anterior or posterior meniscal root attachment to the central tibial plateau.
Biomechanically?
Loss of the root attachment impairs the ability of the meniscus to resist hoop stress when the tibiofemoral joint is loaded.
What else?
There are two main types of meniscal root tears. The first type is low-energy tear occurring in older patients with pre-existing osteoarthritis.
What is the role of meniscal replacement?
There should be only early or minimal chondral changes, normal limb alignment and a stable knee. Cadaveric menisci are matched by size and site and are implanted by various techniques that include a free soft -tissue allograft implantation, separate anterior and posterior bone plugs and bone bridges.
A meniscal allograft may partially replicate the normal meniscus function and significantly reduce pain and improve knee function.
Structured oral examination question 2#
Meniscus – draw, structure, function contents, hoop stresses.
Similar to question 1, but meniscal contents need to be described.
What are the contents of the meniscus?
The meniscus is a dense extracellular matrix (ECM) composed mainly of water (72%) and collagen (22%), interposed with cells. The remaining dry weight is composed of proteoglycans, non- collagenous proteins and glycoproteins (Figure 20.28). The cells of the meniscus are called fibrochondrocytes because they appear as a mixture of fibroblasts and chondrocytes. Cells in the more superficial layer of the meniscus are more fibroblastic spindle-shaped while those cells located deeper in the meniscus are more chondrocytic o void- shaped (Figure 20.29). The outer region of the meniscus is composed of type I collagen while the inner region is 60% type II and 40% type I.
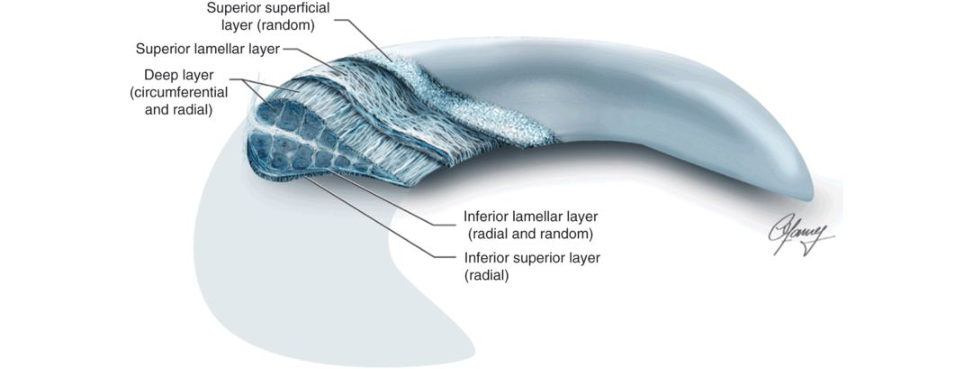
Figure 20.28 Complex collagen arrangement in meniscus. The outer region is the outer third of the meniscus; the inner region is the inner two-thirds of the meniscus; the superficial region is the surface of the meniscus.
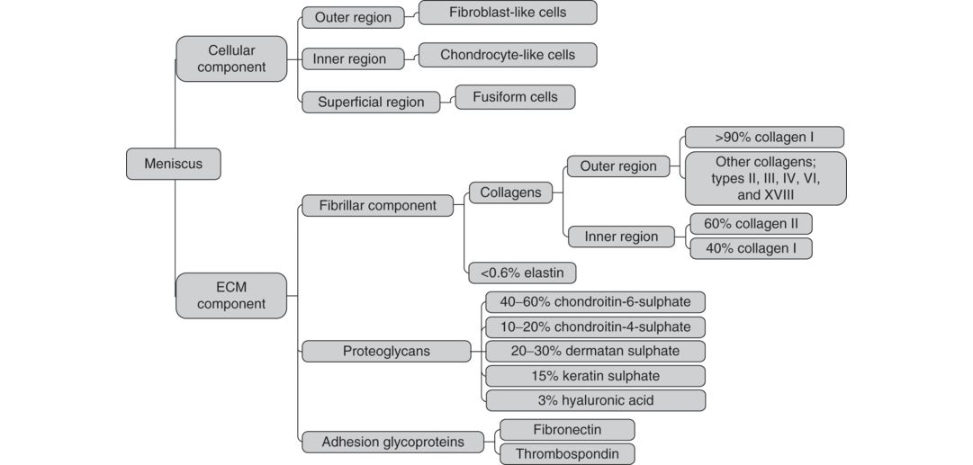
Figure 20.29 The complex composition of the meniscal cellular and meniscal extracellular matrix (ECM) components.
Structured oral examination question 3 (Figure 20.30)#
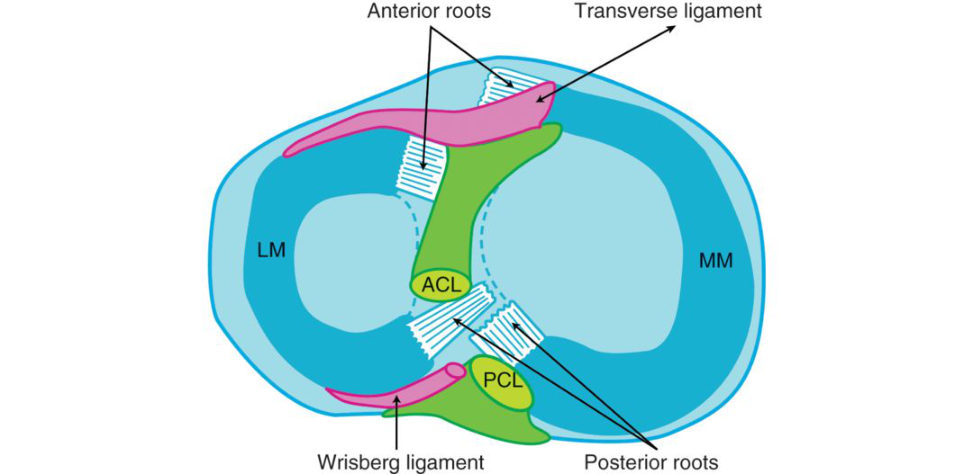
Figure 20.30 Birdeye picture of the tibia.
Draw me the top of the tibia! Label the structures. How are the menisci attached?
What is the function of menisci – load transfer, shock absorption, hoops tresses, etc.?
How do menisci get injured?
Candidates wanting to score well need to get through this opening test material in a timely fashion to set themselves up for the later, more difficult score 7/8 questions.
What do we mean by hoop stresses?
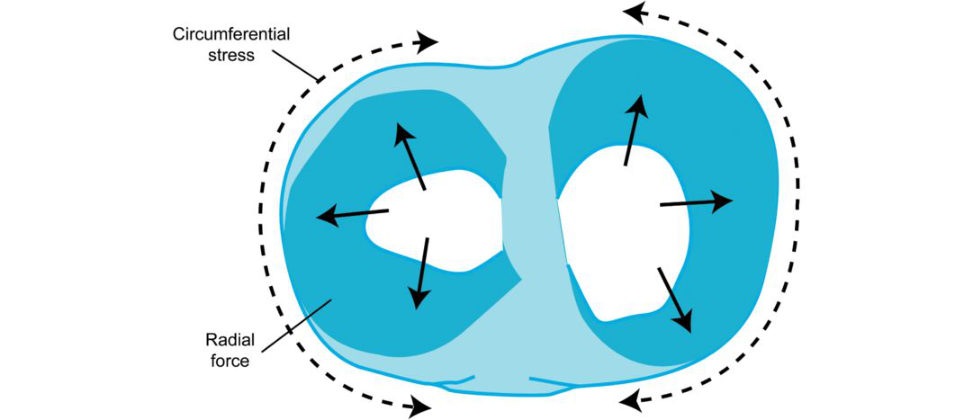
vertical compressive forces are converted into a radially directed force that is taken up as circumferential hoops tresses within the meniscus (Figure 20.31).
Can you draw this for me? Can you explain this free body diagram of forces acting on the meniscus ( Figure 20.32)
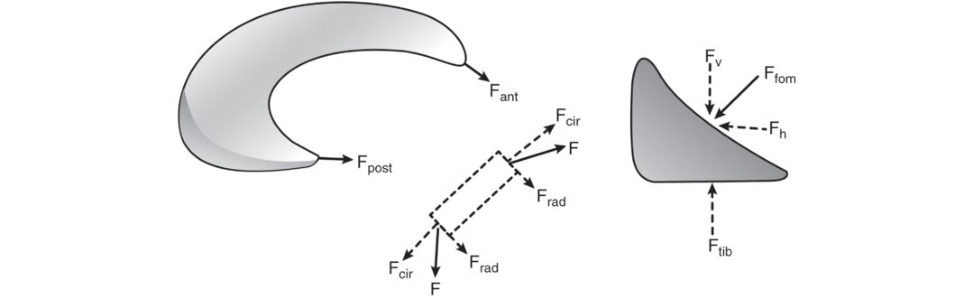
As the femur presses down on the meniscus during normal loading, the meniscus deforms radially but is anchored by its anterior and posterior horns (Fant and Fpost). Ara dial reaction force (Frad) balances the femoral horizontal force (Fh).
How do menisci get injured?
There are two types of meniscal tears, traumatic and degenerate. Degenerative tears occur as the meniscus becomes less compliant and elastic with age.
Figure 20.31 Menisci convert a compressive stress into a radial stress that is taken up by a circumferential (hoops tress within the meniscus.
Figure 20.32 Free body diagram of forces acting on the meniscus during loading.
Structured oral examination question 4#
Meniscus anatomy and function (see above).
What is the histology of the meniscus?
The meniscus is primarily constituted of interlacing networks of collagen fibres (predominantly type 1 interposed between cells.
What about the layers of the meniscus?
There are three collagen layers: superficial, lamellar and deep. The circumferential fibres function inhoops to accept stress without gross deformation or extrusion from the joint surface. The radial displacement is opposed by posterior and anterior attachments on the tibial plateau.
When does a meniscus stop growing in a child?
Anatomically, the meniscus is fully vascularized at birth, but the area of vascularity recedes toward the periphery with age, such that, by the age of 10, only the peripheral 10–30% of the meniscus is vascularized, as is seen in the adult meniscus.
What meniscus is usually damaged with ACL injury?
Medial meniscus tears are more common inpatients with chronic ACL insufficiency, lateral meniscus tears are predominately found in acute ACL injuries. The lateral meniscus is more mobile than the medial meniscus and can become trapped between the femur and tibia during ana cute pivoting episode.
3. Invertebral disc structure and function#
Introduction#
Tipping the balance is that the basic science of degenerative disc disease may additionally find its way into a general adult and pathology viva on PID.
A good starting point is a basic understanding of the anatomy and function of the spine.
Structured oral examination question 1#
Describe the anatomy of the vertebral column
The normal adult vertebral column typically consists of 33 vertebrae (seven cervical; 12 thoracic; five lumbar; five fused sacral and four fused coccygeal). It extends from the occipital condyles of the skull at the atlanto-occipital joint to the apex of the coccyx. Movement of the vertebral column occurs through the 23 discs in the human spine.
What are the individual anatomical features of each vertebral region?
In the cervical region there are C1 (atlas) and C2 (axis) which are considered specialized vertebrae. The C3 to C7 section is referred to as the subaxial region. In the thoracic region there is a progressive increase invertebral body mass from T1 to T12, pedicles are small in diameter, laminae are vertical with a ‘roof tile ’ arrangement, the spinous processes are long, overlapping and projected downwards and the intervertebral foramen is larger with less incidence of nerve compression.
What are the functions of the spine?
Functions of the spine include: Protection of the spinal c ord. It offers attachment points for the ribs and muscles of the back and trunk.
What are the functions of the intervertebral disc?
The intervertebral disc: Allows the spine to twist and bend throughout a wide range of positions. Functions to absorb energy and distribute loads applied to the spine. 25 No need to complicate matters for yourself and mention this in the exam lest it alerts the examiners, who may then start asking you difficult questions.
What is a motion segment?
The motion seg mentis the functional unit of the spine.
What is the structure of the intervertebral disc?
There are three main regions to the intervertebral disc each with differing structural compositions: (1) outer annulus fibrosis, (2) inner nucleus pulposus and (3) endplates.
What is the structure of the annulus fibrosus?
It is mainly composed of type I collagen, water and proteoglycans. It has a high collagen/low proteoglycan ratio. Fibroblast-like cells are responsible for producing type I collagen and proteoglycans. The outer annulus fibrosus consists of a number of densely packed layers composed of predominantly type 1 collagen called lamellae. Fibres of each lamella run obliquely between vertebrae at about 30° to the horizon, with adjacent lamella typically running at right angles.
Why is this?
This arrangement allows the disc to resist both torsional, axial and tensile loads (distraction and shear). This is sometimes referred to as a hands-in-the-pocket configuration or plies in a tyre tread. Therefore, on progressing from the outer to the inner annulus, the type I collagen level declines and that of the type II increases.
Describe the structure of the nucleus pulposus.
It is mainly composed of type II collagen, water and proteoglycans and polysaccharides. Chondrocyte-like cells are responsible for producing type II collagen and proteoglycans. These cells continually maintain the matrix and rely on diffusion of nutrients from the endplates surviving in relatively hypoxic conditions. Aggregates are held together by type II collagen that is cross-linked by type IX collagen. Equilibrium between the aggrecan and type II collagen helps in creating a load-bearing and c ompression-resisting tissue that gives stability to the disc. This should not draw any examiner criticism ast o not answering the question, 26 as linking structure to function brings higher -order thinking into the topic.
What are the functions of the NP?
The NP resists compressive loads, dampens mechanical loads and evenly distributes forces onto the endplates.
What is the function of the matrix?
The disc matrix is an elaborate framework of macromolecules that atir act and hold water. This viscoelastic matrix distributes forces smoothly to the annulus and the endplates. The NP contains proteoglycan aggregates entrapped in a collagen fibre network.
What about the endplates? What is the function of the endplates?
The endplates are positioned above and below the nucleus and most of the annulus and are thin layers of hyaline cartilage that are considered part of the disc, not part of the vertebral body. The annulus and nucleus are firmly attached to the endplates and separation is difficult.
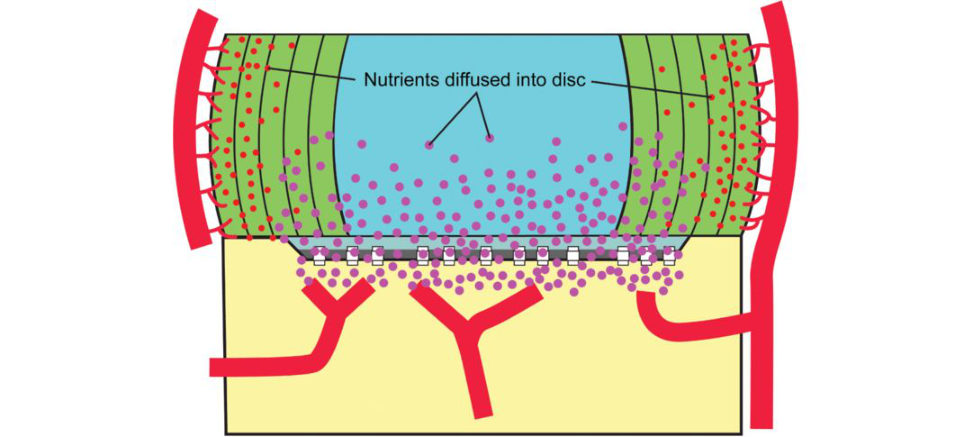
How can oxygen and glucose and other nutrients diffuse through the usually impermeable tough periosteum of the vertebral body?
Under normal circumstances, no diffusion would occur; however, the subchondral bone of the vertebral bodies has special channels called marrow cavities that allow for diffusion to occur (Figure 20.33).
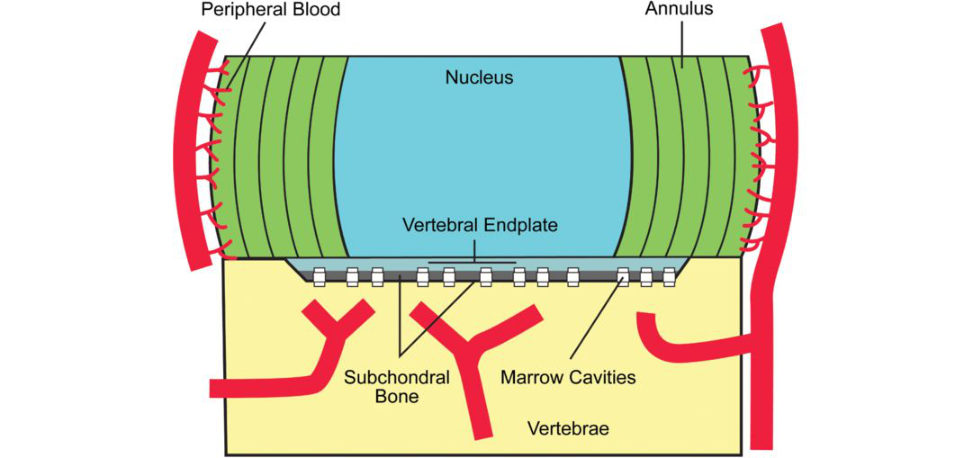
What about the blood supply of the intervertebral disc?
They receive their blood supply by diffusion through the vertebral body endplates. A network of vessels located centrally in the endplate allows nutrients to diffuse into the nucleus pulposus and annulus fibrosus (Figure 20.34). Nutrients are supplied to the disc primarily through diffusion.
What happens to the disc with ageing?
With ageing there is decreased vascularity of the endplates.
There is an increase in the proportion of type I to type II collagen and an increased ratio of keratin sulphate to chondroitin sulphate.
What is the nerve supply to the intervertebral disc?
The posterior and posterolateral disc are innervated by the sinuvertebral nerve, the lateral disc by the grey ramus communicans (a sympathetic nerve of the autonomic system), and the anterior disc by sympathetic branches from the sympathetic trunk or ganglion that courses anterolaterally over the vertebral bodies (Figure 20.35).
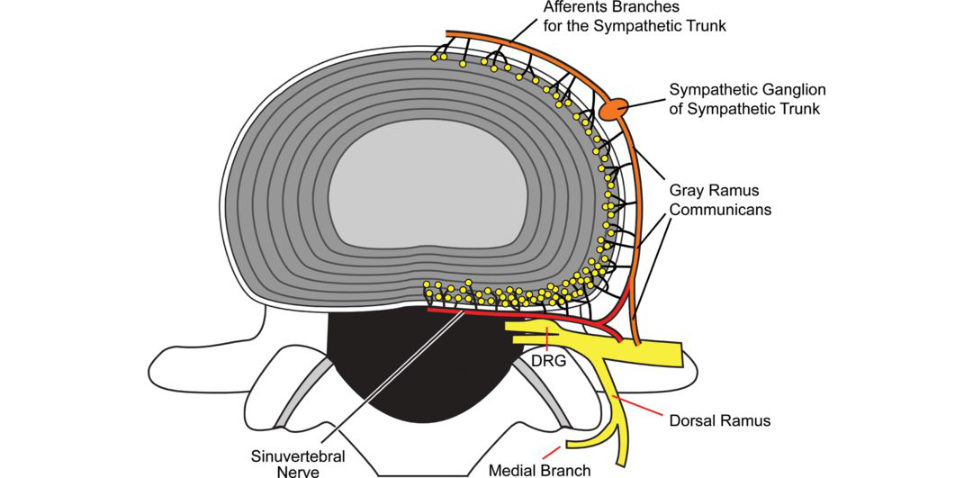
Describe the natural history of a lumbar disc prolapse.
Recurrent torsional strain leads to tears of the outer annulus that lead to herniation of nucleus pulposus. Approximately 90% of patients will have improvement in symptoms by 3 months.
What are the risk factors for developing a disc prolapse?
Disc prolapse is related to failure of the annulus fibrosus due to either increased load/pressure or decreased mechanical strength. This means the annulus isless well supported and more prone to tearing.
What are the suggested theories for the mechanism of production of pain in disc disease?
There are several possible mechanisms for development of pain in disc disease. The second type of pain is mechanical in nature and is due to the degenerative disc reducing in height and therefore providing a reduced structural role, which causes increased load through the posterior elements (e.g. facet joints) and their subsequent degeneration.
Finally, there is an altered cytokine profile within the degenerative disc with increased IL-1 that may be implicated in discogenic pain.
Figure 20.33 Diffusion of nutrients into the intervertebral disc.
Figure 20.34 Blood supply of the intervertebral disc.
Figure 20.35 Nerve supply of the intervertebral disc.
Structured oral examination question 2#
Intervertebral discs, describe parts, contents, effect of ageing, and what is lumbago vertebra.
What is this (Figure 20.36)?
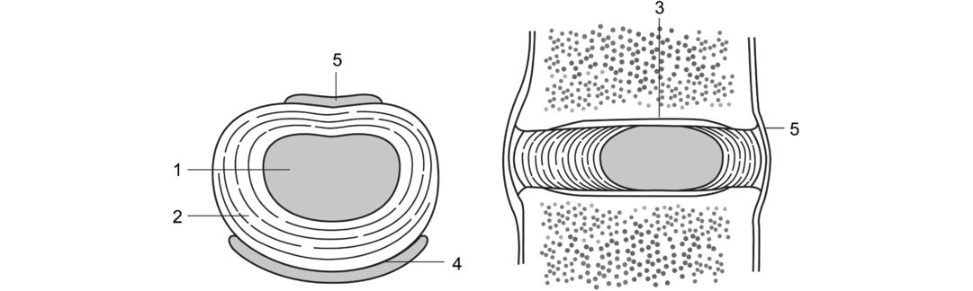
It is a picture of an intervertebral disc.
Figure 20.36 The intervertebral disc: 1, nucleus; 2, annulus; 3, cartilaginous endplate; 4, anterior longitudinal ligament; 5, posterior longitudinal ligament.
Can you name the various blank labels of the disc?
the overall viva table is proceeding well go on to talk about how IVD structure is related to its function.
Can you describe the various parts and contents of the disc?
Go through the three components of the disc (AF, NP and endplates) and try to link structure to function (see above question 1).
What are the functions of the disc?
The disc essentially functions as a shock absorber to redistribute compressive loads and resist tensile, rotational and shear forces.
What happens to the disc with ageing and how does this affect function?
In the NP the concentration of viable cells decreases, proteoglycan and water concentrations decrease and there is a partial loss of structural integrity. This is a solid score 6, but the answer could be better explained in terms of the changes.
proteoglycans, age as they undergo continuous proteolytic degradation (MMP s and.
ADAMs). At the same time, the production of collagen type I increases.
This results in a number of changes.
The NP becomes progressively more fibrous and opaque, and with increased pigmentation. As the collagen content increases and changes from type II to type I, demarcation between the NP and AF becomes less distinct and separation of adjacent annular laminae occurs.
Score 7/8.
How is ageing different to degeneration?
This is a difficult, controversial topic that is testing higher -order thinking. Intervertebral discs receive the vast majority of their nutrient supply from diffusion across their endplates. With ageing, the number of vascular channels perforating the osseous vertebral endplates diminishes. This leads to reduced porosity across the vertebral endplates and an accumulation of cell waste products and degraded matrix molecules that impair cell nutrition and function. This gradual loss of viable cells within the NP further compromises matrix synthesis. Each factor mediates its effect by either altering the balance of protein synthesis and degradation and/ or the rate of cell death or apoptosis.
What is the pathophysiology of the prolapsed disc?
More stress is placed on the collagen fibres of the AF that they are not designed to tolerate. As such, the collagen structure of the AF deteriorates due to impaired formation, increased cross-linking and increased breakdown.
The endplates become thin, sclerotic and pr one to microfracture.
This reduces a disc’s ability to recover from deformation, tearing.
What are the macroscopic changes that occur?
There is narrowing of the disc space osteophytes at the margins of endplates, increased stress at the facet joints, facet joint degeneration, osteophyte formation.
How do hoop stresses occur in the spine (Figures 20.37 and 20.38)?
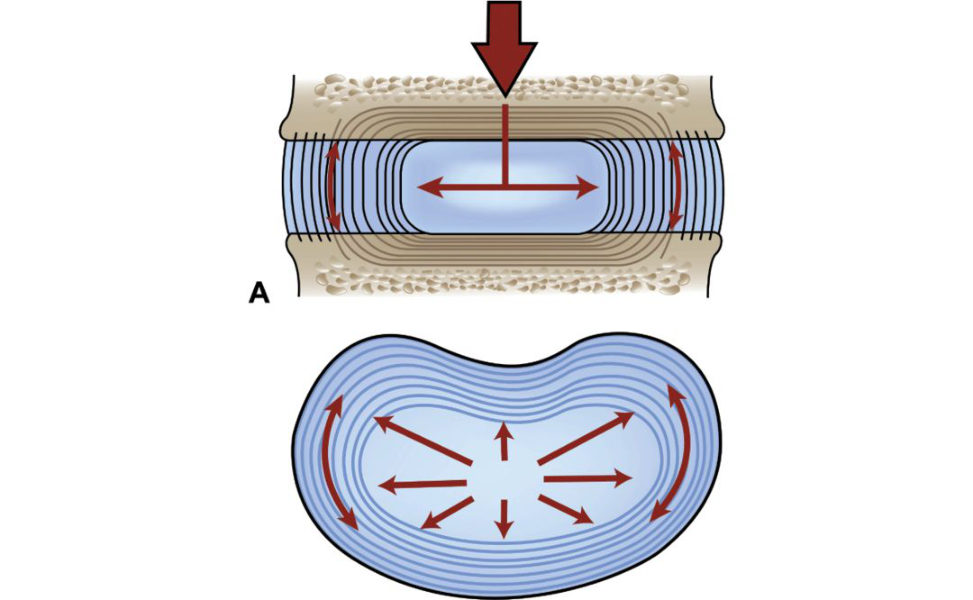
Figure 20.37 Compression force from bodyweight contraction straight arrows) raises the pressure in the NP. This, inturn, increases the tension in the AF (curved arrows) and muscle.29
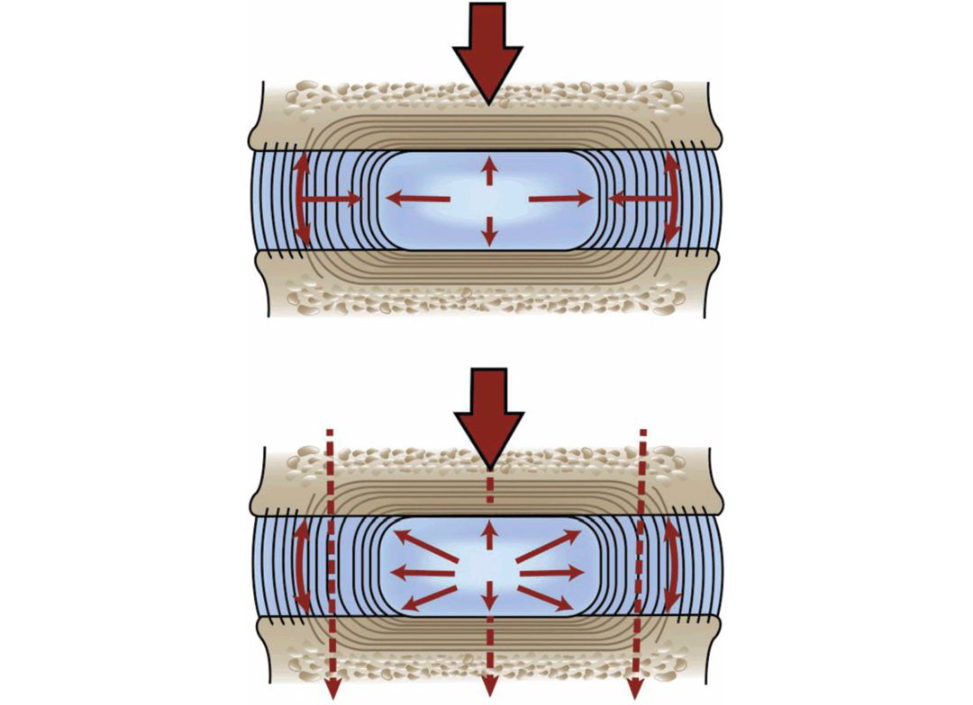
Figure 20.38 The increased tension in the AF inhibits radial expansion of the NP. The rising pressure in the NP is also exerted upward and downward against the vertebral endplates. The weight is partly borne by the AF and NP and is then transmift ed across the endplates to neighbouring vertebrae.30
When loaded from above, the height of the NP is reduced. At the same time, the nucleus is constrained in the up–down sense by the endplates and vertebral bodies. In this way, pressure applied to the NP is passed on to both the AF and the endplates.
How does the disc function as a shock absorber?
The idea that the intervertebral discs act as a shock absorber has been challenged in recent years, with the view that by far the greatest amount of energy absorbed is from the muscles and tendons surrounding the spine, rather than by the disc.
A controversial and misunderstood concept that perhaps should not have been asked.28 The fibre orientation of the AF resists hoop stresses generated by the hydrostatic pressure from the NP (Figure 20.39).
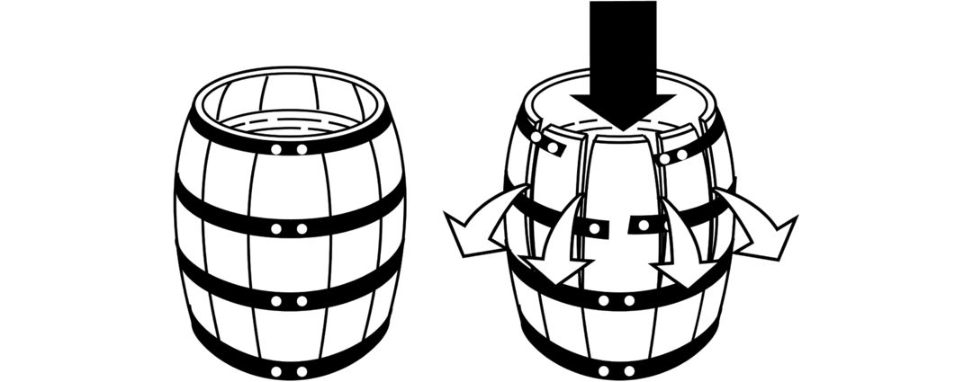
Figure 20.39 Hoop stress. A load of water in a barrel is resisted by the hoops around the barrel. When too great a load is applied, the hoop will break. The annulus functions in a similar manner to that of the hoops around a water barrel.
This is probing for a more detailed answer than just concentrating on the g el-like material features of the NP.
What is lumbago vertebrae?
Sorry, I have no idea. Lumbago is a seldom-used term to mean mild to severe low-back pain. Low-back pain is a more precise term and should preferably be used instead.
What is the role of aggrecan and collagen in the ability of discs to resist compression?
The NP contains proteoglycan aggregates entrapped in a collagen fibre network.
The hydration properties of the gly cosaminoglycan chains of aggrecan cause the tissue to swell until an equilibrium is reached, in, the swelling potential is balanced by tensile forces in the collagen network.
Compressive loading of the spine forces some water from the disc effectively increasing the aggrecan concentration.
An y parameter that decreases proteoglycan concentration or weakens the collagen network will be detrimental to disc function .
Structured oral examination question 5#
What is the purpose of the spine?
The primary purpose of the spine is to provide protection for the spinal cord and axial support system to allow locomotion and function of limbs.
OK, what is the primary site of movement in the spine?
[The penny drops!] Much of the ability to rotate and move within the spinal column is possible due to the intervertebral discs.
Tell me about the anatomy of the intravertebral disc?
[The largest discis actually L4/5, but the examiner either didn’t know himself or didn’t want to push me at this stage.] The classic paper to quote and read is Coventry et al.31 There are three parts to this.
OK, can you tell me about the structure in more detail?
The annulus fibrosus makes up the peripheral portion of disk structure and is predominantly made up from fibrocartilage and type I collagen. The orientation of the fibres varies in successive layers and alternates at about 45°.
What is the nerve supply?
The majority of the nerve supply lies in the outer rings of the annulus fibrosus, with supply from the sympathetic chain interiorly.
And posterior?
I can’t recall! [Sinus vertebral nerve dorsally]
Why is discitis common in children then?
Blood vessels occur in the annulus up to late teens, and into the cartilage endplates up to 8 years, which is why discitis occurs in this specific paediatrics group.
4. Muscle structure and function#
An appreciation of muscle anatomy and physiology is important in the understanding of muscle injury.
However, a passive read through of this topic in a standard orthopaedic textbook is quite poor preparation for a viva question. It is worth knowing this subject well as it is definitely an A-list topic.
Structured oral examination question 1#
What is this picture (Figure 20.40)?

This is an electron micrograph picture of skeletal muscle.
Why do you say this?
We can see striations alternating light (I) and dark (A) bands.
Can you identify sarcomeres, A bands, I bands, Z lines, M lines and H zones (Figure 20.41)?
A sarcomere is the basic unit of striated muscle tissue. It is the contractile unit of a muscle cell. Actin fibres are anchored on the Z line. The I band represents just actin filament sin adjacent sarcomeres where there is no overlap with myosin filaments. It is darker on the edges where there is a double, overlapping, hexagonal array of thick filaments (mostly myosin) and thin filaments (actin plus the regulating proteins: troponin and tropomyosin). The central H zone of the A band contains only thick myosin filaments. The relationship between the A band and H zone can be confusing. TheA bandis a dark overlap of thin and thick filaments that also contains the central H zone composed of thick myosin filaments only (Figure 20.42).
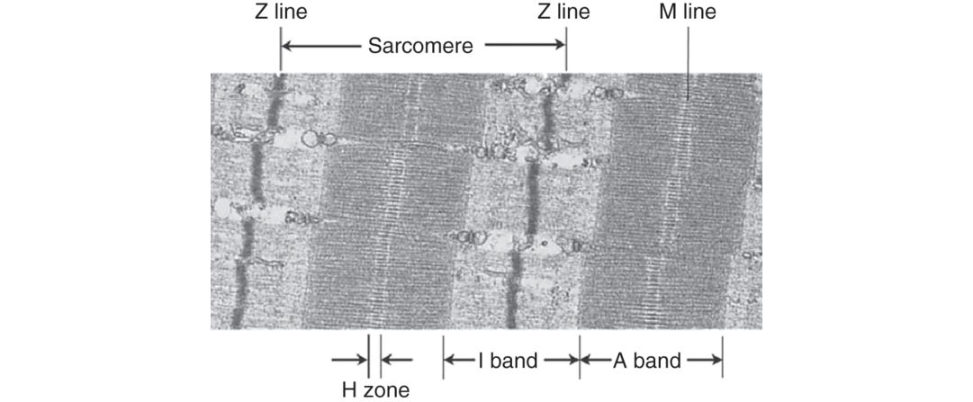
What do you mean by isotropic and anisotropic bands?
Candidates need to be careful (especially in the basic science viva) not to use terms they do not fully understand.
Each sarcomere contains an anisotropic (doubly refractive therefore dark inphase microscopy) band bounded by two isotropic (singly refractive therefore light) bands. In the centre of the A band, there is a lighter region known as the H zone or H band.
What is the structure of actin and myosin?
The thick filaments are made of a protein called myosin. It is shaped like a golf club with two heads. The thin filament is made of a protein called actin. In the resting state, tropomyosin blocks the myosin binding sites on actin. This results in a conformational change in tropomyosin, exposing the myosin binding sites on actin.
What happens to the I and A bands with muscle contracture? Can you identify which sarcomere is contracted in these pictures (Figures 20.43 and 20.44)?
In a relaxed muscle, actin and myosin myofilaments lie side by side and the H zones and I bands are at maximum width. During contracture the actins are pulled towards the centre of each myosin myofilament. In a fully contracted muscle, the ends of the actin myofilaments overlap, the H zone disappears and the I band becomes very narrow.
Can you draw what is happening to the actin and myosin within the muscle sarcomere when the muscle contracts?
(Figure 20.45)
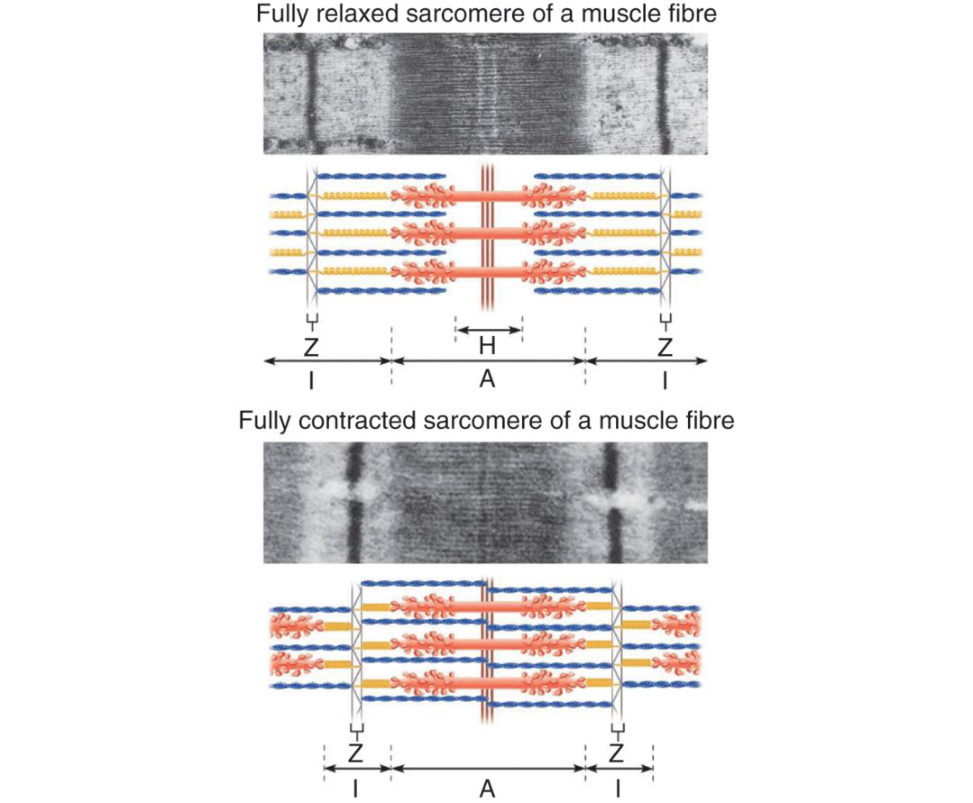
This question (we think) tests inequal measure a candidate’s drawing ability and muscle sarcomere knowledge.
How do muscles contract? Explain how skeletal muscles contract.
Having dealt with the microstructure of the sarcomere the second part of the topic deals with how the myosin heads interact with the actin filaments. The use of ATP to break cross-bridges and reset myosin heads. In resting muscle fibres, Ca2+ is stored in the sarcoplasmic reticulum. The arrival of the action potential a t the ends of the T-tubules triggers the release of Ca2+. The Ca2+ diffuses among the thick and thin filaments where it binds to troponin on the thin filaments. When the process is over, the calcium is pumped back into the sarcoplasmic reticulum using a Ca 2+ ATPase. The hydrolysis of ATP causes the myosin heads to change shape and swivel which moves them towards the next actin binding site. Via the repeated hydrolysis of ATP, the skeletal muscle will contract.
What do we mean by the cross-bridge cycle (Figure 20.46)?
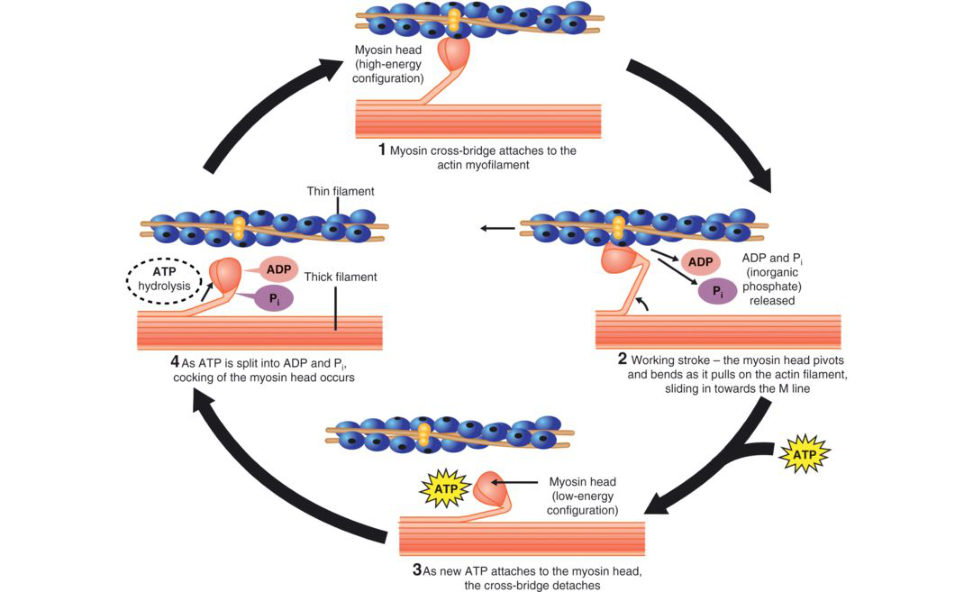
The cross-bridge cycle consists of four steps: 1. 2. Formation of cr oss-bridges.
Myosin head attaches to the myosin-binding site on actin.
3. Power stroke.
During the power stroke the cross-bridge rotates, sliding the filaments.
4. Detachment of myosin from actin.
As the next ATP binds to the myosin head, the myosin head detaches from actin.
Continuing cycles applies the force that shortens the sarcomere.
What is the role of AT Pin muscle contracture?
AT Pis the immediate source of energy for muscle contraction.
What are the actual events occurring in muscle contraction and relaxation?
Excitation –contraction coupling At the end of the T-tubules the depolarization triggers Ca2+ release from the sarcoplasmic reticulum. Ca2+ binds to the troponin C molecule, resulting in a cooperative configurational change in the troponin–tropomyosin complex. Link between thick and thin filaments, swivel of myosin head. Muscle recovery Ca2+ removed from sarcoplasm and transported back into the sarcoplasmic reticulum.
Mg2+ ATP bound by actinom yosin.
Cross-bridges disconnected.
Actinom yosin-ATPase inhibited.
Active tension disappears.
Figure 20.40 Unlabelled electron micrograph picture of skeletal muscle.
Figure 20.41 Bare labelled electron micrograph picture of skeletal muscle.
Figure 20.42 Labelled diagram of skeletal muscle.
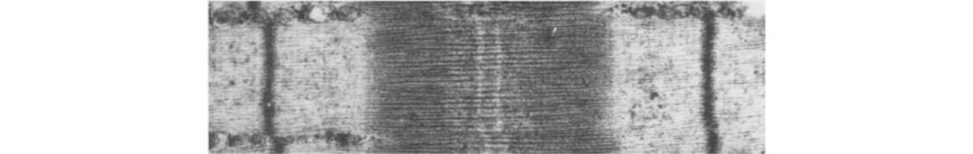
Figure 20.43 Relaxed muscle.

Figure 20.44 Contracted muscle.
Figure 20.45 Skeletal muscle actin/m yosin arrangement with relaxation and contracture.
Figure 20.46 Cross-bridge cycle.
Structured oral examination question 2#
Viva question 2 tests similar knowledge to viva question 1, but they are not identical.
How do you classify skeletal muscles?
Muscles can be classified according to: Shape and fascicular architecture. The number of joints over which the muscle crosses. Type of muscle action or function (their interaction injoint movement) (agonists, antagonists, synergists and fixators).
Tell me about the types of muscle contraction that can occur. What do we mean by isometric and isotonic muscle contracture?
1. Isometric contraction (iso = equal + metric = length): Force is generated but the muscle does not shorten (no movement). Muscle is held at a fixed length. The muscle contraction is activated , but instead of being allowed to lengthen or shorten, it is held at a constant length. 2. Isotonic contraction (iso = equal + tonic = tone or tension): Constant force with change in muscle length (movement). a. Concentric contraction (con = towards + centric = centre).
Eccentric contraction : (Ecc = away from + centric = centre)
It is a contraction in which the origin and insertion of the contracting muscle are moved away from each other by an external force.
Biceps curls exhibit both concentric and eccentric contraction.
Isokinetic contraction (iso = equal + kinetics = motion):
This involves keeping the speed (distance per unit time constant on an actively contracting muscle while the load is changed in order to maintain a constant velocity.
This is the warm-up question!
What macroscopic types of muscles do you know?
Muscles can be broadly classified into either parallel, where the muscle fibres are parallel to the line of pull, or pennate, where the short muscle fibres are oblique to the line of pull (Figure 20.47). Parallel muscles are subdivided into the following subtypes: 1. 2. Fan-shaped (triangular) (pec major). 3. Fusiform muscles (biceps). Pennate muscles can be subdivided into: 1. 3. Multi pennate muscles are where a series of bipennate muscles lie side by side in one plane.
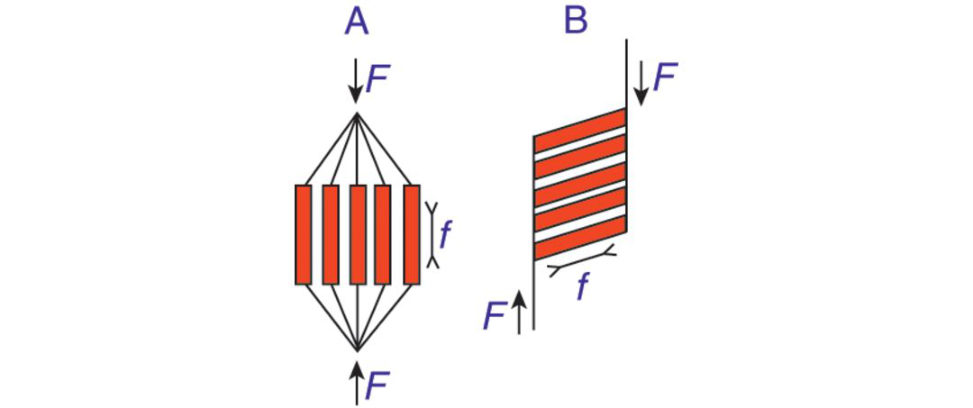
However, their range of movement is diminished because of the shortness of muscle fibres and oblique direction of pull.
Pennate muscles are located in positions requiring small but powerful movements.
Figure 20.47 The two arrangements of muscle fibres within a muscle. (A) Parallel arrangement. (B) Pennate arrangement. Double-headed arrows (f) indicate direction of force exerted by individual muscle fibres.
What is the role of the horizontal component of a pennate muscle?
The force of muscle action is resolved into two component forces – one acts in the line of pull and the other at right angles to it. This is not in the standard orthopaedic textbooks! That’s what makes the basic science viva so feared!
Can you draw me the structure of a muscle?
Epimysium wraps around an entire muscle. Perimysium subdivides each muscle into fascicles, bundles of 10–100 muscle fibres. The sarcomere drawing (Figure 20.49) deals with muscle ultrastructure and is more complicated to draw and explain.
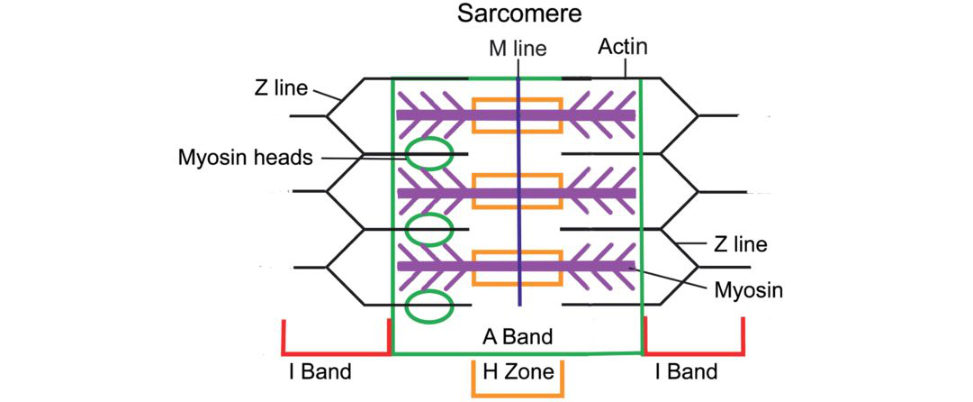
Actin – thin filaments have actin because if you’re active actin) you will be thin.
Myosin – o ands short and fat letters.
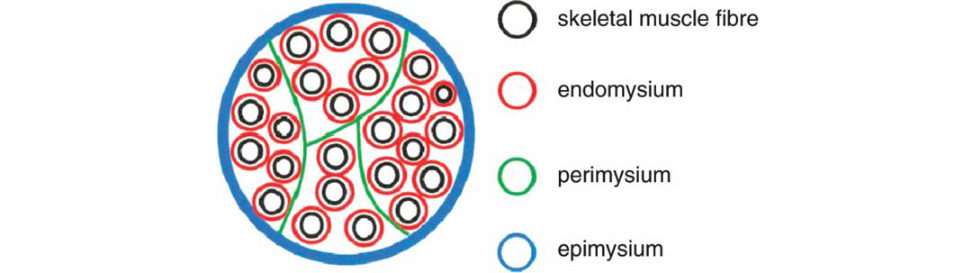
Figure 20.48 Candidate drawing. Cross-section of a skeletal muscle.
Figure 20.49 Candidate 20-second exam drawing of skeletal muscle sarcomere. Z line is where the thin filament (actin creates a zig-zag pattern. One sarcomere is Z-line to Z-line. In between the I bands is the A band (darker on the edges, just myosin present in the H zone).
What are the different types of skeletal muscles and can you draw them?
Muscles can be divided into: 1. 2. Fusiform 3. Attached obliquely to a central tendon that runs the length of the muscle. Produce more tension (more muscle fibres).
Unipennate (palmer interosseous), bipennate (rectus femoris) and multi pennate (deltoid) – to how many sides of the tendon do the fascicles attach?
4. Convergent (fan-shaped) Broad at origin converging to a narrower insertion, less pull than parallel muscle spec major).
5. Circular – fascicles arranged in a concentric ring. Act as sphincters, a ring around a body opening
(orbiculari soris).
fusiform, be able to discuss the advantages of each type of muscle shape (Figure 20.50).
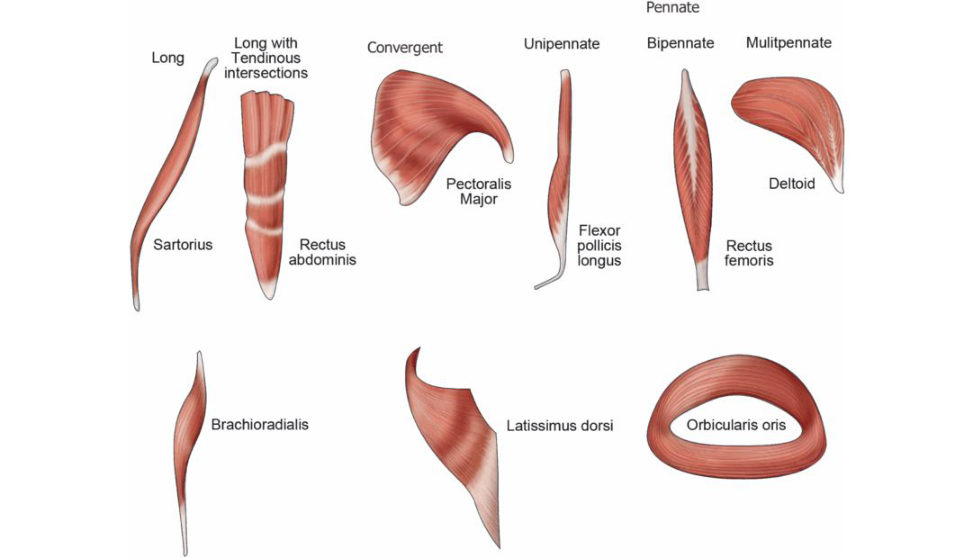
Figure 20.50 Muscle shape and fibre arrangement.
What is the hierarchical structure of muscle (Figure 20.51)?
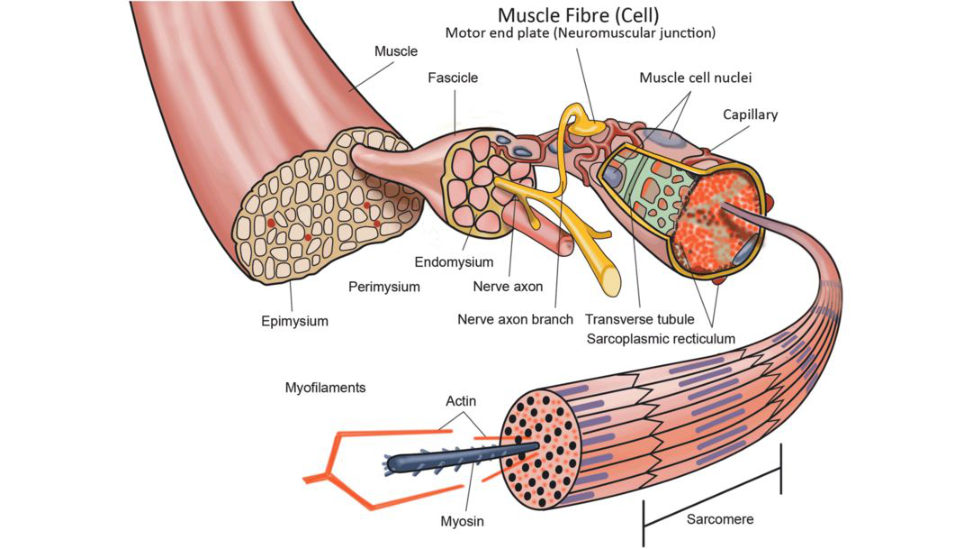
Figure 20.51 Hierarchical structure of muscle.
Bundles of muscle fascicles make up a single muscle = muscle bundles (fascicles) make up a single muscle. Bundles of 10–100 muscle fibres make up a muscle fascicle. A fascicle is the smallest unit of structure visible to the naked eye.
Draw the structure of striated muscle fibres including the myofibrils with light and dark bands, mitochondria, the sarcoplasmic reticulum, nuclei and the sarcolemma (Figures 20.52 and 20.53).
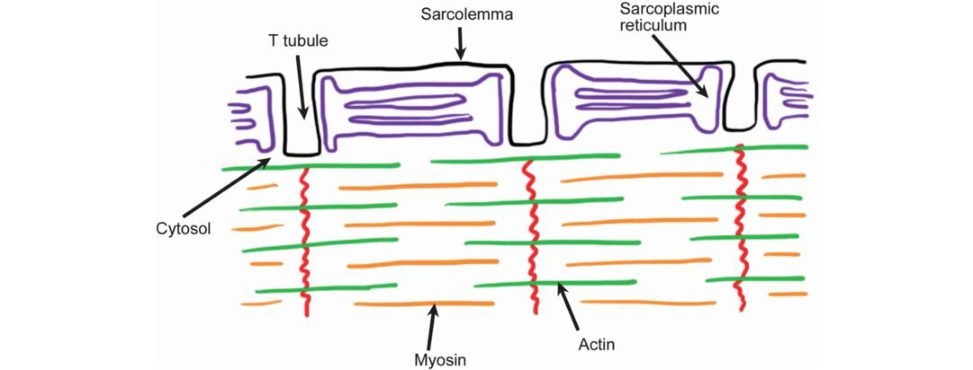
Figure 20.52 Candidate diagram. Sarcoplasmic reticulum arrangement in skeletal muscle.
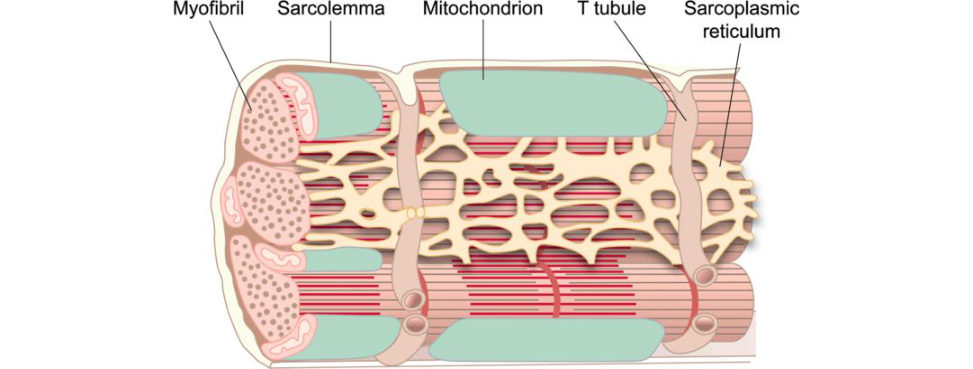
Figure 20.53 Sarcoplasmic reticulum arrangement in skeletal muscle.
The sarcomere is the smallest contractile unit of skeletal muscle. The sarcoplasmic reticulums tores calcium (Ca2+) in intracellular membrane-bound channels.
How does muscle move at a microscopic level, how do troponin, myosin and tropomysin interact?
Similar info to that asked for in oral examination question 2. This is one of the pivotal knowledge areas in the muscle section the T r & Orth curriculum sets out to test. Troponin has three subunits, I, T and C.
Troponin I is inhibitory and is able to block actin –myosin interactions.
Troponin T enables binding of troponin and tropomysin.
Troponin C binds calcium.
the troponin–tropomyosin complex is situated on the actin filament in a way that prevents actin –myosin cross-bridge formation ( Figure 20.54).
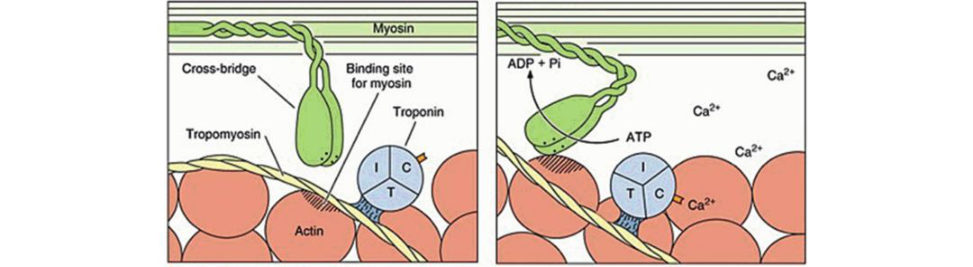
A rise in myoplasmic Ca2+ allows Ca2+ to bindwith troponin C. This change permits myosin–actin cr oss-bridge cycling.
When Ca2+ concentrations return to normal resting levels, the actin binding sites are again blocked from forming cross-bridges.
Figure 20.54 Cross-bridge. Troponin T (tropomyosin binding), troponin I (inhibitory protein) and troponin C (calcium binding). Binding of Ca2+ to the Tn Cunit of troponin exposes the myosin binding site on actin.
What about length versus strength of muscle contraction, and the gr aph, which shows this (Figure 20.54)?
Skeletal muscle fibre force production is defined in terms of myofilament overlap, i.e. in terms of sarcomere length. At optimal length, where actin –myosin interactions are maximal, muscle generates maximum force (region 2). At lengths shorter than the optimum region 1), force decreases owing to double interdigitation of actin filaments with both myosin and actin filaments from opposite sides of the sarcomere.
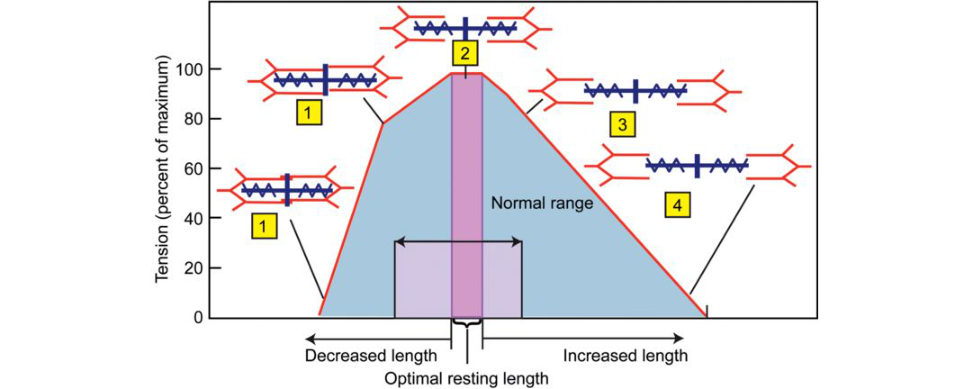
Figure 20.55 Length versus strength of muscle contraction.
What about the force–velocity relationship ( Figure 20.56)?
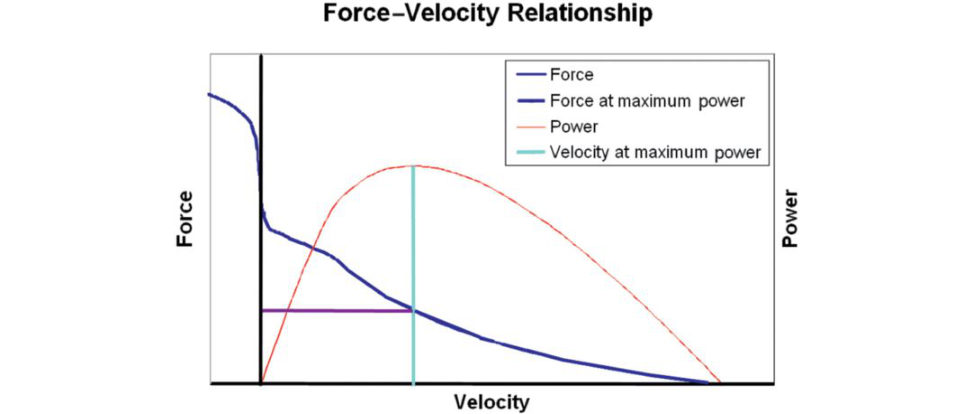
Figure 20.56 Force velocity curve of a skeletal muscle. Right of the vertical axis concentric contractions (the muscle is shortening), left of the a xis eccentric contractions (the muscle is lengthened underload);
power developed by the muscle in red.
The force–velocity relationship in muscle relates the speed at which a muscle changes length with the force of this contraction and the resultant power output (force × velocity = power). At maximum velocity no cross-bridges can form, so no force is generated, resulting in the production of zero power (right edge of graph). The reverse is true for stretching of muscle.
it functions, is dependent on the speed the sarcomere is contracting.
When the filaments are being moved at a higher velocity, fewer myosin heads can bind to the actin filament sat a given time and as a result the total force is lower.
At speed 0, or an isometric contraction, the force is greater. This can be explained by the force required to stretch passive structures and lengthen the muscle (Figure 20.57).
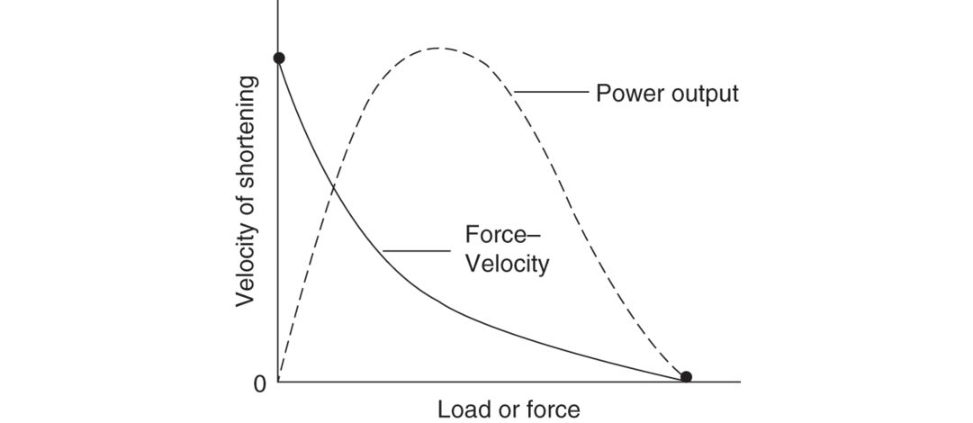
Although the force of the muscle is increased, there is no velocity of contraction and zero power is generated.
Figure 20.57 Force velocity curve with eccentric contracture. Force and velocity are inversely related such that at zero (0) velocity maximum force is generated, and at maximum velocity zero (0) force is generated.
5. Structure and function of tendons and ligaments#
Introduction#
Tendon and ligaments are complex connective tissues often grouped together as they share similar tissue composition and properties.
structural differences between these two tissues that the examiners may wish to discuss.
Tendon and ligament disorders are especially common, so it is important to have a clear understanding of their function in both health and disease.
Potential score 7/8 candidates should have something up their sleeve if the examiners probe into new treatment options.
Structured oral examination question 1#
Tendon structure and function. Leading onto a discussion about tendinopathy versus tendonitis.
What is the function of tendons?
Tendons attach muscle to bone and function to: Transmit tensile loads from skeletal muscle contracture to bone resulting injoint movement.
What are ligaments?
Ligaments are dense bands of collagenous tissue (fibres that span a joint and become anchored to bone at either end.
What is the function of ligaments?
Ligaments attach bone to bone and function to: Transmit tensile load from bone to bone. Provide joint stability by maintaining joint congruency.
What are the differences in structure between ligaments and tendons (Table 20.5)?
If a fairly low-key viva start the generalized details contained in Table 20.5 should be sufficient. However, candidates are often probed in more detail about specific percentage differences in composition between tendons and ligaments (Table 20.6).
What else?
Cells (fibroblasts) occupy around 20% of the total tissue volume, while the extracellular matrix accounts for the remaining 80%.
The extracellular matrix is composed of water (70%) and solids (30%).
The solid part of the matrix is mainly composed of collagen, but also ground substance and a small amount of elastin.
Type I collagen is higher in tendons (95–99%) compared to ligaments (90%) and Type III collagen accounts for 1–5% in tendons and 10% in ligaments.
What functions does the ground substance perform?
The ground substance comprises hyaluronan, proteoglycans (decorin, biglycan, fibromodulin, lumican), structural glycoproteins and a wide variety of other molecules. It contains proteoglycan aggregates that bind most of the extracellular water of ligaments and tendons, making the matrix a highly structured, gel-like material.
What about elastin?
Elastin isnt usually present in ligaments to any large degree.
How is collagen synthesized?
Candidates need to rehearse an answer based around the cellular collagen synthesis diagram. Collagen synthesis occurs in several stages with both intracellular and extracellular steps. The first stage in the synthesis of collagen is the formation inside the cell of mR NAf or each type of polypeptide alpha-chain. Several adjacent collagen molecules pack together (aggregate), overlapping by a quarter staggered array and appear as cross-striations under anele ctr on microscope.
Describe the structure of a tendon.
Most of the extracellular matrix is water (70%), but around 30% of the matrix is solid, comprising mainly type I collagen, ground substance and a small amount of elastin.
What about its hierarchical structure?
We have included both for completeness sake (Figures 20.58 and 20.59). Our own preference is for the classic tendon structure described by Kastelic et al. (Figure 20.58).
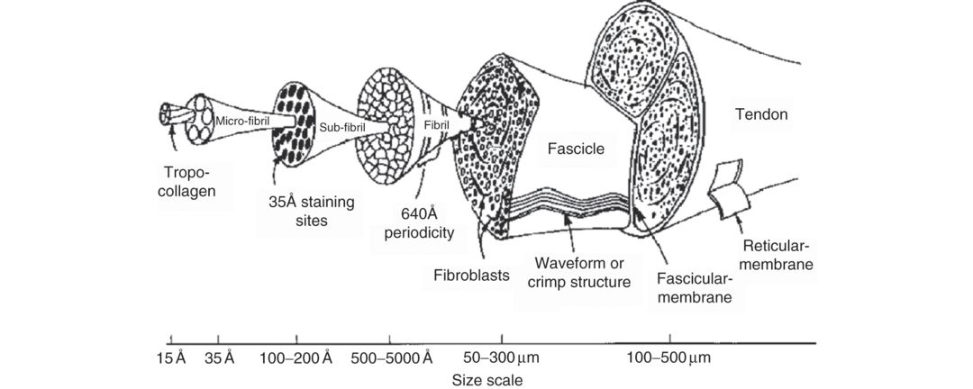
Figure 20.58 Classic tendon hierarchical structure by Kastelic et al.
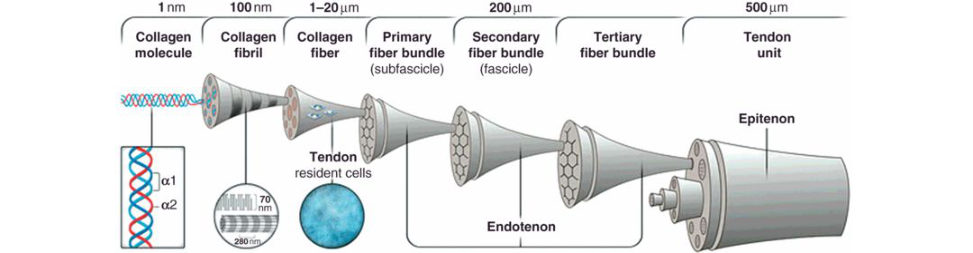
Figure 20.59 Alternative tendon hierarchical structure.
1. Classic tendon structure, description by Kastelic et al.33 Tropocollagen molecules assemble into microfibrils, these microfibrils into subfibrils.
Multiple fibrils combine to form a tendon fascicle, and fascicles, separated by the endotenon, join together to form the macroscopic tendon.
2. Alternative hierarchy structure of tendon.
Multiple collagen fibrils are packed into larger structures to form collagen fibres. Multiple secondary fibre bundles form tertiary fibre bundles, groups of which inturn form the tendon unit.
which facilitates the gliding of bundles against oneanother during tendon movement.
The endotenon is contiguous with the epitenon, the fine layer of connective tissue that sheaths the tendon unit.
What is a collagen fibre?
A collagen fibre is the smallest tendon unit that can be tested mechanically and is visible underlight microscopy.
Describe the structure of a molecule of collagen.
This question can be asked across a number of section 2 Tr & Orth topics such as bone, articular cartilage or even intervertebral disc. The structural unit of collagen is tropocollagen. Tropocollagen is formed in the fibroblast cell as procollagen that is then secreted and cleaved extracellularly to become collagen. Almost two-thirds of the collagen molecule consists of amino acid triplets (GLY-X-Y), where X is often proline andY is often hydroxyproline.
What about cross-linking?
Tropocollagen molecules are stabilized and held together by cross-linking.
Tell me about ligament ultrastructure.
The ultrastructure of ligaments is similar to that of tendons, there is a higher percentage of proteoglycans.
Ligaments exhibit non-linear anisotropic mechanical behaviour, interactions of collagen, other matrix materials.
What are the differences in structural collagen arrangement between ligaments and tendons?
In tendons, the collagen fibres are arranged completely in parallel, as they need to withstand large tensile loads in one direction only . Ligaments exhibit non-linear anisotropic mechanical behaviour and under low loading conditions they are relatively compliant, due to recruitment of ‘crimped’ collagen fibres as well as to viscoelastic behaviours and interactions of collagen and other matrix materials.
You have mentioned viscoelastic behaviour what do we mean by this?
Creep, stress relaxation hysteresis and rate-dependent deformation Tendons are less viscoelastic when compared to ligaments.
How do ligaments fail? What is the reason for midsubstance rupture and bony avulsion?
The most common mechanism of ligament failure is rupture of a sequential series of collagen fibre bundles distributed throughout the body of the ligament and not localized to one specific area. Table 20.5 Structural differences between tendons and ligaments.
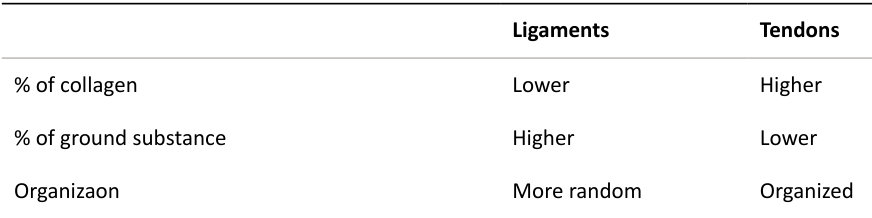
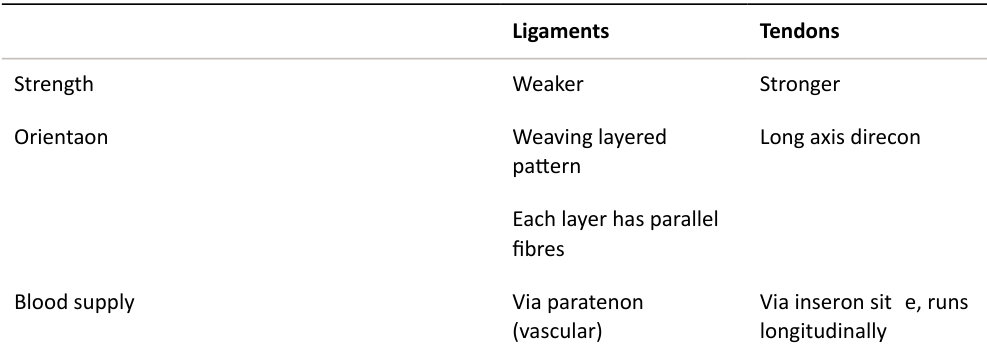
Sheathed avascular tendons via single vinculae (mesotendon) and diffusion
Table 20.6 Compositional comparison between tendons and ligaments.
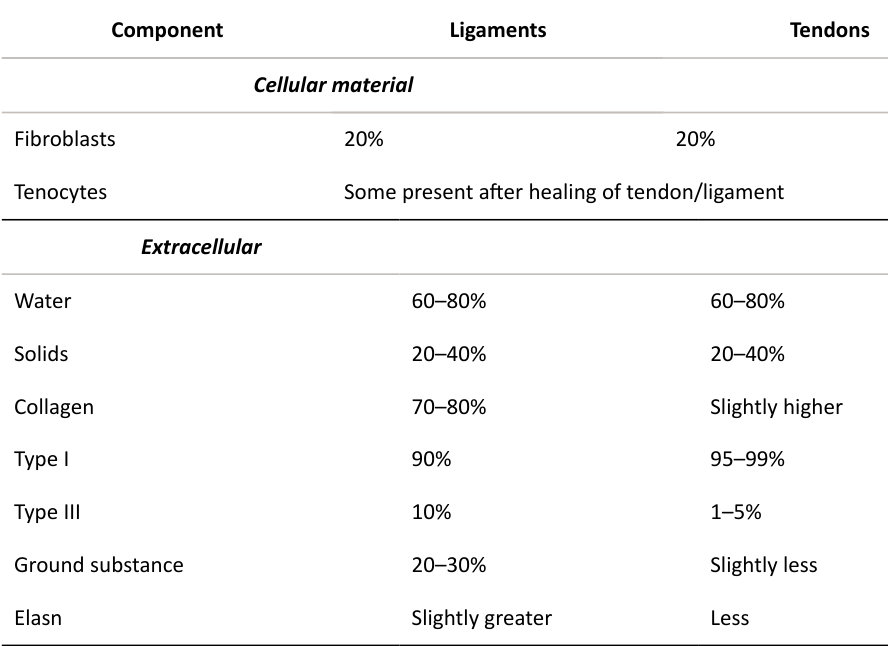
Structured oral examination question 2#
How do tendons and ligaments heal after injury? What factors affect healing?
After injury, a large number of growth factors and cytokines are released by the injured tendon and adjacent tissues, including in terleukins, vascular endothelial growth factor (VEGF), platelet-derived growth factor (PDGF), fibroblastic growth factor (FGF), transforming growth factor beta (TGF-β), connective tissue growth factor (CTGF), epidermal growth factor (EG Fand insulin-like growth factor 1 (IGF1). There are three phases of tendon/ligament healing (Table 20.7): 1. In strict terms this is section 3 material, but there is almost always some sort of varying overlap between structure and function of connective tissue ( section 2 ) and pathology (section 3 ). During this period, the repair tissue changes to fibrous tissue, this again changes to scar-like tendon tissue after 10 weeks.
Are there any new methods developed to improve tendon healing?
There have been attempts at biological augmentation of tendon healing.
Such as?
These include applying growth factors, and biomaterials, at the site of tendon damage.
What is their basis for use?
Table 20.7 Cells and matrix changes associated with tendon healing.
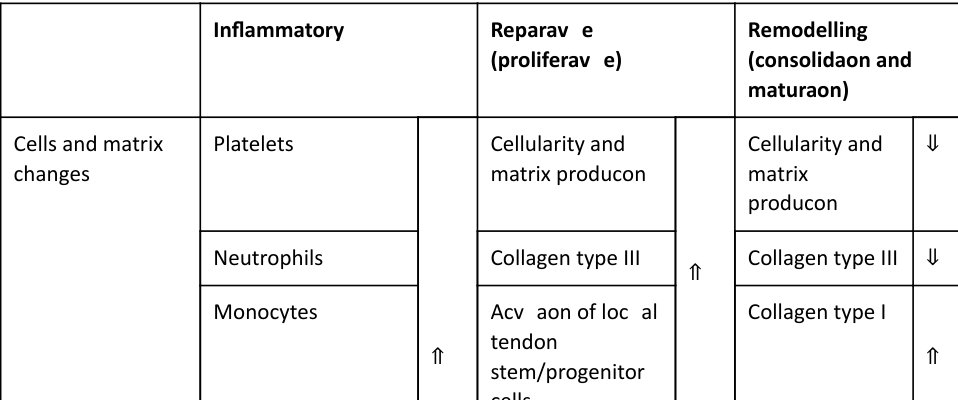
| Inflammatory | Reparative (proliferative) | Remodelling (consolidation and maturation) | ||||
|---|---|---|---|---|---|---|
| Cells and matrix changes | Platelets | ⇑ | Cellularity and matrix production | ⇑ | Cellularity and matrix production | ⇓ |
| Neutrophils | Collagen type III | Collagen type III | ⇓ | |||
| Monocytes | Activation of local tendon stem/progenitor cells | Collagen type I | ⇑ | |||
| Erthyrocytes | ||||||
| Circulation-deriv ed mesenchymal stem cells | ||||||
| Molecular changes | Interleukin-6 | bFGF | GDF-5, -6 and -7 | |||
| bFGF | GDF-5, -6 and -7 | IGF-1 | ||||
| IGF-1 | IGF-1 | TGF-β | ||||
| PDGF | PDGF | |||||
| TGF-β | TGFβ | |||||
| VEGF | VEGF |
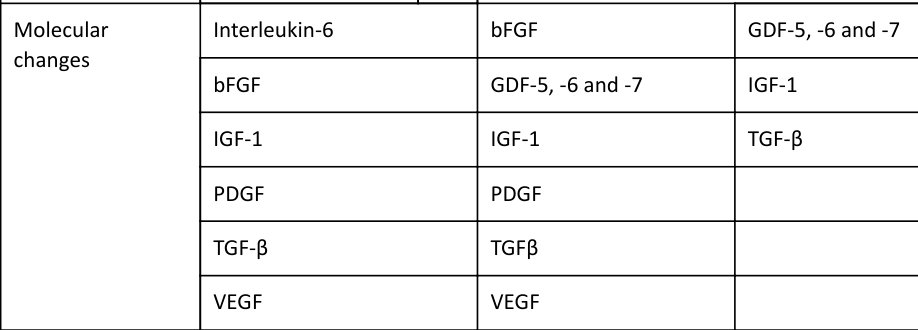
Growth factors
Tendon injury stimulates the production of a variety of growth factors at multiple stages in the healing process leading to increased cellularity and tissue volume.
or by implanting scaffolds or even suture material containing growth factors.
Mesenchymal stem cells
Mesenchymal stem cells can be applied directly to the site of injury or can be delivered on a suitable carrier matrix.
Structured oral examination question 3#
Tell me about ligament ultrastructure.
Ligaments are dense bands of collagenous tissue (fibres that span a joint and become anchored to bone at either end.
What are the differences in structural arrangement of collagen between ligaments and tendons?
In ligaments, collagen fibres are not arranged completely parallel like tendons; fibres are branched and interwoven (Figure 20.60).
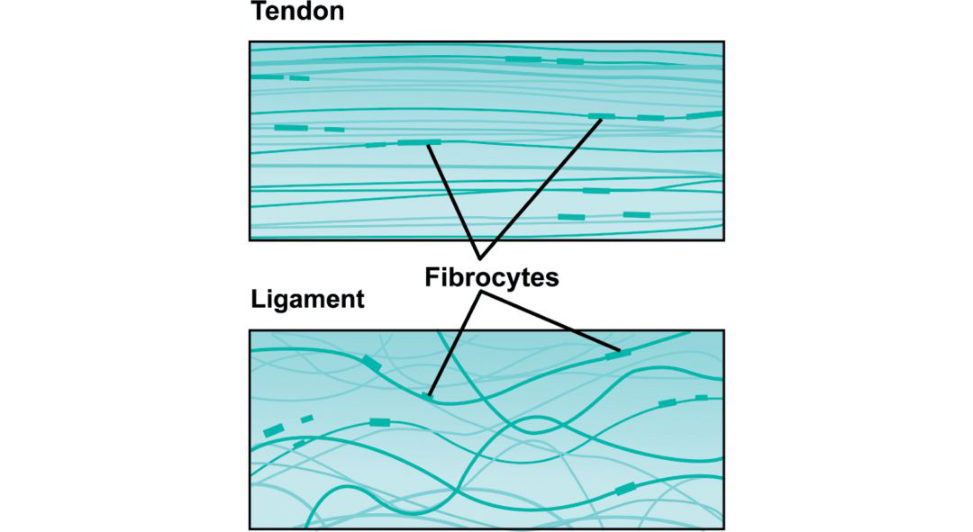
Figure 20.60 Collagen arrangement in tendon and ligament tissue Tendon: parallel bundles of collagen fibres. Ligaments: irregular wavy bundles of collagen fibres.
Why?
This is because although ligaments need to withstand large loads mainly in one direction.
In any single layer the fibres lie parallel to each other, but in subsequent layers they lie in a different direction.
When unloaded the collagen fibres in both tendons and ligaments are arranged in a wavy
This arrangement allows tendons and ligaments to be initially stretched without much resistance, increasing their capacity to absorb energy.
How do ligaments fail? What is the reason for midsubstance rupture and bony avulsion?
The most common mechanism of ligament failure is rupture of a sequential series of collagen fibre bundles distributed throughout the body of the ligament and not localized to one specific area.
But why is this? What is the reason? CANDIDIATE : With tendons, ligaments and bones their stiffness increases with increasing strain – they are strain-rate sensitive Bone is more sensitive to strain rate than tendons or ligaments, so its stiffness increases more proportionally . Therefore, avulsion is more common at slow strain rates and tendon and ligament tearing is more common at higher strain rates. During slow strain rates, avulsion is common, while, as the strain rate increases, the bone becomes stronger than the tendon or ligament and so tearing becomes more common. So why do bony avulsions occur in children and midsubstance ligament tears occur in adults?
The ligament/bone junction is relatively weak in children resulting in a greater chance of avulsion.
Structured oral examination question 5#
Draw the stress–strain curve of a ligament/tendon and describe its various parts as you go along.
There are several minor variations of the stress strain curve for tendons/ligaments seen in textbooks. Although the stress–strain curves of tendons and ligaments are broadly similar, there are a few subtle differences. Therefore, clarify (if in doubt) whether you have been asked to drawout the stress–strain curve for a ligament, tendon or if the examiners want to focus on a curve demonstrating the composite features of both materials.34 Stress–strain curve for ligament There are four regions that are commonly used to describe the stress-strain curve (Figure 20.61). 1. Non-linear (toe) region. Collagen crimped: low stiffness; change in slope as collagen fibres straighten; modulus of elasticity is not constant; the ligament becomes stiffer as more fibres are recruited. T oe region ends at about 2% of strain when all crimpled fibres straighten. 2. Elastic linear region. If strain isless than 4%, the ligament will return to its original length when unloaded; therefore, this portion is elas tic and reversible, and the slope of the curve represents an elastic modulus. 3. Progressive failure or yield region.
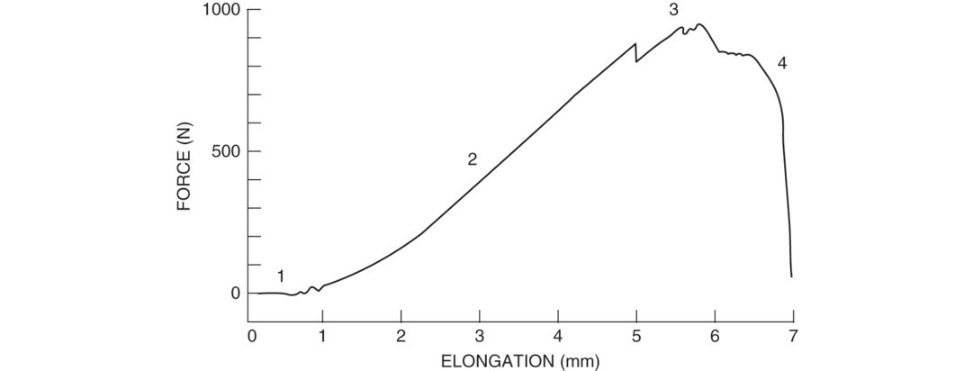
The ligament undergoes irreversible plastic deformation.
4. Complete rupture. When the ligament is stretched to more than 8% of its original length, macroscopic failure occurs, and the stress–strain curve falls quickly to zero.
What is the normal operating condition of the A CL within the knee?
During everyday activities (such as walking or light jogging) the ACL operates along the ‘toe region’ of the stress–strain curve. Loading of the A CL beyond the linear region which may occur with a bad football tackle or ski accident will result in ligament damage and possible rupture.
What about the stress–strain curve of a tendon?
The stress–strain curve (Figure 20.62) is very similar to that of ligaments except: 1. This is much less prominent than in ligaments because fibres are more aligned. Waxy collagen fibres straighten out with a small increase in load. 2. Elastic (linear region. Elastic recovery at stresses < 4%. 3. End of linear region. Corresponds to strains of 4–8%. Collagen fibres slide past oneanother, irreversible changes such as tearing or permanent stretching of tendon. 4. Macroscopic failure.
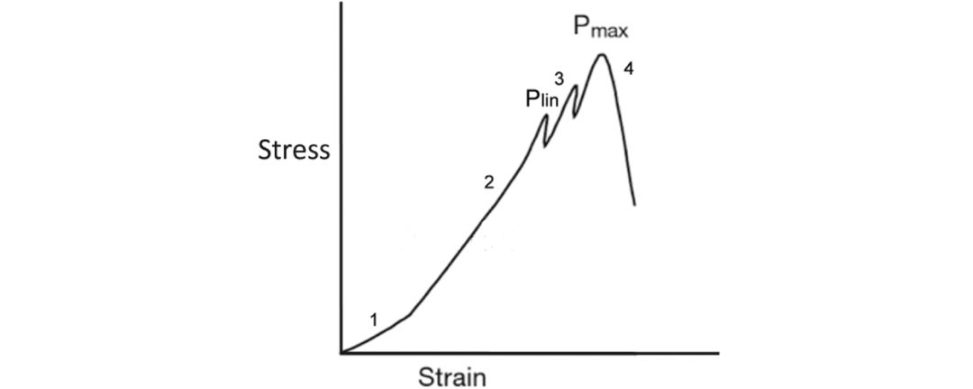
Can you draw me the stress–strain curve for the ligamentum flavum?
The ligamentum flavum has a high percentage of elastin fibres present so its stress–strain curve is completely different to that of the standard ligament/tendon curve (Figure 20.63).
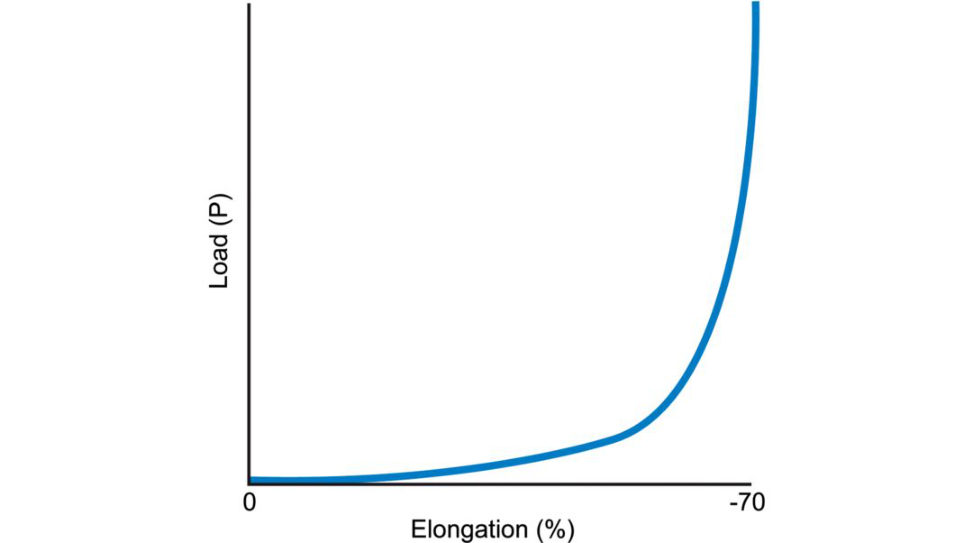
The elastic fibres allow the ligament to return to its original shape and size after the load has been released.
What is the difference between force/elongation curves and stress–strain curves?
Force/elongation curves are essentially the same ass tress–strain curves. For this reason, we often divide load by sample area to get strain and displacement by sample length to get strain. Now any derived quantity is independent of sample size and can be regarded as a true material property.
How do tendons receive their blood supply?
The vascular supply to a tendon arises from three distinct areas: (1) musculotendinous junction; (2) osseotendinous junction; and (3) vessels from various surrounding connective tissue such as the paratenon, mesotenon and vincula. The situation is more complicated insheathed avascular tendons in that the blood supply must enter the mesotenon in vincula that tether the tendon to its sheath incertain locations to supply one tendon segment. Avascular tendon areas receive nutrition via diffusion.
What is tendinopathy?
It is characterized by pain, focal tendon tenderness, decreased strength and movement.
What about pathogenesis of tendinopathy?
The pathogenesis is poorly understood. The exact relationship between tendinopathy and tendon rupture remains unknown. It is thought that tendinopathy could lead to tendon rupture.
What changes are occurring in the tendon?
Tendinopathy can be identified by the following histological characteristics collagen fibril disorganization.
How do we treat tendinopathies?
eccentric exercises (involves active lengthening of muscles, tendons), steroid injections.
What about PRP injections, how do they work?
Platelet-rich plasma (PRP) is a blood derivative containing PRP.
What is the evidence for their use?
35 The main points are that it should not be considered a first-line treatment but reserved for chronic tendinopathy refractory to standard non-operativ e management, such as physiotherapy and steroid injections.
Any other options?
Extracorporeal shock-wave therapy has some benefit in calcified tendinitis of the shoulder , and ultrasonography are other treatment options.
What is the difference between tendinitis and t endinosis.
Tendinosis is degeneration of the tendon. This can often be due to repetiv e microtrauma. Tendinopathy is typically used to describe any problem involving a tendon.
How do tendons and ligaments insert into bone?
There is direct and indirect attachment to bone.
Direct insertion in to bone is similar for tendon and ligament and consists of four zones.
Zone 1. Tendon. Parallel collagen fibres at the end of the tendon or ligament.
Zone 2. Uncalcified fibrocartilage Collagen fibres intermesh with unmineralized fibrocartilage.
Zone 3. Calcified fibrocartilage. Fibrocartilage gradually becomes mineralized.
Zone 4. Bone. Mineralized fibrocartilage merges into cortical bone.
This allows a gradual increase in the stiffness of the tissues other.
Otherwise, high stress levels will occur at the interface due to the difference in stiffness between the two materials. There is a gradual change in structure, composition and mechanical behaviour between tendon/ligament and bone.
The continuous change in tissue composition from tendon/ligament to bone aids in the efficient transfer of load between the two materials.
With indirect insertion the deep la yer anchors to bone via Sharpey’s fibres.
Can you give me any examples of direct and indirect ligament insertion?
ACL direct and indirect superficial.
Figure 20.61 Stress–strain curve of ligament (ACL). The stress–strain curve is initially upwardly concave, but the slope becomes nearly linear in the prefigure phase of tensile loading.
Figure 20.62 Stress–strain curve of tendon tested to failure intension.
Figure 20.63 Stress–strain curve of tendon with large amounts of elastin (ligamentum flavum).
Structured oral examination question 6#
This is a coronal MRI through the thigh, can you tell me what has happened (Figure 20.64)?
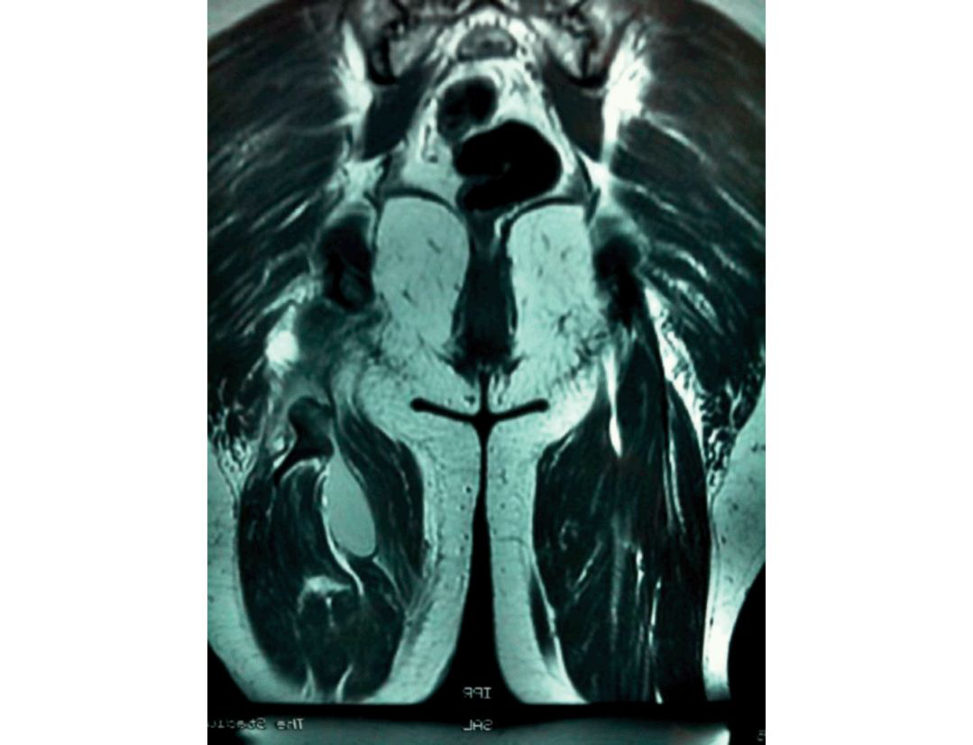
[I was not sure exactly what I was looking at initially!] There appears to be a tendon pulled off the bone, along with an associated haematoma.
Appears to be, or actually is?
There is a definite avulsion of tendon from the bone. Be confident.
What’s the function of the bone attachment?
[I really didn’t know where to go, so I gave a very basic answer!] It represents an interface between bone and tendon.
But what is the function?
It allows a load to be transferred from muscle to bone and stores energy.
What type of load?
Tensile?
What is the difference in general terms between ligaments and tendons?
[I started to talk about ligaments attaching bone to bone!]
Figure 20.64 Coronal T1 MRI image of thigh.
Mark 4 – poor fail.
No, I mean structurally!
[Best answer – up to 99% of dry weight. Remember that tendons and ligaments are made up from 80% EC Mand 20% cells.]
What are the cells found in tendons and ligaments?
Fibroblast represents the vast proportion of cells, a t about 20% of the total mass.
You mentioned collagen, which is the common type?
Type 1 represents the most common type. Mark 5 – fail
That was alit ile guarded, give me a figure.
70–80 % (actually 90%) [I knew what was coming next!]
Tell me about type 1 collagen.
Type 1 collagen consists of three polypeptide chains, two alpha and one beta. [This was wrong, it’s two (alpha 1) and one (alpha 2). Mark 6 – pass
How does this structure retain its stability?
There is cross-linking which is allowed to occur due to hydrogen bonds.
Can you draw a picture of collagen in a ligament and tendon and explain how they differ?
I drew a longitudinal section basically with a well-aligned pattern for a tendon and more haphazard for a ligament. In each la yer they are parallel, but in subsequent layers the collagen is at a slightly different angle.
Can you draw a schematic of this hierarchical structure?
[I talked about the layers as I drew, only got to the fibril and he was bored!] (Figure 20.65) Remember there are lots of different ways to draw this diagram, just use one and learn how to draw it and talk.
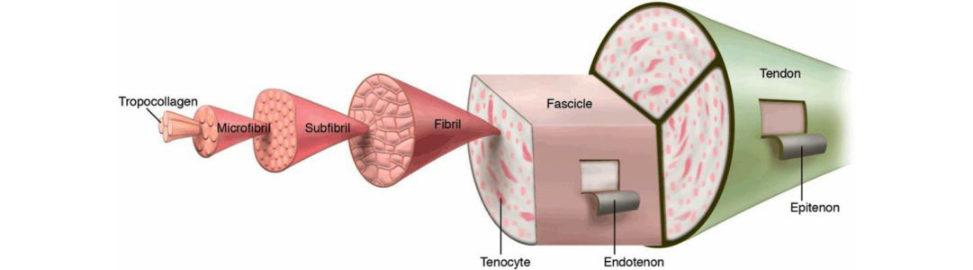
So, what makes up the extracellular matrix?
This essentially is a pr oteoglycan matrix, with plasma proteins and glycoprotein. These proteoglycans bind water and provide a gel-type matrix.
Figure 20.65 Anatomy of a normal tendon.
Mark 7 – good pass
Can you draw the stress–strain curve for tendons and ligaments and talk through it (Figure 20.66)?
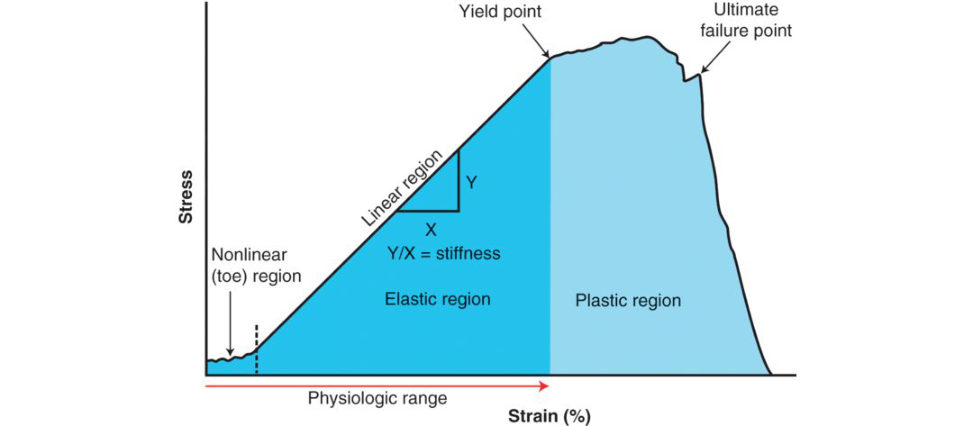
There are four major regions of the stress strain curve: (1) the toe or toe-in region, (2) the linear region and (3) the yield and (4) failure region. In physiological activity , most ligaments and tendons exist in the toe and somewhat in the linear region. As the collagen fibrils become uncrimped, then we see that the collagen fibril backbone itself is being stretched, which gives rise to a stiffer material. Thus, a key concept is that the overall behaviour of ligaments and tendons depends on the individual crimp structure and failure of the collagen fibrils.
Figure 20.66 Stress–strain curve for tendon and ligament.
Mark 8 – excellent Pass
This emphasizes the fact you must be able to talk to a basic level on all topics, or you may flounder very early on in the question. This question will be in your basic science viva and last
5 minutes.
6. Structure and function of the nervous system#
Introduction#
The difficulty, section 3 (nerve injury, section 9 (electrophysiological investigations).
On top of this, the core material is quite dry, the viva questions the y are likely to be asked.
Structured oral examination question 1#
With reference to nerve conduction studies: what do you see indifferent types of injury (axonotmesis, neurotmesis, etc.)? The normal reference ranges? Please draw a cross-section of a nerve and label.
There are three main types of nerve injury: 1. 2. Axonotmesis where the axon is damaged but the supporting connective tissues remain intact. 3. Neurotmesis where both the axon and its sheath are damaged. In neuropraxia, there is focal oedema or breakdown of the myelin sheath which disrupts the nerve’s ability to conduct signals and can lead to slowing or ‘blocking’ of conduction. The axon itself is preserved and so there is no Wallerian degeneration and no secondary degeneration of muscle fibres. There are a number of hallmarks of neuropraxia on nerve conduction studies (NCS) and electromyography (EMG). EMG will show: Electrical silence persisting after 3 weeks in a completely stunned state (there won’t be any fibrillations as the muscle fibre isn’t denervate dand there will be no voluntary activity duet o the severity of the signal block).
Single (or limited) motor units at high rates in isolation in a.
Axonotmesis
Here there is injury primarily to the axon and its myelin sheath, usually following a more severe crush, or even avulsion.
Wallerian degeneration will occur distal to (and alit ile proximal to) the site of the lesion and will spread in an anterograde direction, i.e. peripherally over the coming days. First, they degrade myelin and signal macrophages to remove debris.
When the distances involved in regeneration are long, then a number of factors may preclude successful re-innervation, particularly if the target muscle fibres have atrophied or fibrose din the meantime. Perhaps the most visible manifestation of this is
‘synkinesis’ seen in Bell’s palsy where apa tien t may try to smile and ends up blinking.
NCS will show:
Reduced amplitudes of sensory and motor fibres.
Relative preservation of conduction velocities (noting that some fast fibre dropout.
EMG will show:
3 weeks in the lower limbs as thed enervated muscle fibres upregulate their acetylcholine receptors.
Reduced interference patterns (i.e. fewer motor units being recruited) for the degree of recruitment.
Neurotmesis
Here there is complete destruction of the nerve and surrounding supportive tissues, usually caused by serious injuries such as anatomical severance of nerve and/or extensive avulsion or crushing.
Schwann cell, the perineurium, disruption Prognosis in these situations is usually poor .
NCS will show:
Initial preservation of distal responses for the first 3–5 days for motor studies and 6–10 days for sensory studies until Wallerian degeneration reaches distal regions.
Thereafter there will be absent sensory and motor responses.
EMG will show:
Where axonal loss is severe, there will be an immediate and complete lack of voluntary activity .
For the first few weeks there will only be electrical silence and then fibrillations will appear around
2 weeks later in the upper limbs and 3 weeks later in the lower limbs.
This differentiates this state from severe neuropraxia (see above).
Fibrillations will be abundant and of large amplitude in the first 6 months, and then diminish as the muscle tissue a trophies and/or fibroses.
What are nerve conduction studies?
Nerve conduction tests are used to evaluate the function of mot or and sensory nerves. Sensory nerve action potential (SNAP). Motor nerve conduction studies examine the conduction of a signal along the course of a peripheral motor fibre to its muscle fibres. It is reduced by a reduction in myelin (e.g. external compression or demyelinating conditions).
Please draw a cross-section of a nerve and label (Figure 20.67).
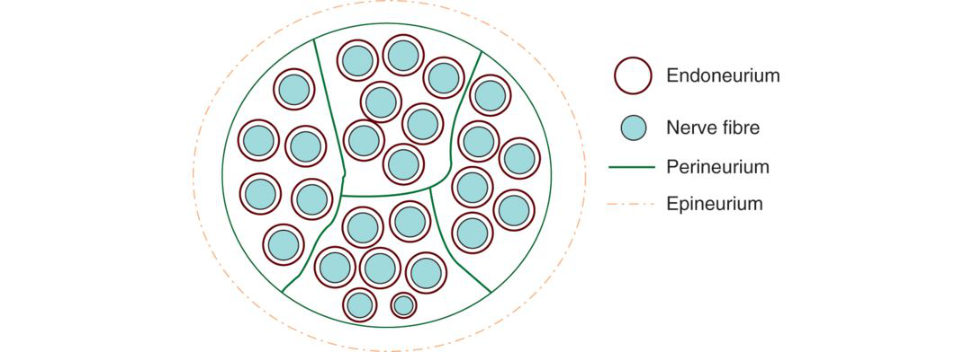
Figure 20.67 Candidate diagram. Cross-section of a nerve fibre.
Axons are grouped together in spatially arranged motor or sensory bundles called fascicles. Groups of fascicles are contained within a peripheral nerve surrounded by a connective tissue la yer called the epineurium. The epineurium is the outermost layer of dense connective tissue surround inga peripheral nerve.
Structured oral examination question 2#
Nerve action potential: explain the graph with relationship of membrane potential to sodium and potassium concentrations exchange pump, channels.
Neurons exhibit a lipoprotein cell membrane, a negative resting cell (around –70 mV), chloride (Cl–) ions within the cells.
The concentration gradient is maintained by:
A metabolically active Na+/K+ exchange pump.
A lipid membrane that prevents the passage of water-soluble ions.
Irregular distribution of permanent ions across anim permeant membrane when a large impermeable organic ion is present on one side.
What is a resting potential?
A resting potential is a term used to describe the electrical potential across the membrane of a cell in its inactive unexcited state.
What is an action potential?
The whole basis of an action potential is based around a change in permeability to sodium and potassium due to opening/closing of voltage-gated channels in response to a stimulus ( Figure 20.68). When the membrane potential increases to around –50 mV, most of the voltage-gated sodium channels rapidly open to allow Na+ to enter the cell, and the membrane potential spikes to more than 30 mV. However, this open channel configuration is unstable and exists for only a fraction of ase cond before a second conformational change occurs with an inactivation g ate to block the sodium channel, thereby stopping the flow of Na+.
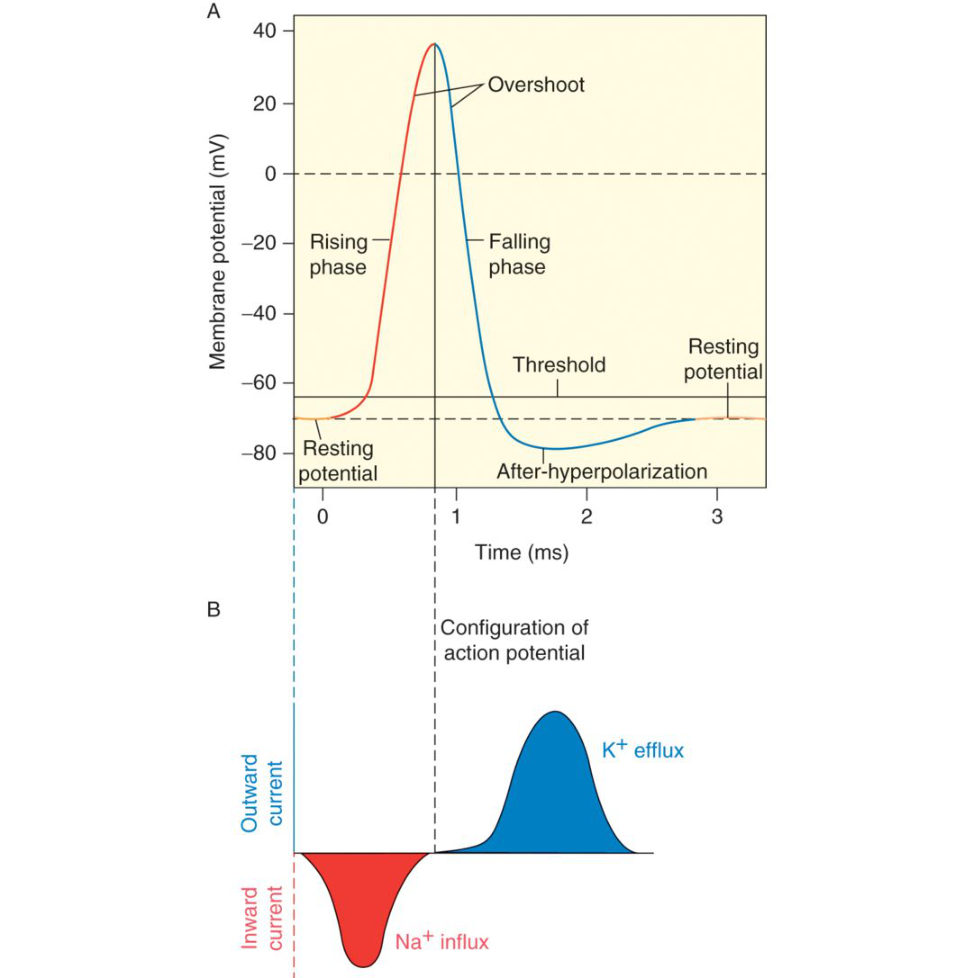
The electrical potential f alls to a level below the original resting potential of –70 mV
(repolarization).
The potassium channels eventually close and the sodium–potassium pump will continue to restore the neuron to its original resting potential.
What do we mean by the threshold stimulus?
The threshold stimulus is the minimum stimulus intensity needed to produce an action potential.
Figure 20.68 Action potential ‘hops’ from one non-myelinated region (Node of Ranvier) to the next (saltatory conduction). 1, Rest ing stage. 2, Depolarization stage. 3, Repolarization. 4, Hyperpolarization.
Structured oral examination question 3#
Nerve picture ... asked how action potential and muscle contraction produced ...
Can you drawout an action potential and t ell me what is going on as you go along (Figure 20.69)?
Neurons possess a membrane potential of –70 mV due to the voltage difference between the intracellular and extracellular space. Action potentials are important for nerve signalling occurring as a result of rapid changes in membrane potential. The threshold stimulus is the minimum stimulus intensity needed to produce an action potential.
Can you be more specific and point out some features of the diagram (Figure 20.70)?
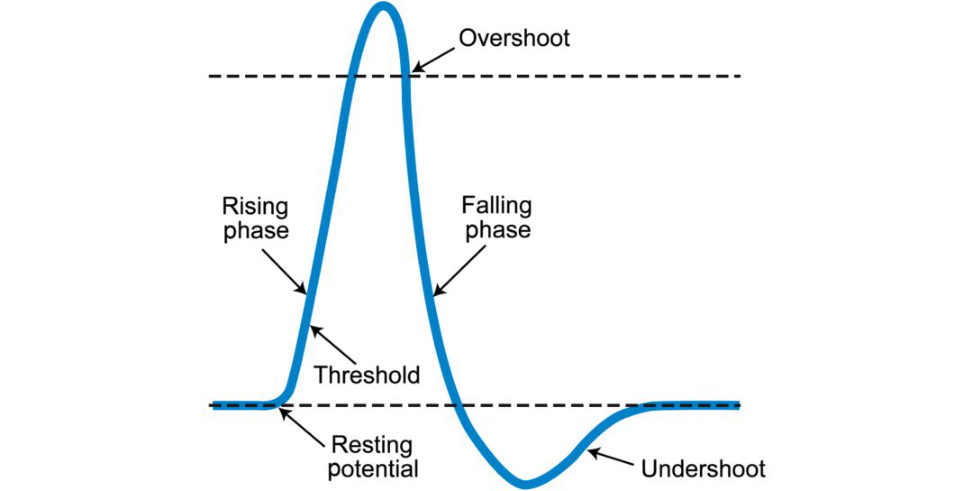
Point out: Threshold: Threshold is the membrane potential a t which enough voltage-gated sodium channels are open so that the relative permeability of the membrane is higher for sodium ions than it is for potassium ions. Rising phase/depolarization : When the inside of the membrane has a negative potential, there is a large driving force on sodium ions. Overshoot: Because of the high permeability to sodium, the membrane potential g oes to a value that is close to the equilibrium potential for sodium (~ +55 mV).
Tell me about the refractory periods.
Refractory periods: the absolute refractory period is due to the inactivation of sodium channels. This means that more depolarizing current is necessary to initiate another action potential.
What are the channels dependent on and how does this cause depolarization?
There is depolarization of the membrane from the initial restings tate of –70 mV due to ionic conductance and the polarity across the cell membrane becomes positive.
What do you mean by ionic conductance?36
Conductance is the inverse of electrical resistance. High conductance indicates that electrical charge moves easily through a membrane. The Na+ channels remain open for 1 ms before closing. The refractory period relates to the channels remaining closed for a few milliseconds and notable to reopen, thus limiting the number of stimuli to which a nerve can respond.
What happens at the motor endplate?
The motor endplate includes the terminal portion of the nerve and the muscle membrane. There is a small gap known as the gap junction that separates the nerve from the muscle at the motor endplate. The presence of an action potential a t the nerve terminal triggers the opening of voltage-gated Ca2+. Ca2+ triggers the release of acetylcholine. This results in a depolarizing potential called an endplate potential spreading over the surface of the muscle fibre.
which elicits the movement of actin, myosin filaments, resulting in muscle contraction.
Acetylcholine is destroyed by an enzyme called acetylcholinesterase that inactivates acetylcholine by detaching it from its receptor.
What is the postsynaptic membrane?
The postsynaptic membrane is the specialized portion of the muscle cell membrane subjacent to the axon terminal.
Do you know of any diseases affecting the neuromuscular junction?
Myasthenia gravis. This is characterized by antibodies that bind to nicotinic acetylcholine receptors with resultingly sis of postsynaptic receptors.
How is a muscle contraction produced?
The Ca2+ then initiates contraction, which is sustained by AT PAs longas Ca2+ ions remain in the sarcoplasm to bind to troponin, which keeps the actin-binding sites ‘unshielded andas longas AT Pis available to drive the cross-bridge cycling and the pulling of actin strands by myosin, the muscle fibre will continue to shorten to an anatomical limit.
What do we mean by the sliding filament mechanism of muscle contraction?
In the 1950s Huxley and Hanson discovered that skeletal muscles were composed of hexagonal latices of actin and myosin filaments and that muscle contraction resulted from relative sliding between the two filaments.
What is a power stroke?
For thin filaments (actin) to slide past thick filaments (myosin) during muscle contraction myosin heads must pull the actin a t the binding sites, detach, re-cock, attach to more binding sites, pull, detach, re-cock, etc. This results in the myosin head pivoting toward the centre of the sarcomere, after which the attached ADP and phosphate group are released.
Detachment: A new molecule of ATP attaches to the myosin head, causing the cross-bridge to detach.
What do we mean by Wallerian degeneration?
When a nerve is cut or crushed Wallerian degeneration occurs. Proximal to the injury retrograde (primary degeneration) occurs to the next Node of Ranvier. Macrophages ingest the fragmented myelin to provide a clean endoneural tube for advancement of regenerating axons.
Figure 20.69 Candidate basic drawing of action potential.
Figure 20.70 Candidate basic drawing of action potential with labels.
Structured oral examination question 4#
Candidate is shown an axial CT of C5 (Figure 20.71) with fracture with discussion of why you do not get cord injury at that level commonly.
Figure 20.71 Axial CT image of C5 burst fracture.
Central cord syndrome (MUD-E)
Results from bleeding, infarction, or oedema to the central grey matter of the spinal cord.
Blood supply comes from periphery to centre.
Motor loss > Sensory
Motor loss affects Upper extremity > Lower extremity
Distal > Proximal
Commonly follows hyper-Extension Injury in an elderly patient with pre-existing spondylosis.
Pain and sensation affected.
Touch and proprioception unaffected.
Dissociative anaesthesia.
Hands and upper extremities are located centrally in corticospinal tract.
Finger and wrist motor function more affected than shoulder and biceps function.
Relatively good prognosis although full recovery rare.
Anterior cord syndrome
Preservation of posterior column-proprioception and vibration sense is intact.
Bilateral loss of motor function, light touch pain and temperature.
Brown–Sequard syndrome
Ipsilateral loss of motor function and pr oprioception/vibr ation.
Contralateral loss of pain and temperature (spinothalamic tract crosses over).
With a C5 fracture, why don’t you get cord injury at that level commonly?
Apa tien t with a burst fracture of the C5 vertebral body. The burst fracture will typically injure the C6 spinal cord situated at the C5 vertebra and also the C4 spinal roots that exit the spinal column between the C4 and C5 vertebrae. Such an injury should cause a loss of sensations in the C4 dermatome and weak deltoids (C4) due to injury to the C4 roots. Due to oedema (swelling of the spinal cord), the biceps (C5) may be initially weak but should recover. A T11 vertebral injury usually results in a L5 lumbar spinal cord level.
Structured oral examination question 5#
Photograph of cut section of median nerve shown at wrist all prepared for surgical repair.
What is this picture (Figure 20.72).
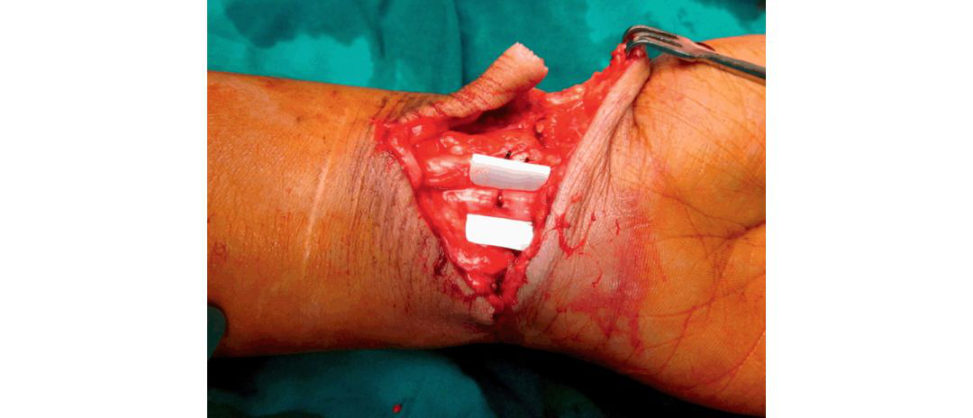
This is picture of a cut nerve at the wrist.
What factors adversely affect recovery of a nerve after repair?
List factors in terms of (1) patient, (2) injury, (3) surgical. Patient 1. 2. Systemic factors. Injury 3. 4. Associated vascular or bony injury. 5. Crush or traction injury. 6. More proximal injury (increased timet o reach target organ). 7. Nerves that supply multiple sites with sensory and motor components. 8. Large gap. Surgical 9. Delay in repair (increased time for end-plate degeneration). 10. Repaired under tension. 11. Infection. 12. Need for nerve graft. 13. Quality of repair.
What happens to a nerve when it is cut? How does it regenerate?
Within 2– 3 days Wallerian degeneration commences, which involves axonal and myelin disintegration both in an antegrade and retrograde direction Antegrade Wallerian degeneration then continues with Schwann cells and macrophage infiltration to remove cell debris, leaving only the basement membrane for about 3–6 weeks. Nerve regeneration then begins on the columns of Schwann cells called Bunger bands. Growth continues a t the restricted rate of 1–3 mm/day, but simultaneously scar tissue interferes with growth.
Any new developments in nerve regeneration?
Sorry, no idea.
Figure 20.72 Median nerve laceration a t wrist.
Structured oral examination question 6#
Can you drawout a neuron for me?
Have an easy to drawout drawing already rehearsed from your exam preparation ( Figure 20.73).
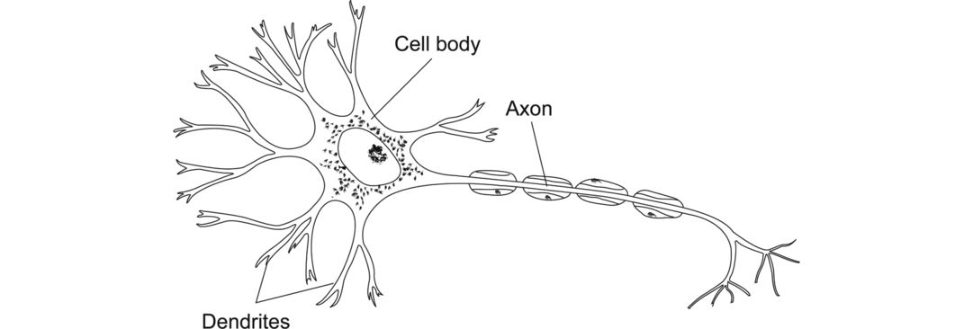
Figure 20.73 Candidate drawing of a neuron.
Neuron
The functional unit of the nerve.
Made up of a cell body and an axon.
Cell body
Gives rise to the axon and dendrites.
Contains most of the neuron’s organelles.
Dendrites
Thin branching extensions of a neuron that receive messages from other cell bodies and conduct impulses towards the cell body.
Sensory.
Axon hillock
Cone-shaped region of an axon where it joins the cell body, the region where the signals travel down the axon are generated.
Axon
The extension of a neuron.
The primary route of conduction to tissues.
Size of axon is between 0.2 and 20 μm.
Longest part of the nerve.
Glial cells
Anchor neurons and form myelin sheath.
In CNS, glial cells are:
Oligodendrocytes (make myelin astrocytes and microglia.
In PNS glial cells are:
Schwann cells.
Size of the nerve axon determines whether it will be myelinated.
Myelinated larger axons
Invaginated by one Schwann cell per axon internode.
Unmyelinated axons
Bundled together surrounded by one Schwann cell – no myelin.
Remak bundle.
Myelin
Lipid- and protein-rich multilaminar substance.
Laid down in the PNS to form a neurilemma.
No neurilemma is present around CNS myelinated axons.
Nodes of Ranvier
Gaps between Schwann cells along an axon.
Structured oral examination question 7#
Draw a cross-section of a nerve and nerve fibre.
[I talked about the three layers and the only four components of a nerve fibre I knew] (Figure 20.74).
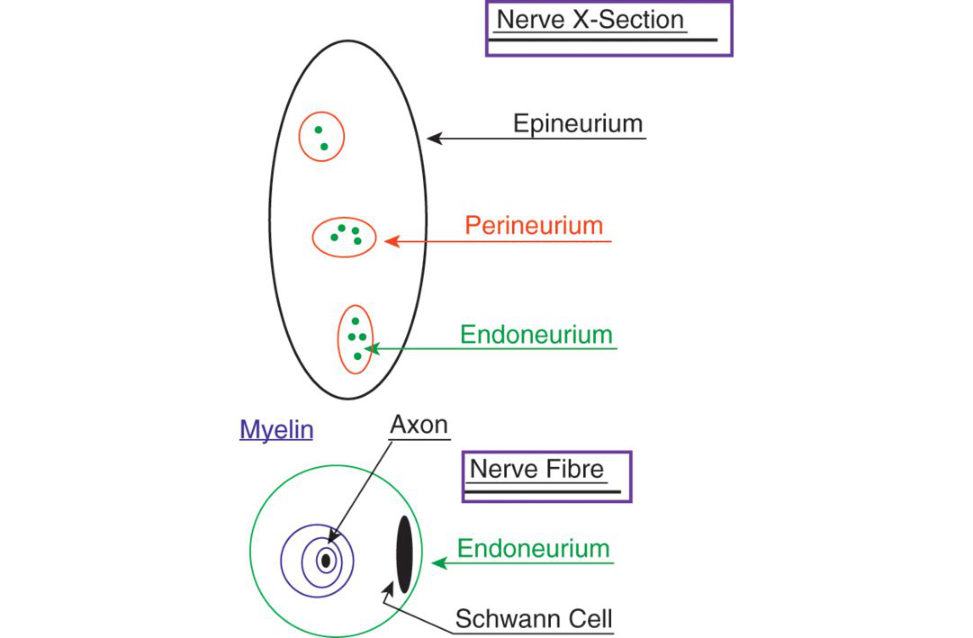
How are nerve injuries classified?
For a score 6 pass all you need to know is Seddon37 and Sunderland.38 Seddon classified the injury originally into three types andS underland defined these into six. Seddon defined neuropraxis as ionic block with possible segmental demyelinization (Sunderland 1), axonotmesis with axon severed but endoneurial tube intactS underland 2), endoneurial tube tornS underland 3) or only epineurium intactS underland 4).
If you cut the median nerve during surgery, what factors affect long-term results?
In children, I believe you get good results in 50% and 40% in adults. The good results in children are actually 75% and 50% in adults, although this drops on a yearly basis year on year. The examiner either didn’t know himself or decided to leave this point.
What will you do if there is a 2-cm graft?
If there is going to be tension on the graft, I would either use a nerve graft or a conduit.
What nerve gratis are available for use?
Sural nerve, which has up to 20 cm, medial or lateral antebrachial cutaneous nerve.
What about nerve conduits?
I have never seen a nerve conduit, but they may allow up to 2 cm of nerve growth. Lucky escape.] A nerve conduit involves reconstruction of a gap defect by the placement of proximal and distal nerve stumps into a tubular repair construct. As a result, these constructs may reduce axonal escape or misdirection improve regeneration in to the distal nerve and enhance functional recovery. Tubular conduits also offer the possibility of avoiding nerve autograft harvest and thereby avoid the potential morbidity of that procedure.
Figure 20.74 Diagram of cross-section of a nerve and nerve fibre.
References
1. Better still, dont mention it.
2. Ellioft DS, Newman KJ, Forward DP, et al. Bone Joint J.
3. Tactical miscalculation from too long a coffee break and non-focused chitchat.
4. Urist MR. Bone: formation by autoinduction Science. 1965;150(3698):893–899.
5. Wall A, Board T. Bone: Formation by Autoinduction . London: Springer; 2014.
6. This can use up a lot of precious time.
7. Much simpler for candidates to not mention them and just stick with the two above.
8. These contradictions make basic science unnecessarily complicated.
9. You could be given a diagram of articular cartilage or be asked to draw it. An excellent candidate with an excellent answer.
A score 6 candidate would discuss enough detail of each layer for a safe pass, but will need alit ile prompting from timet o time.
10. If you are proactive you should be able to draw and talk at the same time, so practise this beforehand.
11. You are only going to be able to do this if you have already practised to perfection drawing out articular cartilage in 30 seconds flat.
12. The candidate was hesitant and needed to be prompted.
13. Dense collagen skin.
14. Depending on your interpretation.
15. The word ‘esoteric’ perfectly describes the basic science viva questioning.
16. All chondrocytes are not the same.
17. You may be asked to drawout a proteoglycan.
18. Looks like a test-tube brush.
19. This is really a subtopic discussion rather than an isolated question.
20. Collagen synthesis and structure can easily take up 5 minutes of a viva, especially if a candidate’s answers are sluggish.
21. Testing clinical application of basic science.
22. If a candidate is poor at drawing diagrams they may need to compensate for this by more detailed diagram practice beforehand. In the big scheme of things, poor artistic ability shouldnt make a massive input into a candidate’s performance and/or mark.
23. The viva usually develops in a slightly different direction than the previous two viva questions.
24. Andrews S, ShriveN, Ronsky J. The shocking truth about meniscus. J Biomech. 2011;44: 2737e40.
25. Smeathers J. Shocking news about discs. Curr Orthop. 1994;8(1):45–48.
26. Providing a convoluted answer.
27. If the examiners let you.
28. The question should not have been asked in its present form if at all.
29. Neumann DA. Maryland Heights, MI: Mosby Elsevier; 2010.
30. Neumann DA. Maryland Heights, MI: Mosby Elsevier; 2010.
31. Coventry MB, Ghormley RK, Kernohan JW. J Bone Joint Surg. 1945;27(3):460– 474.
32. Rudert M, Tillmann B. Acta Orthop Scand. 1993;64(1):37–40.
33. Kastelic J, Galeski AB aer E. The multic omposite structure of tendon. Conn Tiss Res. 1978;6(1):11– 12.
34. Essentially the f our regions of the curve (toe, linear, plastic and failure).
35. Fralinger DJ, Kaplan DJ, Weinberg ME, Strauss EJ, Jazrawi LM. J Bone Joint Surg Rev. 2016;4(6):e5.
36. This info is not contained in your average basic science orthopaedic textbook and requires a deeper level of knowledge to answer.
37. Seddon HJ. Three types of nerve injury. Brain. 1943;66(4):237–288.
38. Sunder landS. Advances in diagnosis and treatment of root and peripheral nerve injury. Adv Neurol. 1978;22:271–305.