Chapter 22 Orthotics and prosthetics
Firas Arnaout
Introduction#
prosthetics is a subject often neglected during revision, hand injuries or amputations.
This chapter attempts to cover the concepts that have been tested previously in the FRCS (Tr & Orth)
The questions and answers provide a high-order thinking framework to build on your answer in the exam oral tables.
Candidates are likely to be shown a clinical photograph, followed by a starting question.
This will be followed by a competency question, which is a pass–fail benchmark.
Remember that examiners are looking for a logical, confident approach.
Learn to draw as you talk, this will assist the examiners to understand what you are drawing, especially if your artistic skills are not the best!
Therefore, agility and the ability to adapt your answer to the specific question asked is an essential skill for the FRCS exam, and this is best mastered through repeated practice with other exam candidates and consultants.
Candidates can also be asked about orthotics and prosthetics in both the MCQ and clinical components of the exam.
Orthotics#
[Hands the candidate a picture of an orthosis] What is an orthosis?
It supports weak muscles and corrects or compensates for skeletal deformity.
What are the ideal characteristics of an orthosis?
The ideal orthotic should bee ffectiv e, lightweight, cosmetically acceptable, easy to put on and take off, and comfortable.
What are the different types of orthotics that you know of? Can you give me examples of each?
They limit joint motion and stabilize flexible deformities. An example is the rocker sole that can lessen the bending forces on an arthritic ors tiff mid foot during the midstance as the foot changes from accepting the w eight-bearing load to pushing off. An example is the TLSO, which can be supportive in the case of fractures or corrective in the case of idiopathic scoliosis. Another example is the AFO, which can be supportive for weak muscle in polio or corrective in cerebral palsy.
What different materials are used to make orthotics?
Orthotic materials need to belight, strong and sufficiently hard-wearing to survive for the duration of their intended use.
[Shows a photo] Can you tell me what this orthosis is made of and the different types of this material that can be used to make an orthosis (Figure 22.1b)?
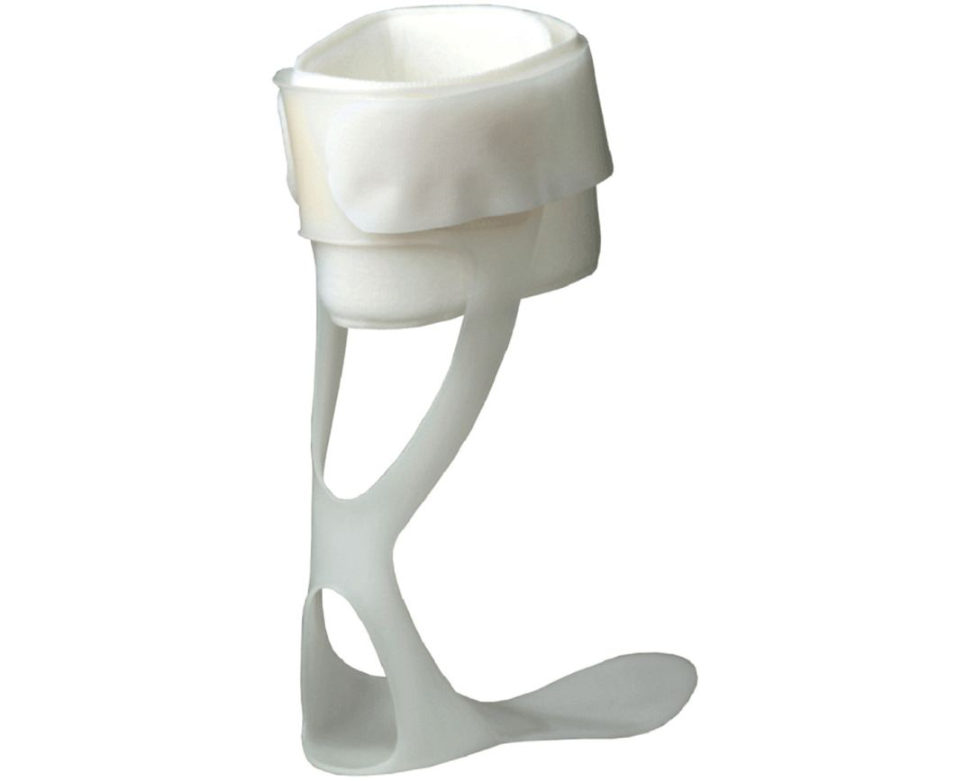
This is made of plastic Plas tic can be thermoseting or thermo forming. However, they are durable, which makes them good for making prostheses and orthoses that are to be put under great stress.
The y can be moulded at high temperatures, such as those used to make AFO (e.g. polyethylene), or a medium temperature, which can be moulded directly on the patients as they have low heat conductivity (eg.
Or moulded at low temperature for making hand therapy splints in clinic; these can be modified if required by gentle heating in water or by a hairdryer (e.g. orthoplast).
How does an orthotic work?
They work according to the three-point pressure principle to control the forces on the body part. This is the same principle that was proposed by Sir Charnley for fracture immobilization.
[Shows the candidate a picture of an orthosis (Figure 22.1d)] Can you describe this orthosis for me?

It could be something you have never seen. In the 1960s the American Academy of Orthopaedic surgeons suggested standard reproducible terminology of orthoses. Described by the joint or region of the body it encompasses.
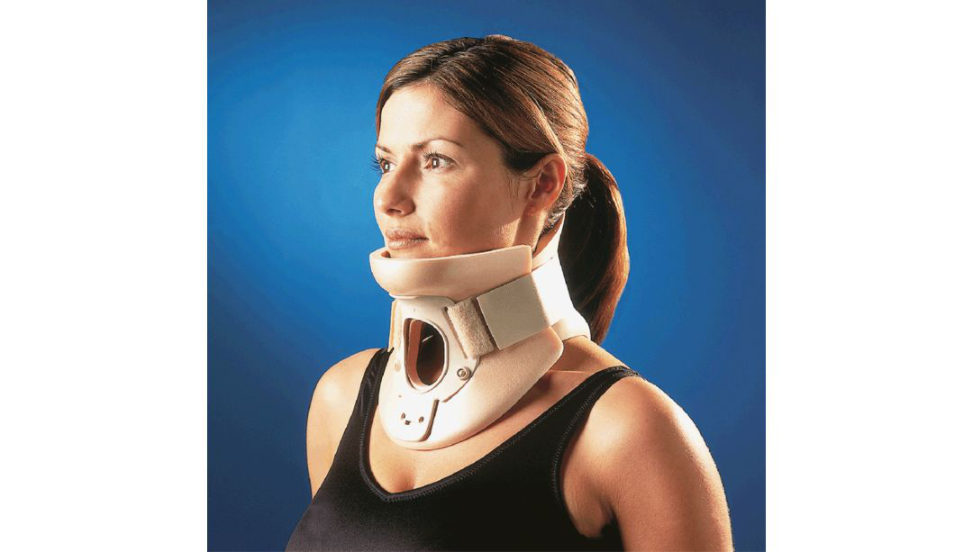
Figure 22.1a Orthosis (courtesy of Blatchford).
Figure 22.1b Plastic foot drop splint (courtesy Blanchford).
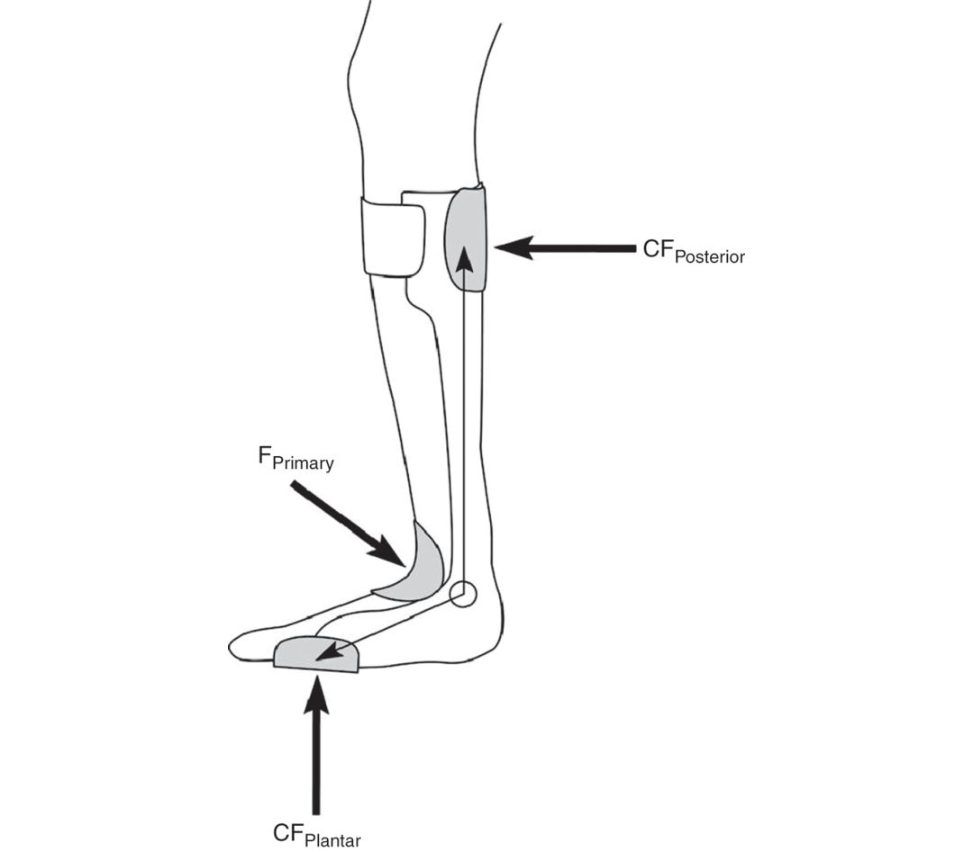
Figure 22.1c Three-point pressure principle for an orthotic.
Figure 22.1d Lightweight carbon fibre AFO (courtesy of Steering Group).
Hence:
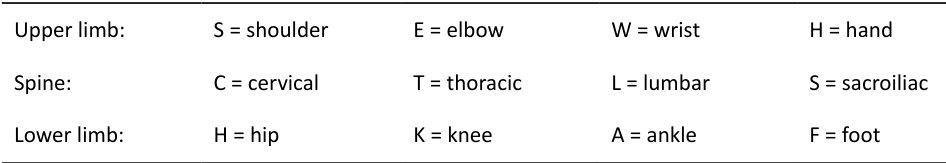
Then describe whether it is corrective or accommodative.
Then describe whether it is static or dynamic.
Then describe the materials it is made from.
[Shows a photo] What can you see and can you explain how it works?
This is a GRAFO (ground reaction ankle and foot orthosis). This is based on Newton’s third law; for every action, the reis an equal and opposite reaction. Therefore, by controlling distal joints one can alter the GRF and affect more proximal joints. GRAFO is formed from a toeplate and rigid ankle in neutral position, and a rigid anterior tibial shell.
GRF can be positioned anterior or posterior to the knee joint to encourage either flexion or extension.
What is functional bracing?
This was advocated by Sarmiento from the USA. In a review paper he published in the BJJ in 2006, he described how his technique has evolved. The principle is to stabilize the fracture while allowing weight-bearing and joint movements.
[Shows a photo] Tell me about these orthoses.
The first one is UCBL (University of California Biomechanics Laboratory) (Figure 22.1e). The second one is a Boston brace (Figure 22.1f), this is used to treat paediatric scoliosis. It is custom-made and works on the principles of three-point fixation. The third one is aChar cot restraint orthotic walker (CROW) (Figure 22.1g), which is used in the end-stage foot disease of diabetes.

How can we prevent complications of orthotics?
The principles to minimize orthotic –limb interface pressures are: 1 – Maximize lever arm.
Figure 22.1e UCBL.
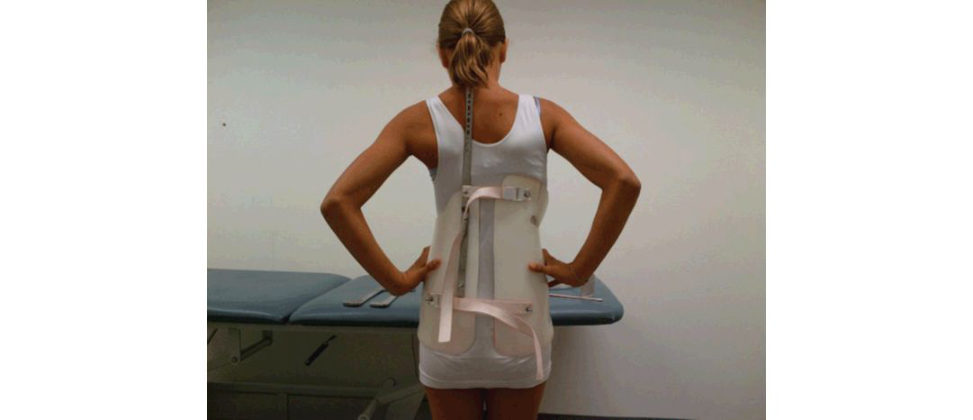
Figure 22.1f Boston brace.

Figure 22.1g Charcot restraint orthotic walker (CROW).
Prosthetics#
[Shows a picture of a below-knee prosthesis (Figure 22.2a)] What is a prosthesis?

Orthotics is that a prosthesis is an artificial device that is externally applied to replace the function or appearance of part of the body.
How can you classify prostheses?
Prostheses can be classified according to structure into exoskeletal or endoskeletal.
Can you describe this prosthesis?
The good candidate who scores 7 and 8 is the one who volunteers relevant information without being asked, hence sending the examiner into a semi-snooze state. 1 – The suspension system that attaches the prosthesis to the residual limb. 2 – The socket which is the connection between the stump and the prosthesis, and is custom- made to the stump shape. Weight-bearing areas for the socket include the heel pad, transtibial, patellar tendon, lateral tibial flare medial tibial flare, transfemoral and ischial tuberosity. 3 – The shank, which is a link between the socket and the terminal device, and also serves to restore length. 4 – The terminal device. 5 – Cosmetic c over.
How is the load transferred from the prosthesis to the limb?
There are two types of load transfer; direct and indirect.
Direct load transferor end-weight bearing is accomplished with knee disarticulation or ankle disarticulationS yme’s).
Indirect load transfer is when amputation is performed through a long bone (BK Aor AKA) and the end of the stump does not take all the weight and the load is transferred indirectly by the total contact method.
What are the different types of knee joint mechanism?
This can be single-axis, which has the advantage of being lightweight, or polycentric with four bars linkage and a moving centre of rotation that provides controlled flexion during the gait cycle – this is good for longer residual limbs. The new design development includes a microprocessor-controlled knee plus a motor. Battery life, weight and cost are significant limiting factors.
[Shows a picture of a foot prosthesis] Can you describe these two prostheses to me and explain the difference?
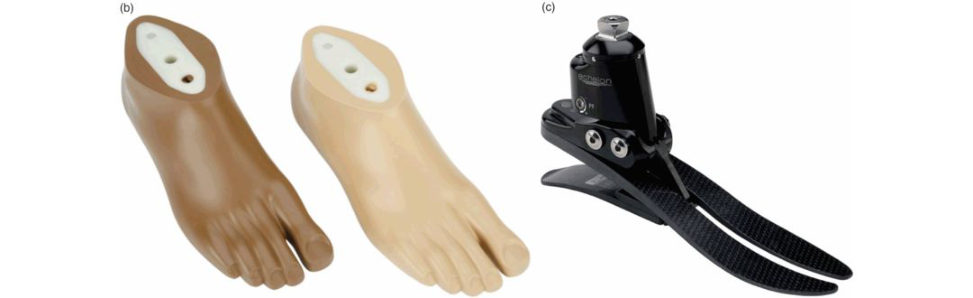
The first photo is of a solid ankle cushioned heel, so-called SACH prosthesis (Figure 22.2b). This is a non-energy-storing device used for patients with low activity levels as it is light inweight, cost-effectiv e and requires litile maintenance. The second photo is of an energy-storing non-articula ting foot prosthesis (Figure 22.2c). The third photo is of an energy-storing and articulating hydraulic prosthesis. These reduce the energy requirements of walking, but are heavy and costly.
[Shows a photo of a below-knee prosthesis] What are the most common complications of this prosthesis? And how do you prevent them?
One of the most common complications is pis toning, which can occur during the swing phase due to ineffective suspension or during the stance phase due to poor socket fit or stump volume changes.
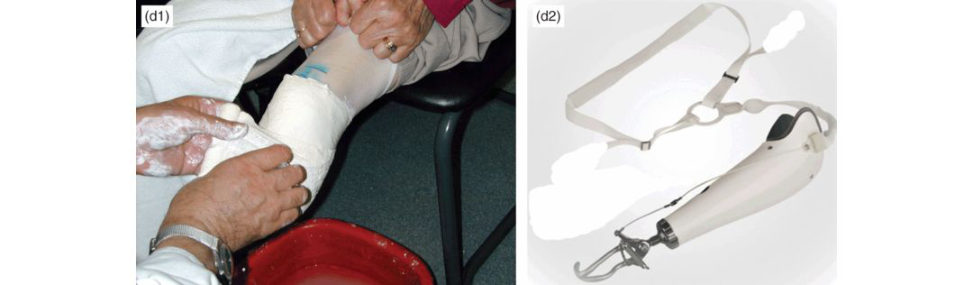
To avoid these, a plaster of Paris mould is made by the prosthetist to mark the pressure-sensitiv e and pressure-relieving areas which are to betaken into account when the prosthetic is being fashioned, trying to minimize the pressure through unprotected bony prominences (Figure 22.2d).
It is important to try to maximize the surface area through, the underlying limb .
The material at the interface should also be moisture-absorbent to avoid maceration of the skin.
[Shows a photo of an upper limb prosthesis] What do you see (Figure 22.e)?
This is an upper limb prosthesis, it looks to be a functional one and is body -powered as it has a figure-of-eight harness.
What different types of upper limb prostheses do you know of (Figure 22.2f)?
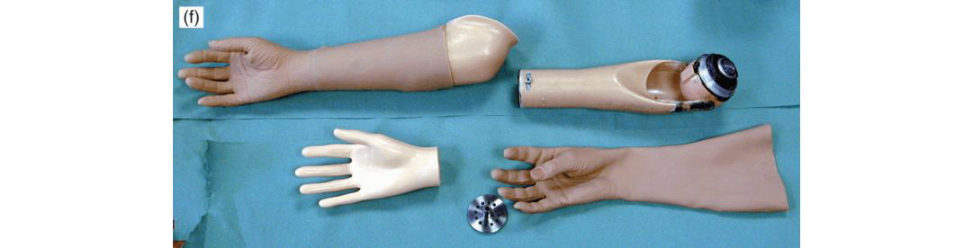
Upper limb prostheses can be cosmetic, functional or myoelectric. Functional prostheses can be body-powered, activated by shoulder movements via a harness and cables; these tend to have poor cosmesis. They also can be myeoelectric, which are powered by muscles sending signals via attached electrodes to the prosthesis. These prostheses are heavy and therefore best-suited fortrans radial amputations.
Figure 22.2a Prosthesis.
Figure 22.2b and 22.c Solid ankle cushioned heel and energy-storing non-articula ting foot prosthesis.
Figure 22.2d Plaster of Paris mould.
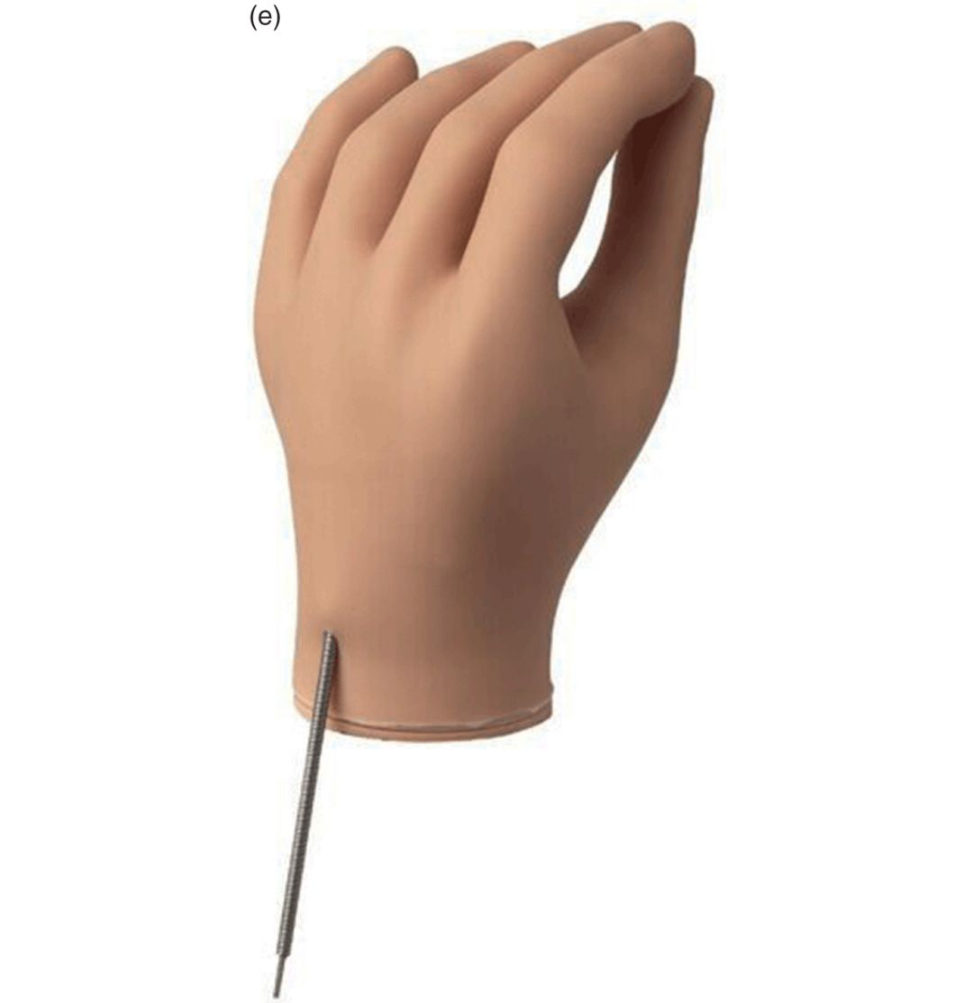
Figure 22.2e Upper limb prosthesis.
Figure 22.2f Upper limb prostheses.