Chapter 25 Tribology and biomaterials
Structured oral examination question 1#
Picture of THA with osteolysis shown.
This is an X-ray of a THA in an elderly patient complaining of pain. What do you see (Figure 25.1)?
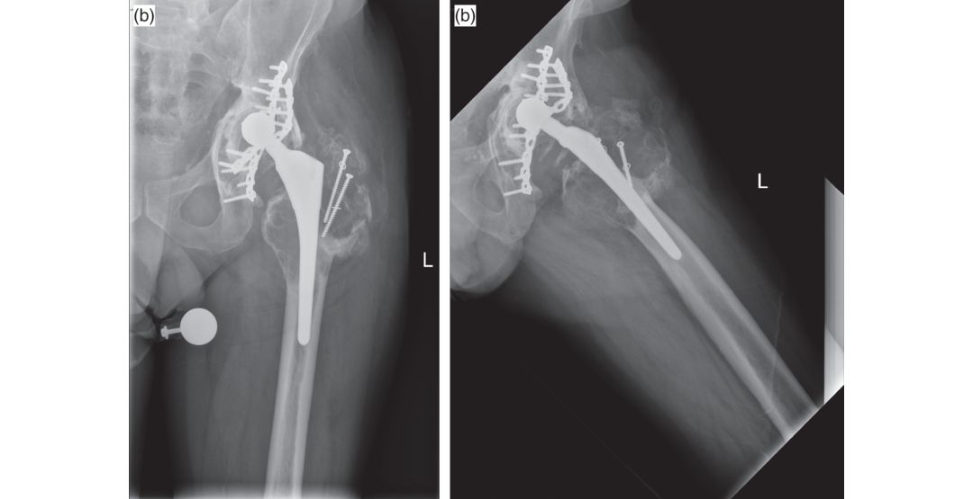
Figure 25.1a and 25.1b Anteroposterior (AP) and lateral radiographs of hybrid THA with areas of osteolysis around greater trochanter.
Plain radiographs of a reverse hybrid THA.
What do you think caused this?
Potential causes are infection, poly w ear ...
Tell me about wear.
Wear is a progressive loss of material from the surface.
What types and modes of wear do you know?
Well there are four modes of wear and various types of wear (I couldn’t remember how many). Mode 1:
Mode 2: Wear from an articulating surface and a non-articula.
Mode 3: Third-body wear, which is particles coming.
Mode 4: Wear between non-articula ting surfaces such.
OK, how about types of wear?
There are mechanical and chemical. Chemical includes corrosive and corrosive freting.
Do you know how we can measure wear?
There are linear and volumetric wear which are two methods of measuring wear. For example, the bigger the femoral head the greater the volumetric wear and the smaller ...
Are you sure? Poly has changed over the last 50 years. So, tell me then, what’s the ideal size of a femoral head?
[I was waiting for him to ask me this question, I had some papers in mind and drawings.] McKee and Farrar [1] used large heads and had minimal dislocation but significant wear, Charnley [2,3] initially used size 41.5-mm diameter femoral heads but had massive wear and early failure. He then.
OK, let’s move on, how does osteolysis happen?
It’s a histiocytic response to wear debris.
OK, what does that mean?
They release osteolytic factors like TNF-alpha, osteoclast-activ ating factor and interleukins. Also, as the patient walks they release the debris into the effective joint space causing further inflammatory response and lysis [4].
References#
1. McKee GK, Watson-Farrar J. Replacement of arthritic
Surg Br. 1966;48:245–259.
2. present and future developments. 1960;1:821–826.
3. Arthroplasty of the hip. 1961;1:1129–1132.
4. Ing hamE, Fisher J. The role of.
2005;26(11):1271–1286.
Structured oral examination question 2#
Tell me about synovial fluid.
Synovial fluid is produced by the synovial membrane in the joint. It is a dialysate of blood plasma without the cloting factors, haemoglobin or RBC. It exhibits non-Newtonian flow characteristics.
Tell me about lubrication.
Lubrication is when a film of lo wer shear strength is present between two bearing surfaces, reducing friction.
What is friction?
The resistance of two surfaces to slide against each other.
Tell me about the two hypotheses surrounding joint lubrication in synovial joints.
The first is fluid-film lubrication, in this hypothesis the joint surfaces are separated by a fluid film which fully supports the applied load, preventing contact between the surfaces. However, realistically, both fluid-film and boundary lubrication occur in synovial joints, depending on the specific joint in question and the particular type of loading applied.
Do you know the lambda ratio?
in fluid film it’s 3 and in boundary it’s less than 1.
Can you tell me about the different types of fluid-film lubrication?
There are various types of lubrication, the y include hydrodynamic lubrication (HD), elastohydrodynamic (EHD), micro-elastohydrodynamic (MEHD), squeeze film, weeping and boosted lubrication. In hydrodynamic lubrication the reis no contact between the joint surfaces.
A model that is more likely in synovial joints is elastohydrodynamic (EHD) lubrication. In EHD lubrication elas tic deformation of the bearing surface enlarges the area of the surface and traps pressurized fluid.
A modification of the elas tohydrodynamic model of lubrication is micr o-elastohydrodynamic lubrication (MEHD). This smoothes out the bearing surface and allows a fluid film to be created which is sufficient for fluid-film lubrication.
Tell me about weeping lubrication.
Contrary to boosted lubrication where the water is compressed into the cartilage leaving behind a concentrated fluid pooled with hyaluronic acid in the joint.
What are asperities?
the taller they are, the rougher the surface, also increasing friction.
OK, what types of lubrication happen in prosthetic joints?
Well, it is believed that boundary lubrication predominates but mixed conditions do occur . For example, ceramics are more hydrophilic than metals, thus they have improved lubrication and lo wer friction ( Figure 25.2).
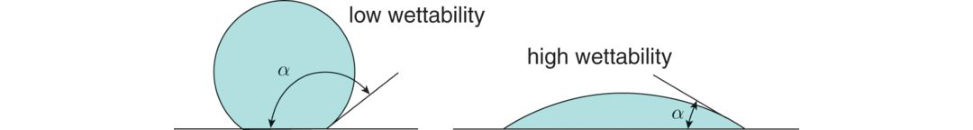
Figure 25.2 Lubrication [I drew this picture at the same time].
OK, so what else decreases friction in the joint?
The cartilage.
So, tell me about cartilage.
The cells are chondrocytes and ECM includes fibres, collagen (mainly Type II), elastin, proteoglycans, cartilage oligomeric proteins (COMP) and cartilage matrix protein (CMP).
If you have answered all questions and the y have time the y might ask you a question to fill the 5-minute time. I used the above definition (cells, matrix and water) to answer questions on bonecartilage, meniscus, ligaments and tendon and just changed the cell component and the ECM (i.e.
Structured oral examination question 3#
Bone
What makes up bone?
Bone is a highly differentiated connective tissue made up of cells (10%) and extracellular matrix 90% (ECM). The ECM contains inorganic and organic matrix, the inorganic matrix includes calcium hydroxyapatite and osteocalcium phosphate. The organic matrix includes collagen Type I, proteoglycans, non-collagen matrix proteins (osteocalcin, osteonectin, os teopontin), growth factors and cytokines. Lamellar bone is mature bone with organized layers and its structure is arranged according to the stress on the bone. Also in flat bones it comprises 80% of the adult bone.
Can you draw cortical bone for me (Figure 25.3a)?
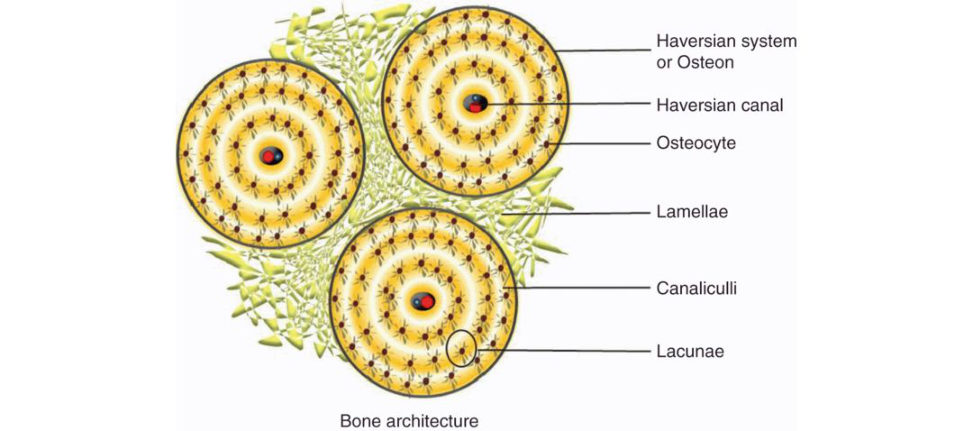
Figure 25.3a Drawing of cortical bone.
Which cell forms the majority of the bone cells?
The osteocyte forms approximately 90% of bone cells, it forms from osteoblasts.
Tell me about the osteoclasts.
Osteoclasts are large multinucleated giant cells; When laying on bone they have a contact area called ruffled borders which increase their surface area.
Bisphosphonates work on the ruffled borders.
I was drawing something like this as I talked (Figure 25.3b).
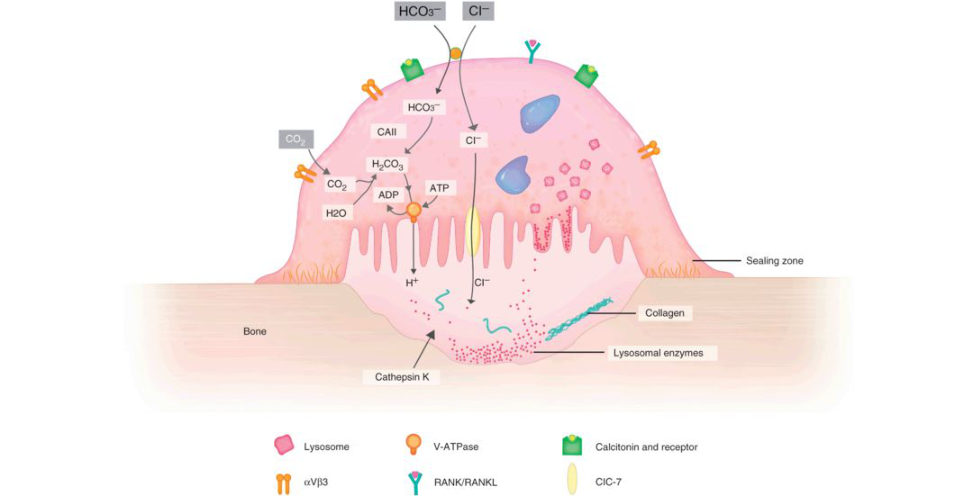
Figure 25.3b Osteoclast.
How does the blood reach it?
Bone receives 5–10% of cardiac output. The nutrient artery enters mid diaphysis and divides into ascending and descending branches supplying the inner two-thirds of the cortex.
How is bone metabolized?
A complex interplay and interaction of various hormones, growth factors and cytokines.
How does vitamin D regulate calcium?
Vitamin D is either taken through diet or activate din the skin by ultraviolet light. In the kidneys it causes increased calcium retention and phosphate excretion ( Figure 25.3c).
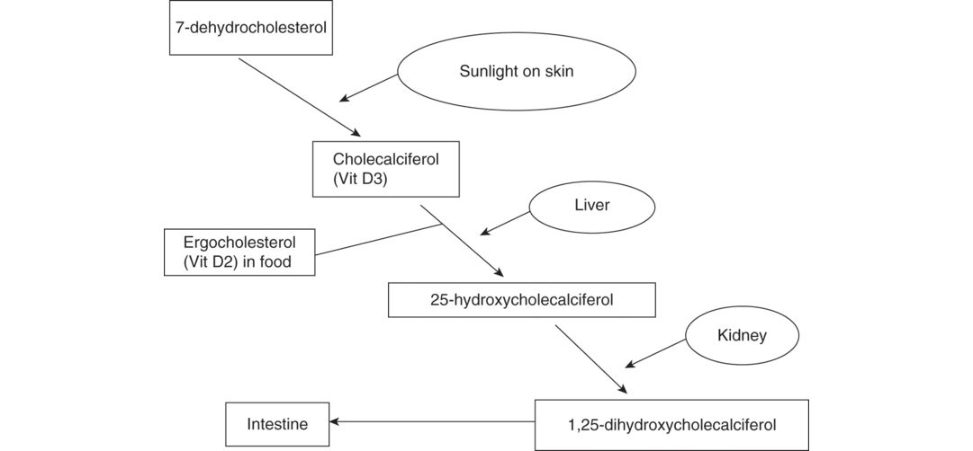
Figure 25.3c Vitamin D metabolism.
Structured oral examination question 4#
Bone gratis
So, you have apa tien t with a tibial plateau fracture on your operating t able and you find a big bony defect that needs filling. How do you approach that?
Bearing in mind this is a basic science.
What types of bone gratis do you know?
There are autogratis, allo gratis and z enogratis. Also , there is demineralized bone matrix (DBM), synthetic, bone morphogenetic protein (BM Pand stem cells. AUTOGRAFT utilizes bone obtained from the same patient receiving it. ALLOGRAFTS are obtained from a different patient than the one receiving it. They are available indifferent methods depending on their processing and preservation, deep fr ozen–70°C, freeze dried –169°C and fresh.
What would you use for your case?
but I would prefer to use autograft as it has no immunogenicity, but it has donor site morbidity whereas allogratis have no donor site morbidity.
Ahhh, what’s graft incorporation?
It is the process by which invasion of the graft by the host cells and the graft is then replaced either partially or completely by host bone or rejected. 1. 2. 3. 4. 5. Remodelling, which continues for years.
So, we know how an autograft is taken, do you know the process of allograft donation and bone banking?
Yes, living donors are consented and in case of cadavers as longas there.
The donors get screened for comorbidities and bloods are taken. Bloods for hepatis B & C , HIV, syphilis and Rhesus status.
The graft g oes through processing of cleaning then preservation. The gr aft gets debrided from.
OK, quickly tell me about the synthetics and what you are going to use for this tibia?
(I realized I have told him all about bone graft but not t old him what I will use). (JBJS Am 2008) performed an RCT of autograft vs. calcium phosphate cementin tibial plateau fractures and showed significantly reduced rates of subsidence, also Buckley published similar results in 2009 in calcaneal fractures.
References#
1. Russell TA, Leighton RK. Comparison of autogenous bone graft and endothermic calcium phosphate.
J Bone Joint Surg Am. 2008;90(10):2057–2061.
2. Johal HS, Buckley RE, Le IL, Leighton RK. A prospective randomized controlled trial
Trauma. 2009;67(4):875–882.
Structured oral examination question 5#
THA stem design
What are these (Figure 25.4a)?

Figure 25.4a Exeter and Charnley femoral stem.
The hip replacement on the left is an Ex eter.
OK. What are the differences between the two?
The Exeter hip replacement is a collarless, polished double-taper cemented hip replacement.
By what biomechanical principles are they supposed to work?
The Exeter femoral stem works by utilizing a t aper slip design and controlled subsidence. The stem will subside on average 1.3 mm in the first 2 years, followed by a period of stability. As the stem is loaded the taper engages into the cement, producing radial hoops stress which is distributed to the bone interface minimizing stress shielding.
relying on achieving mechanical interlock at the bone–cement interface and sufficient adhesion to achieve force transfer.
The load on the femoral head is transmift ed through the [1].
What material are they made of?
The Exeter stem is made of stainless steel alloy (Orthinox), it has high strength with ductility plus.
Which one will you use in your practice and why?
I will use the Exeter stem based on the theories I mentioned before; also it has excellent survivorship in the NJ Rand a.
What is cement?
Cement is a synthetic polymer of methyl methacrylate (PMMA). The important factors that affect cement over time are creep, stress relaxation and fatigue. It functions to fill the defect in between the stem and the bone, act for load transfer, allows modulus matching between implant and bone, and in the case of the taper slip stems, allows controlled subsidence of the stem. It is strong in compression and weaker under tension and has a low elastic (Y oung’s) modulus compared to metal and bone.
Can you draw the relative moduli on a graph and compare it with other materials used in Orthopaedics (Figure 25.4b)? What is 3, what is 2, what is 11?
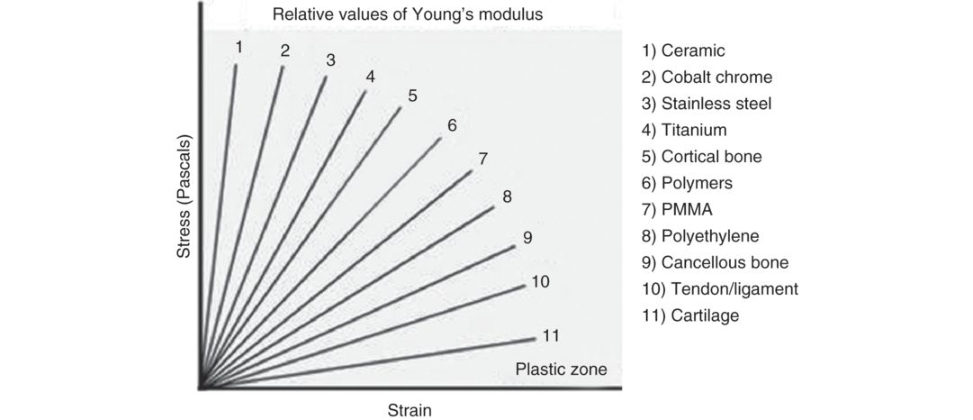
Figure 25.4b Diagram stress/strain curve and Young’s modulus.
Figure 25.4b is important as it tests a candidate’s ability to appreciate.
What are the design principles behind the use of uncemented joint replacements?
The uncemented joint replacement can be put in in two ways. The first is a press-fit design, the secondis a line-to-line fixation. In line-to-line fixation, the bone is prepared to be the same size as the eventual implant, e.g. A cup the same size as the prepared acetabulum is inserted but, in this case, additional fixation, such as screws, is frequently required.
What can you tell me about the surface finish of the implant?
The surface finish allows either bony ingrowth or ongrowth. Ingrowth requires a pore size between 50 and 400 μm, and the percentage of voids within the coating should be between 30% and 40% to maintain mechanical strength.
Do you know anything about the design of the pores?
The porosity of the stem should not be greater 50%.
How do stems fail?
The cemented stems fail in four modes: 1a. 1b. 2. Medial stem pivot. 3. 4. Cantilever bending.
Do you know any name associated with this classification?
Sorry. Gruen’s mode of cemented femoral stem failure.
Reference#
‘Modes of failure’ of cemented stem-type femoral components: 1979;141:17–27.
And the uncemented stems?
Delamination of the HA coating , there is also a mechanism known as flag-staffing. If a relatively small stem is inserted in apa tien t.
References#
1. ShenG. Femoral stem fixation. An engineering interpretation of the long-t erm.
2. The Exeter Universal cemented femoral stem at 20 to 25 years: 2016;98B(11):1441–1449.
Structured oral examination question 6#
Articular cartilage
What do you see (Figure 25.5)?
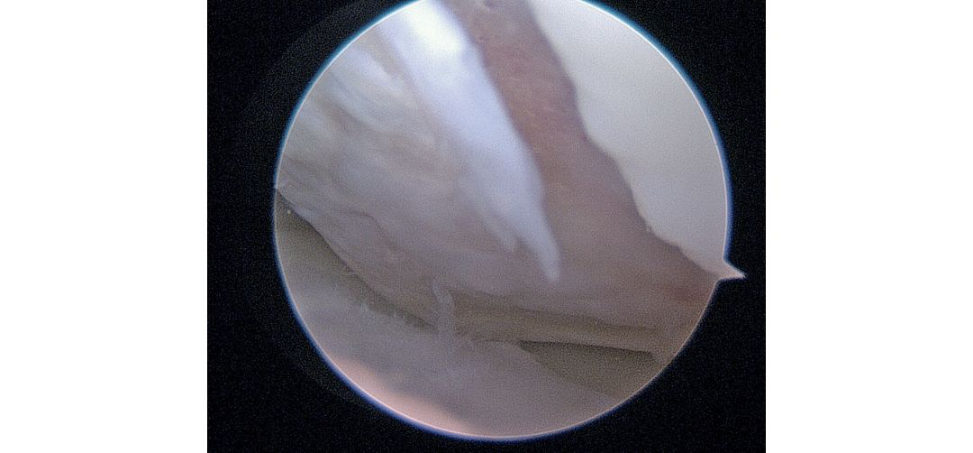
Figure 25.5 Knee arthroscopy picture focal area of cartilage loss.
This is a picture of a knee arthroscopy showing a grade IV cartilage defect.
What is cartilage?
The cells are chondrocytes, and the ECM includes fibres, collagen (mainly Type II), elastin, proteoglycans, cartilage oligomeric proteins (COMP) and cartilage matrix protein (CMP).
Draw a cross-section of cartilage.
I drew all layers, superficial, middle and deep, arcades of Benninghoff, the tidemark and calcific zone.
What is the importance of the tidemark?
The tidemark is the boundary between the calcified and uncalcified cartilage made visible by histological staining.
What is the importance of water in cartilage?
70% of articular cartilage is water; 30% of it exists between the collagen fibres and this is determined by the negative charge of the proteoglycans (PG) which lie within the collagen matrix. Because the PG are bound closely the closeness of the negative charges creates a repulsion force that must be neutralized by positive ions (hydrogen ions in water) in the surrounding fluid.
What happens in osteoarthritis?
The collagen network is disrupted either by trauma or an increase in degradation enzymes concentration – this allows the proteoglycans to atir act more water and softens the articular cartilage thus.

OK, so how will you treat this defect? [Going back to the arthroscopy picture.]
This is grade IV on the Outerbridge Arthroscopic Grading System. Using the hookas a reference, it measures.
How would you do that?
The goal is to allow access of marrow.
I would prepare the defect until I achieved stable vertical walls and the calcified cartilage layer was removed.
3–4 mm apart, looking for the fat droplets.
Postoperatively patients are allowed protected weight-bearing.
If that defect was larger than 4 cm2
however, I will refer this patient to a knee surgeon expert in this field. I’m also aware.
Would you do an ACI?
Well, NICE does recommend it, but it has strict criteria and it has to be done at
Structured oral examination question 7#
Fracture fixation
Tell me about your approach to the fixation of this fracture (Figure 25.6a).
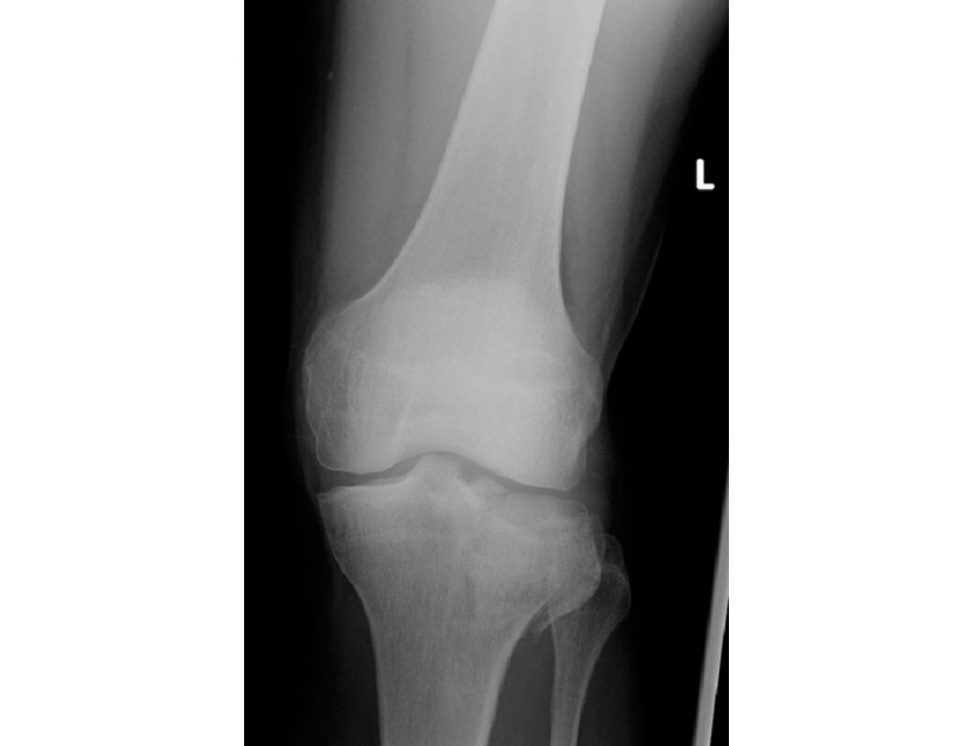
Figure 25.6a Anteroposterior (AP) radiograph of the left knee demonstrating tibial plateau fracture.
First, I would assess the patient the soft tissue and.
Yes, yes, there are no tricks in this question everything is fine with the patient this is a question about the biomechanics of fracture fixation.
Right, OK, this is a plain radiograph of a comminuted displaced, intra-articular fracture of the tibial plateau. The principles regarding the fixation of this fracture are anatomical reduction and absolute stability of the articular.
Tell me about how you would achieve a stable fixation of the articular surface.
I would then use 6.5-mm partially threaded cancellous screws to act as both a subchondral raft and also to compress the fracture fragments and achieve absolute stability and primary bone healing.
Why do you want to achieve absolute stability?
The lack of movement means that the osteoclasts involved in the remodelling of bone will essentially ignore the fracture site and proceed directly across the fracture site using cuting cones, therefore healing by primary bone healing without the formation of callus.
How does a screw work?
A screw converts rotational movement into longitudinal advancement. With a lag screw, the screw is partially threaded therefore as the distal threads bite in the fracture fragment, the proximal smooth barrel.
What are the parts of the screw?
It is easy to draw and illustrate (Figure 25.6b).
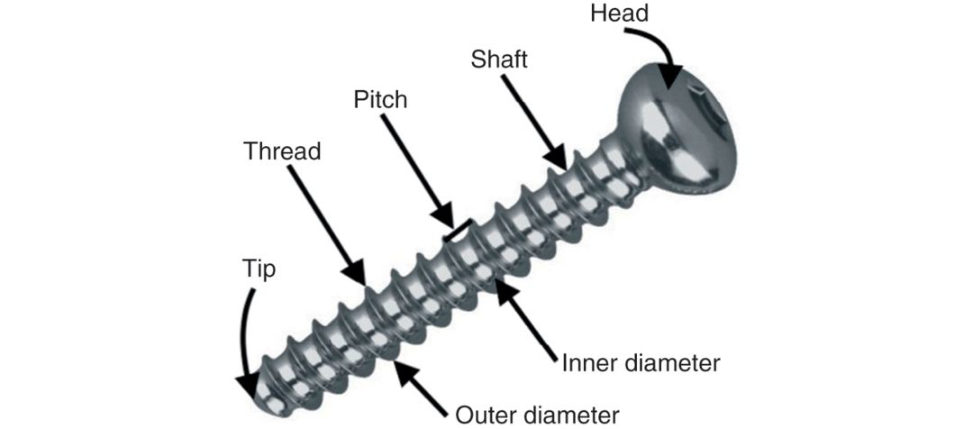
Figure 25.6b Design features of orthopaedic screw.
You said you will use a cancellous screw. What is the main difference between a cancellous and acor tical screw?
Pitch, core to outer diameter and tip. Pitch: closely spaced threads incor tical screws with smaller pitch compared with deeply cut.
Tip: cortical screws are blunt.
You mentioned you will use your plate in bridging mode, what other modes do you know?
But iress, bridging, compression, tension band, neutralization.
So why would you use this one in bridging mode?
If the other features of length, axis and rotation are correct then the fracture would be expected to heal by secondary bone healing with callus formation.
What do you understand by Perren’s strain theory?
Strain is defined as change in length over original length. The theory suggests that the mechanical environment (strain) governs the type of tissue that is laid down between the fracture fragments. Granulation tissue can.
Describe the stages of fracture healing.
The stages are haematoma and inflammation, soft callus (1 week to months), hard callus (1– 4 months) and then remodelling (years). In the first stage, haematoma forms and provides key cells such as macrophages, key inflammatory cytokines (IL1, IL6, TGF-β) are secreted and eventually haematoma is replaced with granulation tissue. Once the fracture has united the final phase of remodelling happens where hard callus is remodelled from woven bone to hard, dense, lamellar bone by the process of osteoclastic resorption followed by osteoblastic bone formation.
What factors influence fracture healing?
Two key factors are involved, mechanical environment and biology. Local factors such as open or closed injury, high mechanism, bone loss, site and type of bone.
Structured oral examination question 8#
Osteoporosis
Could you define osteoporosis for me please?
In 1993 WHO defined osteoporosis as a systemic skeletal disease characterized by low bone mass and deterioration in the microarchitecture, leading to enhanced bone fragility and a consequent increase in fracture risk. It is considered normal when the bone mineral density is within 1 standard deviation of the mean peak bone mass of a healthy 25-year-old. Osteopenia when it is 1–2.5 below the mean and osteoporosis when it is> 2.5 below the mean. Type 1 is most common in women after menopause.
How does a DEX Ascan work?
DEX Ascan is dual-energy X-ray absorptiome try used to assess bone mineral density (BM DIt involves the use of two X-ray beams of different energies passed through the neck of femur or lumbar spine (L2–L4). The result is then compared to a sex- and race-matched BMD of a healthy young adult population (25–30) producing a T score.
This is a DEX Ascan report (Figure 25.7), how would you interpret it?
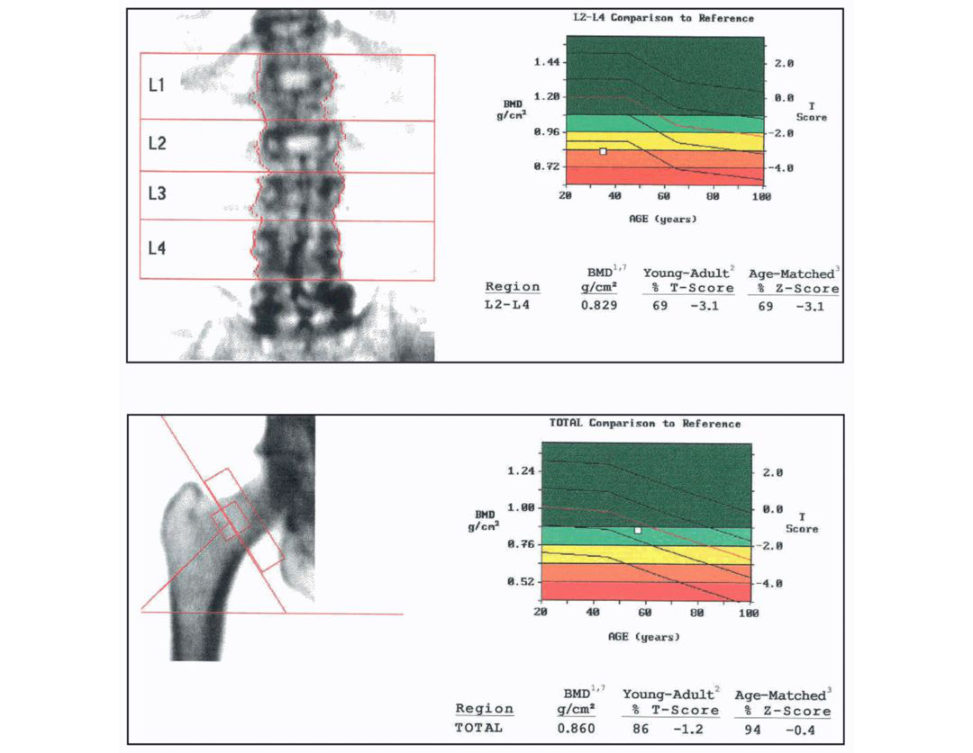
Figure 25.7 DEX Ascan report for proximal femur and lumbar spine.
You are expected to know how to interpret a DEX Ascan report. Simplifying it, I just concentrated on the T score and explained that the risk of fracture approximately doubles for each standard deviation decrease inT score. It depends on what the score is, you then can define it as normal/osteopenia or osteoporosis. 1. 2. 3. 4. T score.
How would you manage this patient?
Prior to obtaining the DEX Ascan I would have performed an initial work up which includes detailed history, examination and bloods. In the history I will.
I would also use the FRAX tool which computes 10-year.
Treatment will be according to the NOGG [3] and NICE guidelines [4].
If the patient is at risk or has confirmed OP, then I would provide them with information regarding lifestyle changes. Lifestyle measures to improve bone health include increasing the.
(www.shef.ac.uk/FRAX)
How much calcium and Vit D do you give them?
In postmenopausal women and older men (> 50 years) at increased risk of fracture a daily dose of 800 IU cholecalciferol should be advised. In postmenopausal women and older men receiving bone-protectiv e.
Which pharmacological treatment would you choose?
Alendronate 70 mg once-weekly or Risedronate are first-line treatments in the majority of cases.
How do bisphosphonates work?
The nitrogen group inhibits protein prenylation with an end result of loss of guanosine triphosphatase (GTPase) formation, this is needed for ruffled border formation and cell survival. The nitrogen-lacking bisphosphonates are metabolized into a non-functional adenosine triphosphate (ATP) analogue, which induces cell apoptosis.
References#
1. Kanis JA, Gluer CC. An update on.
Commift ee of Scientific Advisors, International Osteoporosis Foundation.
2. Kanis JA, McCloskey EV, Johansson HO den A, Melton LJ, 3rd, Khaltaev N.
3. National Osteoporosis Guideline Group (NOGG). 2017.
4. NICE guidelines:
Compston J, Cooper A, Cooper C, et al. Guidelines for the diagnosis and management of.
Compston J, Bowring C, Cooper A, et al. Diagnosis and management of osteoporosis in.
2013;75:392–396.
Structured oral examination question 9#
Antibiotic prophylaxis
Which antibiotic do you use for infection prophylaxis in arthroplasty?
Our hospital policy recommends cefuroxime 1.5 g at induction provided that.
How does cefuroxime work?
Cefuroxime is a beta lactam antibiotic; it inhibits the cr oss-linking of polysaccharides in.
Could you tell me about other antibiotics you know and their mechanism of action?
In general, I divide the antibiotics by their mechanism of action to antibiotics working on.
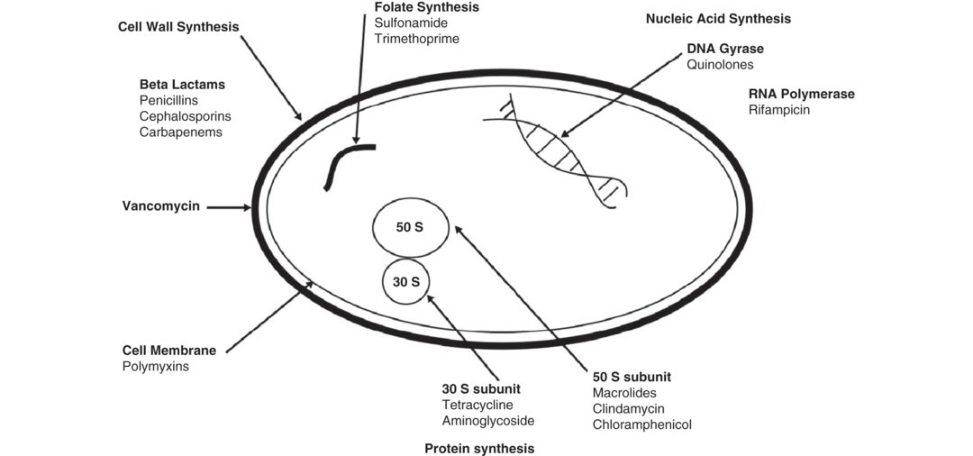
Figure 25.8 Simple bacterium (I drew a simple bacterium which is available in most books).
How do the bacteria develop resistance?
Bacteria can develop resistance either by intrinsic resistance or by acquired resistance to antibiotics. Bacteria can develop the ability to hydrolyze the.
How does MRSA develop resistance?
MRSA develops resistance through a gene called mecA, it produces the enzyme penicillin- binding protein 2a (PBP2a). 20% of patients are staph carriers and 5% are MRSA carriers. Patients must have three negative samples before considering joint arthroplasty.
Carriers are treated with nasal mucopirocin and 4% chlorhexedine.
How do you prevent infections in your department?
laminar flow theatres, minimize theatre traffic, prophylactic IV antibiotics within 1 hour of incision, antibiotic-loaded cement shaving at time of surgery, good hand-washing technique, draping with disposable drapes and ioband, opening of sets within the laminar flow, efficient surgery, good haemostasis and sound wound closure and avoid hypothermia throughout the procedure. however, this is debatable depending on departmental policies, early mobilization and physiotherapy, optimal medical management, timely but safe discharge.
Structured oral examination question 10#
Theatre suite
How would you design a theatre suite?
When designing a theatre suite, the first important aspect is theatre location, it needs to beclose to related facilities such as ITU , A&E, Surgical wards, and Radiology. Outer zone: Clean zone: Disposal zone: sluices (Figure 25.9). Lights should be satellite with 40,000 lux at the wound site. Optimum temperature for the patient is 25°C and for the staff is 19°C. We aim to create a microclimate for the patient to prevent hypothermia by using Bair huggers, warmed mat iress and fluids ...

Figure 25.9 Disposal zone. Four zones: outer zone, clean zone, aseptic z one and disposal zone. The purpose of having zones is to have defined boundaries.
Which ventilation system is used in your department?
We have theatres with a laminar flow ventilation system.
What is laminar flow?
It is a system that produces an entire body of air flowing in one direction with uniform velocity and.
Tell me about the ex-flow Howarth system
[I had no idea, the only thing I could remember was a trumpet type of airflow.
OK, tell me about the vertical laminar flow.
Vertical laminar flow was introduced by Charnley and is the most common type used. It creates a room within a room, with panels from the ceiling to 2 m from the floor. It filters particles of 0.5 μm with 99.9% efficiency.
Does it filter viruses?
Umm, no.
What are the advantages and disadvantages of horizontal vs. vertical laminar flow?
Horizontal is easier to install, but positioning of staff and equipment is restricted because of the sideways flow of air. Vertical laminar flow does not restrict staff and.
What are the sources of infection theatres?
Patient surgeon, instruments and airborne.
How do you measure bacterial contamination in the air?
By slit samplers called Casel lait draws in air over 1 minute which passes overculture plates, which are then incubated over 48 hours and colonies formed are counted. It is measured in.
Do you think laminar flow prevents joint infection?
I believe it is a combination of multiple factors. Results of the MRC trial in 1982 (Lidwell et al.) published in BMJ showed that deep sepsis in arthroplasty was reduced significantly by the use of antibiotic-loaded cement prophylactic IV antibiotics peri operatively, laminar flow and body exhaust suits [1]. Charnley also showed a reduction in deep.
References#
1. Lidwell OM, Lowbury EJ, Why teW, Blowers R, Stanley SJ, LoweD. Effect of ultra clean air in operating.
1982;285:10–14.
2. Charnley J. Postoperative infection after total hip replacement with special reference.
3. Hooper GJ, Rothwell AG, Frampton C, Wyatt MC. The ten-year results of the New Zealand Joint
Registry. J Bone Joint Surg Br. 2011;93(1):85–90.
Structured oral examination question 11#
VTE
How do you set up a VTE protocol in your department?
I would set up a protocol to assess all elective and trauma patients. Risk assessment will be performed using a published tool or guidelines such as the NICE guidelines to balance their risks of VTE against bleeding. They will be stratified in to a low-risk group or a high-risk group. The low-risk group will be offered mechanical prophylaxis only and the high-risk group will be offered both mechanical and pharmacological prophylaxis suitable for them.
What are the current guidelines for elective hip replacement?
The guidelines will be changing in 2018 and aspirin will be considered; however, the current guidelines suggest starting mechanical prophylaxis at admission, either anft-embolism stocking or intermift ent pneumatic compression devices. This should continue un.
What are the guidelines for total knee replacement and how do they differ from total hip replacements?
It is the same protocol, but the duration is shorter 10–14 days.
OK, what is the new guideline that is coming up?
In the new guidelines it is recommended to offer VTE prophylaxis to people undergoing elective hip replacement surgery. LMWH (for 10 days) followed by aspirin (for 28 days). LMWH (for 28 days) combined with anft-embolism stockings (until discharge).
And for knees?
Offer VTE prophylaxis to people undergoing elective knee replacement surgery.
LMWH (for 14 days) combined with anft-embolism stockings.
Rivaroxaban.
Consider intermift ent pneumatic compression if pharmacological prophylaxis is contraindicated in people.
Is there a role for chemical prophylaxis inpatient’s lower limb immobilization?
The new guidelines suggest considering pharmacological VTE prophylaxis for people undergoing foot or ankle surgery, in particular: When total anaesthesia time is greater than 1 hour.
What is the mechanism of action of LMWH, aspirin and Riv aroxaban?
It also prevents formation oft her omboxane A2, which is a prothrombotic agent secreted by platelets. If you have time you can draw the intrinsic and extrinsic pathways and explain where each drug works (Figure 25.10).
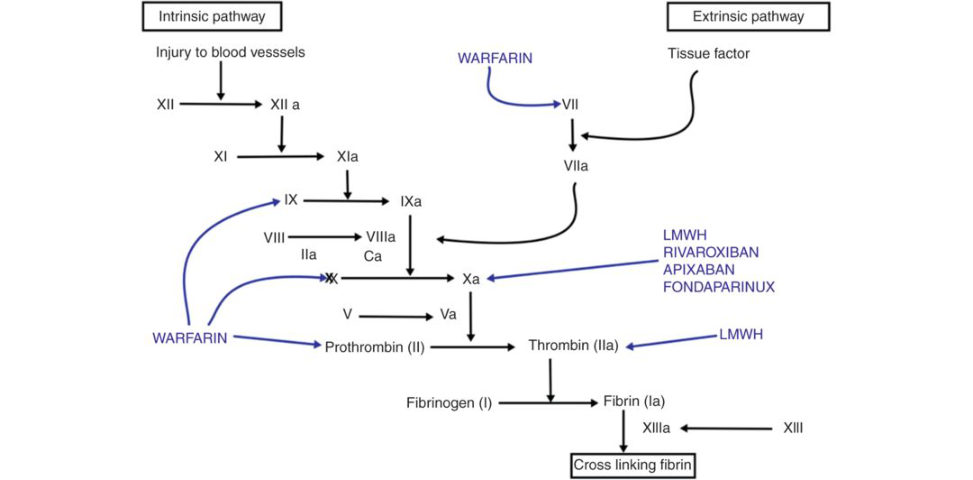
Figure 25.10 Intrinsic and extrinsic cloting pathway .