Chapter 28 Diagnostics
General radiology viva advice#
While candidates will be asked bits and pieces of radiology during a topic discussion the assumption that a stand-alone 5-minute radiology topic is probably too much detailed knowledge for the average candidate (and examiner) to stretch out discussion for is wrong. We know candidates who have had very detailed questioning on the principles of either bone scans or MRI scanners lasting the full 5 minutes of a viva. A candidate scoring 6 would start to runout of steam at 3 minutes or struggle if they are seriously probed about the topic in detail.
The other aspect of radiology which is extremely important and can certainly set you apart from the average candidate is to be able to describe radiographs, MRI and CT scans well.
MRI features well. This is not always an easy skill to acquire, so our suggestion would be to arrange one or two tutorials from a local friendly radiologist who will be able to put you on the spot in describing various scans and radiographs.
Structured oral examination question 1#
Radiographs
Figure 28.1a X-ray of cervical spine lateral (C5–6 dislocation).
What are X-rays?
X-rays are electromagnetic radiations of wavelength 15–0.01 nm.
How are X-rays generated?
X-rays are released on heating a fine tungsten filament to around 2200°C in a vacuum.1 Electrons travelling from the filament (cathode) to the target (anode) convert a small percentage (1%) of their kinetic energy into X-ray photons (by the formation of Bremsstrahlung and characteristic radiation). If a high-speed electron hits the nucleus of a target atom, all its kinetic energy is transformed into a single X-ray photon.
Most high-speed electrons have near or wide misses with the nuclei. The closer the high-speed electron approaches the nuclei, the greater is the electrostatic a tir action on the electron the braking effect, and the greater the energy of the resulting Bremsstrahlung photon.
How does digital radiography work?
The detector generates a digital image that can either be printed or sent to PACS (picture archiving and communication system).
What measures will you take to minimize radiation exposure to staff while using an image intensifier?
The main source of radiation for the surgeon and the team is the scattered radiation from the patient Measures to minimize the radiation exposure to staff are: TDS (time/dis tance/shielding) (1) COMMENT: (2) Distance: (Staff to stay 1 m away from the X-ray source.) (3) Shielding: Lead aprons (0.25 mm thick), thyroid shields and protective goggles.
What is collimation?
Reduction in the size of the window through which the X-rays.
What is the maximum safe dose of occupation-r elated radiation exposure?
The whole-body exposure of 20 mSv over a year is.
What does the picture show and what is its use in theatre (Figure 28.1b)?

Figure 28.1b Dosimeter.
It is used to estimate the radiation dose deposited in an individual wearing the device.
Anything else?
Ideally all orthopaedic surgeons should wear a personal radiation dosimeter This should be in a constant position beneath the protective lead gown to record any personal dose. (1) minimization of radiation use, (2) maximizing the distance between the individual and the X-ray source, beam and scatter, (3) use of lead screens, (4) personal protective garments and (5) monitoring personal exposure dose. 0.01 mS v/day (UK: 2.2 mSv/year). (2) Cosmic radiation during high-altitude flights : 0.001–0.01 mSv/hour. (3) X-ray chest: (4) CT head: (5) CT abdomen: 9.9 mSv equivalent to 500 chest X-rays. (6) X-rays were discovered by German scientist Wilhelm Roentgen in 1895.
(7) Lead aprons help in reducing the exposure by a factor of 4 in lateral view and a factor of 16 in posteroanterior view. Thyroid guards decrease the exposure 2.5 times the normal.
0.5 mm equivalent thickness of lead and the 0.15
(8) Within 2 m of the C-Arm unit.
Structured oral examination question 2#
Ultrasound
What is ultrasound?
Ultrasound is a form of imaging that utilizes high-frequency sound waves to image interfaces between tissues with different.
What are the advantages of ultrasound?
It is safer than CT as it does not emit ionizing radiation and unlike MRI can be used inpatients with cardiac pacemakers or metal clips.
And the disadvantages?
Its main disadvantage is that it is operator-dependent.
What is the physics behind ultrasound imaging?
The passage of electric current through a piezoelectric crystal causes deformation of the crystal surface, inturn producing sound waves. The reflected waves when received back by the transducer cause distortion of the crystal surface, producing a voltage, which is then converted to an image. The duration between the sound wave emission and detection reflects the depth of the tissue beings tudied.1 The amount of energy reflected at the interface between tissues depends on the difference in acoustic impedance of those tissues. The larger the difference in acoustic impedance, the more energy will be reflected, and the brighter the resulting imag e.3 However, at the interface between soft tissue and air or bone, nearly all the w ave’s energy is reflected. It also explains why a coupling gel is required between the probe and patient skin to eliminate air.3 As a sound wave passes through the body it gradually loses its energy in a process called attenuation. This gives greater amplification to those echoes which take longer to return to the transducer, producing an even image.3
Frequency 3–50 MHz with a high-frequency probe used.
Tell me a few of the practical applications of ultrasound in orthopaedics.
Diagnosis and treatment monitoring in developmental dysplasia of the hip (the viva can drift to Graf’s classification of DDH from here). (4) Soft -tissues welling – size, extent, solid or cystic ± guided biopsy. (5) Steroid/anaesthetic injections in to tender areas (plantar fasciitis), joints (subtalar/sub acromial) and around neuromas (Morton’s neuroma) (Figure 28.2).
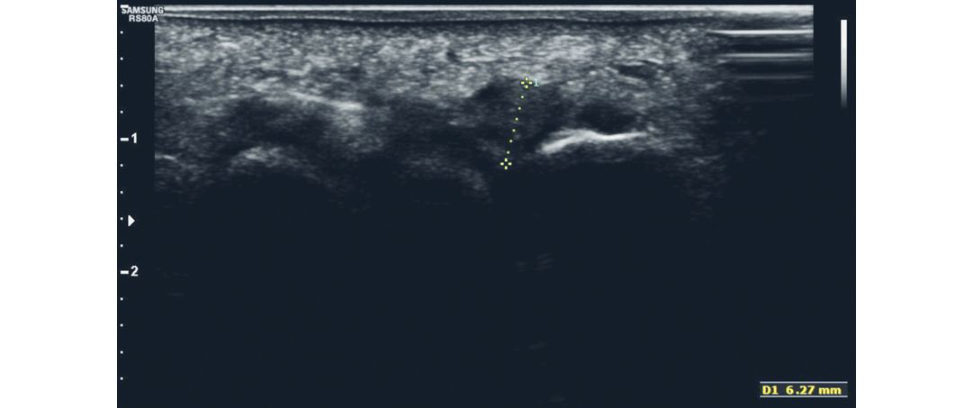
Figure 28.2 Ultrasound scan for interdigital neuroma.
Structured oral examination question 3#
CT scanners
How does a CT scanner work? What are the principles of a CT scanner?
The X-rays are liberated from the axially rotating X -ray tube. With modern multi detector CT transverse (or axial) anatomical sections can be produced with high resolution and reformatted to create reconstructions in an y plane. The 3D CT scans allow better visualization of complex intra-articular fr acture/spinal problems but at the cost of slight loss of definition subtle fractures can fade away/be created). General information (1) CT was discovered by Sir Godfrey Hounsfield (Haye sUK) and the first patient brain scan was done in 1971. Sir Hounsfield was awarded the Joint Nobel prize (with Allan McLeod Cormack of Massachusetis) in 1979. (2) Hounsfield units are a measure of the attenuation coefficient of the tissue being scanned. (Bone = 1000 HU.) Bone windows are usually centred on 300 HU with a width of 1200 HU. (3) Limitations.
Give some orthopaedic indications for CT scan.
(1) Complex peri-articular fractures – for example, fractures of the acetabulum, tibial plafond, tibial plateau, proximal humerus, Lisfranc’s, talus, calcaneum and vertebrae. (3) CT arthrography/myelography (if MRI is contraindicated). (5) Drilling/ablation of osteoid osteoma.
(6) Customized implants: CT scans are increasingly used for.
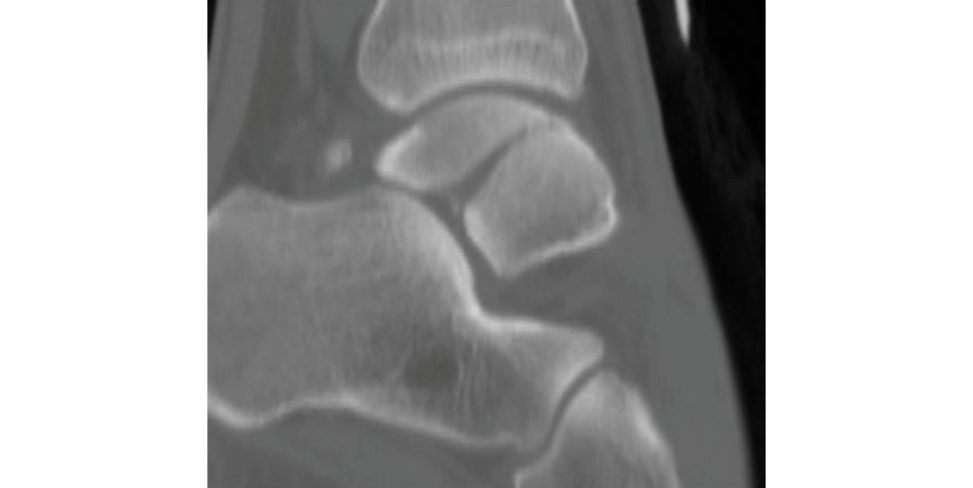
Figure 28.3 Sagift al reformatted image of ankle CT demonstrating t alar body fracture.
Structured oral examination question 4#
MRI scanners
Please describe the findings (Figure 26.4a,b)?
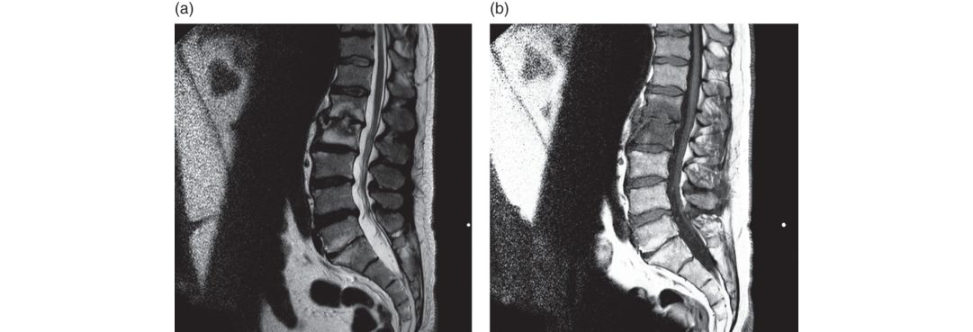
Figure 28.4 Sagift al T2 (a) and sagift al T1 (b) images of the lumbar spine. This demonstrates L1/2-disc space abnormality with adjacent endplate oedema. It could represent either disc space infection or acute inflammatory discovertebral lesion as might beseen in spondylitis.
This is an MRI scan of the lumbo-sacral spine of ... Dated ... Age ...
Is it a T1-weighted image or T2?
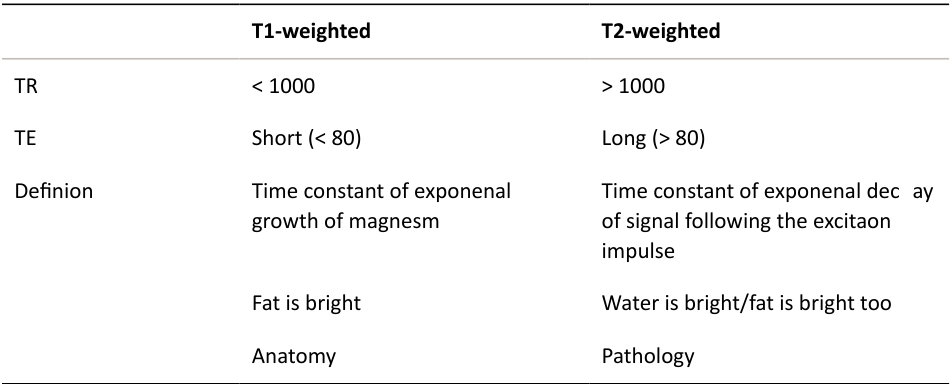
The image to the left is a T1 image as it has a TR (timet o repetion) value of (< 1000), whereas the image on the left is a T2 image (TR > 1000).4 (Don’t rely on fluid/fat signals forjudging the type, as they can be confusing.
What are the differences between T1 and T2 images?
What contrast is generally used with MRI?
An important but rare complication of gadolinium is nephrogenic systemic fibrosis (a fibrosing dermopathy), which has been reported to occur rarely inpatients with Stage 4 renal failure.
What are the contraindications for MRI scan?
(1) Implanted cardiac pacemaker and/or defibrillators. (2) Internal hearing aids/cochlear implants. (3) Implanted nerve stimula tors/dorsal column stimulators. MRI is usually used with extreme caution within the first 6 weeks postoperatively when any metallic clip (including skin clips) or implant has been utilize das they will not have become incorporated securely in tissues.
What else?
Certain types of intracranial aneurysm clips are an absolute contraindication to the use of MRI because excessive, magnetically induced forces can displace these clips and cause serious injury or death.
What are the advantages of MRI use?
MRI provides excellent soft tissue cont ast. It is particularly good for.
What are the disadvantages of MRI use?
and it is not as good as CT for cortical bone imaging.
What are the indications for MR arthrograms?
(1) Shoulder: Suspected capsular/labral tears (Figure 28.4c). (2) Hip: (3) Knee: (4) Wrist: Scapholunate dissociation, TF CC tear, occult scaphoid fracture. (5) Ankle:
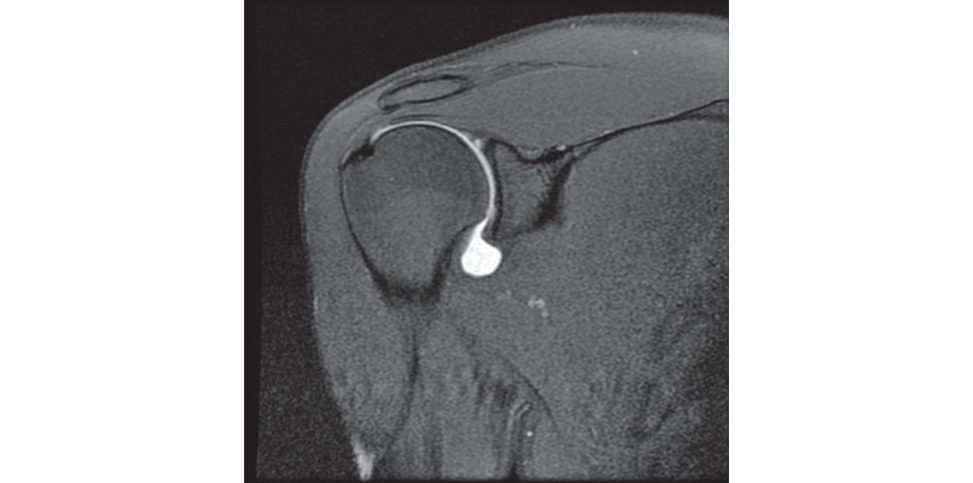
Figure 28.4c MRI arthrogram of shoulder demonstrating dye leakage from rotator cuff tear.
What is the basic principle of an MRI scanner?
The MRI scan involves exploiting the magne tic momen t/nuclear spin property of the hydrogen nucleus (in the tissues) when placed in ast rong magnetic field. Radio waves (64 MHz) are then applied using the transmift er coil. Larmor equation Frequency of precession = gyromagnetic ratio (constant) × strength of the external magnetic field
What do the terms PD, STIR and FATSAT sequences mean?
PD = Proton density-weighted image. It is commonly.
FAT S AT and STIR are both sequences used.
FAT S AT : It can be applied to T1/T2/PD sequences.
T1 fat-saturated sequences are commonly used in MR arthrography and after the administration of contrast.
STIR : Short tau inversion recovery. This is a very robust, commonly used sequence, which.
What is TE?
When a second radiofrequency pulse is applied after the first one is turned off, then the time duration between the first wave and the echo formation is termed TE.
What is extremity MRI?
Extremity MRI involves placement of only the involved extremity in the magnetic bore, while the rest of the body remains outside.5 Advantages are: (2) Improved patient comfort and reduced claustrophobia.
What is your option if the patient is claustrophobic in an MRI scanner?
Open MRI scanner ± sedation. Imaging artefacts 1. The f at image is slightly shifted with reference to the water image, hence low signal lines can sometimes beseen where these two are shifted away, or high signal lines can beseen where they overlap. 2. T1- weighted images are less susceptible to metal artefacts than T2 images. Hence MARS (metal artefact reduction sequences) are commonly applied to study tissues around hip resurfacing implants.
3. Magic angle artefact: tendons normally yield low signals in all sequences due to low T2 relaxation times. However , if the collagen fibres of the tendon make an angle of 55° to the external magnetic.
Structured oral examination question 5#
Bone densitometry
What is bone densitometry?
Bone densitometry, also called dual-energy X-ray absorptiome try or DEX Ascan, uses simultaneous measurement of the passage through the body of X-rays with two different energies.

What are its uses?
(2) Assessment of the effect of treatment for osteoporosis. (4) Evaluation of preventive measure for bone loss associated with ageing/metabolic disorders. (5) Measure periprosthetic bone loss (particularly cementless hip arthroplasty).
OK. You have now started bisphosphonates on this patient for osteoporosis, how will you find out whether your treatment has been effective Will you repeat the bone density scan? When?
The average annual increase in BM Din patients treated with alendronate is about 0.0085 g/cm2. This change is smaller than the typical year-to-year (within-person) BMD variation of 0.013 g/cm2. After 3 years of treatment, 97.5% of patients taking alendronate had an increase in hip BMD of at least 0.019 g/cm2, with a strong correlation between hip and spine measurements.
Hence, if needed I would repeat the bone density scan after 3 years, to evaluate efficacy of the treatment
Name some techniques used to measure bone density in the axial skeleton? (The same question can be asked regarding appendicular skeleton.)
(1) DEXA. (2) Quantitative CT (rarely used). (3) Quantitative MRI (rarely used).
Does DEXA measure true bone density or apparent? (A rather pointed question!)
DEXA measures apparent density (obviously) as it is a two-dimensional measurement quantified ing /cm2. Quantitative CT gives a volumetric (three-dimensional).
Which of the bone density measurement techniques can differentiate between cortical and trabecular bone?
Quantitative CT and quantitative MRI.
What is FRAX score?
FRAX (Fracture Risk Assessment Tool) is the tool used to assess 10-year probability of hip/major osteoporotic fracture of patient sIt integrates clinical risk factors with bone mineral densitometry for femoral neck.
What is the Singh and Maini index for osteoporosis?10
The Singh index has been described on the basis of the presence/attenuation of various compressile/tensile trabeculae.
Any concerns with using the Singh index for measuring osteoporosis?
The Singh index traditionally was used in the diagnosis and classification of osteoporosis. DEX Ascan provides a more precise estimate of bone mineral density and is considered the gold standard for diagnosis and quantification of osteoporosis (Figure 28.5).
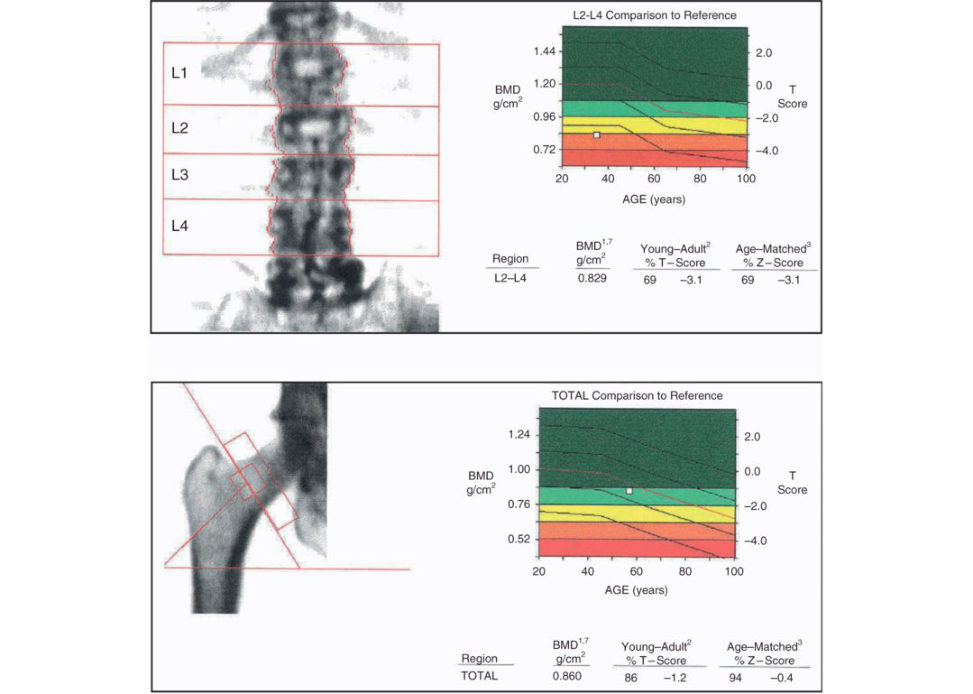
Figure 28.5 DEX Ascan.
Structured oral examination question 6#
Bone scanning
What are the principles of bone scanning? How does a bone scan work?
Bone scan involves the intravenous injection of 99mT -MDP (technetium methylene diphosphonate compound). The gamma camera contains sodium iodide crystals, which absorb 99mT gamma rays. Some features of 99mT-MDP that could be asked by the examiners: (1) Half-life: urine – 70% of the administered dose is excreted within 24 hours. (4) Emits only gamma rays (not alpha or beta).
What is a SPECT scan and give any uses.
The scans are obtained with an arc of 360° around the patient The images can then be reconstructed in axial, coronal and sagift al planes. Sequential imaging with SPECT and CT with the patient in the same position can provide increased diagnostic accuracy by allowing fusion of the anatomical images.11
What is PET scan and what is it used for?
It involves injection of 18F fluoro-2-deoxy-glucose (FDG), which is a glucose analogue. 110 minutes. Successful chemotherapy can cause a decrease in uptake compared to scans before starting chemother apy.1
What is the duration for which a bone scan can be positive following a fracture?
The dynamic flow component can remain positive foras longas 2–3 weeks following the fracture before returning to normal. The delayed static sc an is usually positive for 6 months–2 years due to continuing bone healing and remodelling.
What are the phases of a bone scan?
Timing following injection Significance Use Name
Timing following injection Significance Use

(2) Vascular soft -tissue abnormalities such as tumours
(3) Dating of traumatic lesions such as fractures

(5) Tumour: osteoid osteoma and osteoblastoma, especially spine
(6) Primary malignant bone tumours, benign bone tumours
(7) Painful joint arthroplasty
(8) Avascular necrosis
(9) Paget’s disease
Delayed 24 hours – –
What is a ‘flare phenomenon’ in bone scan?
The paradoxical increase in uptake and size on bone scan following chemotherapy for metastatic lesions, despite clinical improvement. This can.
Why is a bone scan not the best investigation to study the extent of a bone tumour?
The malignant neoplastic lesions may show increased uptake beyond the actual extent of the tumour due to the presence of hyperaemia and bone oedema occurring
How does 67gallium localize insites of infection?
(1) Gallium is taken up by neutrophils as well as bacteria. (2) Binding to lactoferrin/plasma transferrin. (4) Increased capillary permeability.
What advice will you give the patient after a bone scan?
(3) If travelling abroad in the 7 days following the scan, take a doctor’s note along asports and airports have very sensitive radiation detectors which may pickup tiny amounts of radioactivity remaining after the scan.
This is a bone scan of apa tien t with a painful hip arthroplasty. What do you think (Figures 28.6a and b)?
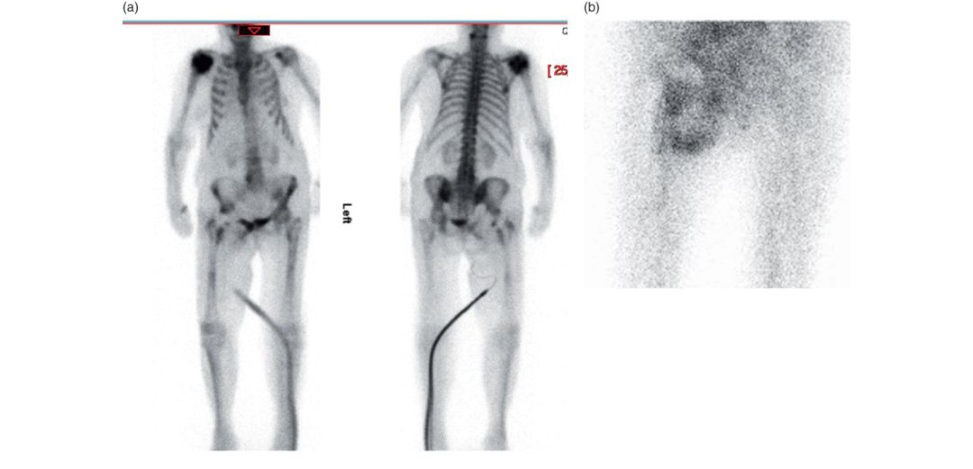
Figure 28.6 The hypervascular abnormality seen on images is suggestive of a soft -tissue abscess with a necrotic centre, possibly related to infection of the right hip prosthesis.
The bone scan images are abnormal. They show a large area of intense hypervascularity at.
Describe the role of a bone scan in the investigations for a painful arthroplasty.
In cases of cemented hip and knee replacements, the bone scan can remain positive for up to 1 year following the operation. In the case of an uncemented THR, there can be increased uptake around the distal tip of the femoral stem for many years postoperatively. The reactive bone uptake in total knee replacement may persist up to 36 months after surgery. Painful arthroplasty, more than 1-year postoperative: Gallium- and indium-labelled WBC scans are more specific for infection.
Structured oral examination question 7#
Nerve conduction studies
What are nerve conduction studies?
Nerve conduction studies examine the electrical function of nerves and muscles. They can detect loss of axons by looking.
How are they performed?
The sensory responses are called SNAPs (sensory action potentials) ( Figure 28.7). Their responses are called CMAPs (compound muscle action potentials) ( Figure 28.8). Here, the extensor digitorum communis (EDC) muscle is being assessed (Figure 28.9).
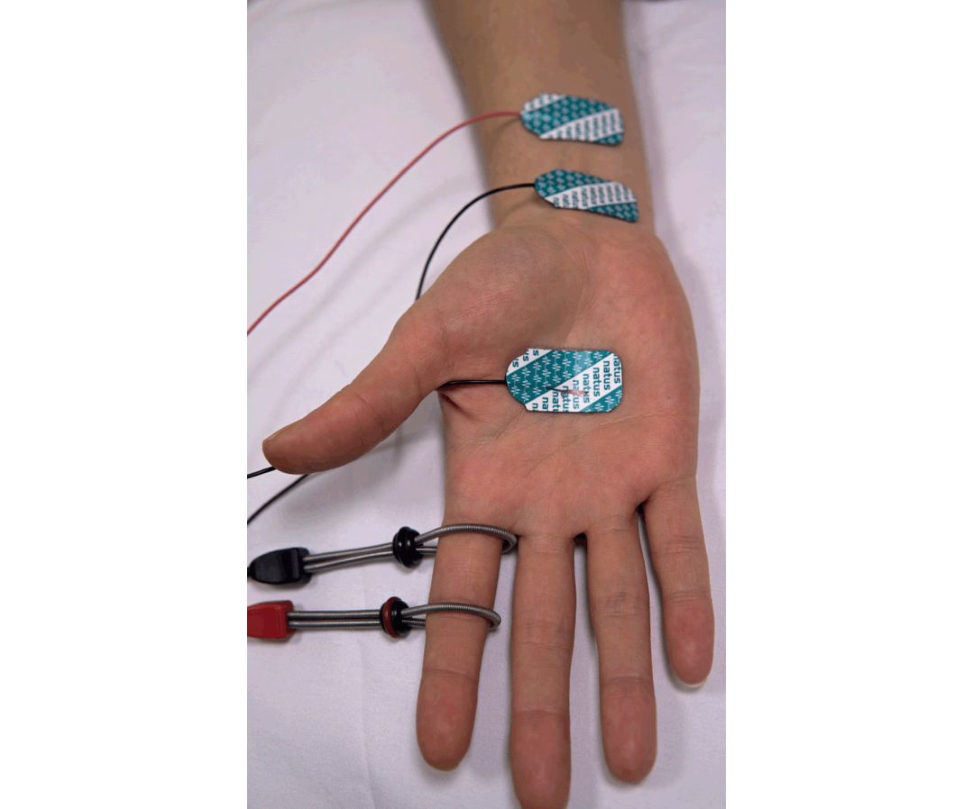
Figure 28.7 Sensory testing orthodromic stimulation using ring electrodes) of the median innervated digit II.
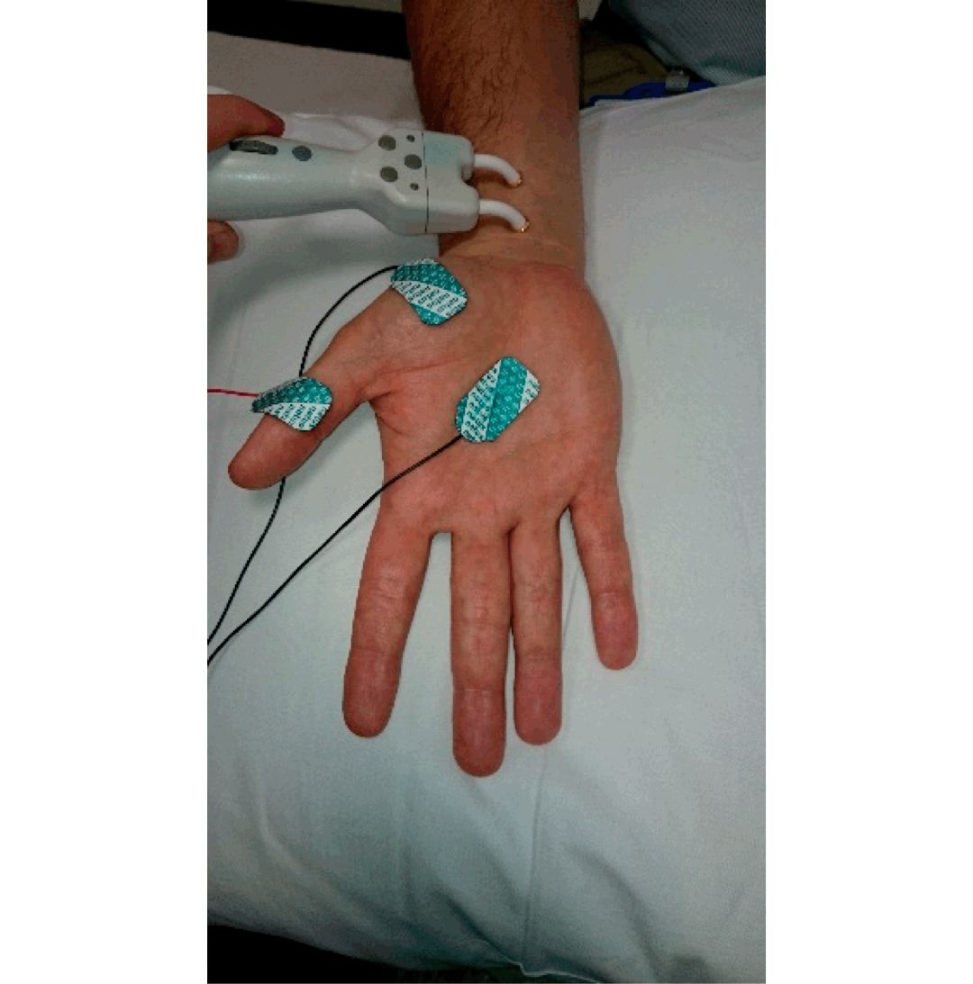
Figure 28.8 Motor testing of the median innervated abductor pollicis brevis (APB) muscle.
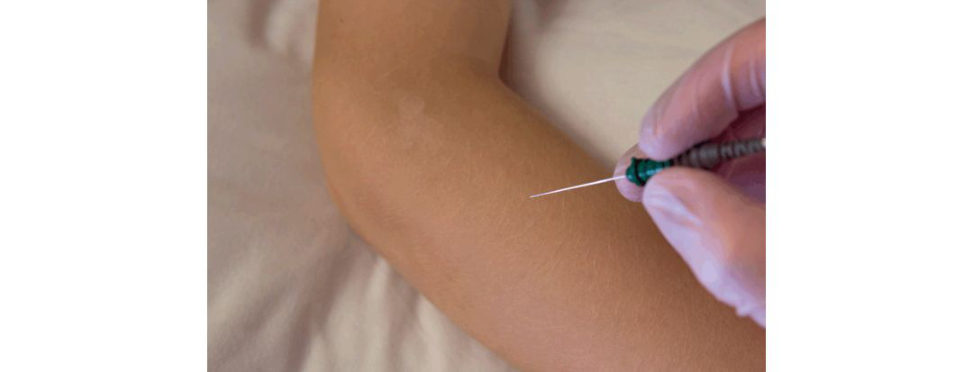
Figure 28.9 EMG studies.
Why are the SNAPs so important and draw the anatomy.
SNAPs determine whether a nerve lesion is post-ganglionic (i.e. Because the dorsal root ganglion (DR Gis the cell body of the peripheral nerves, and is located outside of the intervertebral foramina, they tend to be spared from radicular compression, even if their dorsal roots are compressed (Figure 28.10).
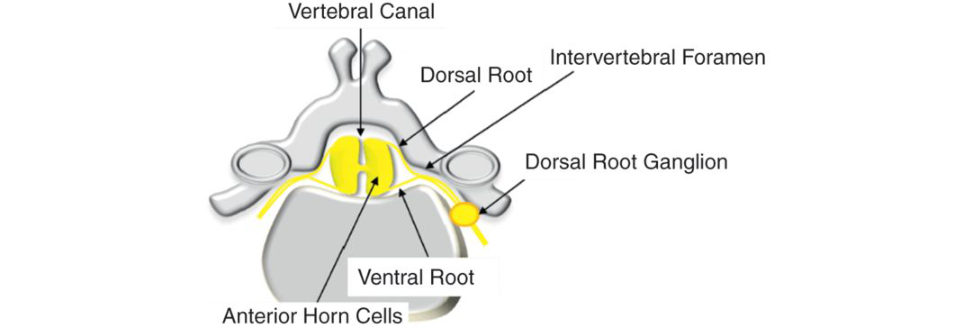
Figure 28.10 Cross-sectional arrangement of dorsal root ganglion.
Structured oral examination question 8#
Nerve conduction studies
Tell me some of the uses of nerve conduction studies? What are the indications for nerve conduction studies?
Nerve conduction studies (NCS) are used to assess peripheral nerves. (1) The presence and severity of peripheral nerve dysfunction. (2) Whether it is axonal or demyelinating. (3) Localization and distribution. (4) Clues to the underlying aetiology . (5) Prognosis.
What is latency, amplitude and conduction velocity?
Latency = time between the stimulus discharge and the onset of response in milliseconds. For sensory nerves where stimulation and recording are directly over the nerve, this is the distance between the stimulation site and the recording site (mm) and divided by the time for signal transmission (ms) (Figure 28.11). This will therefore include not only the time taken for the current topass along the nerve, but also the time taken for neuromuscular transmission and then muscle membrane depolarization and contraction. Hence the calculation will be the distance (mm) between proximal and distal stimulating sites / (proximal latency (ms) – distal latency (ms)) (Figure 28.12).
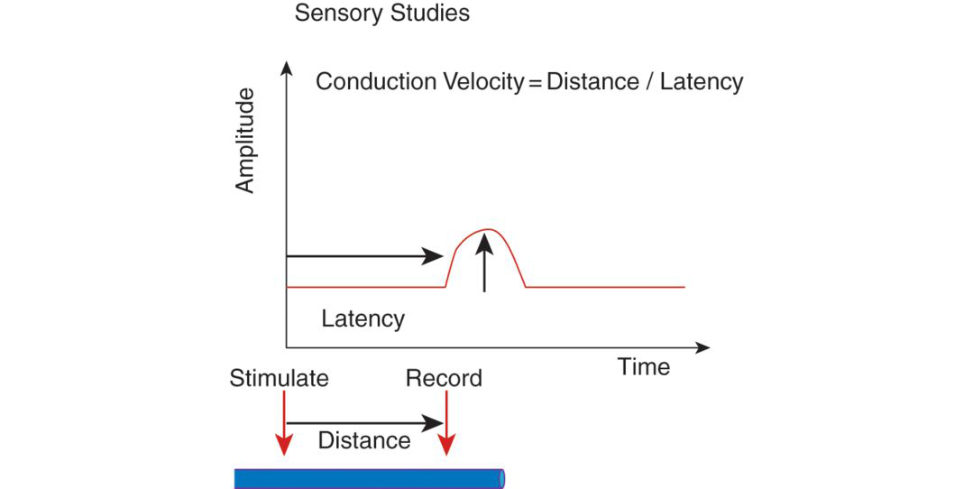
Figure 28.11 Sensory conduction velocity.
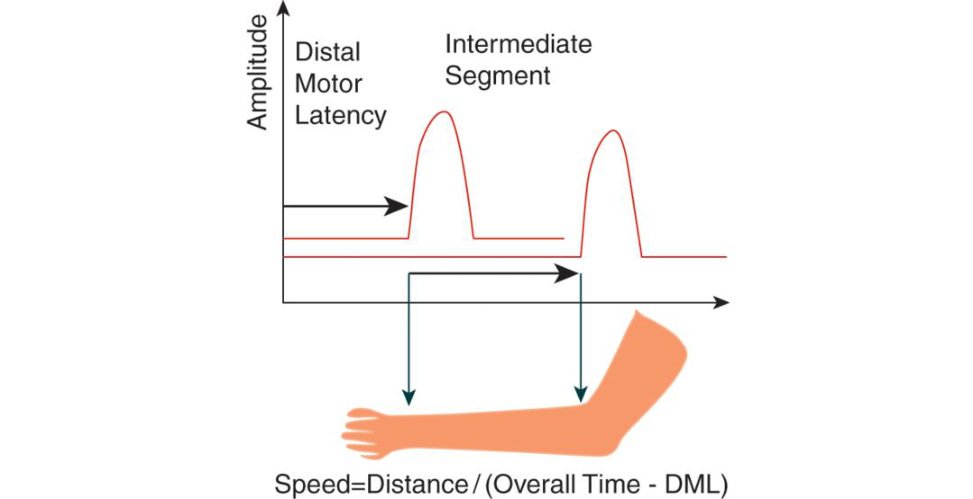
Figure 28.12 Motor conduction velocity.
What is the normal conduction velocity?
Conduction velocities are sensitive to temperature, as cooling slows the velocities Performing NCS in the upper limbs above 32°C is therefore a standard of practice to avoid misdiagnosing conditions such as carpal tunnel syndrome.
What is supramaximal stimulation?
When electrically stimulating the nerve sit is important to ensure that all the nerve fibres are fully stimulated to their maximum response. Failure to ensure this will result in inaccurate readings. It is one of the most common reasons.
What are orthodromic and antidromic potentials?
Nerve fibres are designed to transmit their signal in one direction only by voltage and time- gating mechanisms. F or sensory nerves this is from the peripheries toward the central nervous system (CNS). Motor nerves transmit signals from the CNS to the peripheral nerves and then muscles. However, when nerves are externally stimulate das in NCS, depolarization is bidirectional. Int heUK, orthodromic responses are preferred in the hands as they provide the most accurate take off latencies which are important for evaluating carpal tunnel. Antidromic potentials are generally larger amplitude because the sensors are closer to the underlying nerve but are more susceptible to signal artefacts due to co- stimulation of mot or fibres (Figure 28.13).
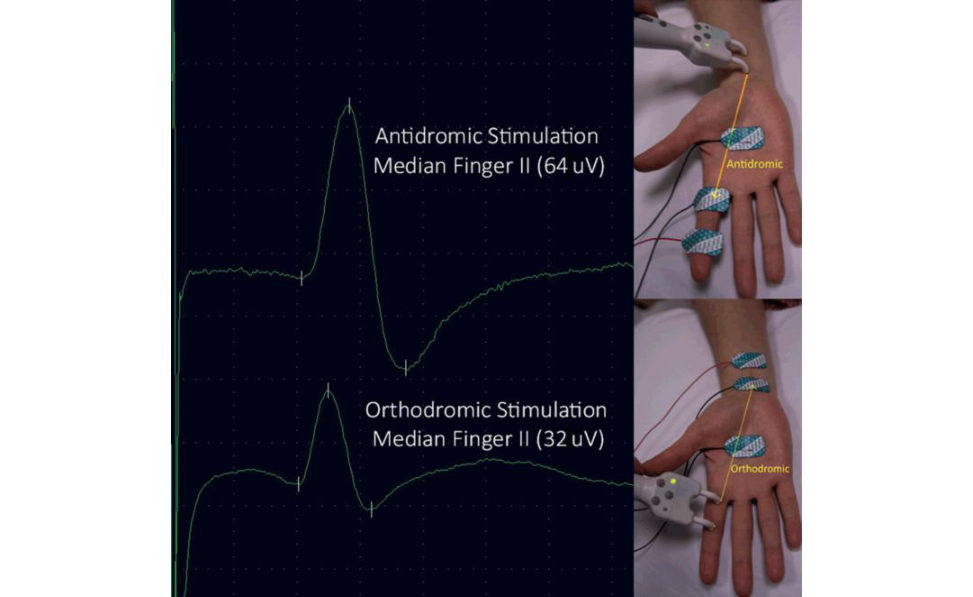
Figure 28.13 Note the difference in amplitude produced by orthodromic and antidromic stimulation.
What are the usual SNAP values you would expect to see in a healthy individual and is there an easy way to remember them?
If one takes an average build 40-year-old, the minimal SNAP amplitudes will be 5, 10, 15 microvolts for the ulnar, median and radial responses respectively, and 5 and 10 microvolts for the superficial peroneal and sural SNAPs.
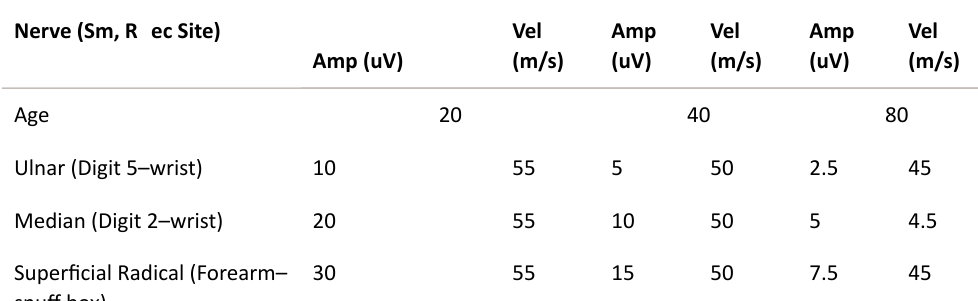
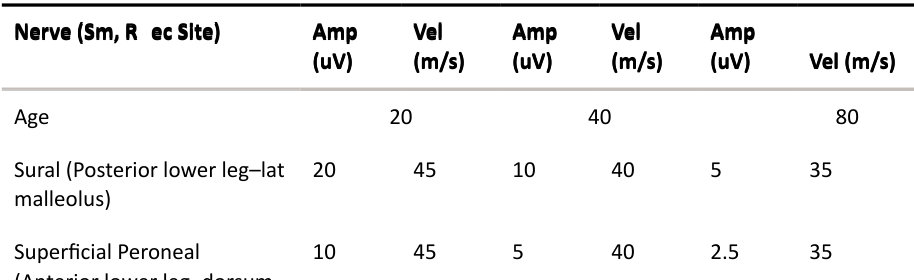
Superficial Peroneal (Anterior lower leg–dorsum ankle)
What are the typical values of CMAPs?
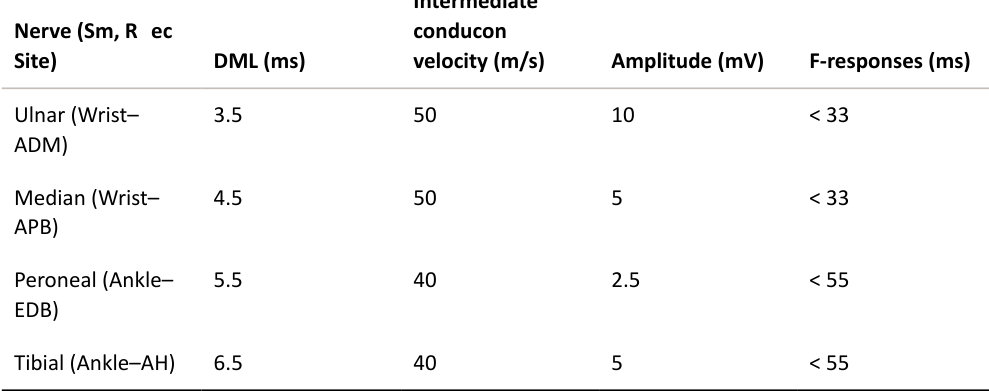
For a typical 40-year-old person, the following values would be expected (Table 28.2). In contrast to the sensory response, there is more variability from overall muscular build, hence a person with a small hand may have a smaller ADM amplitude of around 6–7 mV and a strapping builder would be expected to have a larger ADM amplitude of around 13–15 mV. A 50% asymmetry in amplitude will also be abnormal. Table 28.2 CMAP values.
What are F-waves?
Electrical stimulation of a peripheral nerve causes depolarization in both directions (orthodromic and antidromic) (Figure 28.14). These are small responses which tend to be around 10% of the motor amplitude and are termed F-waves (so-called because they were first described in the feet but are also present in the hands).
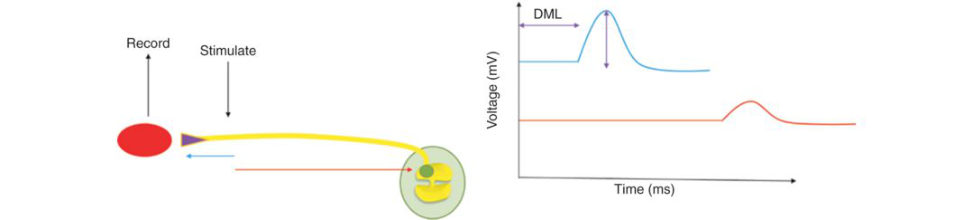
They are measured as a latency (ms) and reflect conduction across the entire motor pathway (up and down).
33 ms in the upper limbs and 55 ms in the lower limbs for average height individuals.
Significance:
(1) Evaluation of proximal (nerve root/plexus/proximal segment) lesions.
(2) Early loss of these in Guillain–Barré Syndrome.
(3) Radiculopathy (C8/T1 and L5/S1).
Here are two examples of F-waves from the ulnar nerve (Figure 28.15). The first one shows normal.
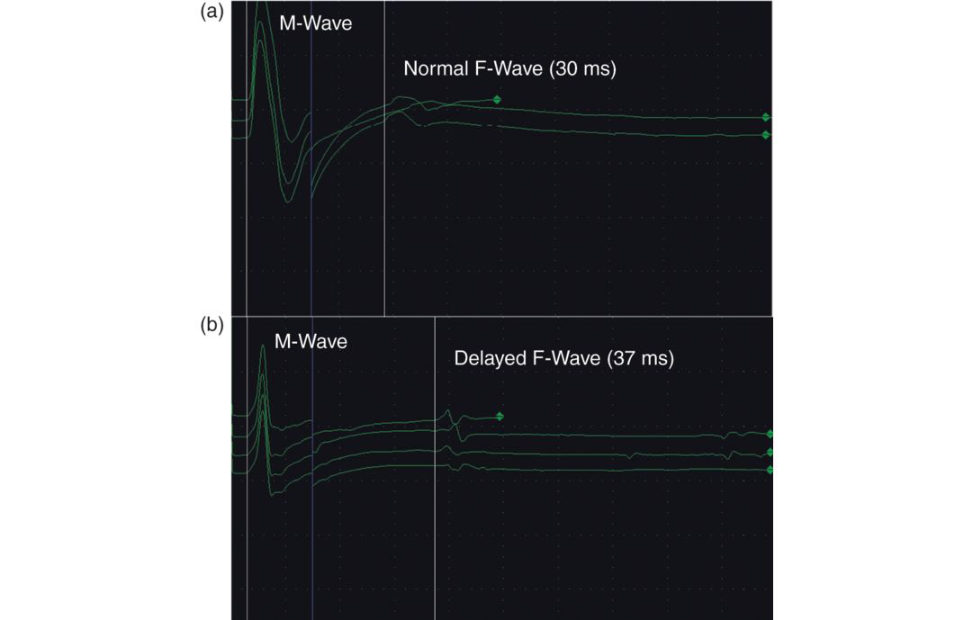
The second shows delayed latencies.
Figure 28.14 F-waves.
Figure 28.15 Latent responses. (a) F-waves, (b) normal delayed.
What is the ‘H’ reflex?
This is a true reflex whereby a selective stimulation of the 1a muscle spindle sensory afferent fibres will activate a monosynaptic spinal cord reflex causing contraction of the corresponding muscle. It is the neurophysiological equivalent of an ankle jerk and is only routinely studied in the tibial innervated soleus muscle (Figure 28.16). (2) In evaluation of dem yelinating neur opathies (early loss in Guillain–Barré Syndrome).
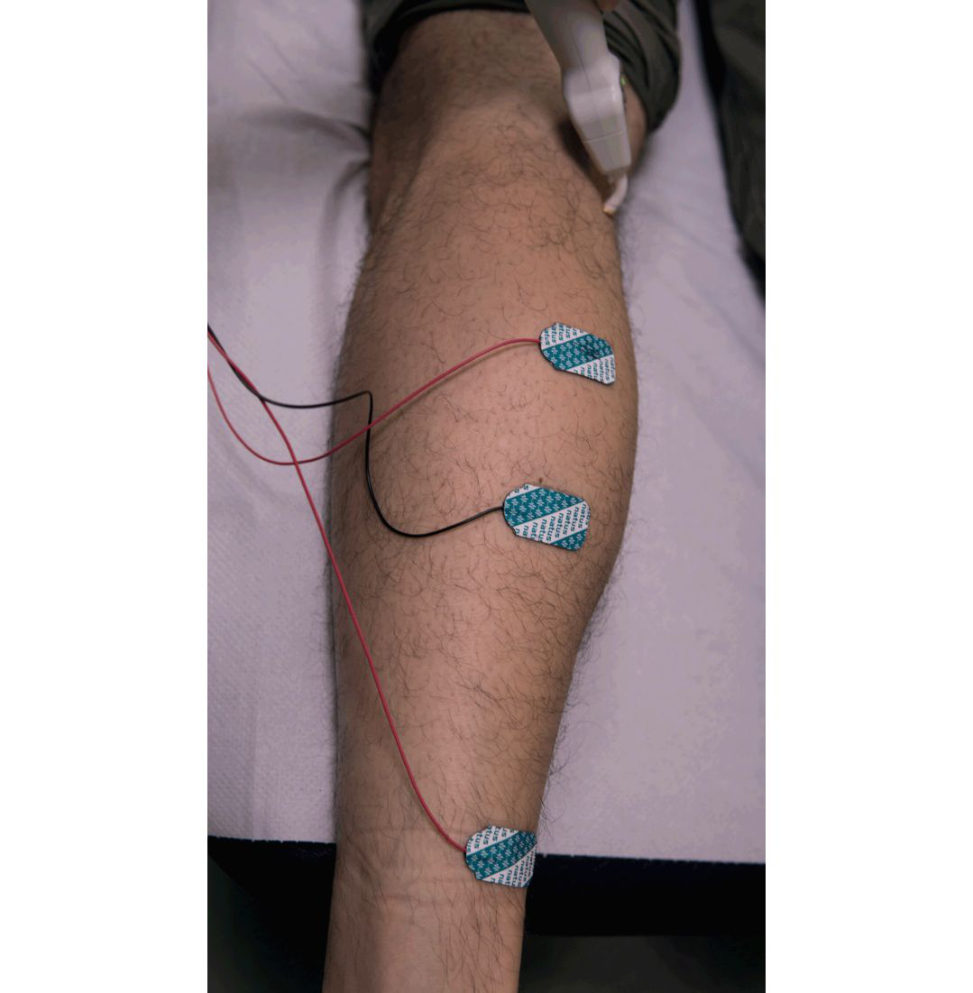
Figure 28.16 Here you can see the tibial nerve being stimulate dat the popliteal fossa and the recording electrodes are placed over the soleus and the Achilles tendon (a ground electrode is placed between the stimulation and recording electrodes to reduce artefact).
How does H-reflex differ from the direct motor or M-wave?
Initially , there are no direct motor responses from direct orthodromic stimulation (M-responses = CMAPs), only via the H-reflex (Figure 28.17a). However, there will be collision of impulses from the now activated motor fibres (ascending antidromically) which will arrest and diminish the H-reflex (Figure 28.17b).
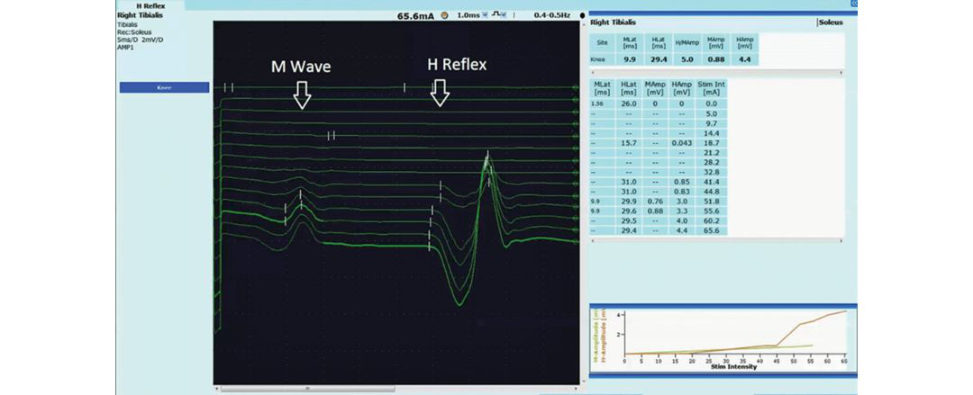
(3) Hence, H-reflexes are present at low stimulation and decrease with increasing.
(4) H-reflexes are proportional to height and for an 170 33.
(5) After the age of 1 year, the H-reflex
(flexor carpi radialis).
Figure 28.17a H-reflex.
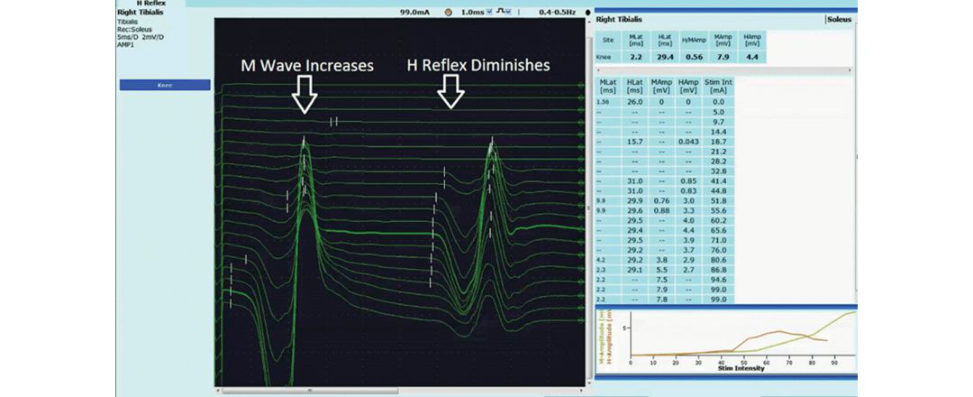
Figure 28.17b Diminished H-reflex.
Structured oral examination question 9#
EMG
Describe ‘endplate activity ’ on EMG.
A healthy muscle should be silent at rest. However, if the EMG needle is inserted into the ‘endplate’ region, i.e. the point where the neuromuscular junctions (NMJs) are located, two types of activity can be detected. (1) Spontaneous release/leakage of acetylcholine from the NMJs leading to non- propagating contraction of parts of some of the muscle fibres. (2) Direct irritation of the NMJs leading to some release of acetylcholine. Both of these usually occur together and the neurophysiologist will usually first be alerted by the pa tientas these sites of insertion are often quite painful in contrast to other regions of muscle tissue where EM Gis usually painless.
What is ‘insertional ’ activity on EMG?
When an EMG needle is inserted into a muscle it causes a brief period of irritation leading to a brief burst of activity lasting up to 300 ms and is called ‘insertional ’ activity . In Figure 28.18, the needle was just inserted and was followed by sustained elctrical activity with the patient at rest lasting around 700 ms (100 ms is shown here).
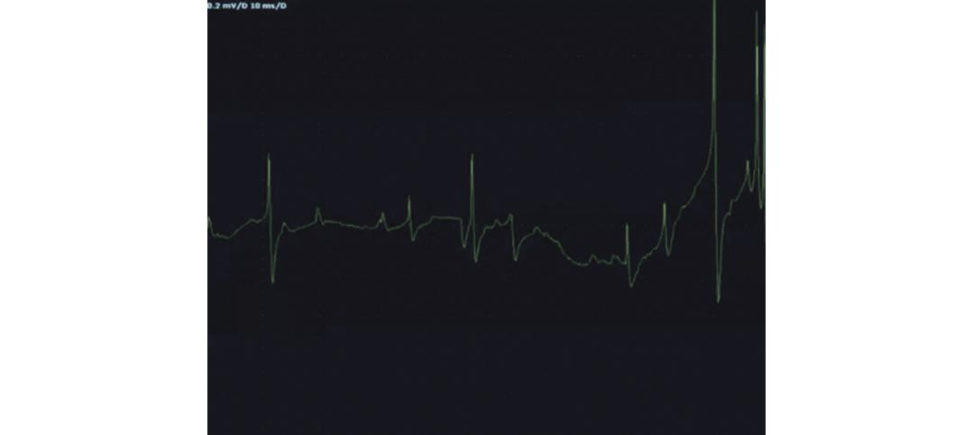
Figure 28.18 Insertional activity on EMG.
Name some of the types of ‘spontaneous’ activity found in a relaxed muscle.
Any activity in a relaxed muscle that lasts longer than physiological insertional activity (i.e. 300 ms) AND is outside of an endplate zone isabnormal and is called ‘spontaneous’ activity . 1. In denervation, the y are thought to be caused by secondary upregulation of A Ch- receptors, leading to an increased probability of local depolarization. In the upper limbs they take at least 14 days to appear and in the lower limbs 21 days, following denervation. As conditions become chronic, they diminish in amplitude (Figure 28.19). 2. Positive sharp waves (Figure 28.20): These equate to fibrillations.

b. Initial positive phase followed by a slow prolonged.
c. Thought to differ from fibrillations in that the EMG needle may slightly deform the muscle membrane, making it.
d. Sometimes seen prior to fibrillations but usually.
e. Arise from single fibres.
f. Biphasic or triphasic.
3. Fasciculation potentials:
a. Spontaneous single discharges of a group of muscle fibres representing part/whole of a motor unit and the.
This characteristic differentiates them from voluntary activity which occurs astrains of activity running a t a frequency of at least 5 Hz.
EM Gis particularly useful inlooking for subtle or subclinical fasciculations.
d. They can occur in benign fasciculation syndrome,
– and are a characteristic feature of anterior.
4. Myokymic discharges.
a. Group fasciculation potentials resulting from discharge of
28.22).
b. Characteristic sound of ‘marching soldiers’.
c. Most important use is in differentiating r adiation-induced ple xopathy from.
d. Can be found in any denervating condition.
5. Complex repetiv e discharges.
a. These result from a circus movement of.
b. These often abruptly start and stop and have.
c. Because they need adjacent muscles to be in a state of disrepair to allow pathological spread of the currents (either.
d. In the example in Figure 28.23, you can see just how regular these are.
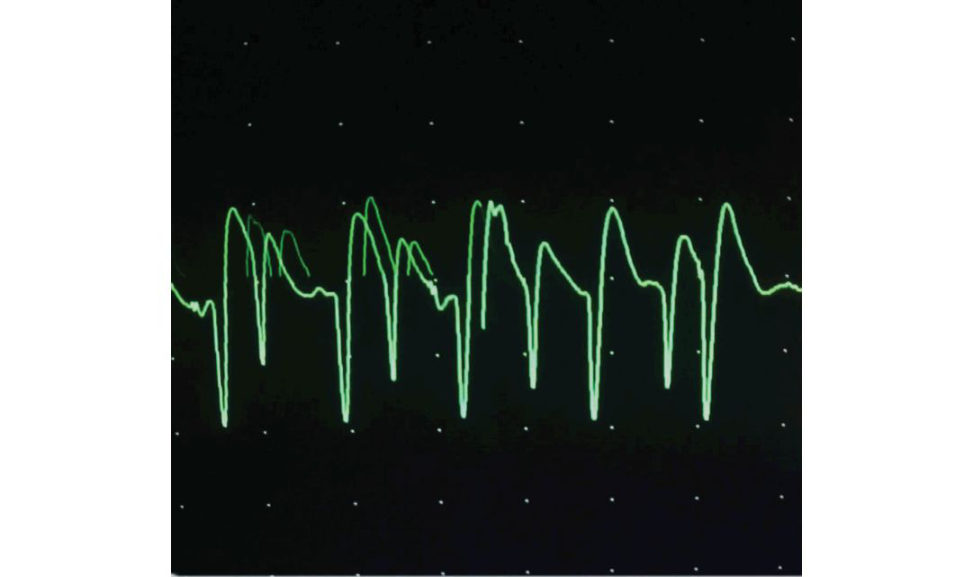
Figure 28.19 Fibrillations diminishing as denervation becomes chronic.
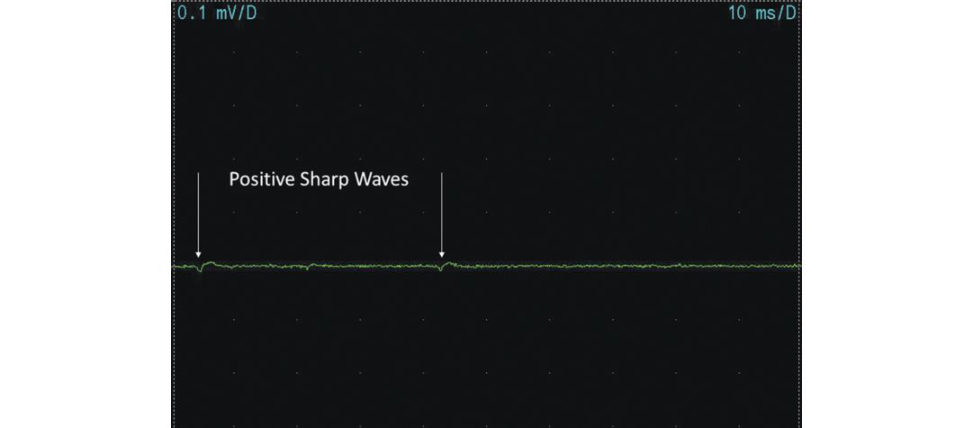
Figure 28.20 Positive sharp waves.
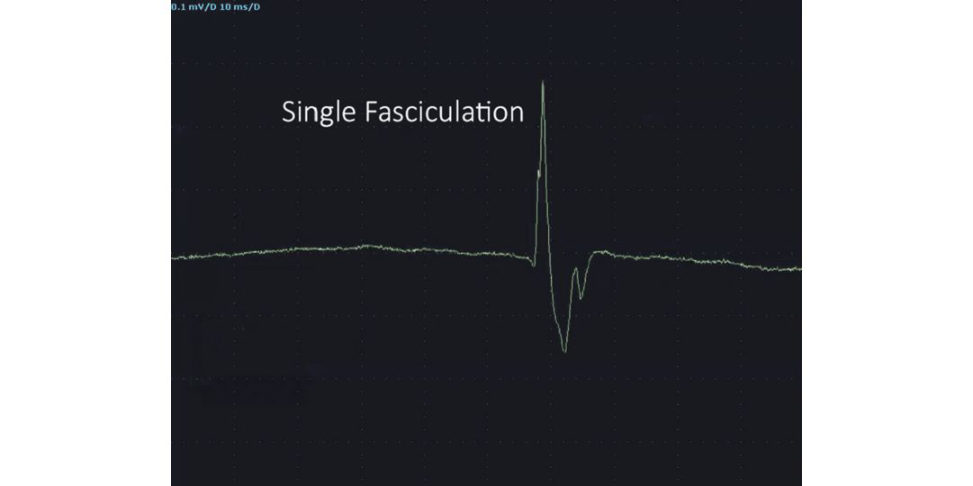
Figure 28.21 Single fasciculations.

Figure 28.22 Group fasciculations.
Figure 28.23 Complex repetiv e discharges.
Structured oral examination question 10#
Motor action potential
Draw and describe a motor unit action potential.
MU APis the summated electrical activity of the muscle fibres innervated by a single motor neuron. It.
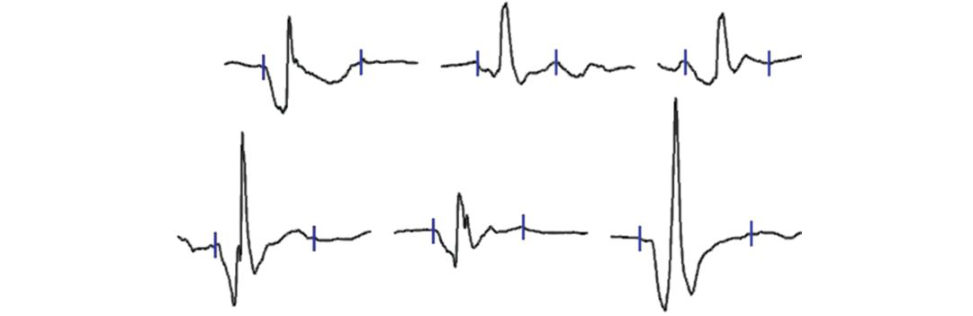
Figure 28.24 Motor unit action potential.
Describe and explain the EMG findings in myopathy.
The electrical characteristics of MU AP sare proportional to the size of the muscle fibres generating them. In myopathies, the fibres shrink, leading to small-amplitude MUAPs. In addition, the density of shrunken fibres increases around the needle insertion site in the muscle so the MUAPS appear small ands pikey (see Figure 28.25). Hence, early recruitment and full interference patterns of these smalls pikey units will be present and is the reason why myopathy patients complain of fatigue. inclusion body myositis.
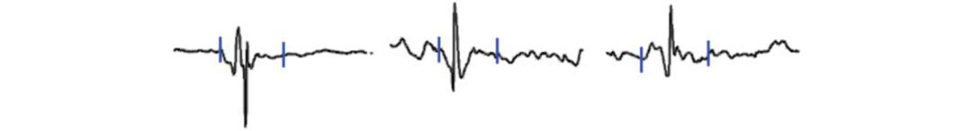
Figure 28.25 Motor unit action potentials in myopathy.
Describe and explain the EMG findings in neurogenic conditions.
The MUAP configuration will change from the acute to the chronic setings. (1) Very acute seting (first 2–3 weeks) of complete axonal loss there will be no MUAPS.
(2) More commonly, axonal loss is partial.
2–3 weeks. Hence, the number of MUAPs visible on the screen (called the interference pattern) will be reduced.
(3) With time nerve regeneration will occur . This will be both locally with terminal sprouting (adjacent.
(4) Local recovery will occur first and results in initially leaky and loose connectivity with those adjacent fibres.
(5) As the innervation becomes increasingly stable and established, the additional
MUAP. The MUAP also enlarges as collectively more.
As regeneration progresses, while they retain their large amplitude, their morphology becomes less complex and their width reduces (Figure 28.26).
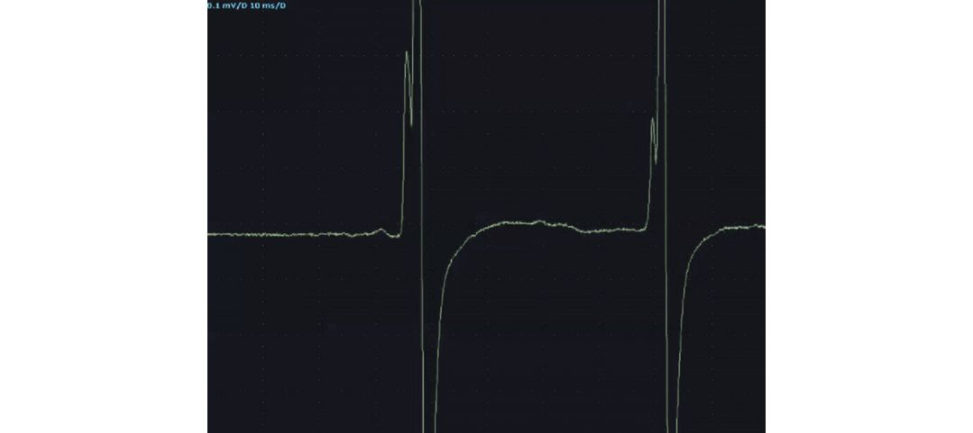
a lower firing frequency during maximal contraction ast here isless drive’ to contract the muscles.
Figure 28.26. EMG findings in chronic degeneration.
Structured oral examination question 11#
Nerve conduction studies#
Can you interpret thes eNC Sofa 40-year-old male with tingling in the right radial 3.5 fingers (Table 28.3)?
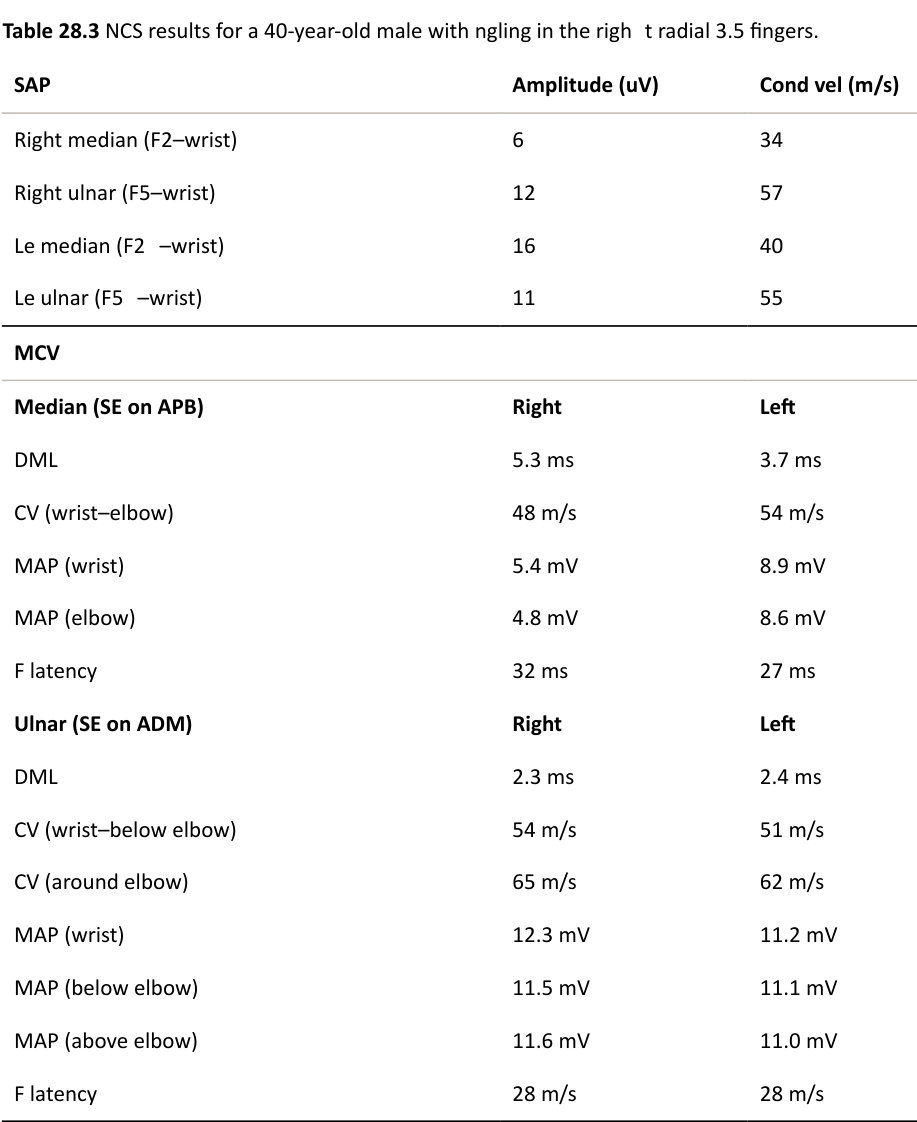
The right F2 is smaller than expected and slower than expected and implies primary demyelination. The right F5 is normal and so there is no evidence of a more widespread neuropathy or brachial plexus lesion. The left F5 is normal.
Therefore, we have bilateral focal median nerve lesions, right more than.
Next, we check the MCVs (motor conduction velocities). The DM Lis quite prolonged on the right and the amplitude is asymmetrically smaller than the left. Left-sided median motor nerve studies and both ulnar nerve motor studies were normal.
there is moderate sensory and motor slowing of median fibres on the right and mild and purely sensory slowing of the median fibres on the left.
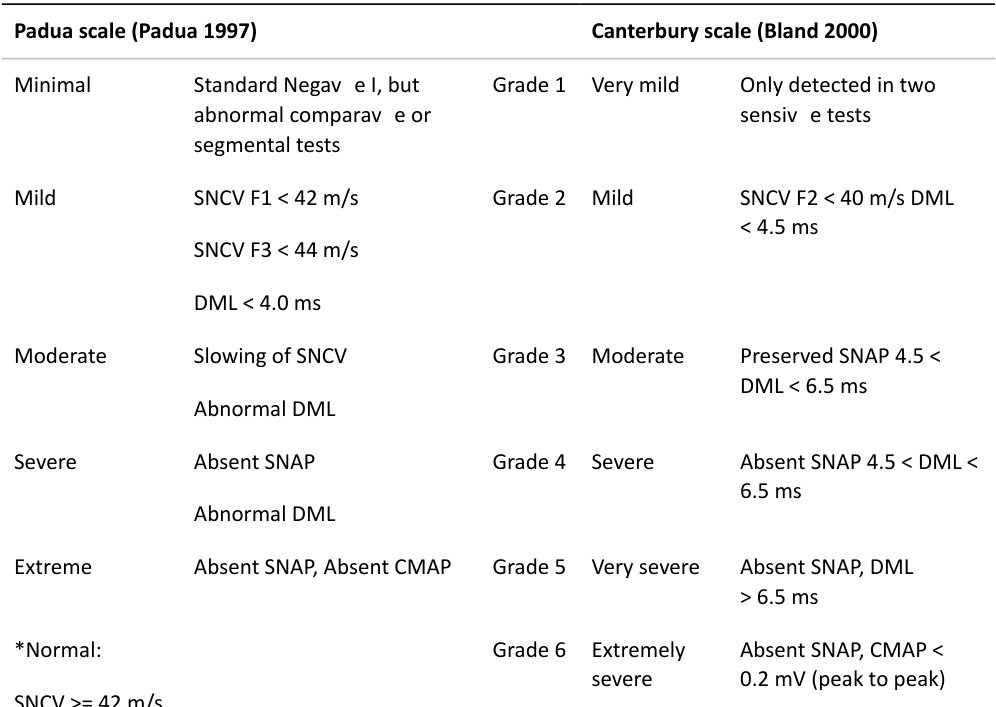
There are two commonly used neurophysiological grading scales
(Table 28.4). While the precise values of normal and abnormal are different between laboratories, the overall gradings reflect the pattern and degree of fibre involvement. This is then followed by axonal loss and the amplitudes reduce.
In Figure 28.27 you can see pure sensory fibre conduction slowing (median–digit II) in the green trace compared to the ‘normal’ side in the grey trace. In this second example (Figure 28.28), you can see distal motor fibre demyelination (median –AP Bin the green trace, compared with the ‘normal’ side in the grey trace. This is a typical finding in a moderate carpal tunnel lesion (Table 28.4).
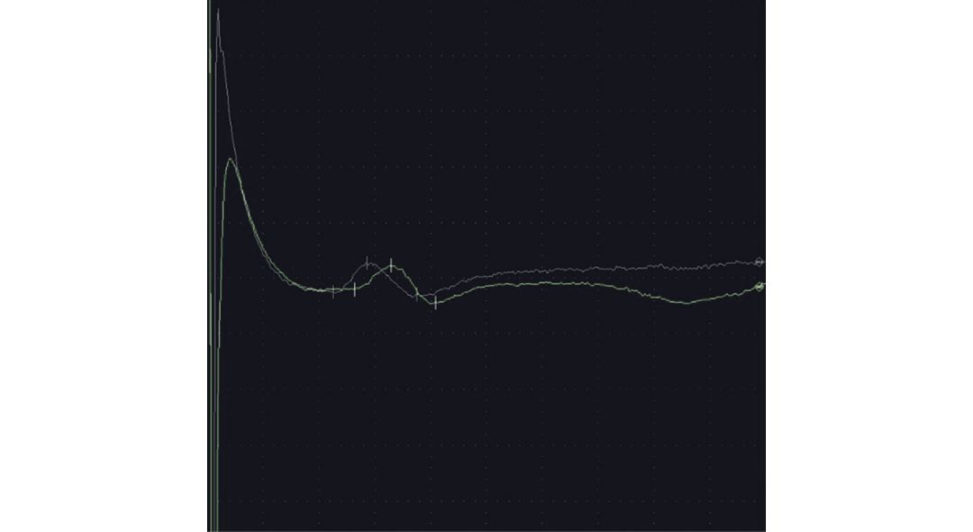
Figure 28.27 Pure sensory fibre conduction slowing.
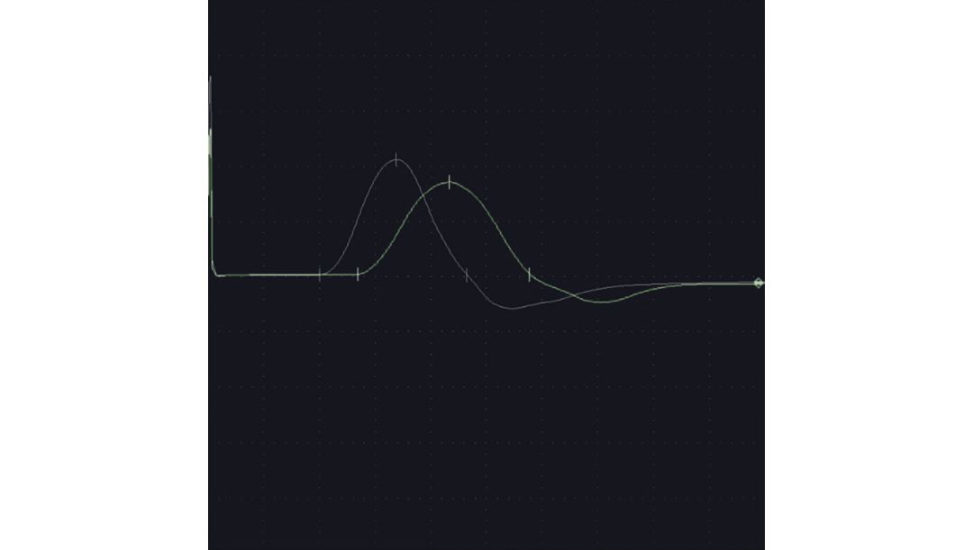
Figure 28.28 Distal motor fibre demyelination.
Table 28.4 Carpal tunnel syndrome grading of severity.
Padua scale (Padua 1997) Canterbury scale (Bland 2000)
Negative Normal findings in all tests 0
DML < 4 ms
Structured oral examination question 12#
Nerve conduction studies
Can you interpret thes eNC Sofa 40-year-old male with tingling in the right ulnar 1.5 fingers (Table 28.5)?
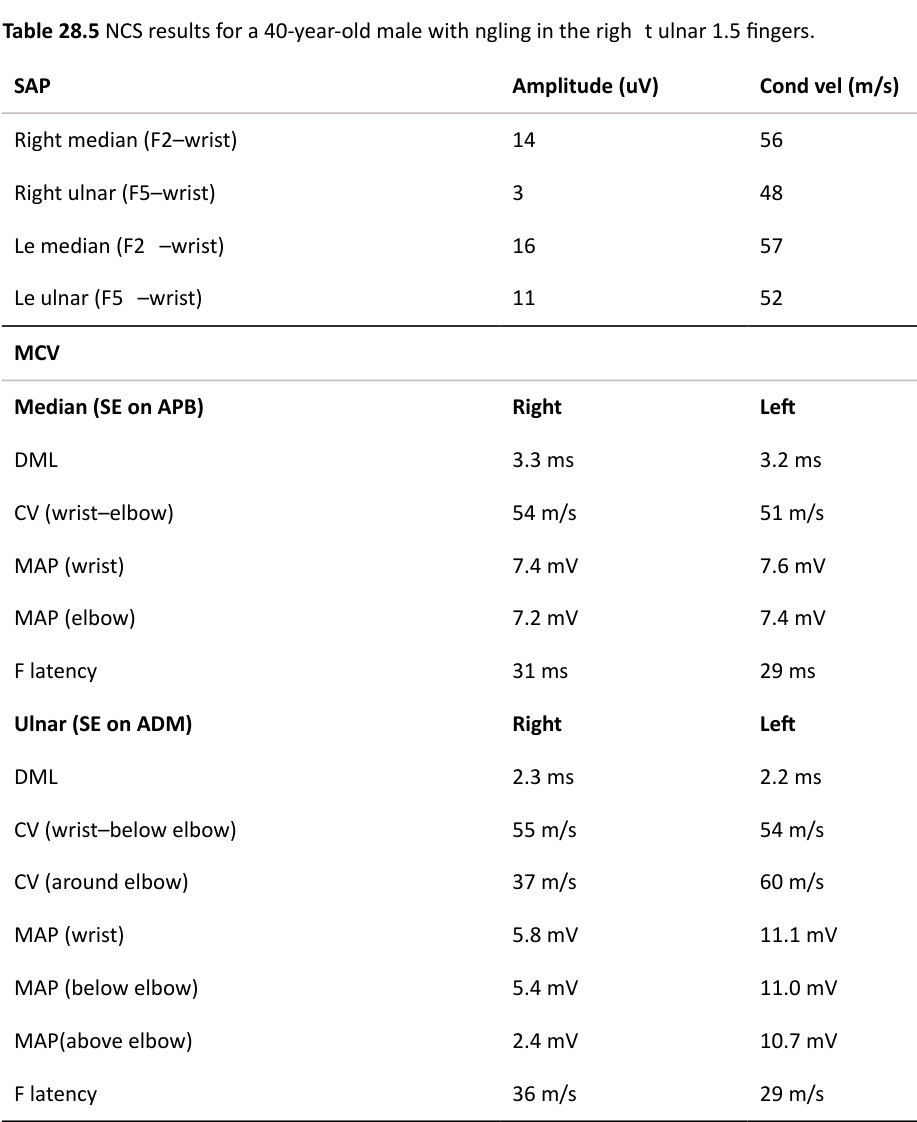
The right F2 SNAP is normal. However, the right F5 is smaller than expected and also asymmetrically reduced compared to that on the left.
Next, we check the MCVs (motor conduction velocities). These are normal for the right median nerve. The F-w ave is also prolonged as the impulses from the anterior horn cells are being delayed through the cubital tunnel.
In summary: These are signs of focal demyelination a t this level which are in keeping with a moderate cubital tunnel lesion.
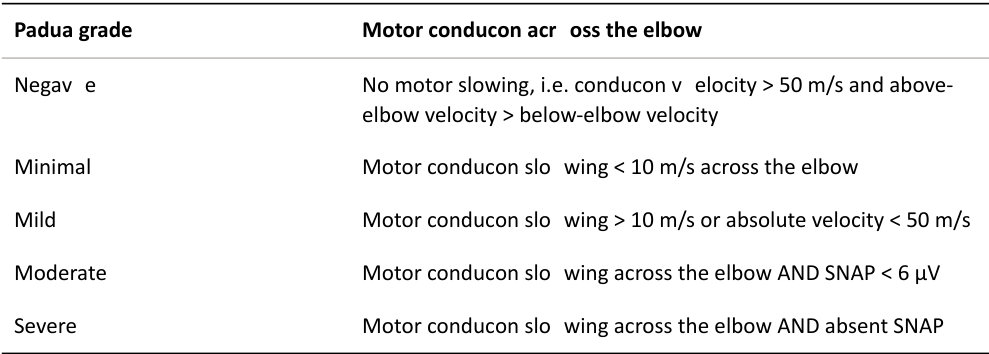
The best-described neurophysiological grading scales Padua14
28.6). In contrast to carpal tunnel, the motor fibres tend to be affected first and are followed by the sensory fibres (with rare exceptions and is thought to relate to the orientation of the fibres against the olecranon groove).
Table 28.6 Padua grading for ulnar nerve compression.
Structured oral examination question 13#
Nerve conduction studies
Can you interpret thes eNC Sofa 20-year-old female with tingling in the right ulnar 1.5 fingers (Table 28.7)?
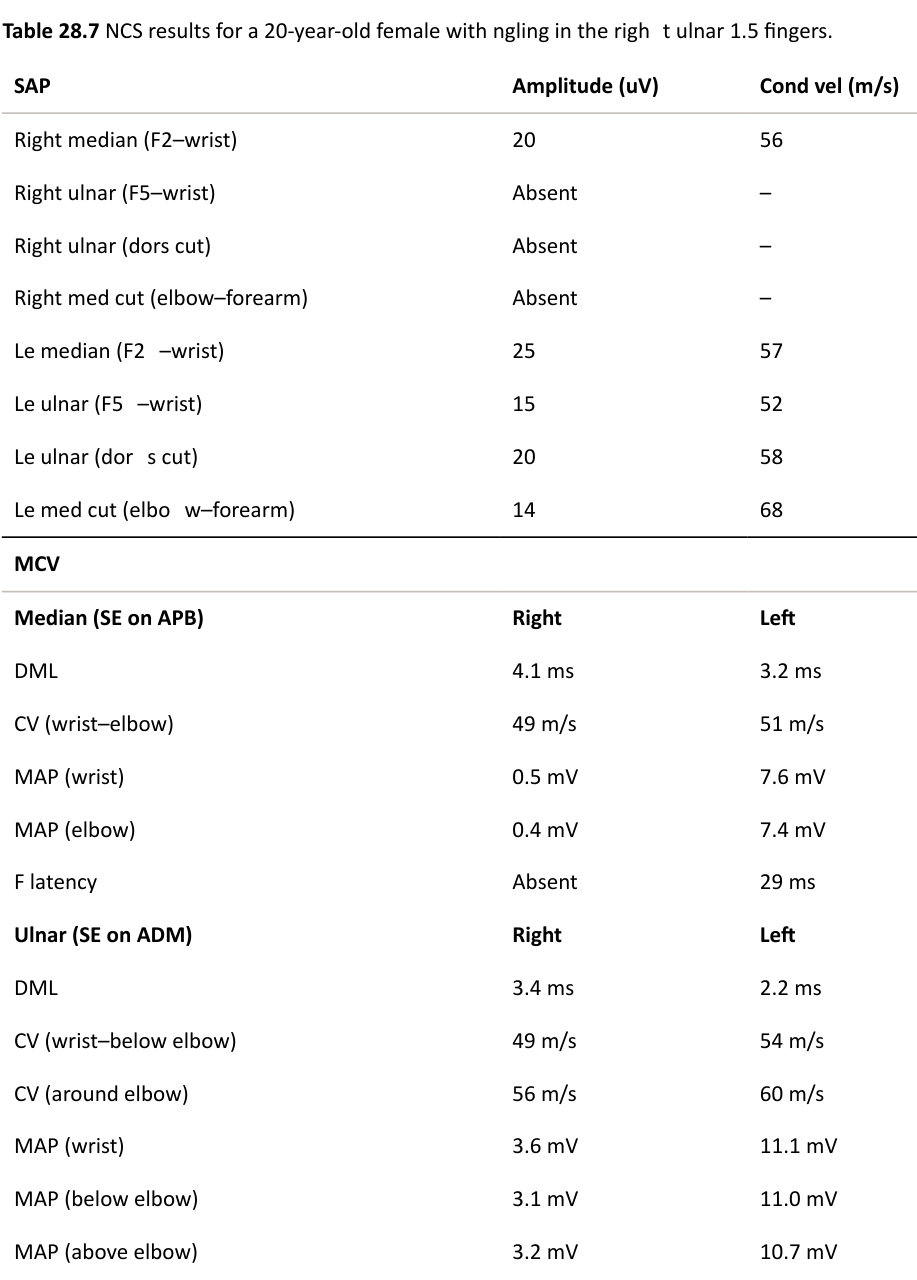
MCV
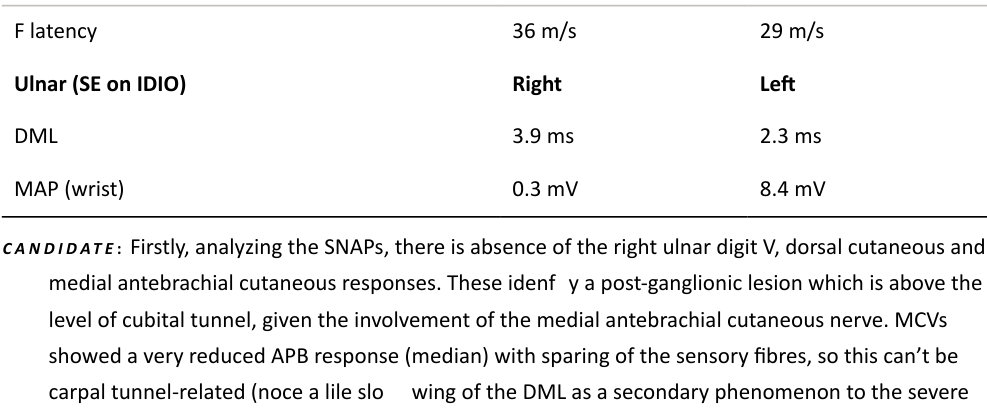
axonal loss). I also see some axonal loss of the ADM muscle, but not as much as the AP Bor IDIO
Table 28.8 EMG results.
EMG
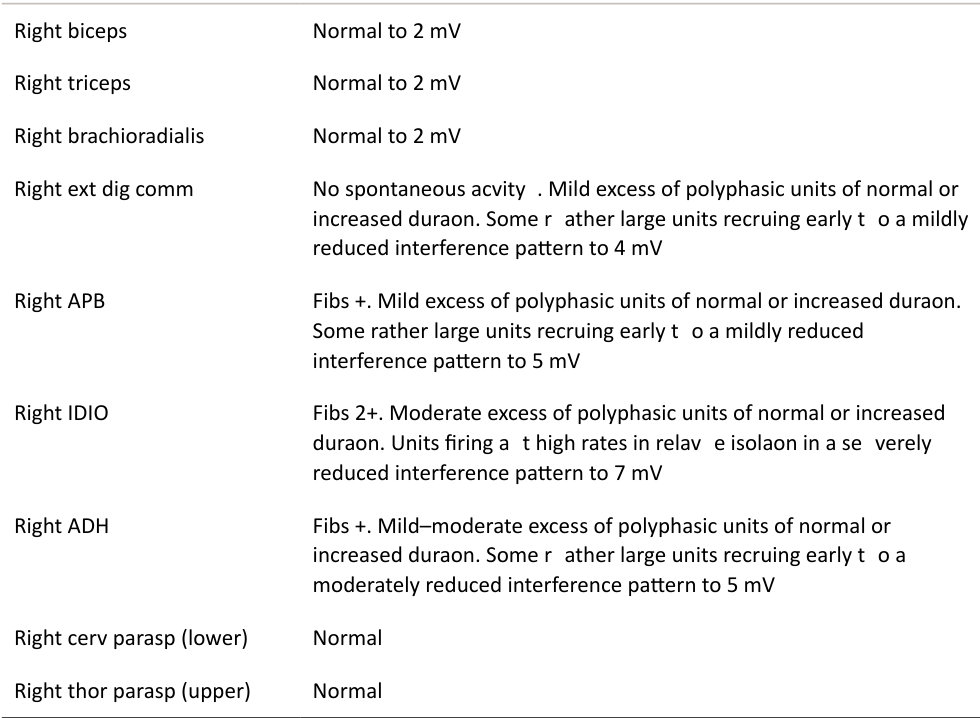
The EMG shows active denervation (fibrillations) with underlying chronic denervation (enlarged, wide, polyphasic units) in the T1–C8 innervated muscles. Paraspinal EMG was normal and so excludes the possibility of a superimposed C8/T1 radiculopathy. Had this been an 80-year-old patient, I would consider a pancoast tumour as the primary differential.
Structured oral examination question 14#
Nerve conduction studies
Can you interpret thes eNC Sofa 40-year-old with numbness in the left leg and a foot drop (Table 28.9)? Table 28.9 NCS results for a 40-year-old with numbness in the left leg and a foot drop.
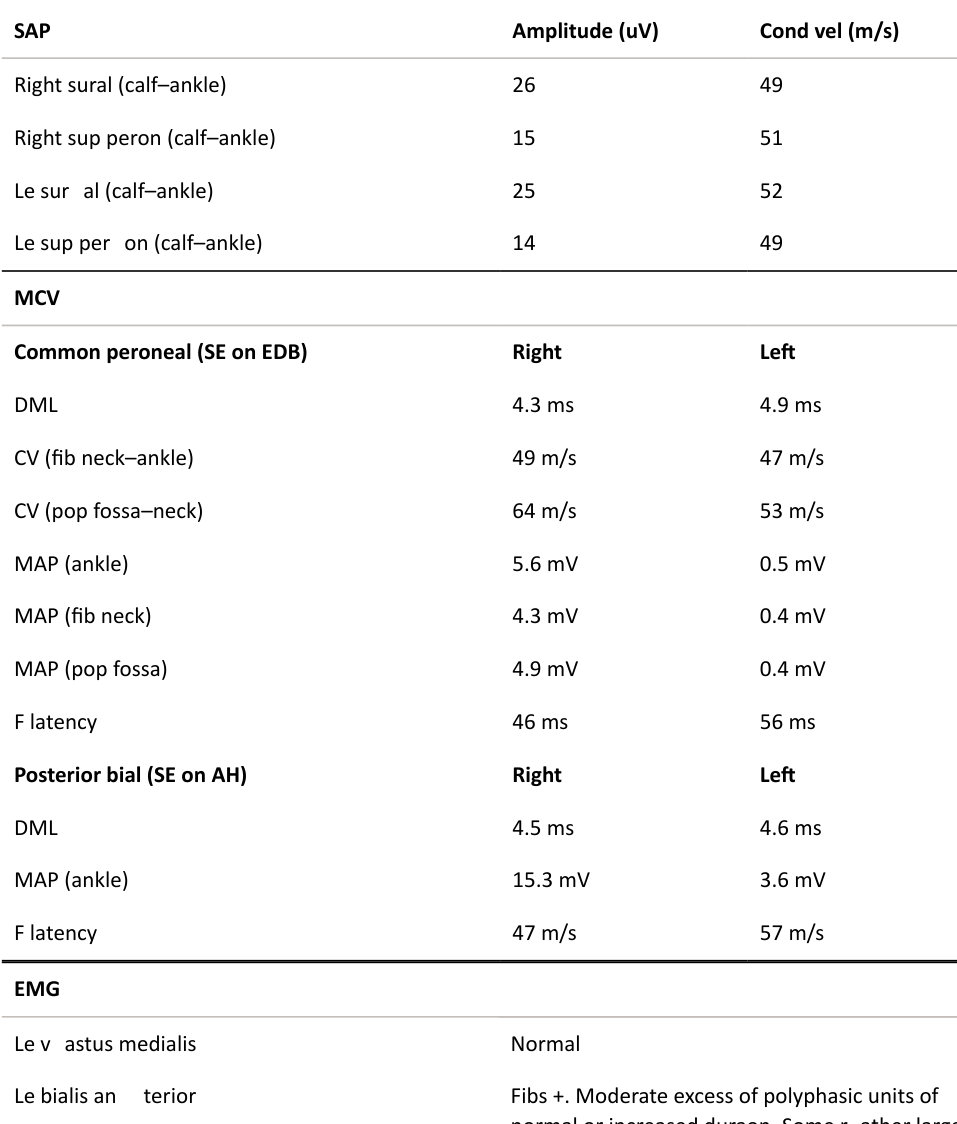
Some rather large units recruiting early to a moderately reduced interference pattern to 6 mV
EMG
Some rather large units recruiting early to a moderately reduced interference pattern to 6 mV.
All the sensory responses are normal and so this cannot be due to a peripheral neuropathy. EMG findings corroborate active moderate denervation in the muscles innervated by L5/S1 root levels. The findings are in keeping with an active left L5/S1 r adiculopathy.
Structured oral examination question 15#
Nerve conduction studies
Can you interpret thes eNC Sofa 40-year-old with numbness in the left leg and a foot drop (Table 28.10)?
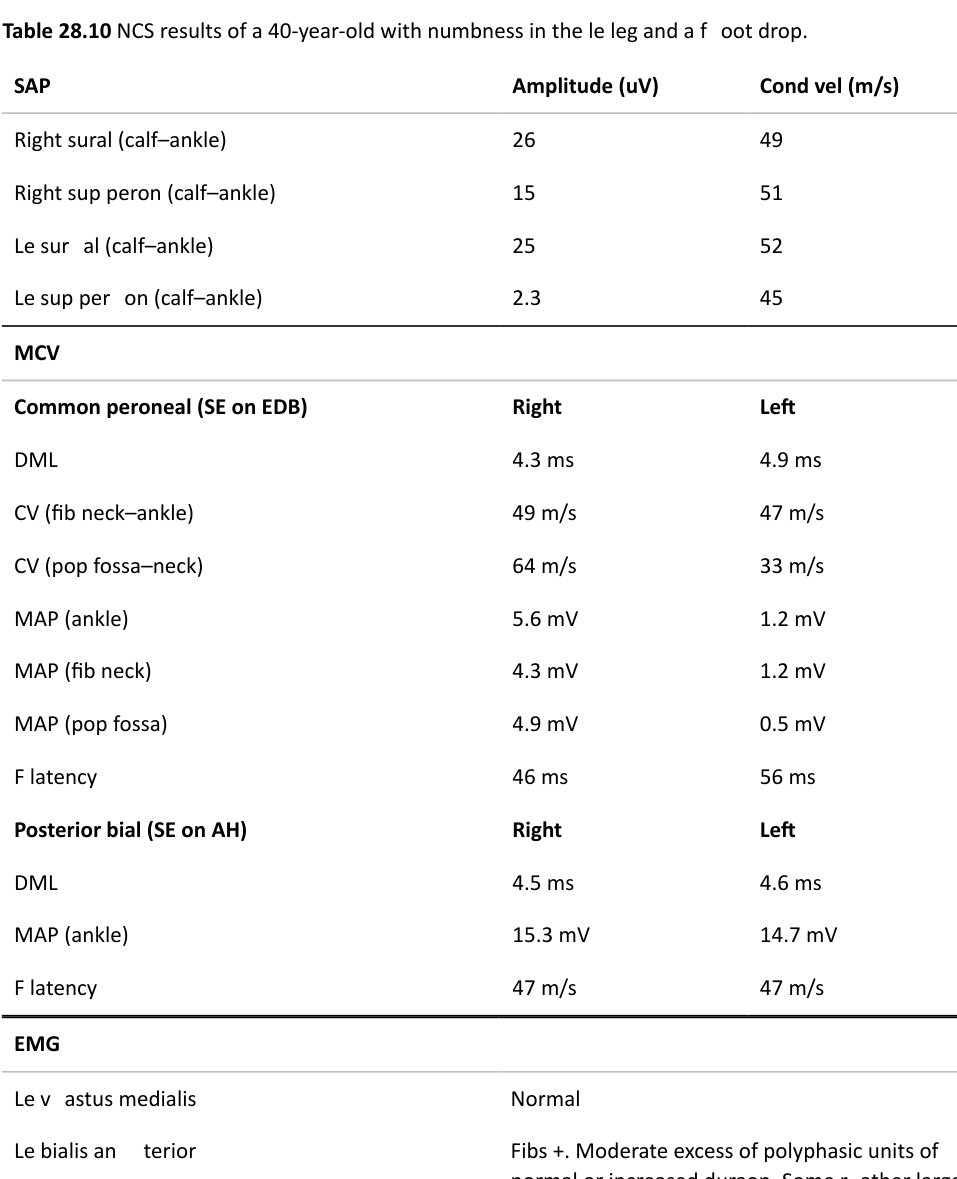
Some rather large units recruiting early to a moderately reduced interference pattern to 6 mV.
EMG
Left tibialis posterior Normal
The left superficial sensory SNAP is reduced and suggests a post-ganglionic lesion. The F- wave is also prolonged as the signal is passing through the demyelinated zone. Absence of denervation in the tibialis posterior muscle excludes a sciatic lesion or L5 r adiculopathy.
Notes
1. Basic Orthopedic Sciences. 2007.
2. Theocharopoulos N, Perisinakis K, Damilakis J, Papadokostakis G, Hadjipavlou A, Gourtsoyiannis N. 2003;85:1698–1703.
3. Martin DJ, Wells ITP, Goodwin C, Physics.
4. Miller MD. 5th Edition. Philadephia, PA: 2008.
5. Einhorn TA, O’Keefe RJ, Buckwalter JA (Eds.). 3rd edition. Rosemont, IL: 2007.
6. Systematic review of the use of bone turnover markers for monitoring the response to osteoporosis treatment: 2014;18(11):1–180.
7. when not to monitor BMD. 2009;58(11):594–596.
8. Kanis JA. Diagnosis of osteoporosis and assessment.
9. www.sheffield.ac.uk/FRAX/tool.jsp
10. Singh M, Nagrath AR, Main iPS. Changes in trabecular pattern of the upper.
11. The basic science of nuclear medicine. 2016;30:3,201– 222.
Neurophysiological classification and sensitivity in 500 carpal tunnel syndrome hands.
13. Bland JD. A neurophysiological grading scale for.
14. Pa duaL, Aprile I, Mazza O, et al. Neurophysiological.