Chapter 30 Statistics and evidence-based practice
Introduction#
Many examinees approach medical statistics with a lot of apprehension. The examiners simply wish to satisfy themselves that as an inquisitive orthopaedic surgeon you understand the basic statistical concepts well enough to be able to scrutinize the published orthopaedic evidence. Statistics of direct relevance (for example NJR survival analysis) are very popular with examiners and are frequently asked. Of the six basic science viva questions most of you would probably be asked at least one question related to
Medical Statistics.
Remember when you answer your question to remain to the point, but whenever you can feel free to use buzzwords designed to show your familiarity and also to tempt the examiner onto your comfort zone.
The answers are deliberately but thoughtiully expanded to better understand the subject around that particular question and to help address potential f ollow-up questions.
Structured oral examination question 1#
What do these lines represent (Figure 30.1)?
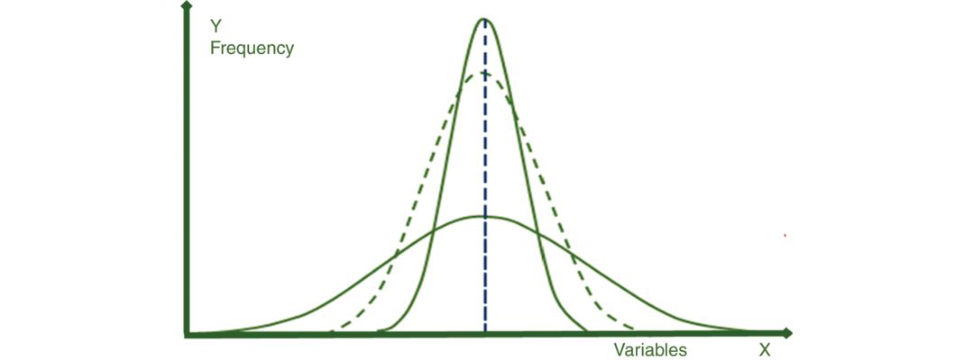
Figure 30.1 Bell-shaped curve normal distribution.
These are all bell-shaped curves of a ‘Normal’ distribution. The x-axis represents a variable (let it be weight,.
Why do you say this is ‘Normal’?
A normal distribution of data is one in which the majority of data are relatively similar, occurring within a small range of values.
What is the significance of this bell-shaped curve?
Although different variables yield different normal distributions, the y all satisfy the 68–95–99.7% rule. Sixty-eight of the observations f all within 1 SD of the mean, 95% of the observations f all within 2 SD of the mean and 99.7% of the observations f all within 3 SD of the mean. Moreover, in normally distributed data, the mean, median and mode are all the same value and coincide with the peak of the curve (Figure 30.2).
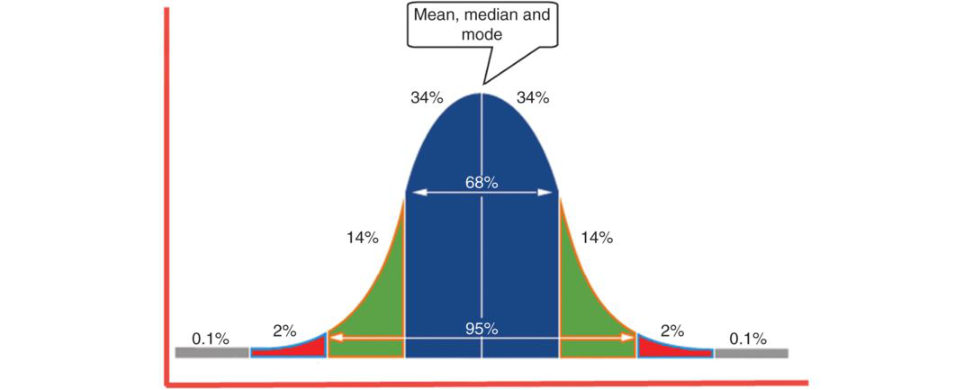
Figure 30.2 Normal distribution curve.
Why is it important to know whether your data are normally distributed or not?
So that we can choose the best way to present, analyze and test our findings. For example, I would use mean and SD to present my normally distributed data in contrast to mode, median and range in non-normally distributed data. I would.
Authors note 1: Describing data
Data are the building stones for any study and it is expected that all candidates are confident inunderstanding and describing data. In this section, we summarize some important aspects.
Data in general are divided into:
1. the objects being studied are grouped into categories based on some qualitative trait;
a. smoking status, living status, marital status, etc.
b. Ordinal: categories with order, e.g. social status,.
Either type can be binary (i.e. married or unmarried;
smoker or non-smoker) or not binary.
2. the objects being studied are measured based on some quantitative trait.
a. number of admissions to an orthopaedic ward, number of spinal metastases, number of patients transfused.
b. Continuous theoretically, any value within an interval is possible with.
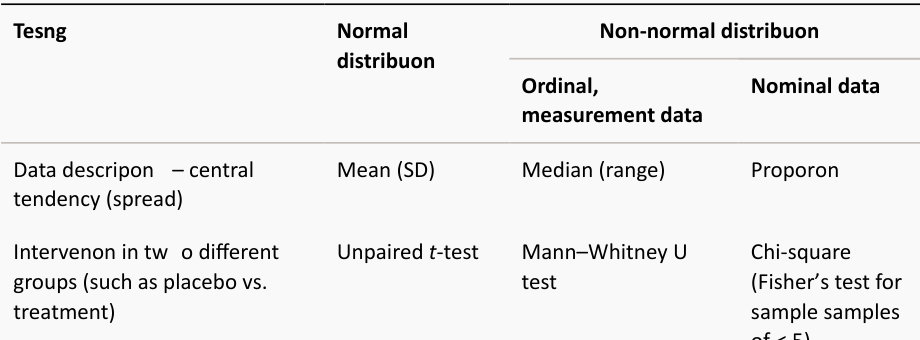
The type(s) of data collected in a study determine the type of presentation and statistical analysis used. If they are normally distributed they can be summarized using means and standard deviation and tested by parametric tests. If data are not normally distributed, they can be summarized using mode, median, range and tested by non-parametric tests (Table 30.1). However, it boosts your answers if you have basic knowledge about the common ones (highlighted in the table).
There are several ways to check data for normality. Ploting normally distributed data produces a symmetrical bell-shaped curve. If the curve is not symmetrical, the data are probably not normally distributed Alternatively, data can be formally
therefore, graphical methods are generally preferable.
Data can also be presented as risk ratio (RR) or relative risk. 24 people skiing down a slope, 6 fall:
The risk = number of events of interest 6/24
The odds = number of events of interest 6/18
0.33
Relative risk or risk ratio (the y mean the same thing and are both abbreviated as RR) is simply the risk of the event.
The risk difference (RD) is the risk difference between two groups. RD value of 0 means no difference between the two groups.
The number needed to treat (NNT) is how many people would need to.
The odds ratio (OR) is simply the odds of the e vent occurring in one group divided by the.
Risk difference (and derivatives like NNT) is more immediately useful than relative risk and odds ratio. The odds and risk ratio are equally variable whereas the risk difference varies more widely and less consistently.
Table 30.1 Statistical tests.
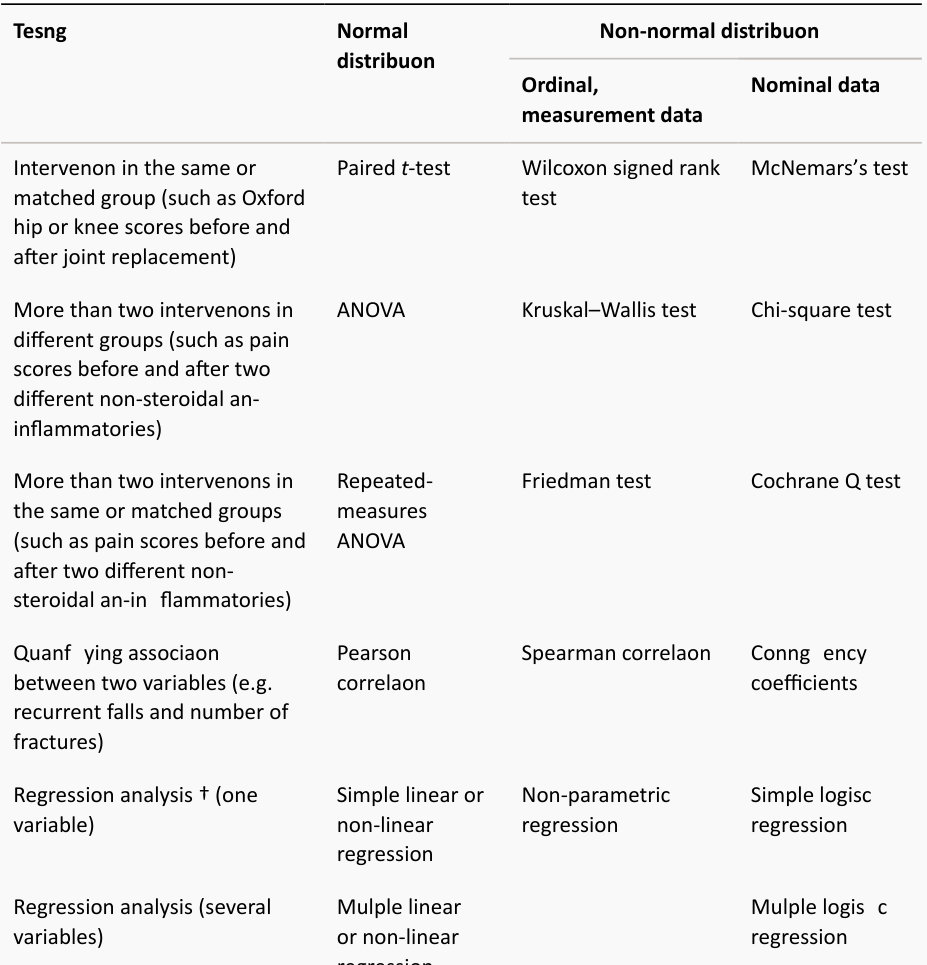
† Regression analysis involves modelling and analyzing several variables, when the focus is on the relationship between a dependent variable (for example, death) and one or more independent variables (for example, age, weight, comorbidities, haemoglobin le vel, etc.).
OK, what about these two curves (Figure 30.3), are they also bell-shaped?
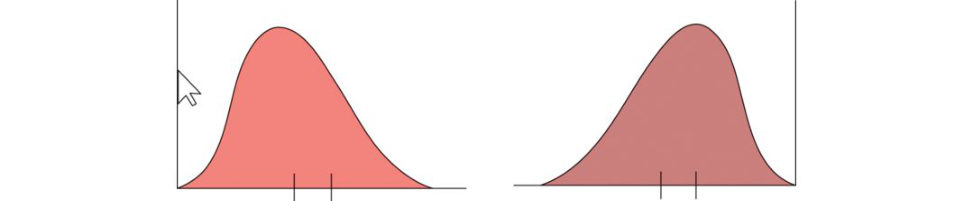
Figure 30.3 Skewed curves.
Not quite, they are skewed curves, they are not symmetric, and the tail is larger on the right.
What is the significance of skewed data and where is the mean in these images?
They are not symmetrical, therefore the mean is pulled by the outliers, so the mean lies toward the direction of skew (the longer tail) relative to the median.
What value would you use to describe this set of data?
I would use median and interquartile range.
OK, what is this chart (shown in Figure 30.4)?
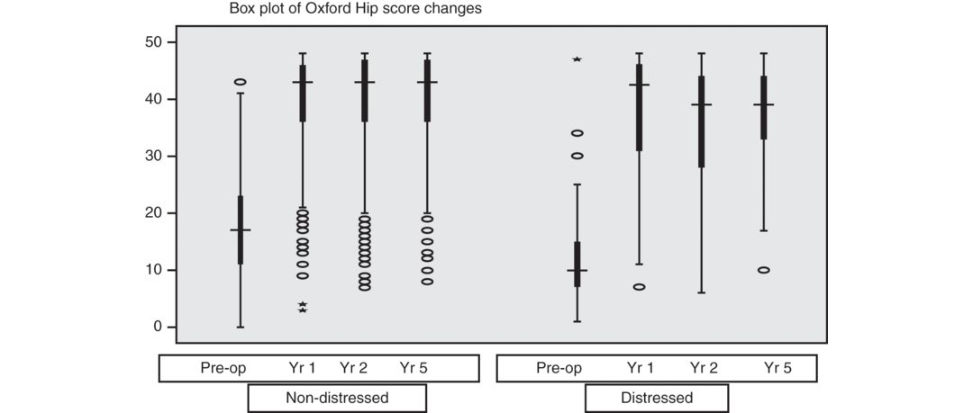
Figure 30.4 Box plot, Oxford hip score.
It shows that in both groups of patients surgery resulted in improvement in Oxford hip score and also that there were more outliers in the non-distressed group compared to the distressed group, postoperative improvement was maintained at 5 years of follow- up and the distressed group appears to have made a comparable if not a slightly larger gain compared to the non-distressed group.
What are the different lines?
The width of the box shows the interquartile range, the line in the middle is the.
What is an outlier?
A value that is much larger or smaller than the rest of the data.
Do you know how you can transform non-parametric data to more normal-looking data?
No.
OK, you can do logarithmic transformation or bootstrap technique, thanks.
Authors’ note 2
The middle of the box plots represents the median and the sides (or theb oft om and top of the box) are always the first and third quartiles. The ends of the whiskers can represent several possible alternative values, such as the minimum and maximum of all of the data, one standard deviation above and below the mean of the data or the 9th percentile and the
91st percentile. Outliers may be ploft ed as.
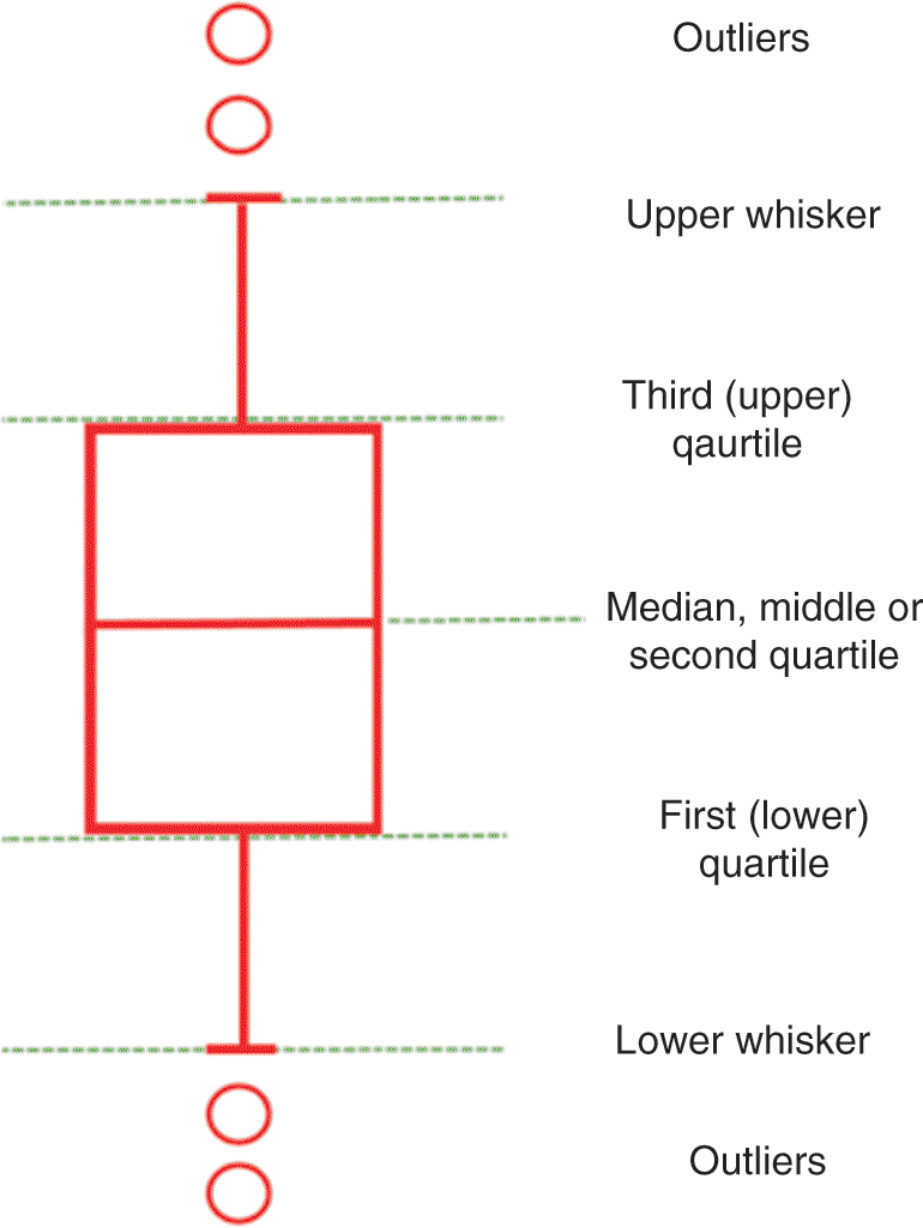
Figure 30.5 Box plot.
Figure 30.6 compares the box plot to the.
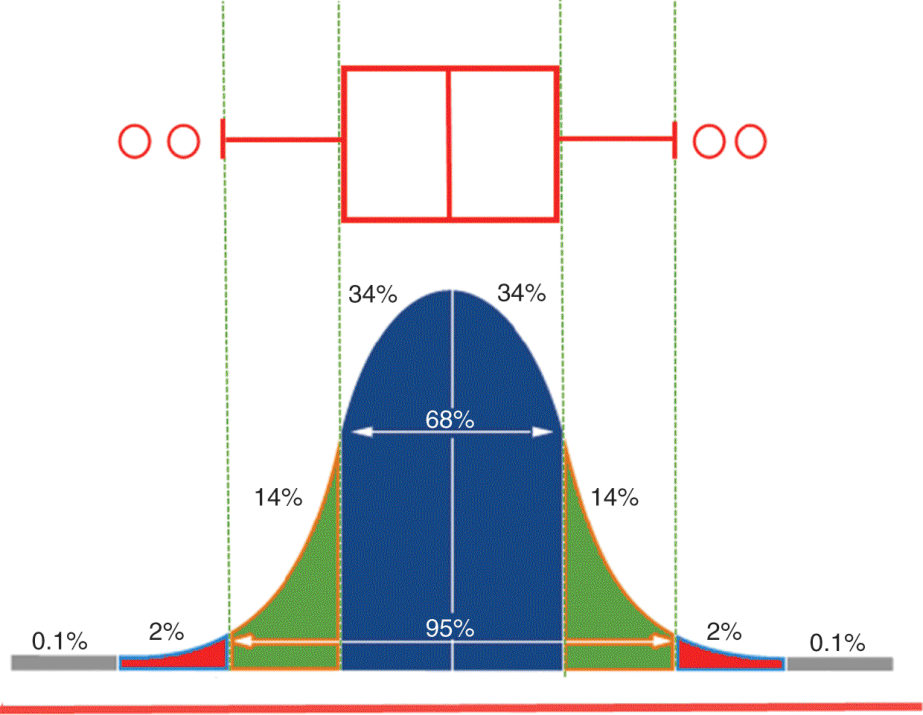
Figure 30.6 Box plot versus bell-shaped curve.
Structured oral examination question 2#
Can you tell me how you would design a clinical trial? Authors’ note 3 Frequently, candidates make the mistake of jumping straight onto a randomized controlled trial, the quest ionis designed to see if you have an overall concept of designing a trial and whether you might have any practical experience.
Design of a clinical trial would begin with a clinical question that might arise out of a clinical context. In the first instance I would conducta literature search utilizing the PIC O principle [a buzzword that would impress the examiner, PICO stands for Patients Intervention, Comparison, Outcome]. The design of the trial would depend on my underlying clinical question.
Tell me more about the level of evidence (Table 30.2). Table 30.2 Level of evidence.
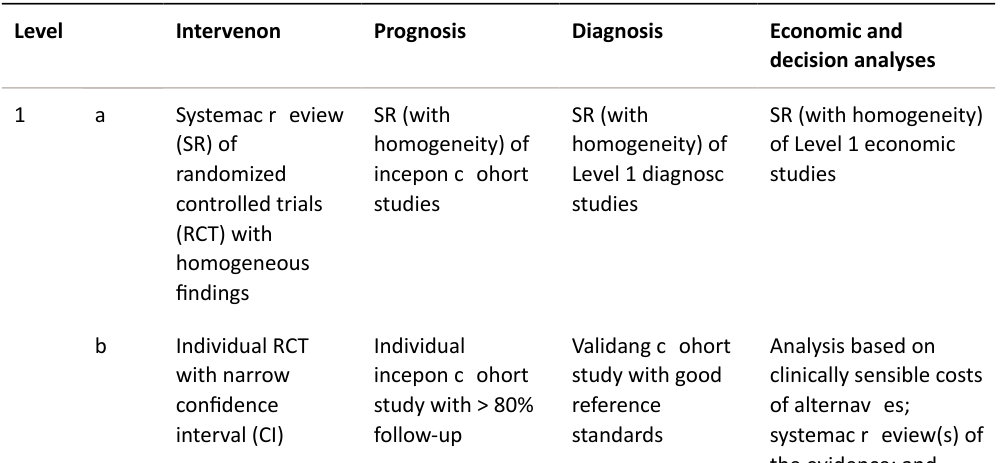
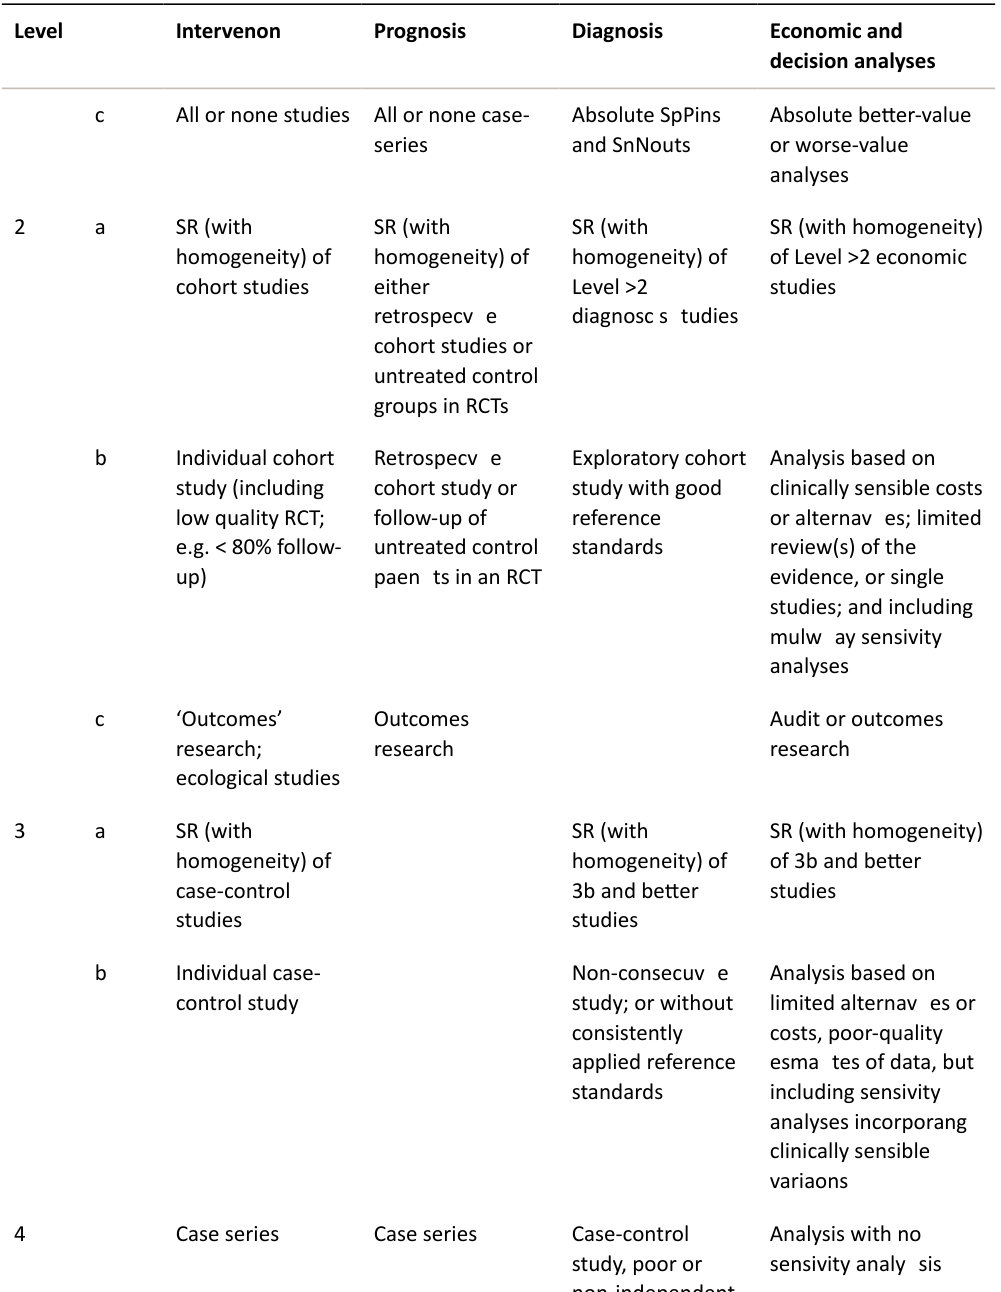
4 Case series Case series Case-control study
Level Intervention Prognosis Diagnosis Economic and decision analyses
5 Expert opinion Expert
1. A complete assessment of the quality of individual studies.
2. A combination of results from two or more prior studies.
3. Studies provided consistent results.
4. Study was started before the first patient enrolled.
5. with cemented hip arthroplasty) compared with patients treated another way (e.g.
6. Study was started after the first patient enrolled.
7. failed total hip arthroplasty), called ‘cases’, are compared with those who did not have the outcome (e.g.
8. Patients treated one way with no comparison.
This chart was adapted from material published by.
For more information, please see www.cebm.net
The general principle of the hierarchy is that controlled studies are generally better than uncontrolled ones, prospective are generally better than retrospective and randomized are generally better than non-randomized studies [1]. Over the last three decades, several systems have emerged to assign a hierarchy for studies based on the aforementioned principles Examples of these systems are the Oxford Centre for Evidence-Based Medicine (OCEBM) [2], the Scotish Intercollegiate Guidelines Network (SIGN) [3] and the Journal of Bone and Joints Surgery Levels of Evidence [1].
Authors’ note 4
or patients to find the likely best evidence in the shortest possible timeTable 30.1 showed the LOE produced by OCEBM.
These levels of hierarchy vary among different systems.
Sometimes ‘lower-level’ evidence from an observational study with a dramatic effect provides stronger evidence than a ‘higher-level’ study such as a
Charnley hip replacement and Ponseti’s treatment of clubfoot are classical examples [4].
It is essential to appreciate that LOE are not recommendations for or against certain treatments and several
i. Is your patient sufficiently similar to the.
ii. Does the treatment have a clinically relevant.
medicine X reduces blood loss 50.
iii. Is another treatment better (e.g. a systematic review might suggest that surgery is the best treatment for back pain, but.
Suppose that you are trying to test a new treatment? Literature search revealed no useful information.
Ideally, I would like to design a randomized controlled trial (RCT) to compare my new treatment to the current (or any another treatment). It is the most rigorous way of determining whether a cause–effect relation exists between treatment and outcome. Good RCT design must ensure [6]: 1. 2. Patients and trialists remain unaware of which treatment was given until the study is completed: 3. 4. The two groups of treatment are treated identically except for the experimental treatment.
What is the difference between the two types?
F or example, if I was testing a new type of cement to help reduce revision rates, I would design my study in such a way that I remove or minimize the effect of any factors that could influence the revision rate. However, inreality the above design is neither practical nor desirable because we would want to see the tested intervention (the new cement here) work similarly in every centre, for every surgeon and with every implant. They measure effectiveness – the benefit the treatment produces in routine practice [ 7].
How do you randomize?
There are manyways of randomization. Ideally this should.
What is the advantage of randomization?
The advantage of randomization ist o avoid bias by equally distributing the known and unknown patient variables (that.
What do you mean by bias?
Bias is a tendency to deviate from the true value due to an error in the study design and thus over- or underestimate the true value of the treatment effect.
Once you complete your trial how would you know if the new treatment is effective or not?
I would perform asta tis tical test and if the P value is < 0.05 this would suggest that there isless than 5% chance.
Would you change your practice based on the results of a P value? Can you imagine a situation where the P value is > 0.05 but you might want to reconsider the intervention?
Yes, where there is a possibility of a type II error.
What is a type II error?
Where the sample size of the trial might be inadequate and therefore even if there.
OK, this is known as the power of the study. Time’s up. Thankyou.
Authors’ note 5
This section summarizes the essential concepts and buzzwords that you need to deliver when you are asked about RCT.
Research is conducted to answer a particular question. Although RCT is the most rigorous way of determining whether a cause–effect relation exists between treatment and outcome, it is not the only way.
1. A literature search to establish current knowledge, thus refining the research question and trial methods to take knowledge forward and avoid unnecessary research repetion.
2. Thus, inclusion and exclusion criteria are important trial design features and should be carefully thought about, e.g. However, excluding patients with dementia because consenting is more problematic is not a good reason and may not be ethically acceptable. This would deprive such patients from future evidence-based treatment.
3. the primary outcome (or the primary endpoint)
represents the greatest treatment benefit. Secondary outcomes (or secondary endpoints) may provide information on therapeutic effects of secondary importance, side effects, or tolerability. Blood transfusion is a good primary outcome. In comparison, drain blood loss, although important, does not tick all the boxes mentioned earlier , hence it is better used as a secondary outcome rather than a primary one (see also the type of data section).
5. Sample size (power). A well-designed study should have the optimal number of participants adequate sample size) to provide an adequate chance of finding a clinically worthwhile difference between treatments. Over-recruitment is undesirable as it is uneconomic and unethical.
Sample size is usually calculated for the
Chosen significance level (usually 5%).
Study power (typically 80% or 90%).
Chosen clinically important difference in the primary outcome.
The variability in response.
There are several pieces of.
6. The true effect of the treatment under investigation is systematically under- or overestimated For example:
i. Question bias : e.g. comparing a new treatment with the most.
ii. Sampling bias: patients with significant comorbidity are excluded from.
iii. Selection bias : patients with underlying prognosis are.
iv. Information bias : including any of a range of factors that distort.
v. Windowing bias: where the investigators’ prejudices influence.
vi. Publication bias : studies with negative or no difference are.
7. Randomization : if adequately conducted, randomization reduces the chance of selection bias because.
8. Blinding is an important design feature to manage both explicit and implicit prejudice, although it is not always possible.
9. Analysis: this is conducted according to a protocol agreed
Intention-t o-treat (ITT), meaning that participants are analyzed according to the group allocated regardless of whether they continued with that treatment.
comparing the groups according to the treatment that they received.
iii. Per protocol analysis includes participants who metall the protocol criteria.
The cons of the last two analyses are that they potentially overestimate the efficacy of.
10. Logistics (ethics approval, local approval, building and.
Structured oral examination question 3#
If you had the choice of deciding between a highly sensitive testor a highly specific test to diagnose as many of the diseases as possible for a particularly debilitating condition, what kind oftest would you go for?
I would choose a highly sensitive test.
Why is that?
In a highly sensitive test more of the diseased cases.
What are the drawbacks of each?
A highly sensitive test may pickup more false positive cases and create unnecessary patient anxiety.
What if you wanted to confirm diagnosis of the disease?
I would choose a highly specific test.
Do you think hip ultrasound is a good screening test for DDH?
it has a high sensitivity to detect the disease before a critical point and has high specificity to reduce false positives.
Should we screen all newborns for DDH using ultrasound?
This is widely debated. Some countries have already started a universal screening programme and showed encouraging results; To run a successful screening programme,several criteria should be met. These criteria can be categorized into three groups: 1. Disease criteria. 2. Accepted and tolerated by patients.
ii. High sensitivity to detect the disease before.
iii. High specificity to reduce false positives.
iv. Cost-effectiv e.
3. Screened population features.
i. Disease has high enough prevalence to allow screening.
ii. Accepted and effective treatment is available.
iii. Patients are willing to undergo further evaluation.
There is an early stage in which DDH can be picked up, with a sensitive test that is acceptable to the population. Furthermore, the cost of the screening programme in comparison to the full costs of delayed detection (including medicolegal costs) has not been established [8].
Authors’ note 6: Diagnostic tests
Sensitivity , specificity, positive and negative predictive values of a diagnostic test are commonly featured in the exam. Our advice is to understand the definition rather than memorizing it.
1. Sensitivity (Sn): the probability of identifying a disease (true.
Sn = true positive / true positive + false negative.
2. Specificity (Sp): the probability of excluding a disease (true negative.
Sp = true negative / (true negative + false positive).
3. Accuracy (A): the probability of correct identification.
A = true positive + true negative / total number.
4. Positive predictive value (PPV): the probability of
when they have tested positive all.
PPV = true positives / (true positives + false positives).
5. Negative predictive value (NPV): the probability of someone not having a disease (true.
NPV = true negatives / (true negatives + false negatives).
Unlike sensitivity and specificity , predictive values are properties of the t est interacting with the prevalence of disease in the population. A high PP V indicates a strong chance that a person with a positive test.
6. Likelihood ratio (LR): the ratio of the chances of truly having a.
LR = Sn / (1 – Sp).
We can calculate the LR for every test. The larger the LR, the better the test. Increasing sensitivity and/ or specificity.
Ploting Sn against (1 – Sp) produces a characteristic curve called ‘receiver operating characteristic ’ (ROC) curves (see Figures 30.7 and 30.8). An ideal ROC curve rises quickly to the upper left corner of the graph (high Sn and Sp) and stays high, leaving a larger area under the curve. Once the overall ROC curve is fixed, the surgeon or experimenter decides how to use the test by choosing a cut-off value.
30.9).
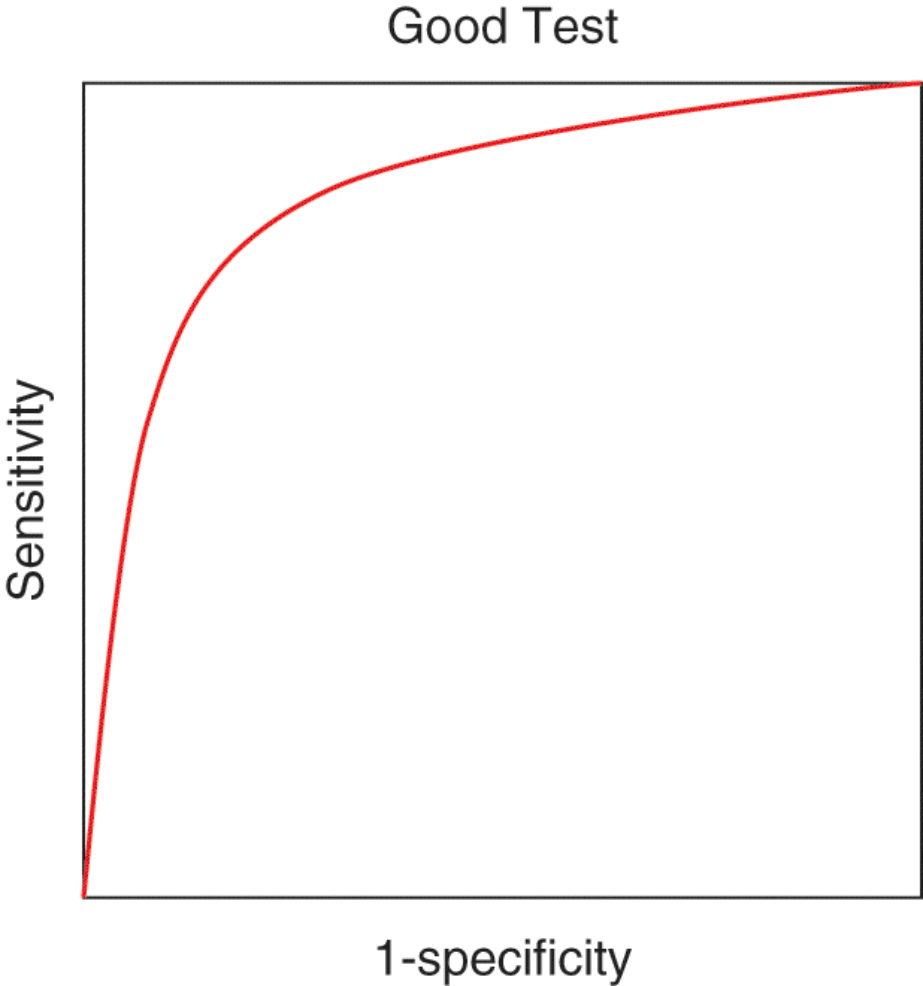
Figure 30.7 Good ROC curve.
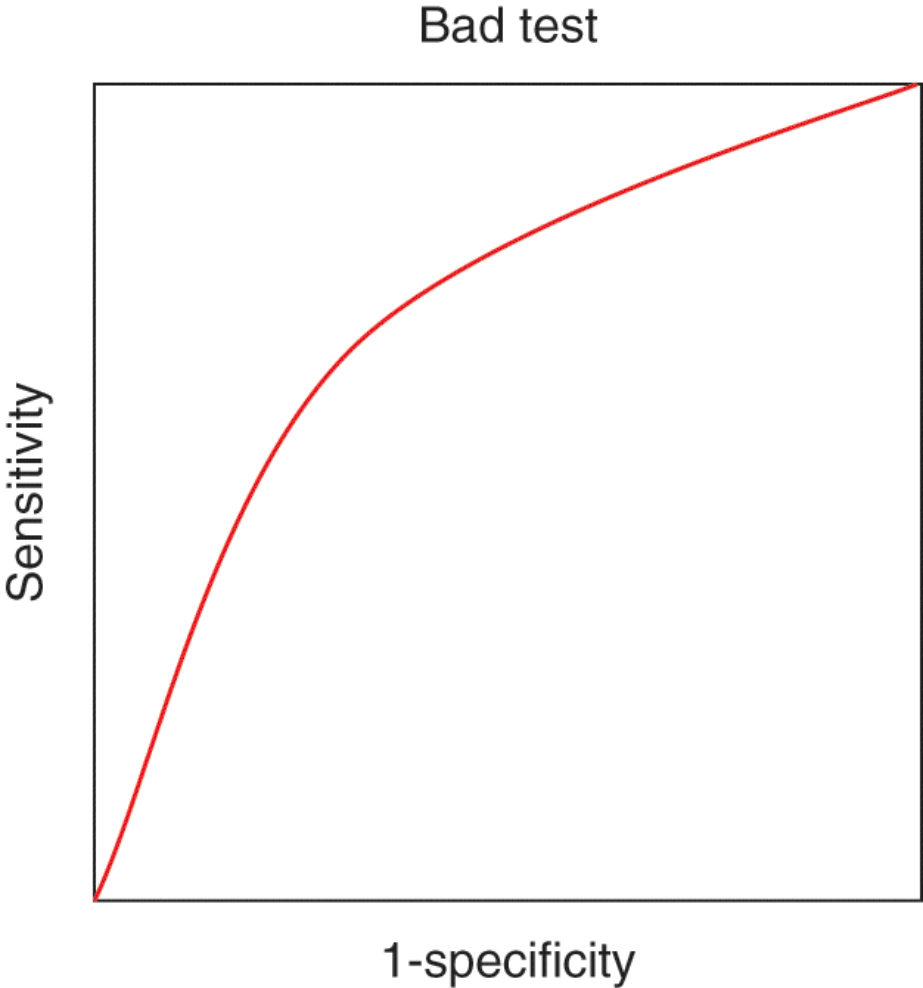
Figure 30.8 Bad ROC curve.
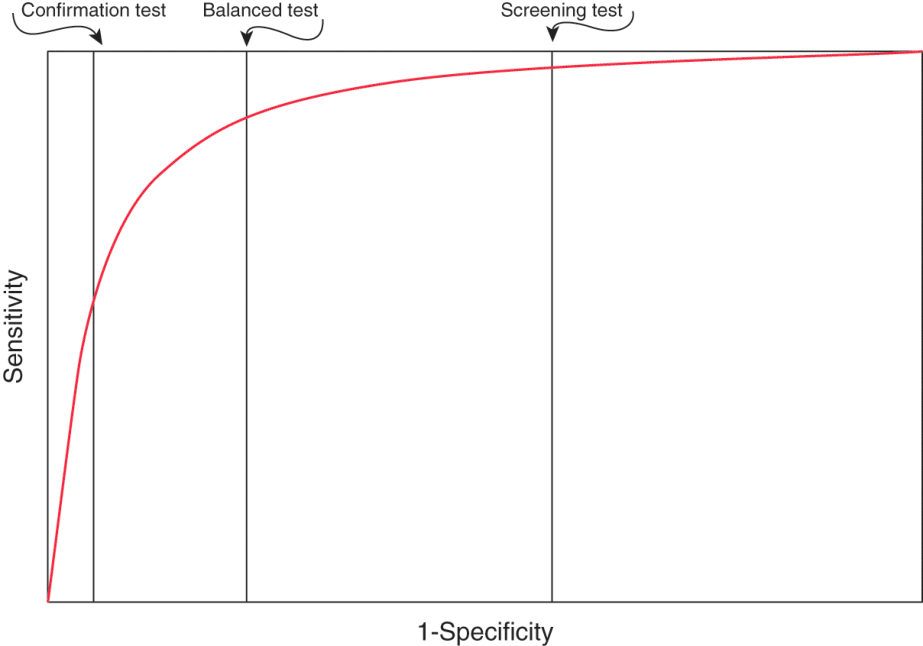
Figure 30.9 Different cut-off values result in a balanced testor a test that is optimized for use in screening or confirmation.
Structured oral examination question 4#
This is an abstract of an RCT comparing TXA to placebo to reduce blood transfusion in total knee replacement (Figure 30.10). Please, read the result section and t ell me your thoughts of the findings.
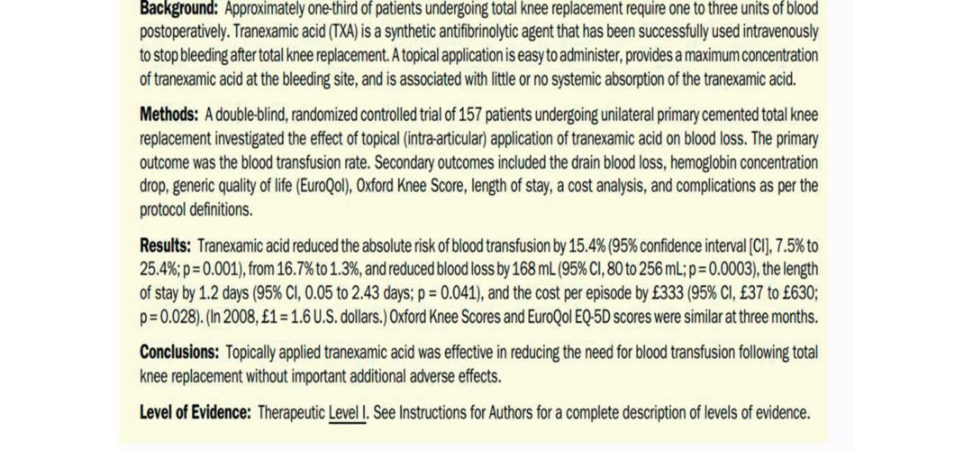
Figure 30.10 Journal abstract.
The results of the trial showed that TX Ahas been effective in reducing blood transfusion rates by 15.4% (from 16.7% to 1.3%). That was statistically significant (P = 0.0001). The trial also showed that TXA statistically significantly reduced blood loss.
What do you think about the 95% confidence interval?
The 95% CI for the blood transfusion was 7.5–25.4%; In other words, if this trial was repeated 100 times, then 95 out of those 100 times, the absolute reduction of blood transfusion would lie within between 7.5% and 25.4%.
How is CIre lated to the P-value?
Traditionally , researchers accept a P-value of less than 0.05. So , in the above study, there is 1 in 1000 (P = 0.001) risk that the 15.4% reduction in the transfusion rate happened by chance and not because of the TXA. For the same reason we should be careful not to discount studies when the P-value is close but higher than 0.05.
Which one would you prefer?
A CIt hat includes no difference between treatments indicates that the treatment under investigation is not significantly different from the control.
You mentioned that the CI of the above study was narrow. Would you prefer a narrow or a wide CI?
A suitable example might be of a confident candidate who is 95% confident to have scored between 70% and 80% in his FRCS exam. Contrast this with another candidate who is equally (95%) confident to have scored between 40% and 90%.
Could the above study findings be wrong and TXA does not reduce blood transfusion?
Yes, this is called type I error when a study concludes that a supposed effector relationship exists when in fact it does not.
How does it differ from type II error?
If this study failed to show that the TXA reduces blood.

Figure 30.11 Type I and II errors.
Which one is worse?
Both should be considered and minimized. The seriousness of the implication may vary depending on the scenario. A new test that fails to detect a cancer when it is.
How do you minimize errors?
A P-value of 0.05 indicates that we are willing to accept a 5% chance that we are wrong when we reject the null hypothesis. The probability of making a type II error is related to the size of the study and the power of the test to detect a difference in the primary outcome. We can minimize type II error by increasing the size of the study and/or ensuring our test has enough power (for example, using Hb level drop rather than swab weights to measure blood loss).
What is the null hypothesis?
As I mentioned earlier , an integral part of a research study is to formulate and test hypotheses. that there is no difference between a new and an old treatment. For example, I cannot reject the statement ‘all cats are white’ by showing you 1000 white cats. However, I could reject it by showing you one black cat!
Structured oral examination question 5#
Have a look at Figure 30.12. Do you know what this plot is?
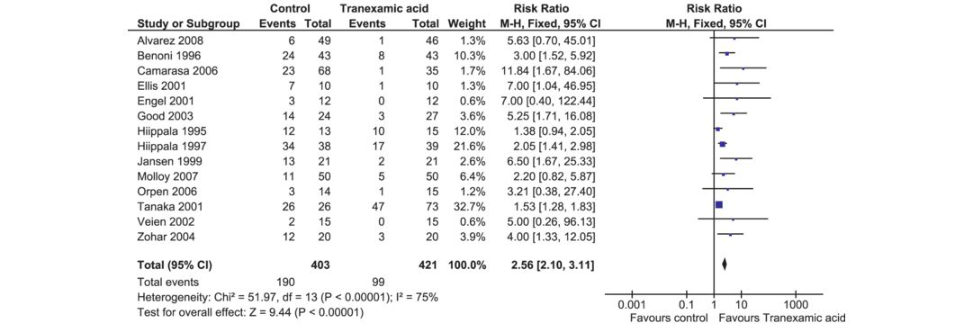
Figure 30.12 Forest plot.
This is called a forest plot (also known as a blobbogram). It numerically and graphically.
What is the difference between a review and meta-analysis?
The meta-analysis is another stage in conducting systematic reviews when authors combine data from different studies statistically with a view to get inga combined and more precise estimate of the interventions effectiveness This is not always possible due to data limitations.
Why do we need reviews and meta-analyses?
For many surgical procedures, there have been a number of clinical studies and it would seem natural to want to combine them to get the most comprehensive overview of the effect of treatment.
What do you mean by homogeneity?
interventions (type, dose, duration, etc.); outcomes (type, scale, duration of followup and usage). Such variations can introduce heterogeneity into study findings (variation greater than that expected by chance).
Heterogeneity can be formally tested using the χ2 heterogeneity testor Q statistic The significantly high Q test suggests heterogeneity.
Roughly, I2 values of < 50% indicate low, 50–75% indicate moderate, > 75% indicate high heterogeneity.
Back to Figure 30.12; can you explain the findings?
The forest plot represents 14 studies comparing tranexamic acid (TXA) to the control. The forest plot consists of several columns: 1. 2. The second column represents the events in the TXA group. It could be blood transfusion, DVT or PE rates. it is blood transfusion rates.) 3. The third column represents the number of participant sin the TXA group. 4. 5. The fitih column represents the number of participant sin the control group. 6. Tanaka 2001 is the highest weighted study (32.7%). 7. In this example it is the risk ratio which is equal to (events/total of the control) divided by (events/total in the TXA group). The risk ratio is one of several ways of presenting proportions: 8. The higher the weight of the study the larger the square (see Tanaka 2001). On each side of the square there is a horizontal line representing the confidence interval. Here, the no effect line passes through 1 because it represents a risk ratio. It would be 0 if it was a risk difference.
If a study plot touches the no-effect line, it means that its effect does not differ from no-effect for that individual study. if the points of the diamond overlap the line of no effect the overall result is ‘no effect’ at the given level of confidence. In this study, the diamond position favours TXA.
That is very good. What about the word ‘fixed’ and the letters ‘M-H’? What do they signify?
The Mantel–Haenszel (M-H) testis used to combine studies in this plot; this is used by the Review Manager (RevMan 5) sotiw are that was developed by Cochrane library. In this example, the size of the effect is a participant who had a blood transfusion. It is reasonable to assume the size of the effect is similar and use the fixed-effects model.
Can you give me an example where a random-effect model should be used?
Yes, when the effects are not similar. Although they measure the hip function, the y are not the same.
How would you interpret the finding in the plot?
The plot shows that TXA reduced the risk of transfusion by 2.56 times with 95% CI (2.10 – 3.11) and P-value 0.00001 (the test for overall effect). However, there is significant heterogeneity as evident by the high I2 value (75%) and this was statistically significant (P-value < 0.00001).
How to deal with heterogeneity?
I expect the authors to explore this heterogeneity further. 1. 2. For example, studies with a high dose of TX Aor those receiving TXA earlier rather than later, etc. 3. In this example, the authors used the fixed-effects model for combining studies. Using the random-effects model may uncover some of the heterogeneity.
4. In the above example, the outcome variable is the effect estimate (RR). The independent variables are characteristics of studies that might influence th eRR such as dose, timing of administration, the use of heparin, the use of transfusion protocol, etc.
Figure 30.13 is another plot of meta-analysis. In fact, it is from the same meta-analysis in Figure 30.12. Do you know the name of this plot?
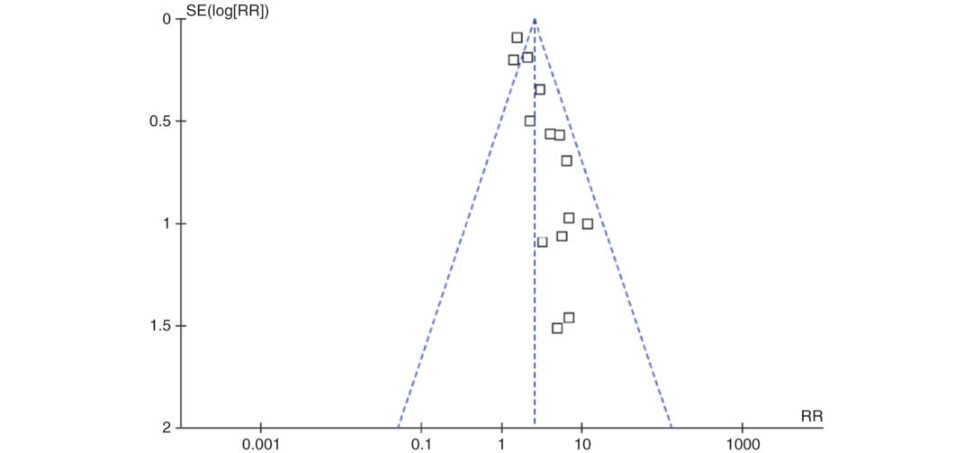
Figure 30.13 Funnel plot.
This is called a funnel plot which is a simple scatterplot of the treatment effects (risk ratio – horizontal axis) from individual studies (small squares) against the precision of the studies represented by standard error (SEver tical axis). SE is the standard deviation divided by the square root of the sample size. Hence, the larger the study, the lower the SE. It is expected that larger studies (big sample size) are more precise (low standard errors) and will be scattered very close to each other around the pooled effect at the top of the plot. The smaller studies are scattered widely toward theb oft om, giving the classical inverted symmetrical funnel. The funnel plot shows trials scattered asymmetrically around the pooled RR with small trials having greater effect. There are two explanations for these findings. This may be due to smaller trials of lower quality tending to overestimate the true effect; hence they are on the right side of the pooled effect. It might also reflect publication bias, where small trials that did not show benefit were not published (publication bias).
Authors’ note 7
See the below figures for comprehension: Figure 30.14 showed that I2 is 0% and there is no significant heterogeneity in the included
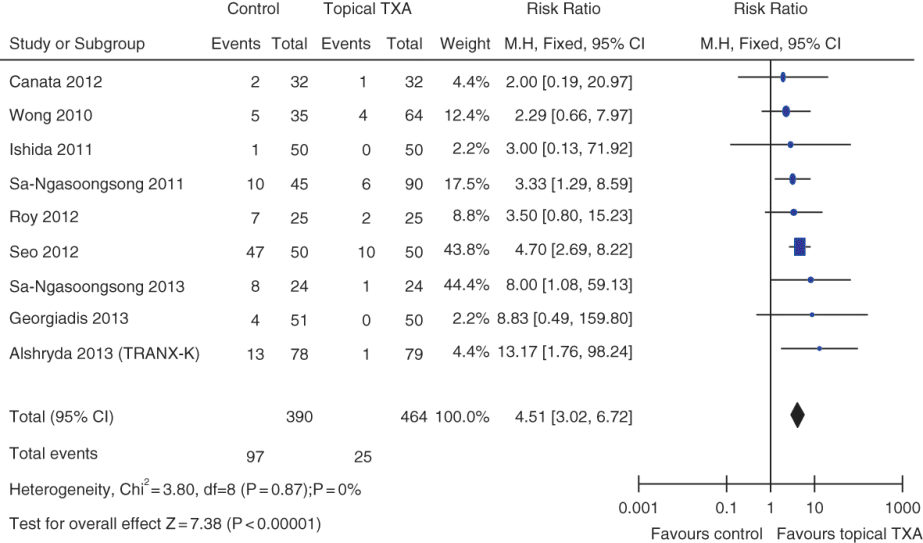
(effects against SE) and the plot showed the studies distributed symmetrically around the effect line (4.5 RR).
Figure 30.14 Forest plot with homogeneity.
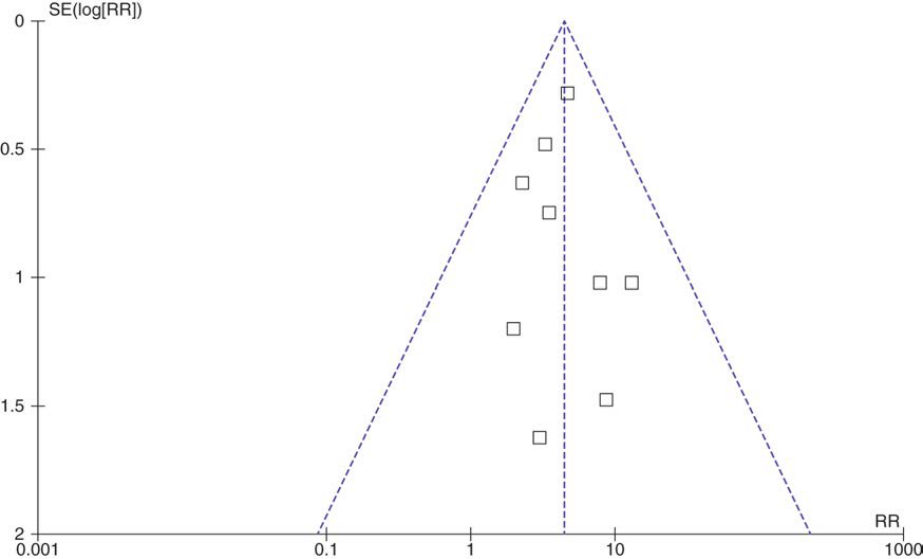
Figure 30.15 Funnel plot with symmetrical distributions of the studies around the effect line.
Structured oral examination question 6#
The following plot (Figure 30.16) is from the Norwegian Joint Registry about the effect of cement on the implant longevity. Can you describe the findings?
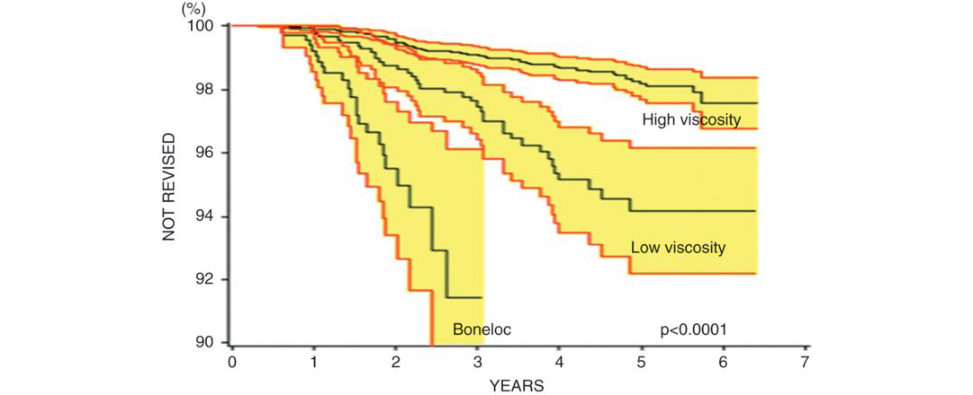
Figure 30.16 Survival analysis curve.
There is asta tis tic ally significant difference between the three groups (no overlaps in the confidence interval and P-value < 0.0001). The high viscosity cement seems to provide a higher survival rate where about 98% survived to 6 years.
What is a survival graph, why do you need this, could you not simply measure mean survival with CI?
Well, a survival graph measures ‘timet o event’, this graph looks at.
What are the different lines in this chart?
The midline is the mean value and the upper and lower lines represent the CI.
Why did the upper and lower lines diverge towards the right?
This is because as the study progressed there were fewer patients remaining in the study. therefore, the CI becomes wider.
Looking at this chart, can you predict the survival probability at 20 years?
No, it is not possible to estimate survival.
Can you estimate the mean revision time?
we can only estimate the cumulative risk of revision.
What do you understand by ‘censored data’?
If apa tien t diesis lost to follow-up or withdraws from.
So, are censored data wasted then?
No, they contribute data until the point of censoring.
Have you noticed an y, can you tell me if there is a problem with this chart?
Yes, the CI for Boneloc and low-viscosity cement is very wide, and I.
The below plot is from the National Joint Registry of England and Wales (Figure 30.17). Take a look at this chart and tell me what you understand.
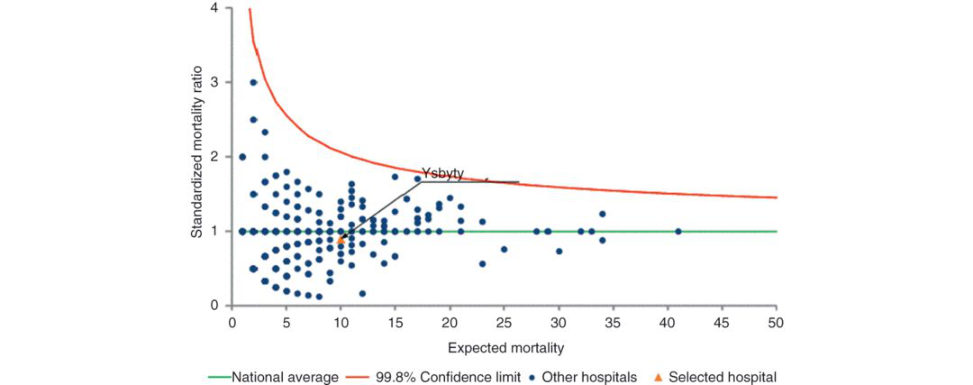
Figure 30.17 National Joint Registry report.
This shows the 90-day mortality rate following joint replacement (not specified in this chart whether hip or knee replacement) for a selected hospital (orange triangle). The central green line denotes the average national expected mortality and the redline denotes the 99.8% confidence limit. Progression along the x-axis means that the hospital has done more cases and/or cases at a higher mortality risk, such as older patients Progression along the y-axis means the hospital has had more deaths. This means the values do not represent percentages of patients who have died, but they represent the proportion of deaths compared to the average.
Hospitals on either side of the green line but below the upper redline have had a level of mortality (when taking into account their case mix and number of cases)
Hospitals above the top redline (which represents a ‘99.8%
Confidence Limit line’) would have.
So, how did this hospital do?
The hospital’s mortality was well within the expected mortality range.
Can you tell me anything about the type of patients the hospital operated on?
Yes, we can see that the orange triangle is not far along the x-axis.
Authors’ note 8: Survival analysis
Survival analysis originally studied time from treatment until death, hence the name, but survival analysis is applicable to many other areas as well as mortality. It estimates the time between entry to a study and a subsequent event. Events may include death, injury, revision of.
it assesses the relationship of co-variables to time-t o-event, such as antibiotic in cement, LMWH.
The following are important definitions.
the time from entry into a study until
Time-to-event: represented by a drop on the survival curve.
(1) lost to follow-up or (2) dropout of
Censoring: the study, or (3) if the study ends.
Censored subjects are represented by a 30.18).
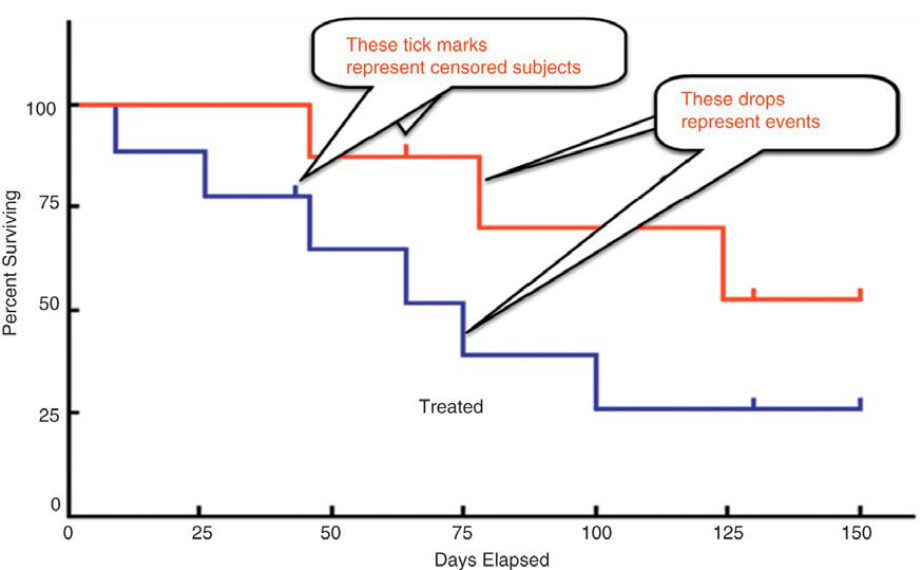
Figure 30.18 Survival curves.
The Kaplan–Meier survival curve is a non-parametric estimate of the survival function. Three assumptions are made in survival analysis:
1. We assume that at any time patients who are censored.
2. The survival probabilities are the same for.
3. We assume that the event happens at the time specified.
The Kaplan–Meier computes the probabilities of occurrence of the event at a certain point of time by multiplying these successive probabilities by any earlier computed probabilities to get the final estimate For each time interval, survival probability is calculated as the number of patients surviving divided by the number of patient sat risk. Patients who have died, dropped out, or move out are not counted as ‘at risk’. These are considered ‘censored’ and are not counted in the denominator. Total probability of survival until that time interval is calculated by multiplying all the probabilities.
The survival analysis design is important because:
1. It is not practical to wait untile vents have happened to all participants for example, all died) before we conclude a study.
2. Although we can compare mean time-t o-event between the groups using a.
3. Although we can compare proportion of events between the groups using risk/odds ratios.
Structured oral examination question 7#
What do you understand by PROM?
PROMs stand for Patient Reported Outcome Measures. They are short, self-completed questionnaires which measure the patients symptoms,.
Can you give me some examples?
PROMs can be generic or disease-specific. The European quality of life measure (EuroQol), Short form (SF) 36, SF12 and Notingham Health Profile (NHP) are examples of generic outcome measures.
What is the advantage of using PROMs?
In the past, clinician-based outcome measures were considered objective when the clinician was assessing patient progress using ‘hard signs’ such as range of motion strength, swelling, etc. Objectivity was dependent on the reliability or reproducibility of the clinicians’ assessments. In contrast, PROMs are.
What do you understand by a ‘validated’ outcome measure?
This means that the outcome measure has been tested and succeeded to show that it measures what it is supposed to measure. this is the quantitative assessment of validity.
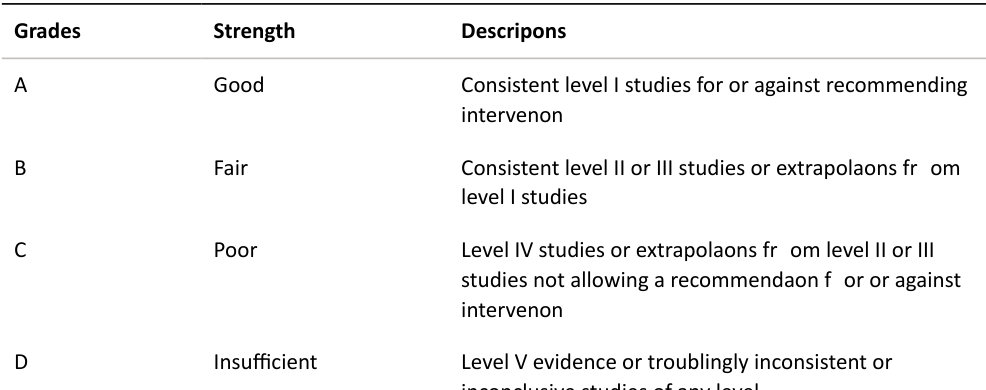
The following was copied from a paper on treating slipped upper femoral epiphysis. (Figure 30.19). Can you tell me what is meant by the grades (B, C and D) highlighted in yellow?

Figure 30.19 A selected paper with grade of recommendation.
These refer to the grades of recommendation, based on levels of evidence. Several have been described. I follow the one that is recommended by the Oxford Centre for Evidence-based.
Authors’ note 9: Outcome measures
Outcome measures have become an essential part of many research projects. In fact, a study is considered weak if outcome measures are not used. Having some.
This can be summarized as follows [11].
1. Content: (are the contents of the measure
Content items are generated in several ways. The following are considered when items are included, excluded or weighed:
A. Type:
i. Clinician-based outcome measure (CBOM).
ii. Patien t-based outcome measure (PROM).
B. Scale: what questions makeup the outcome? How.
C. Interpretation: do higher scores indicate a better.
2. Methodology: this involves assessing validity, reliability and.
A. Validity: does it measure what it is.
i. Construct validity: quantitative assessment of validity.
1. Divergent: two measures do not correlate highly.
2. Convergent: two measures have a high correlation.
Outcome measure must show both convergent and divergent validity evidence for construct validity.
ii. are the contents comprehensive and relevant?
This is established by content experts:
iii. Criterion validity: correlation with golden standard.
1. ability to predict the future state of health, e.g.
2. Concurrent validity: accurately predict current state of.
B. Reliability: measure the condition the same way.
i. that is why there are several questions to measure a single dimension.
ii. Reproducibility: produce the same results when there.
1. Intra-observer (test–retest): reproducibility when used on the same.
2. Inter-observer: agreement between two or more observers using the.
C. Responsiveness: ability of the measure to change.
3. Clinical utility:
APa tien ts’ friendliness (acceptability): easy to complete by patients.
B. Clinician friendliness (feasibility): easy to use and administer, does.
Table 30.3 Grades of recommendation.
References
1. Wright JG. A practical guide to assigning.
2. Phillips Bet al. Levels of Evidence (March
[cited 2012; available from: www.cebm.net].
3. Harbour R, Miller J. A new system.
2001;323(7308):334–336.
4. Chapter 1: Introduction to evidence-based practice . In H
Alshryda, JS Huntley, P Banaszkiewicz (Eds.), Paediatric Orthopaedics:
Clinical Questions , Cham: Springer; 2016: 51–75.
5. Howick J, et al. The 2011 Oxford
www.cebm.net/index.aspx?o=5653. 2011.
6. Why are randomised controlled trials important?
BMJ. 1998;316(7126):201.
7. Roland M, Torgerson DJ. 1998;316(7127):285.
8. Wright J, Eastwood DM. Clinical surveillance, selective
Alshryda, JS Huntley, P Banaszkiewicz (Eds.), Paediatric Orthopaedics:
Clinical Questions , Cham: Springer; 2016.
9. Goel MK, Khan naP, Kishore J. Understanding
Res. 2010;1(4):274–278.
10. Grades of Recommendation Oxford Centre for Evidence-based
www.cebm.net/?o=1025.
11. Suk M, Hanson BP, Norvell DC, Helfet SL (Eds.). AO Handbook. 2004.
Section 6