Chapter 4 Knee
Structured oral examination question 1#
TK Ain valgus knee
This is a radiograph of a 72-year-old lady complaining of pain and gradual deformity of her left knee ( Figure 4.1a and 4.1b). She has been referred to your clinic to be considered for total knee arthroplasty. What can you see?
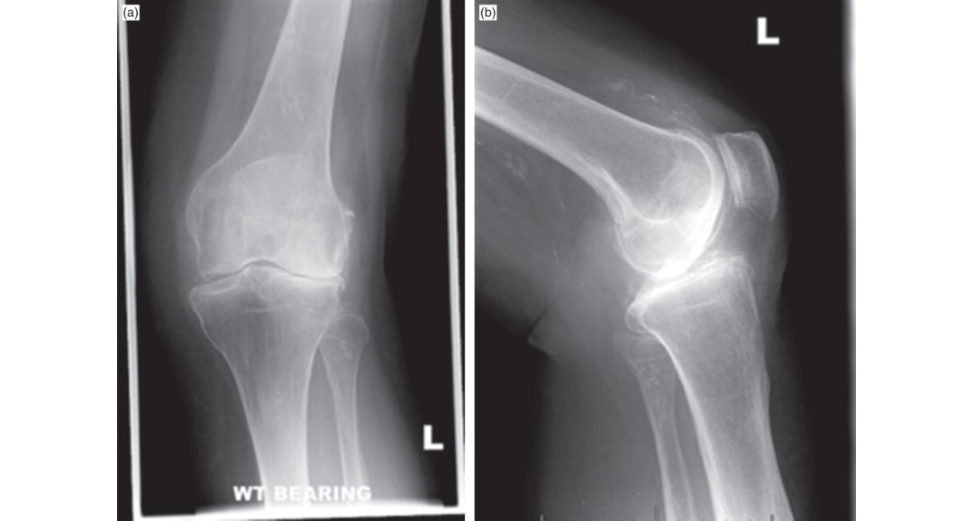
This is a weight-bearing AP radiograph of a 72-year-old female demonstrating severe osteoarthrosis of the left knee with moderate valgus deformity.
How will you manage this patient?
Firstly, I would establish what are the symptoms the patient is suffering from. How the pain is affecting activities of daily living such ascu ting toenails, puting shoes and socks on, how easy it is to go up and downstairs are all questions I would ask. Treatment to date is also important; has the patient had any physiotherapy/rehabilitation, trialled an y analgesics? Clinical examination findings such as assessment of the soft tissue envelope is also important. The competency of the knee collateral ligaments and degree of deformity correction should be assessed in order to plan the type of implants.
after the history and examination, what are you going to do?
The management should commence with non-surgical options and generally should be exhausted before surgical options are explored. As per the NICE guidelines, strengthening, low- impact aerobic exercise and neuromuscular education should all be recommended. Obese patients generally have an increased risk of infection and t end to have an earlier onset of symptoms [1].
What conditions are associated with this pattern of joint disease?
The valgus deformity of the knee with arthritis is commonly seen in women and in inflammatory joint conditions such as rheumatoid arthritis. overcorrection of high tibial osteotomy (HTO),
What are your technical goals of treatment?
My aims are the following: Restoring neutral mechanical axis of 0° (±3°). Balancing ligaments (2–3 mm symmetrical opening). Restoring normal joint alignment and Q angle.
How would you restore the mechanical alignment?
The bony cuts of the femur and tibia should both be made perpendicular to the mechanical axis of the limb. The natural tibia has 3° of natural varus to the mechanical axis; however, we do cut perpendicular to the anatomical/mechanical axis. This is usually 5–7°. The femoral component must be externally rotated by 3° with respect to the femoral neutral axis to create a rectangular flexion gap with the tibia. As the tibia was cut perpendicular to the mechanical axis, hence in 3° of valgus relative to the native plateau, the femoral component rotation will create a rectangular flexion gap.
Tell me more about the intraoperative considerations.
In valgus knees the lateral femoral condyle is often deficient. This is important to remember because if you perform posterior femoral condylar referencing for femoral component rotation the resultant position of the femoral component will be internally rotated with reference to the transepicondylar axis. In severe valgus deformity (7–10°) a distal femoral cut of 5 or 6° can improve patella tracking and avoid the need for lateral retinacular release. With correction of significant valgus deformity, one has to be cautious of the common peroneal nerve palsy in the postoperative period. It may be wise to identify the nerve to ensure no increased tension or damage occurs.
so what will be your choice of implant?
I would use a cemented implant. From the latest report of our National Joint Registry, over 84% of the primary TKA procedures performed are cemented, with less than 5% being uncemented and the remaining being a hybrid fixation. The reis, however, growing evidence for the use of uncemented knees [2]. There are theoretical advantages of mobile bearing devices over fixed bearing devices, such as reduction in shear stresses and subsequent wear as the tibial insert will be ablet o rotate on a smooth tibial plafoorm. However, I would use a fixed bearing insert; the Knee Arthroplasty Trial Group, after alarge multic entre RCT, concluded that there is no advantage with the mobile bearing designs [3–5]. It can also be used inpatients with previous patellectomy.
How would you manage gap imbalance?
Ligament balancing is essential for proper knee stability and range of movement. When both the flexion and extension gaps are tight options would be to reduce the polyethylene thickness or resect proximal tibia as this will equally alter both the flexion and extension gaps. A tight flexion gap with a normal extension gap would require downsizing of the femoral component or shitiing of the femoral component anteriorly [6,7]. Options of management would be to remove posterior osteophytes initially and release some posterior capsule. Flexion instability results when the flexion gap is larger than the extension gap and is often a result of undersized implants, incompetent PC Lor excessive tibial slope. It is imperative to ensure there is no anterior femoral cortex notching as a result of this shift.
Figure 4.1a,b Anteroposterior (AP) and lateral radiographs of left knee.
References#
1. Perry KI, MacDonald SJ. The obese pa tienta problem of larger consequence. Bone Joint J. 2016;98(1
Supple A):3–5.
2. Arnold JB, Walters JL, Solomon LB, Thewlis D. Does the … J Arthroplasty. 2013;28(5):740–746.
3. Campbell MK, Fiddian N, Fitzpatrick R, et al. The Knee … approaches to knee replacement. J
Bone Joint Surg Am. 2009;91(1):134–141.
4. Fransen BL, van Duijvenbode DC, Hoozemans MJ, … Arthrosc. 2017;25(6):1757–1777.
5. Van der Voort P, Pijls BG, Nou taKA, Val starER Jacobs … in 41 studies. Bone Joint J. 2013
Sep 1;95(9):1209–1216.
6. Bercik MJ, Joshi A, Parvizi J. Posterior cruciate-retaining versus posterior-stabilized total knee arthroplasty: a meta-analysis. J Arthroplasty. 2013;28(3):439–444.
7. Huang T, Long Y, George D, Wang W. Meta-analysis of gap balancing versus measured resection techniques in total knee arthroplasty. Bone Joint J. 2017;99(2):151–158.
Structured oral examination question 2#
Basic science: anatomy
This young gentleman sustained a varus type injury to the knee and there is a suspected posterolateral (PLC) injury. Can you describe the lateral structures of the knee by layers (Figure 4.2)?
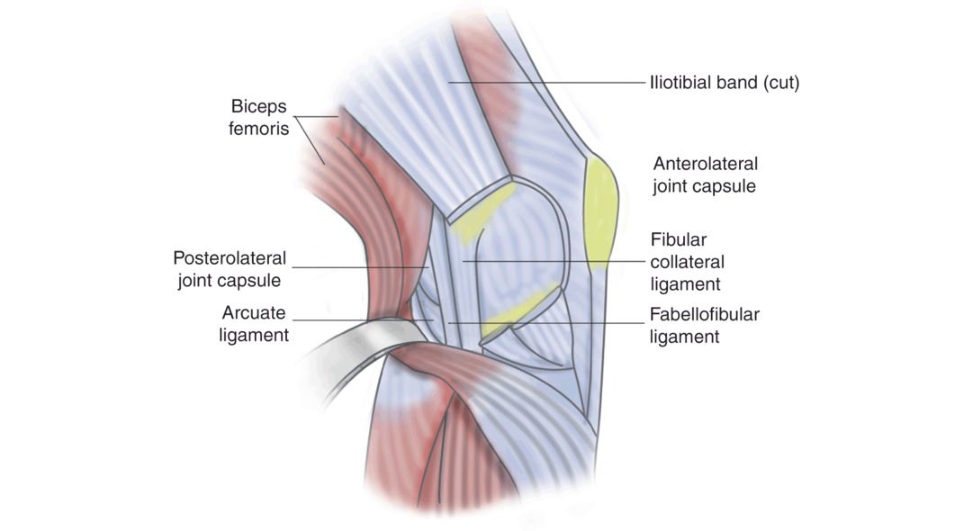
The lateral side of the knee comprises three main layers. The common peroneal nerve lies between layers one and two. The lateral collateral ligament (LCL), fabellofibular ligament and anterolateral ligament (ALL) lie superficially. The lateral genicular artery lies between the deep and superficial layers.
How about the medial side of the knee?
The medial side of the knee, similarly to the lateral side of the knee, is split into three layers. Gracilis, semitendonosis and the saphenous nerve run between layers one and two.
what is the function of the PL C and how commonly is it injured?
The role of the PL Cis to resist external tibial rotation, varus and posterior tibial translation. The PL Cis rarely injured in isolation and is often associated with multi ligament knee injuries; the PC Lis injured less often than the ACL.
Are you aware of any clinical tests to detect a PLC injury?
Hyperextension of the limb on passive extension testing can indicate a PLC injury. Initial g ait examination may reveal a varus thrust. I place the patient prone, and flex both knees to 30°. If there is more than 10° external rotation compared with the normal side, a PLC injury is diagnosed. I then flex both knees to 90° and repeat this manoeuvre. I also use the reverse pivot shift testI place the patient supine with the knee flexed to 90°. If the posteriorly subluxed tibia reduces at 40° of extension, this is interpreted as a positive result. The tibia reduces as a result of the ITB changing from a knee flexor to a knee extender.
What investigations would you perform?
A routine radiograph work up should be performed including anteroposterior (AP), lateral and axial views. Varus and PCL stress radiographs are reliable to assist in PC Land PLC injuries respectiv ely.1 Lateral compartment varus gapping of 2.7– 4 mm is consistent with isolated FCL injuries, whereas more than 4 mm indicates a severe-grade PLC injury. Kneeling stress radiographs are best to assess PCL injuries and an opening of 4–12 mm would indicate an isolated PCL injury.
What are the options of management?
It is rare to sustain an isolated PLC injury; however, if this were expected, the majority can be managed non-operativ ely.2 If part of a mulft-lig ament injury, the PLC should be addressed. Grade 3 injuries are a different entity and the reis good evidence to suggest poor functional outcomes and degenerative changes if non-operativ e measures are pursued. Options of operative approaches for grade 3 PLC injuries include acute repairs, which generally are reserved for bone or soft tissue avulsion injuries such as fibular head avulsions. 3,4 However, more recent evidence by Wester mannet al. has suggested good outcomes can be achieved with both repair and reconstruction of PL C injuries treated concurrently with ACL reconstruction a t 6- year follow-up.5 Anatomical reconstruction using tendon allograft and all three static stabilizers has been shown biomechanically to restore native knee biomechanics with improved outcomes.
Figure 4.2 Diagram representing lateral side of the knee.
References#
1. LaPrade RF, Heikes C, Bakker AJ, Jakobsen RB. The reproducibility and … study. J Bone Joint Surg Am. 2008;90(10):2069–2076.
2. Krukhaug Y, Mølster A, Rodt A, Strand T. Lateral ligament injuries of the knee. Knee Surg Sports
Traumatol Arthrosc. 1998;6(1):21–25.
3. Levy BA, Dajani KA, Morgan JA, Shah JP, Dahm DL, Stuart … ament-injured knee. Am J Sports Med.
2010;38(4):804–809.
4. Geeslin AG, LaPrade RF. Outcomes of treatment of acute … Joint Surg Am. 2011;93(18):1672–1683.
5. Westermann RW, Spindler KP, Huston LJ, Wolf BR. … J Sports Med. 2017;5(7_suppl6).
Structured oral examination question 3#
Meniscus
Tell me about the anatomy and function of the meniscus.
The menisci are crescentic cartilaginous structures interposed between the tibia and femoral condyles. Due to the loose attachment to the capsule, the lateral meniscus has twice the excursion to that of the medial meniscus. Histologically, the menisci have an extracellular matrix composed mainly of water (70%) and primarily type 1 collagen fibres (60%), proteoglycans, elastin and glycoproteins. The blood supply to the meniscus comes from the lateral, middle and medial geniculate vessels with 20–30% of the peripheral portion being vascular. The main functions of the menisci are load transmission with estimated 50% inextension and 85% inflexion, joint conformity and articular congruity, distribution of synovial fluid aiding nutrition and joint lubrication. The menisci also have proprioceptive function, act as shock absorbers and prevent soft tissue impingement during joint motion.
What are the vascular zones of meniscus?
The menisci are relatively avascular structures with peripheral blood supply from the premeniscal capillary plexus formed by branches from lateral and medial geniculate vessels. Studies have shown that the degree of peripheral vascular penetration is 10 –30% of medial meniscal width and 10–25% of lateral meniscal width.
These are the images which belong to a young professional footballer (Figures 4.3b and 4.3c). What can you see?
The first is asa gift al T1 MRI image and the secondis a T2-weighted image.
How would you manage this patient?
I would start by taking a detailed history and clinical examination ... [ EXAMINER interrupts].
How would you treat this patient? [ EXAMINER geting impatient]
I would offer this patient EUA, arthroscopy, repair or excision of bucket handle tear.
Good. What factors affect the prognosis following meniscal repair?
Firstly, the patient age dictates what I would do for the bucket handle tear. Re-tears are common inpatients above the age of 30. I am also much more inclined to preserve the lateral meniscus than the medial meniscus. Other factors include location and pattern, and associated pathology, i.e. ligamentous malalignment and pre-existing arthritis.
Are you aware of any meniscal repair techniques?
The four main meniscal repair methods are open repair, inside out, outside in and all inside.
Let’s move on ...
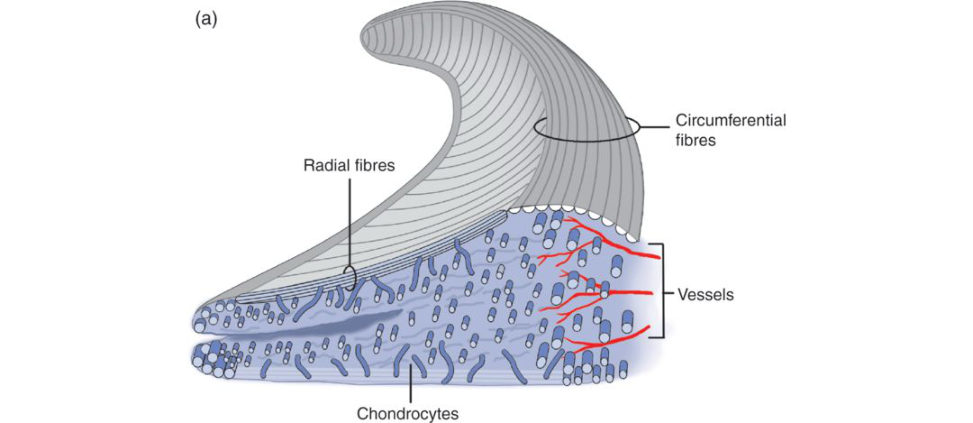
Figure 4.3a Cross-sectional anatomy of the meniscus.
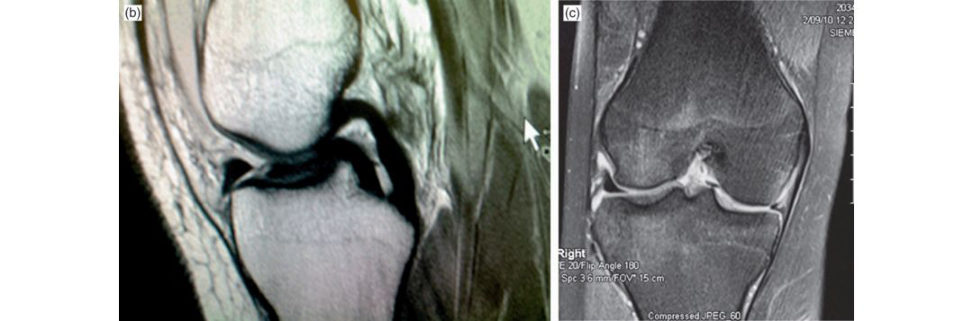
Figure 4.3b and 4.3c T2-weighted sagift al and coronal MRI scan images of the knee.
References#
Arnoczky SP, Warren RF. Microvasculature of the human meniscus. Am J Sports Med. 1982;10:90–95.
Structured oral examination question 4#
Infected total knee arthroplasty (TKA)
This gentleman had aTKA performed 3 months ago. Ten days after surgery he developed a large blister that was drained on the ward. Two weeks later he developed a draining abscess at the proximal aspect of the wound. He was taken to theatre and the abscess was washed out. The skin was debrided and closed primarily. Have you got any concerns?
An acute infection is defined by the American Academy of Orthopaedic Surgeons and the International Consensus on P JI as infection within 3 weeks of the procedure, or in the case of late haematogenous infection, within 3 weeks of development of symptoms.
These are the most recent radiographs and there are no other postoperative radiographs available (Figures 4.4a and 4.4b). What would you like to do for this patient?
I would start by taking a detailed history of the peri operative events, general health as well as current problem.
Are you aware of any staging systems with the use of periprosthetic joint infection?
Local compromising factors are also recorded and include whether active infection is present, synovial cutaneous fistula presence and a subcutaneous abscess of more than 8 cm2. Each category has different grades according to what they score.1
how would you diagnose a periprosthetic joint infection?
I would always start with the history and clinical examination of the patient. Even without signs of infection, a painful TKR can manifestas a low-grade infection.
Obtaining multiple intraoperative cultures, against initiating antibiotic treatment until after cultures and against the use of intraoperative Gram stain.
Nuclear imaging was weakly recommended as an option in patients in whom diagnosis of periprosthetic joint infection has not been established and who are not scheduled for reoperation.
The major criteria include either a sinus tract communicating with the prosthesis or if a pathogen is isolated by culture from at least two separate tissue or fluid samples obtained from the affected prosthetic joint,
isolation of a microorganism in one culture of periprosthetic joint fluid or tissue and (f ) > 5 neutrophils per high power field observed at ×400 magnification.
Anything else?
Analysis of the joint fluid which should include a leucocyte esterase assessment ...
Anything more recent in the literature?
The alpha-defensin test, which is an immunoassay, has recently been shown to have a sensitivity and specificity of 100% in the diagnosis of P JI.
how are you going to manage this case?
It is unfortunate, but I think this gentleman cannot be treated as an acute infection. I would offer this pa tienta revision knee arthroplasty.
And how would you do this?
There are, however, contraindications to this, including infection with a highly virulent organism, sepsis with substantial systemic manifestations and cultur e- negative PJI where appropriate antibiotic treatment cannot be determined.
... ?
I would plan for a two-stage exchange procedure where I would remove all the material I would insert an antibiotic-loaded dynamic cement spacer. 5 Debridement is the most essential part of the procedure with meticulous handling of soft tissues to remove all septic membranes.
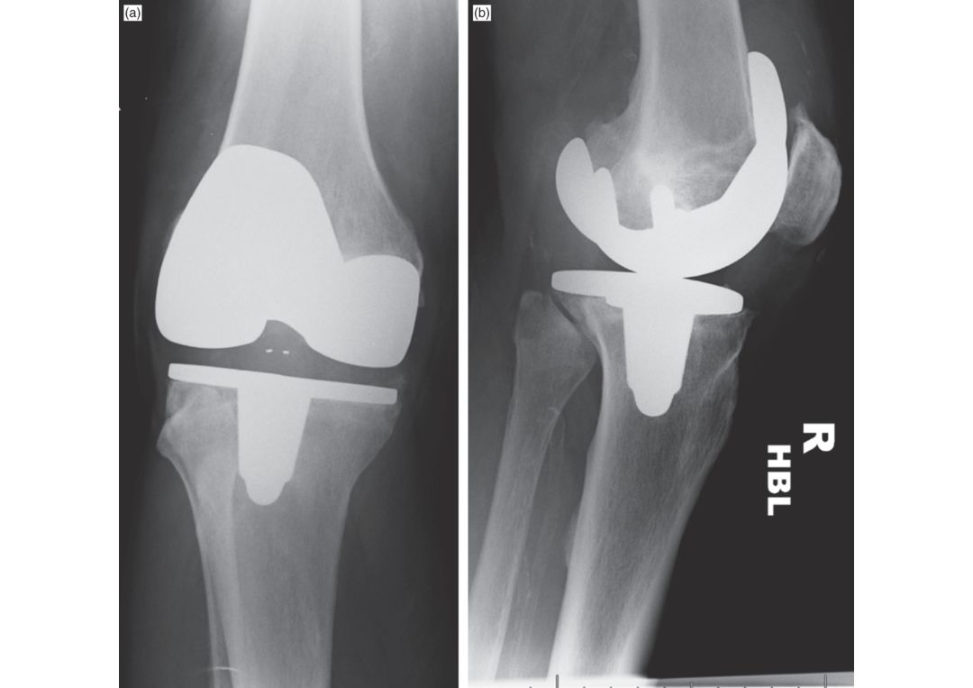
Figure 4.4a and 4.4b Anteroposterior (AP) and lateral radiographs of left TKA .
References#
1. McPherson EJ, Woodson CHol tom P, Roid isN, Shufelt C, Patzakis M. Periprosthetic total hip infection:
outcomes using a staging system. Clin Orthop Relat Res. 2002;403:8–15.
2. Della Valle C, Parvizi J, Bauer TW, et al. Diagnosis of periprosthetic joint infections of the hip and knee. J
Am Acad Orthop Surg. 2010;18(12):760–770.
3. Parvizi J, Zmistowski B, Berbari EF, et al. New definition for periprosthetic joint infection: from the
Workgroup of the Musculoskeletal Infection Society. Clin Orthop Relat Res. 2011;469(11):2992.
4. Deirmengian C, Kardos K, Kilmartin P, et al. The … Relat Res. 2015;473(1):198–203.
5. Ding H, Yao J, Chang W, Liu F. Comparison of the efficiency … arthroplasty: a meta-analysis. J Orthop
Surg Res. 2017;12(1):151.
Structured oral examination question 5#
Unicondylar knee arthroplasty (UKA) vs high tibial osteotomy (HTO)
This is a radiograph of a 42-year-old man who works as a bricklayer (Figure 4.5). He complains of pain over the medial aspect of the knee and has failed non-surgical management. He has come to your clinic for a consultation. What can you see?
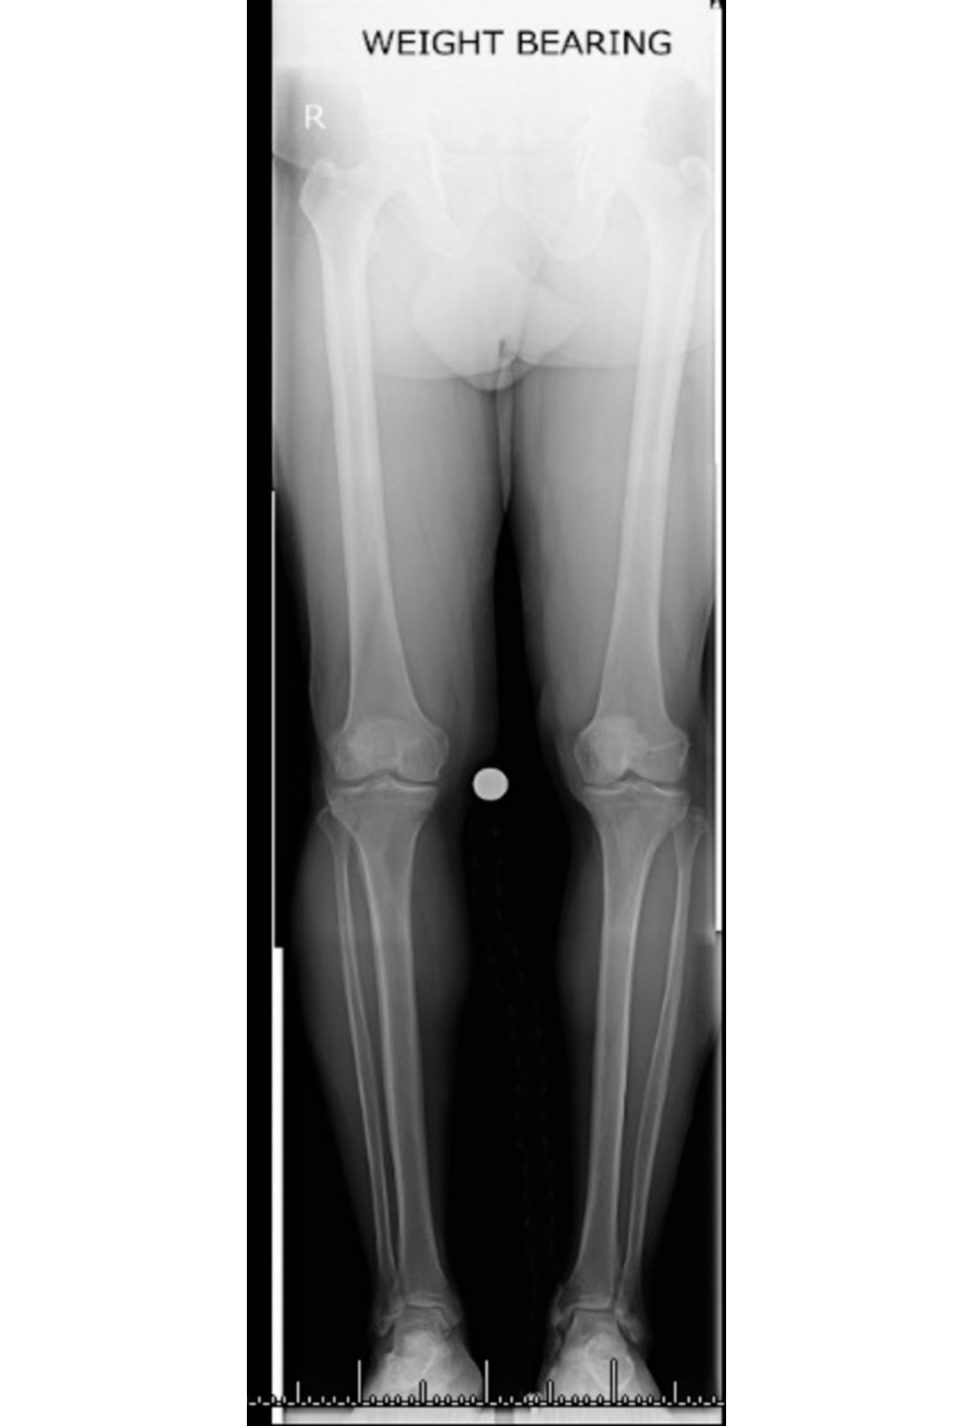
Crude assessment of the tibiofemoral angle appears to show a varus deformity of less than 10°. I would like to take a targeted history and examine the patient The examination should be focused on eliciting localized tenderness in the medial compartment, range of motion, if the varus deformity is correctable and the stability of the knee.
The patient is fit and well, states that the pain is affecting his job and he would like to consider surgical option 5. What would you offer him?
The options of surgical management include a valgizing osteotomy such as a high tibial osteotomy (HTO),
What are the prerequisites of an HTO? And what are your indications?
The ideal candidate for HTO is apa tien t with physiological age of < 65 years, fixed varus deformity < 15° or valgus deformity < 12°, fixed flexion deformity of < 15° and a flexion arc of more than 90°. Preoperative varus must exist and even patients with as liti leas 4° of varus can benefit from an HTO.
Are you aware of any contraindication for HTO?
I would avoid an HTO in apa tien t with marked decreased range of movement, i.e. flexion of less than 90° if possible. The main contraindications are inflammatory arthropathy such as rheumatoid arthritis and psoriatic arthropathy incompetent medial collateral ligament or ACL, large varus thrust with coronal subluxation of > 1 cm, although there are times one can adjust the tibial slope to compensate for ligament deficiency. Consideration of a closing osteotomy or cancellous gratiing are options.
The patient tells you that he has heard about closing wedge osteotomy arthroscopies and partial knee replacements and is keen to consider the alternative options. How do you proceed?
Thorlund et al. published a systematic review and meta-analysis of the benefits and harms of arthroscopy to the degenerative knee [1]. The reis also a recent randomized controlled trial, by Barton et al., demonstrating that an arthroscopy in the year prior to aTKA were linked with significantly reduced Oxford Knee scores; also this cohort had a higher revision rate over a four-year period [2].
which patients would you offer UKA?
The indications and prerequisites for HTO an dUKA are more orless the same between the ages of 55 and 65 years of age. A meta-analysis by Fu et al. demonstrated with careful patient selection that both HTO an dUKA demonstrate effective and reliable results [3].
Are there any contraindications to performing a UKA?
Previously old age, high activity le vel [4], obesity and pattern of OA were seen as contraindications However, recent evidence has shown this is not the case [3]. Increasing BMI has also been found not to be associated with an increased failure rate [6].
What are the advantages of a UKA?
By retaining the cruciate ligaments and remaining healthy joint surfaces, UKA restores the normal ligament driven kinematics of the native knee [7]. Patients undergoing UKA are halfas likely to have a major complication such as a myocardial infarction ors troke within the first 30 days after surgery.
how about the outcomes? Are they comparable? And what does the NJR state?
Lisowski et al. published a 10–15-year outcome prospective study. There was a mean follow-up of 11.7 years and results demonstrated excellent long-term functional and radiological outcomes with a 90% 15-year survival rate [8]. The 10-year revision rate published in the 13th annual report of the National Joint Registry was 12.38%. The low-volume surgeon and low- volume centres will have skewed the NJR revision rate [9].
Right let’s get back to our patient how about the results of TKA following HTO? Are they worse?
There is evidence to suggest the outcomes of TKA following HTO, especially an opening wedge osteotomy, are as good as TKA without a HTO [10].
Let’s say this patient has decided to go ahead with a HTO. How would you go about this? What would be your preference?
I always obtain full-length weight-bearing mechanical axis hip–knee–ankle radiographs. Native tibiofemoral varus alignment, medial joint space degeneration and lateral capsuloligamentous laxity need to be assessed. The Coventry group suggest overcorrection to 8° of anatomical valgus. A second line is dropped from the centre of the femoral head topass through the knee at the intended Mikulicz point (in a varus knee, aiming for 55% – width from medial tibial plateau), Line B. Two lines creating an angle are drawn connecting the caudal points of Line A and B.
You mentioned difficulty with conversion of HT Oto TKA. Tell me more about this.
I may need to consider staging the removal of metalwork and taking some deep samples to ensure infection is not present. Bone stock may be deficient laterally following a closing wedge osteotomy. More recent studies show that closing wedge osteotomy increases patellar height, whereas opening wedge osteotomy lowers patellar height, and this can have implications following TKA. Van Raaij et al. performed a systematic review and reported prolonged surgical time, extra operative procedures and less postoperative knee range of motion (R OM), but no increase in revision surgeries for patients receiving TKA after prior HTO compared topa tien ts receiving primary
TKA.
Figure 4.5 Standing anteroposterior (AP) lower limb alignment views.
References
1. Thorlund JB, Juhl CB Roos EM, Lohmander LS. … J Sports Med. 2015;49(19):1229–1235.
2. Barton SB, McLauchlan GJ, Canty SJ. The incidence and impact of arthroscopy in the year prior to total knee arthroplasty. Knee. 2017;24(2):396–401.
3. FuD, LiG, Chen K, Zhao Y, Hua Y, Cai Z. Comparison of … a me ta-analysis. J Arthroplasty.
2013;28(5):759–765.
4. Prest onS, Howard J, Naudie D, Somerville L, McAuley J. … Orthop Relat Res. 2014;472(1):105–110.
5. Tadros BJ, Dabis J, Twyman R. Short-term outcome … Arthrosc. 2018;26(5):1571–1576.
6. Ali AM, Pandit H, Liddle AD, et al. Does activity affect the outcome of the Oxford unicompartmental knee replacement? Knee. 2016;23(2):327–330.
7. Pandit H, Jenkins C, Gill HS, et al. Unnecessary contraindications for mobile-bearing unicompartmental knee replacement. J Bone Joint Surg Br. 2011;93(5):622–628.
8. Lisowski LA, Meijer LI, Bekerom MP, Pilot P, Lisowski AE. … from a non-designer group. Bone Joint J.
2016; 98B(10 Supple B):41–47.
9. Baker P, JamesonS, Critchley R, Reed M, Gregg P, Dee hanD. Center and … J Bone Joint Surg Am. 2013;95(8):702–709.
10. Meding JB, Wing JT, Rifter MA. Does high tibial osteotomy affect the successor survival of a total knee replacement? Clin Orthop Relat Res. 2011;469(7):1991–1994.
11. Niinimäki T, Eskelinen A, Ohtonen P, Puhto AP, Mann … 1,036 knees. Arch Orthop Trauma Surg.
2014;134(1):73–77.
Structured oral examination question 6#
Dislocate dUKA PE spacer
Have a look at these radiographs (Figure 4.6a and 4.6b). What can you see?
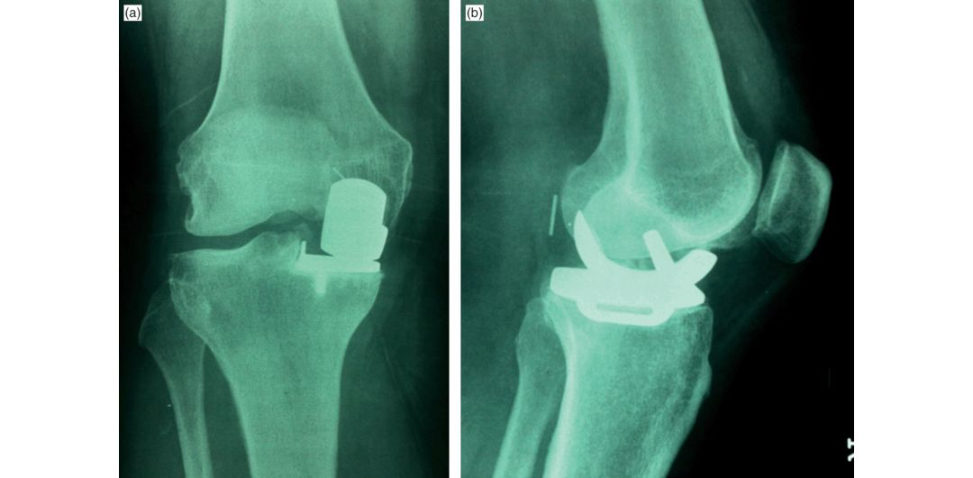
Weight-bearing AP and lateral radiographs of 54-year-old man showing a left media lUKA in situ.
What else can you see?
[A bit hesitant and moving closer to the computer screen. This is followed by a period of silence before the Examiner prompts]
The patient tells you that he fell while coming down the stairs, sustaining injury to the left knee. He complains of global pain and swelling of the left knee and inability to flex it. What’s going through your mind?
There is a faint radio-opaque line behind the femoral component and on the AP radiograph, aver tical lucency can beseen proximal to the medial tibial eminence.
How common is meniscal dislocation?
The meniscal dislocation rate for media lUKA is 1 in 200 and 10% in latera lUKA. The reis increased risk of bearing instability and dislocation with poor soft tissue balancing or unequal flexion and extension gaps.
Any other possible causes for dislocation?
Other causes could include intraoperative MCL damage, progressive stretching of the medial collateral ligament or bearing impingement on unresected osteophytes.
Why is there an increased risk of dislocation in latera lUKA?
Therefore, the medial compartment gets distracted about 2 mm on average in comparison with 7 mm on the lateral side.
How are we going to manage this case?
The spacer could be exchanged for a larger one, but it may dislocate again with continued flexion/extension imbalance.
Definitive management would be revision toPS knee replacement.
Figure 4.6a and 4.6b Anteroposterior (AP) and lateral radiographs UKA.
Structured oral examination question 7#
Posterior cruciate ligament and anterior cruciate ligament reconstruction
These are images of a 26-year-old rugby player who has given a history of falling awkwardly. What can you see (Figures 4.7a–4.7d)?
These are plain radiographs and MR Iof the right knee which show a displaced avulsion fracture of the posterior intercondylar tibial spine.
How would you treat this patient?
I would offer this patient reattachment of the PCL avulsion through open procedure.
What approach would you use?
The posterior approach.
Tell me about the posterior approach to the knee.
The indications include removal of popliteal cysts and neoplasms, posterior synovectomy, open reduction and internal fixation of posterior tibial plateau shear fractures, fixation of bone avulsions associated with a posterior cruciate ligament (PCL) injury, repair of posterior vascular injuries, and more recently, posterior inlay PCL reconstructions. The medial sural cutaneous nerve is identified beneath the fascia. Just lateral to the nerve is the short saphenous vein. The medial sural cutaneous nerve is traced proximally where it pierces deep fascia from the tibial nerve trunk. At the apex of the fossa, the common peroneal nerve separates from the tibial nerve. The tibial nerve lies posterior to the popliteal vein, which inturn is superficial to the popliteal artery. The main structures at risk are the popliteal vessels, small saphenous vein and common peroneal nerve and tibial nerve.
Can you tell me about the anatomy of the ACL?
The AC Lis an intra-articular structure but extra-synovial with a blood supply from the middle genicular artery. It arises from the medial border of the lateral femoral condyle and inserts proximally into the tibial spines. It primarily functions to prevent excessive anterior translation relative to the femur. The main consistency is type 1 collagen; however, there is some type III collagen.
When considering an ACL reconstruction, which gr aft would you use and why?
The two main options are autograft and allograft The two most popular autogratis are hamstring and bone–patella–bone tendon gratis (BPBG) [ 1]. However, hamstring gratis have slow healing properties because of tendon to bone incorporation, which can take 8–12 weeks. Most studies show arthroscopic reconstruction with either gr aft results in similar functional outcome but increased morbidity in BPT Bin the form of early OA and increased knee laxity [2–4].
How about in revision ACL reconstruction? Does the type of gr aft affect the outcome?
[5] published a meta-analysis looking into just this. Autogratis had better outcomes than allogratis in revision ACL reconstruction.
Now tell me about the optimum tunnel placement of your bony tunnels in an ACL reconstruction.
The principles of ACL reconstruction are placement of tunnels anatomically and isometrically, using biologically active gratis which are adequately tensioned to allow early rehabilitation. The clockface method is a method for assessing femoral tunnel height; however, without proper alignment of the arthroscope it can be imprecise. In order to achieve ‘graft isometry’ the optimal position of the femoral tunnel was thought to be 11 or 1 o’clock depending on the side of surgery. These ridges, the lateral intercondylar ridge and the bifurcate ridge, will dictate where I place the femoral tunnel; however, this does require some extensive ACL remnant resection. This restricts flexion of the knee and may result in elongation of the gr aft causing incompetence and recurrent instability.
a tunnel placement results in excessive tightening of the graft when the knee is extended.
The presence of impingement with correct placement of the tunnels necessitates notchplasty of the anterior portion of the lateral femoral condyle.
How would you manage a child with an ACL injury who came to your clinic? Say she was 12 years old?
I would counsel the patient with regards to rehabilitation and activity modification . One should always consider the physis when planning reconstruction, as damage to the distal femoral physis can cause deformity. If transphyseal reconstruction is considered, then soft tissue gratis need to be used and bone plugs need to be avoided.
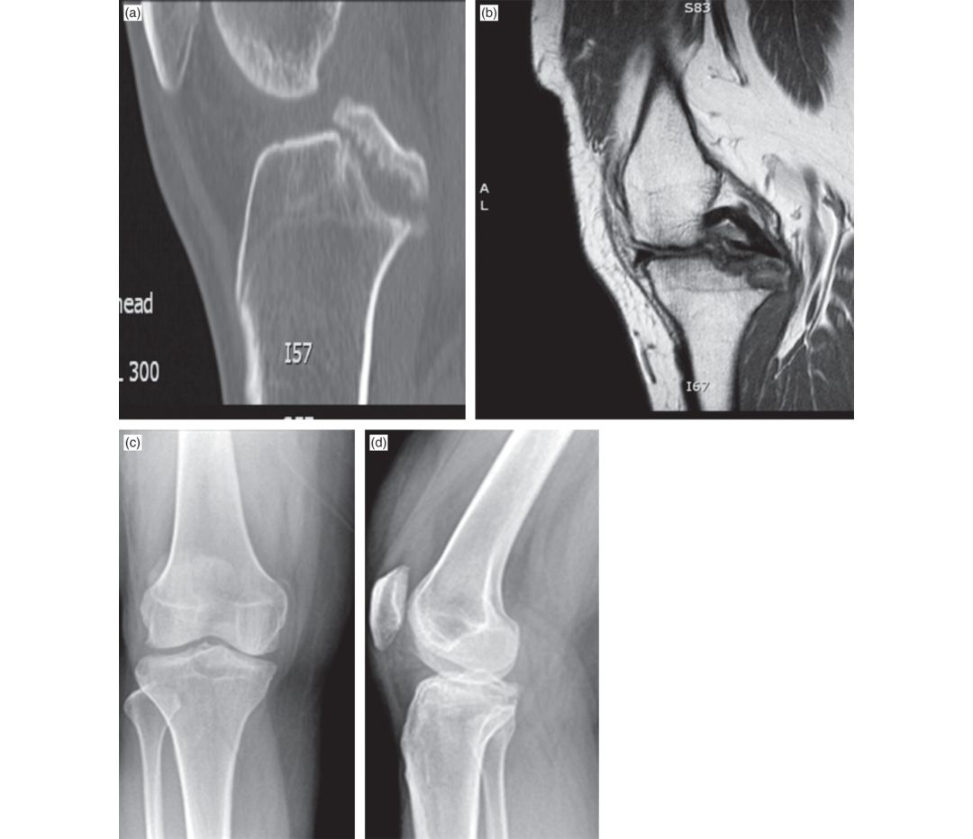
Figure 4.7a, 4.7b, 4.7c and 4.7d CT, MRI and plain radiographs of right knee.
References#
1. Xie X, Liu X, Chen Z, Yu Y, PengS LiQ. A … ligament reconstruction . Knee.
2015;22(2):100–110.
2. Xie XX iao Z, LiQ, et al. Increased incidence of osteoarthritis of knee joint … years. Eur J Orthop Surg Traumatol. 2015;25(1):149–159.
3. Howell SM, Taylor MA. Failure of reconstruction of the anterior cruciate ligament due to impingement by the intercondylar roof. J Bone Joint Surg Am. 1993;75(7):1044–1055.
4. Webster KE, Feller JA, Hartnett N, Leigh WB, Richmond AK. … trial. Am J Sports Med. 2016;44(1):83–90.
5. Gras siA, Nit riM, Moulton SG, et al. Does the type of … Bone Joint J. 2017;99B(6):714–723.
Structured oral examination question 8#
Revision knee replacement
Have a look at these images and tell me what you can see (Figure 4.8a and 4.8b).
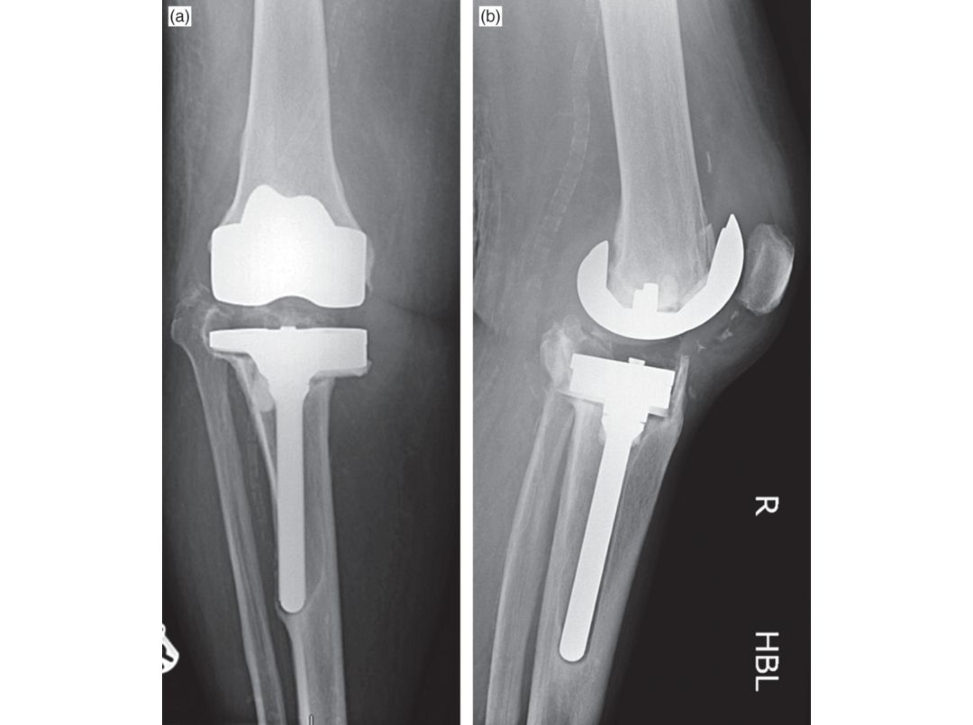
These are AP and lateral radiographs of a failed left total knee replacement. The tibial component is stemmed and has a medial augment, suggesting that this in itself is a revision implant. The radiographs are suggestive of infection un til proven otherwise.
. After investigation you conclude this is aspetic loosening. The patient is keen to consider single-stage revision surgery. What are your concerns with regards to these radiographs?
The collateral ligaments are likely to be dysfunctional, especially the MC Las the tibial component has subsided significantly and may be compromising the insertion of the MCL. The soft tissue envelope shadow on the radiograph appears contracted and calcified which may lead to wound complications. I would always take deep samples in all revisions to exclude infection asP JI can often be misdiagnosed.1 The extensive bone loss will require a stemmed implant to promote load-sharing of the diaphysis.
And what are your goals of surgery?
I would want to restore the joint line by achieving well-fixed implants and achieve a stable knee joint in a balanced fashion.
Are you aware of any classification system for bone loss around knee arthroplasty?
The most commonly used classification system is that of the Anderson Orthopaedic Research Institute (AORI), which classifies the femur (F) and tibia (T) separate lyas follows: Type-1 – Intact metaphysical bone with minor defects which will not compromise the stability of a revision component. Type-2 – Damaged metaphysical bone.
Type-3 Bone loss which comprises a major portion of either condyle or plateau. These defects are occasionally associated usually require long-stemmed revision implants
What are the factors you need to consider in the preoperative planning?
It is important to establish, prior to surgery, what components are present, their sizes, the level of constraint, and the surgical approaches previously used. The extraction of the implants and fixation methods all need to be planned prior to surgery.
How would you optimize your exposure in a revision knee replacement?
I would utilize a longer skin incision to identify virgin territory. A full synovectomy needs to be performed and there is a plane which needs exploiting between the muscle and synovium. I may need to use a rectus snip or quadriceps turndown or even a tibial tubercle osteotomy (TTO). A TTO provides excellent exposure and avoids an extensor lag which may beseen with a V-Y turndown as it avoids any violation of the quadricep s tendon. The main problem is a non-union following fixation. The PCL should be sacrificed to aid balancing and assessment of the tibial plateau.
You mentioned that a constrained implant may be required. What are the levels of constraints?
The constraint ladder within knee implant design includes TC3 (Figure 4.8c). High central post which will substitute for a MCL deficiency and requires medullary stem support. ↓
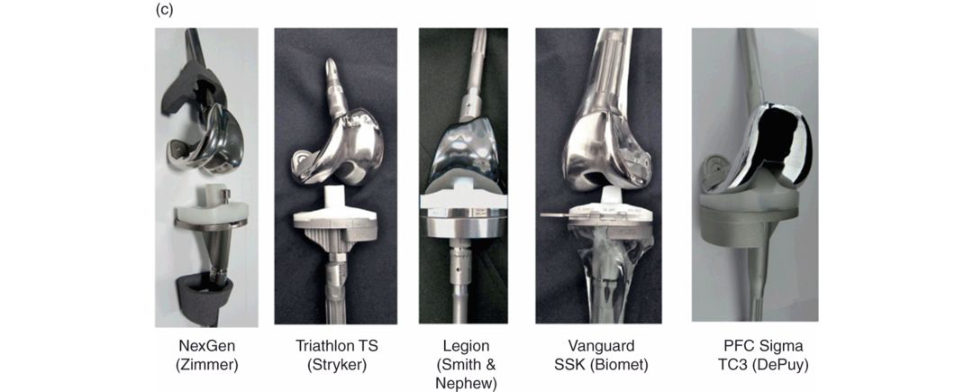
Used for global instability (total collateral disruption/r ecurvatum) and severe distal femoral bone loss, osteolysis/fracture.
↓
Fusion – may be required for chronically infected unstable knee with a poor soft tissue envelope .
What is your intraoperative plan for revising a knee replacement with bone loss?
Removal of implants, i.e. extraction, is the first step. My aim is to achieve stable fixation a t the epiphysis, but often one has to use stemmed implants to achieve diaphyseal fixation aswell as metaphysical sleeves to achieve press-fit metaphysical fixation, especially when there is a significant amount of bone loss. Distal femoral augments can be used to match the flexion gap.
[Going back to the radiographs] What are the principles of management of bone loss in revision knee replacement in this patient?
The options of management of the extensive bone loss are: 1. 2. The use of bone gratiing with structural or morsellized graft. 3. The use of modular augmentation of the components with wedges or blocks of metal. Recent studies show modular porous coated press fit metaphyseal sleeves may be used to fill AORI type 2 and 3 defects and provide for stable ingrowth. 4 The utilization of cus tom-made, tumour or hinge implants.
Figure 4.8a and 4.8b Anteroposterior and lateral radiographs revision TKA.
Figure 4.8c Commonly used CCK systems.
References#
1. Koh IJ, ChoWS, Choi NY, Parvizi J, Kim TK; Korea Knee … knee arthroplasty? A multic enter study.
Knee. 2015;22(3):180–185.
Structured oral examination question 9#
Patellar instability
A 17-year-old lady is referred to your patella clinic by her GP due to recurrent bilateral patella dislocations. How would you assess this patient?
I would start by taking a detailed history followed by clinical examination. In the history, I would enquire about age at first dislocation frequency of dislocations traumatic or a traumatic, an y associated syndromes such as bone or connective tissue dysplasia and generalized joint laxity. Examination of the patella includes assessment of coronal and rotational alignment and patella height.
What are the risk factors for patella instability?
The risk factors for patellar instability are complex and multifactorial; however, they can be subcategorized in the following sections: 1. 2. Malalignment. Patellar malalignment is an abnormal rotational or translational deviation of the patella along any axis. External tibial t orsion/foot pronation increased femoral anteversion and genu valgum especially in adolescence – miserable malalignment syndrome. 3. Soft tissue (dynamic). Core muscle instability in the hip. 4. Abnormal gait.
5. Genetic factors such as connective tissue disorder syndromes and generalized hypermobility.
Two-thirds of patients are known to have multiple anatomical factors predisposing to recurrent patella dislocations.
Tell me about the important stabilizers of the patella.
It provides 50–60% of the total medial restraining force and resists lateral translation in early knee flexion (20–30°). Amis et al. concluded that the origin was the medial epicondyle [1]. Following on from his work, Schötile et al., in a cadaveric study, identified a radiographic point for the origin, 1 mm anterior to the posterior cortex extension line, 2.5 mm distal to the posterior origin of the medial femoral condyle and proximal to the level of the posterior point of the Blumensaat line on a lateral radiograph with both posterior condyles projected in the same plane, which represented the mean femoral MPFL isometric centre [2]. During acute patellar dislocation the reis a 90–95% incidence of damage to the MPFL. In the past 10 years, MPFL reconstruction has become a popular procedure for treatment of recurrent patellar dislocation. Dejour et al. examined CT scans on 134 patients treated for patellar instability. They identified f our common factors of unstable symptomatic knees: (1) trochlear dysplasia (85%), (2) quadriceps dysplasia (83%), (3) patella alta (24%), (4) tibial tuber osity–trochlear groove distance, pathological when greater than or equal to 20 mm (56%) [3].
How would you investigate this patient?
I would perform the following investigations: 1. A true lateral radiograph is the most helpful view for assessment of patella height and trochlear depth.
2. Axial radiographs (Merchant’s view) to assess patellar tilt angle (normal < 10°), congruence, lateral patellofemoral angle (normal 138°) and trochlear dysplasia.
3. Rotational profile CT scans assess femoral anteversion which normally is 5–15°, If the TT–TG is more than 19 mm this is pathological.
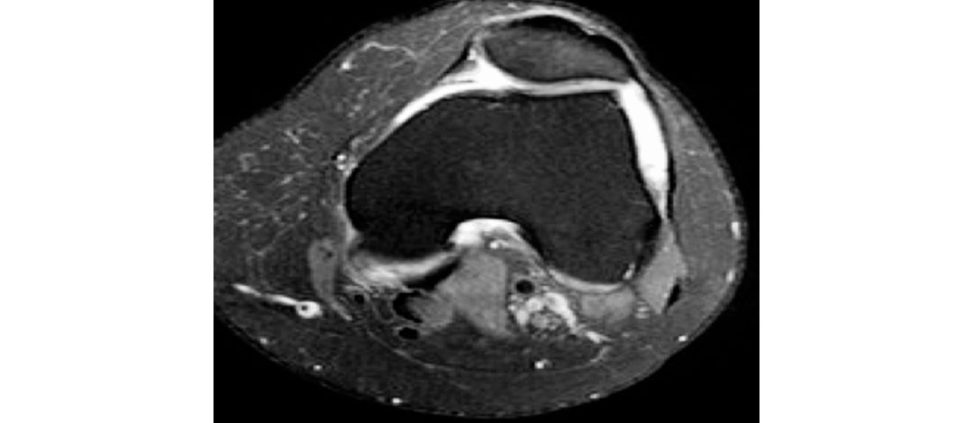
4. MRI for articular surface assessment (OCD), integrity of the MPFL, patella height, TTTG and trochlear dysplasia (Figure 4.9a).
When assessing the patella height, I use the Caton–Deschamps method. A ratio of more than 1.2 indicates patella alta.
I use the lateral view with the knee in at least 30° of flexion.
When would you offer a lateral release?
I would only perform a lateral release if there were isolated lateral patellar tilt. I would not perform this procedure independently.
What are the options of surgical treatment?
Generally, surgical procedures for chronic patellofemoral instability are often used in combination and include bony and soft -tissue procedures at the level of the joint, proximal or just distal to it. The parameters in the Patellar-Instability Severity Score (PIS- Score) include age, patellar tilt patellar alta, TT–TG distance, trochlear dysplasia and positive anamnesis of contralateral patella dislocation. A sc ore of more than 4 indicates a higher risk of redislocation. An ideal candidate for this should have a history of recurrent dislocation and a physical examination demonstrating excessive lateral patella translation and a normal trochlea [4]. A Caton–Deschamps index up to 1.3 can be acceptable, except where there is a very short trochlea or significant knee hyperextension. The key bony procedures for patella instability are: trochleoplasty, tibial tuberosity osteotomy and femoral osteotomy (derotation or angular) [5].
Figure 4.9a MRI scan, T2 axial view demonstrating lateral patella subluxation, knee effusion and shallow trochlea groove.
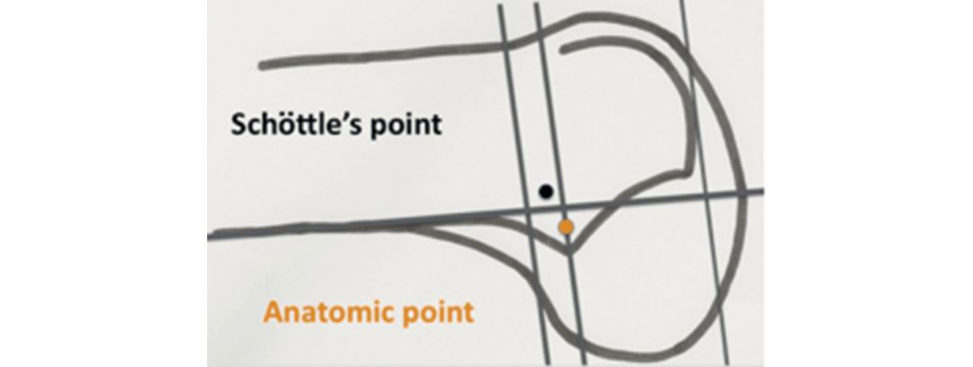
Figure 4.9b Schötile ’s point.
References#
1. Amis AA, Firer P, Mountney J, Senavongse W, Thomas NP. Anatomy and biomechanics of the medial patellofemoral ligament. The Knee. 2003;10(3):215–220.
2. Schötile PB, Schmeling A, Rosenstiel N, Weiler A. … Am J Sports Med. 2007;35(5):801–804.
3. Dejour H, Walch G, Nove-Josserand L, Guier C. Factors of patellar instability: an anatomic radiographic study. Knee Surg Sports Traumatol Arthrosc. 1994;2(1):19–26.
4. Yeung M, Leblanc MC, Ayeni OR, et al. Indications for medial patellofemoral ligament reconstruction: a systematic review. J Knee Surg. 2016;29(7):543–554.
5. Steensen RN, Bentley JC, Trinh TQ, Backes JR, Wilft on … am agne tic resonance imaging study. Am J
Sports Med. 2015;43:921–927.
Structured oral examination question 10#
Pain after TKA
A 70-year-old gentleman has been referred to your clinic with ongoing pain in his knee following his primary uncomplicated TKA. He states the knee has never been quite right since his surgery three years ago. Please describe these radiographs (Figure 4.10a and 4.10b).
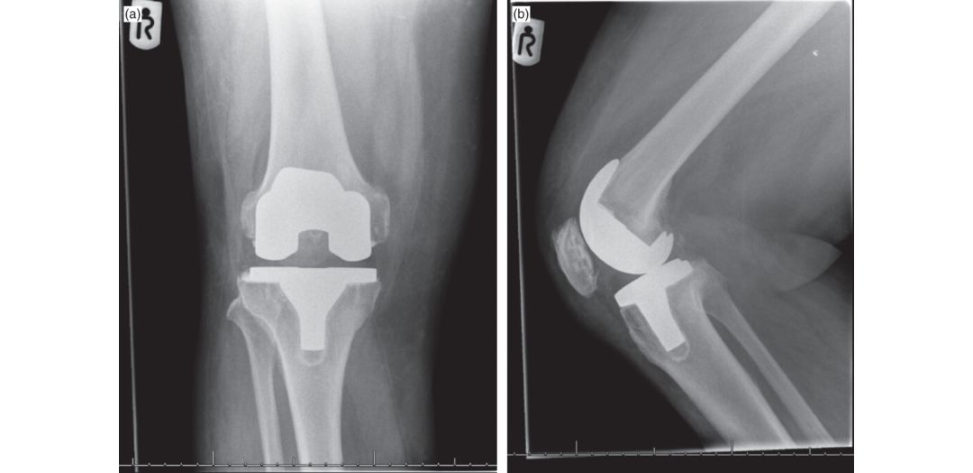
These radiographs demonstrate a cemented cruciate-sacrificing posterior stabilized implant. There is no evidence of tibial tray overhang or over-/under-sizing of the femoral component.
This patient is complaining of generalized knee pain. How would you proceed?
Firstly, I would take a history. If infection has been excluded it is important to differentiate between extra- and intra-articular causes of pain. Lack of pain relief immediately after the TKA could suggest that the pain was not actually originating from the knee.
so this gentleman states his pain was no different following his TKA. What do you think of that?
Extra-articular causes of pain around the knee need to be excluded. Firstly, the hip should be assessed; pain may be radiating from the hip to the knee via the obturator nerve. This will subsequently cause changes in the ground reaction forces and increased lateral loading of the knee [1].
you have suggested causes of pain above and below the knee. What else can cause the pain?
Vascular insufficiency with peripheral artery disease can cause leg pain in the elderly. The history will also identify lumbar spinal stenosis which may require further imaging for assessment. There are multiple periarticular bursae such as the infrapatellar, pes anserine and semimembranosus bursae which can cause pain and inflammation Lateral pain with movement between 20 and 80° classically is a result of iliotibial band dysfunction.
but these causes are all outside the knee. What are the intrinsic pathologies which you should exclude?
Aseptic loosening is common and is frequently described as ‘start-up pain’. Malalignment and wear are frequently responsible for late loosening.
I agree. Aseptic/ septic loosening needs to be excluded. What else?
Pain can be caused by instability as the soft tissues are overloaded. Early failure related to instability may be associated with trauma or more importantly surgical technique.
Tell me how you would assess for malalignment of components?
I would organize a standard radiological series including a skyline view and a CT scan.
What are the consequences of rotational malalignment?
Rotational alignment of the tibial and femoral component plays an important role in TKA. Once correct frontal alignment and proper soft tissue balancing has been achieved , the rotational placement of the components represents the ‘third dimension’ in knee TKA. Femoral component malposition has been implicate din patellofemoral maltracking following TKA, which is associated with anterior knee pain, subluxation, fracture, wear and aseptic loosening [ 1,2].
Do anything about how you determine rotational alignment of aTKA on CT?
Patients with painful early TKA should be assessed for evaluation of mal rotated components.
Anything else?
[Silence] Bergeret al. have described methodology to quantitatively measure component rotational alignment using CT scanning [3].
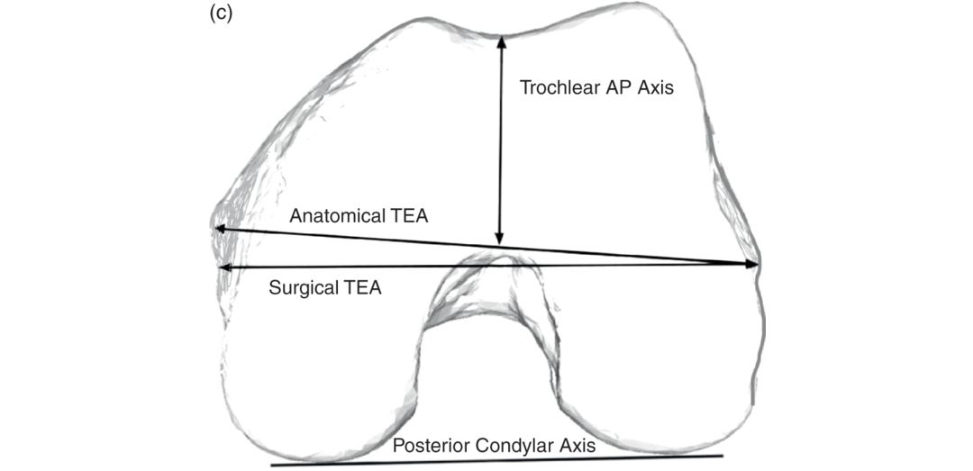
essentially the surgical transepicondylar axis (TEA) is on average 3° externally rotated in relation to the posterior condylar axis while the perpendicular axis to the trochlear anteroposterior axis is 4° externally rotated to the posterior condylar axis and finally the anatomical TEA is on average 5° externally rotated to the posterior condylar axis (Figure 4.10c).
The rotation of the tibial component (tibial posterior component axis) is measured in relation to the posterior tibial plateau axis,
Tibial component axis normal value = 18°.
Figure 4.10a and 4.10b Anteroposterior and lateral radiographs right TKA.
Figure 4.10c Femoral component rotational alignment.
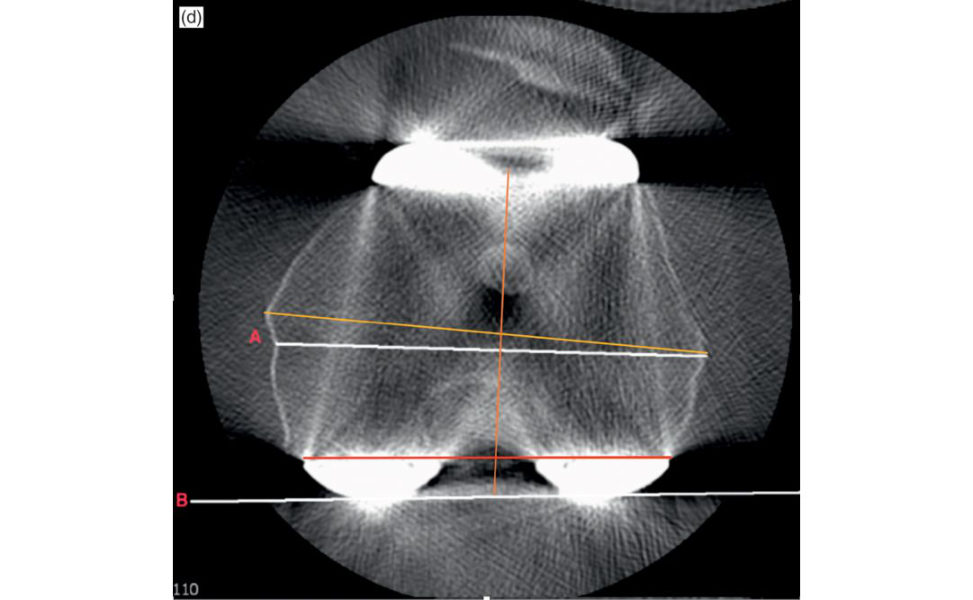
Figure 4.10d CT measurement of femoral implant rotation. The posterior condylar bone cut (redline) is 1–2° internally rotated in relation to the surgical TEA (whiteline A). However, the whiteline B represents the line of the posterior condyle of the femoral component. The yellow line represents the anatomical TEA and the orange line represents Whiteside’s line.
References#
1. Mandalia V, Eyres K, Schranz P, Toms AD. Evaluation of patients with a painful total knee replacement. J
Bone Joint Surg Br. 2008;90(3):265–271.
2. Nicoll D, Rowley DI. Internal rotational err or of the tibial component is a major cause of pain after total knee replacement. J Bone Joint Surg Br. 2010;92B:1238–1244.
3. Berger RA, Crossett LS Jacobs JJ, Rubash HE. Malrotation causing patellofemoral complications after total knee arthroplasty. Clin Orthop Rel Res. 1998;356:144–153.
Structured oral examination question 11#
Osteotomies around the knee
A 28-year-old gentleman who works as a postman attends your clinic, complaining of knee pain. He has had it for many years but is now unable to work. What do you think (Figure 4.11a)?
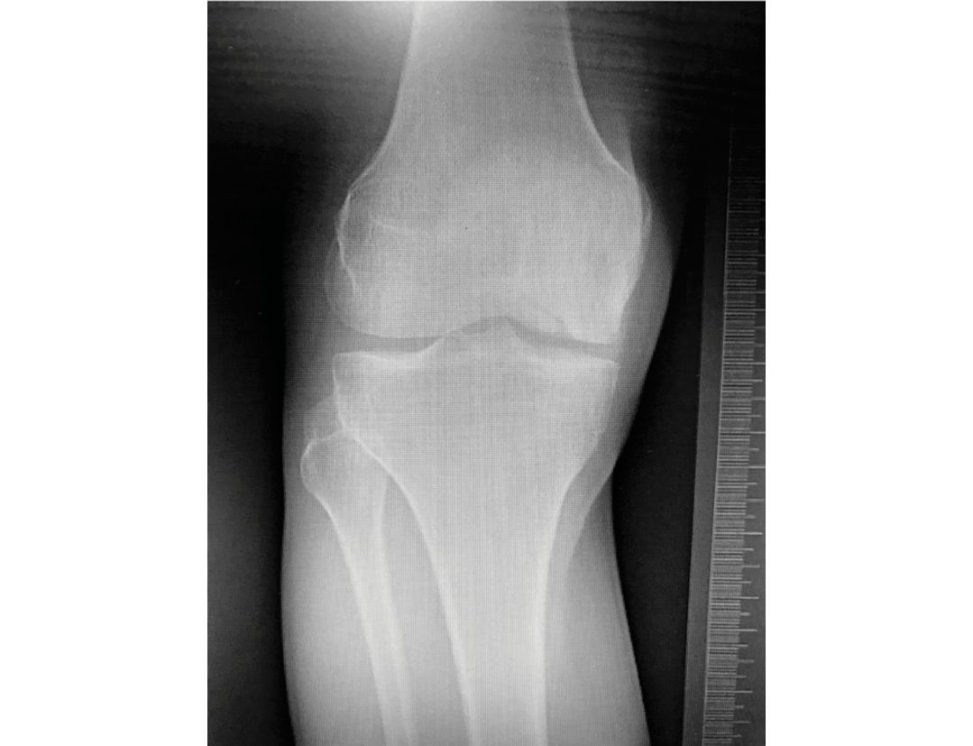
The weight-bearing AP radiograph demonstrates narrowing of the medial tibiofemoral joint space.
What are the pertinent features in the history and examination?
I would like to find out if this is traumatic or a traumatic, take a detailed pain history including site, severity and if he has mechanical symptoms. I would assume this patient has had osteochondritis dissec ans in the past.
let’s assume he has been through all conservative treatment and is keen to undergo surgery. Tell me about your management plan.
Firstly, I would like to assess his lower limb alignment. If I were to offer him a chondral procedure, I would certainly ensure his overall alignment is not in varus.
What would you like to see?
I would also like to see a lateral and some further imaging of the joint surface would be helpful to plan further surgery.
so what information would you like?
Firstly, I would like to assess the deformity in the frontal plane, and according toPa ley, should include the mechanical axis of the lower limb, overall malalignment, lateral distal femoral angle (LDFA), medial proximal tibial angle (MP TA) and the joint line convergence angle (JLCA). The tibial width is gi vena percentage of 100% starting medially (0%) and ending laterally (100%).
Tell me, what are the key biomechanical parameters and normal values for frontal alignment?
The LDFA is normally 87° (85–90°) and theM PTA is normally 87° (85–90°). The JLCA is 0–2° [1] (Table 4.1).
what do you think of this patient’s full-leg standing radiographs (Figure 4.11b)?
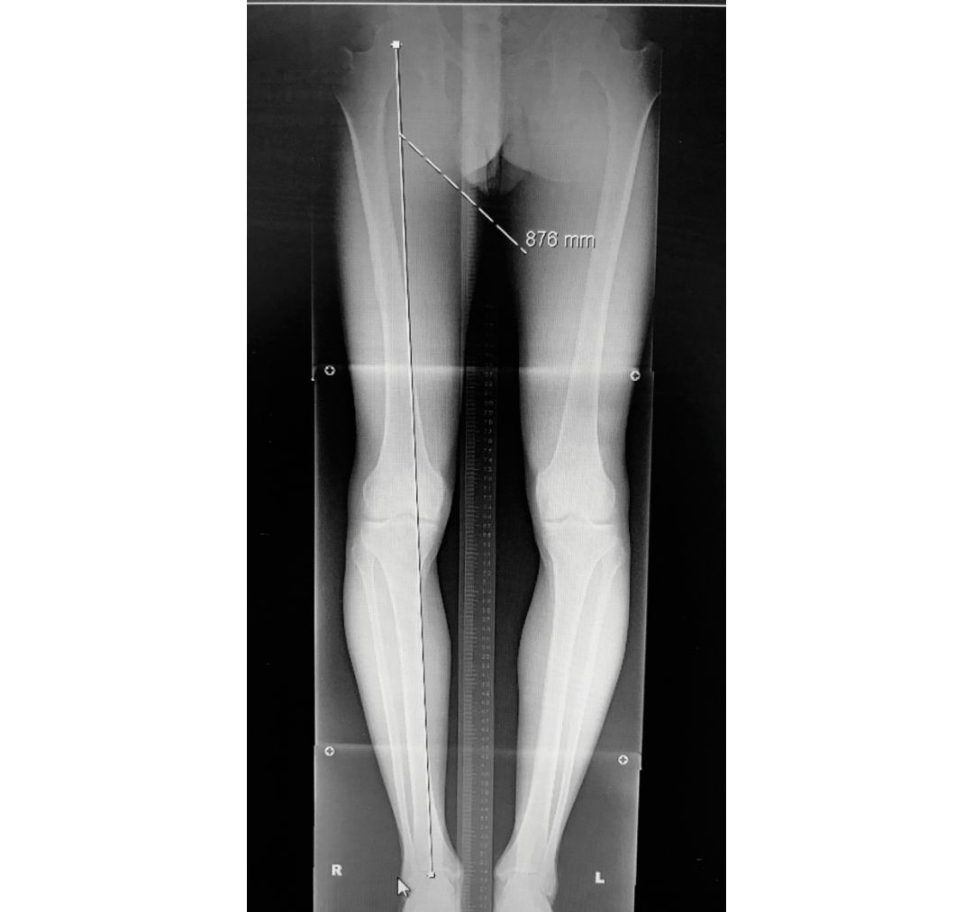
He looks to be in varus. The weight-bearing line is passing well into the medial compartment.
the MRI demonstrates the OC Din the MFC, the meniscus is preserved and there is some chondral thinning of the medial tibial plateau. What would you offer him?
Firstly, I would offer him a valgizing osteotomy. Once his alignment is corrected, I will be able to safely perform some form of chondral surgery, if needed.
... Please explain the rationale.
I would like to offload them and perform a valgizing osteotomy in the form of a high tibial osteotomy or distal femoral osteotomy.
Explain?
I perform an osteotomy in the bone where the deformity lies. As we can see from the limb alignment analysis (Table 4.1), theM PTA is 80°, which isabnormal. As theM PTA is 80°, normal being 87°, the deformity lies in the proximal tibia.
What osteotomy would you offer him?
Given the proximal tibia is inv arus, and this is where the deformity lies, we will need to increase theM PTA to the normal 87°.
Why?
The opening wedge HTO has gained popularity because it does not require a fibular osteotomy, common peroneal nerve dissection disruption of proximal tibiofibular joint, and bone stock loss (Bonasia et al., 2014).
if you’ve decided on a medial opening wedge HTO, how would you go about it and tell me the considerations intra operatively?
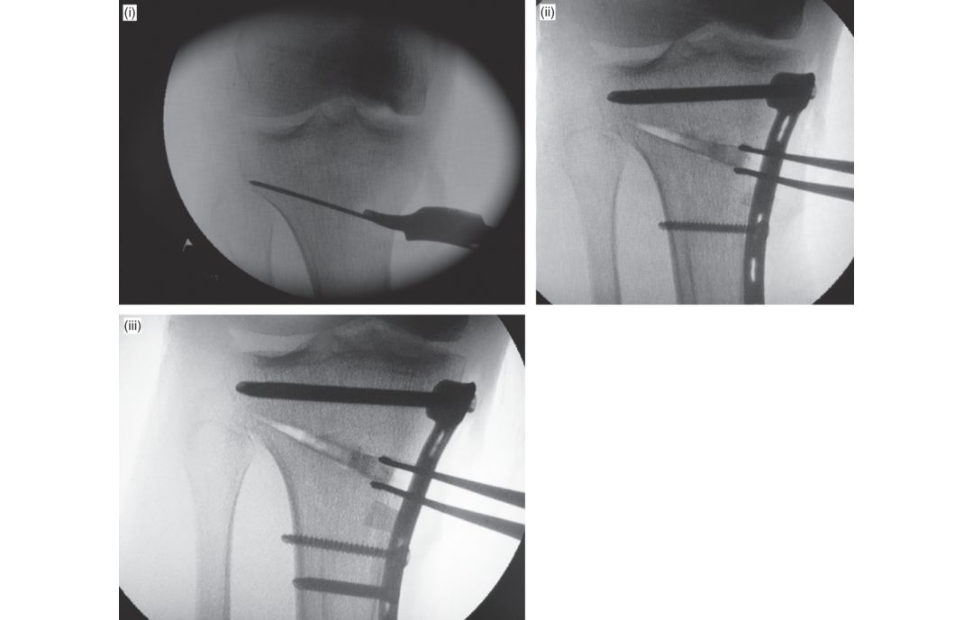
I would prepare the patient supine on a radiolucent table under tourniquet with intravenous antibiotics a t induction. I would approach the proximal tibia via a direct anteromedial oblique approach. I would mark out my biplane osteotomy to increase the stability of the construct. To ensure the trajectory of the saw cut is in the plane of the joint, I place 2 K-wires parallel with the joint under fluoroscopy. The callipers are then used to measure the exact distance for the opening wedge as per the preoperative plan to 0.1 mm (see
Figure 4.11c).
What would be your postoperative rehabilitation programme?
I would like to see an X-ray at the six weeks mark to ensure there has been no less of correction.
Figure 4.11a Weight-bearing anteroposterior (AP) radiograph of the right knee.
Figure 4.11b Standing anteroposterior (AP) longleg radiographs.
Table 4.1 Limb alignment analysis.
Angle

(i) Positioning of the first guide wire, note the position of the hinge point.
(ii) Application of the T omofix plate following opening of the wedge.
(iii) Image demonstrating maintenance of the gap opening following gap filling and application of the plate.
Figure 4.11c Intraoperative images of opening wedge HTO.
References#
1. Paley D, Herzenberg JE, Tetsworth K, McKie J, Bhave A. Deformity planning for frontal and sagift al plane corrective osteotomies. Orthop Clin North Am. 1994;25(3):425–465.
2. Bonasia DE, Dettoni FS ito G, et al. Medial opening … Am J Sports Med. 2014;42(3):690–698.
3. Staubli AE, Jacob HAC. Evolution of open-w edge … IntOrt hop. 2010;34(2):167–172.