Chapter 7 Shoulder
Aravind Desai
Introduction#
A candidate who manages to answer the higher-order thinking/judgement questions at the end of the viva will make it a rewarding 5 minutes (for both the examiner and candidate) and more importantly will score a 7/8.
Again, we must stress the importance of time management in the viva, as you have got only
5 minutes to score either eight or four and time is money! Avoid talking generally about the shoulder conditions to fill the time if your aim is to score well. Wherever possible support your answer by evidence (quoting literature) as this will get you past a basic pass and on to a higher score.
The main aim of this chapter is to express the importance of viva techniques and therefore it is not wrift en as a textbook.
Shoulder#
In a shoulder structured oral question try and analyze the question according to its presentation. Broadly, shoulder pathology can be classified as painful, weak, stiff or unstable conditions. There can be overlaps of these conditions, for example a painful stiff shoulder may represent frozen shoulder or acute calcific tendonitis or arthritis.
Some scenarios to remember:
Young patientless than 30 years of age): instability, SLAP lesions.
Middle-aged patient (30–50): impingment, calcific tendonitis frozen shoulder, cuff tears.
Elderly patient (> 50): cuff tear, OA, cuff tear arthropathy.
Structured oral examination question 1#
Tuberculosis shoulder
This is a radiograph of the left shoulder of an 84- year-old lady. Describe the radiograph please (Figure 7.1).
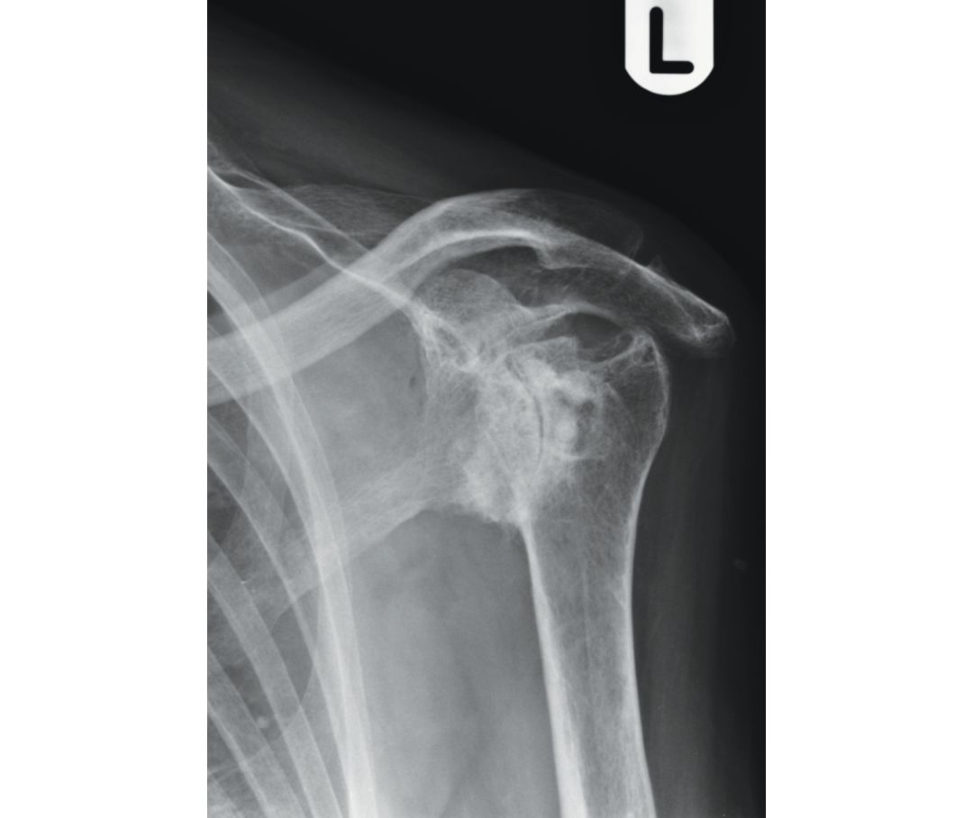
Well ... This is the plain radiograph of an 84-year-old lady’s left shoulder . Anteroposterior (AP) view.
What do you think is wrong with this shoulder?
Well, to be certain, I need to ask a few questions and examine the patient ...
Go on then and ask some questions.
Is she right-handed or left-handed?
Right-handed.
How long has she had a problem with this shoulder?
70 years.
How did the problem start?
It started as a painless lump when she was 14 and a few months later she began to have a discharging sinus that required several joint washouts and medication.
Does she have an active sinus now?
No, the sinus healed after she underwent shoulder washouts and started her medication and has never recurred.
That is good. What are her current problems?
Well she has some restriction of movements and therefore visited her GP, who had performed this X-ray and sent her to you for your opinion.
Then I would examine the patient.
She has 60° of abduction and forward elevation and has very restricted rotations.
I would like to know the power of her cuff muscles.
It is not possible to assess the power as she has very restricted range of movements.
Now ... [Bell]
Thankyou.
Figure 7.1 Anteroposterior (AP) radiograph of left shoulder .
Did this candidate do well? Was there a diagnosis? Was there a discussion about the management?
Only a 4 or 5 score would be given as the candidate did not even arrive at a diagnosis and missed all the clues/prompts.
A different candidate with the same scenario:
This is a radiograph of the left shoulder of an 84- year-old lady. Please describe the X-ray.
This is an anteroposterior (AP) radiographic view of the shoulder that shows evidence of joint destruction and loss of articular cartilage.
What do you think is wrong with this shoulder?
This appearance suggests several possible causes such as previous joint infection
Her shoulder difficulties beg an as a painless lump when she was 14 years old and after a few months she went on to develop a discharging sinus that required several shoulder joint washouts and medication.
W as there any microbiological investigation performed at the time of the joint washouts?
Yes, it was diagnosed as acid-fast bacillus and now what will be your management?
Well, I would like to know if she had any reactivation of infection in the last 70 years?
No.
In that case what is the expectation of the patient?
The patient does not want any surgical treatment. She wants to know if she can have an injection in to her shoulder which can prevent the pain at the extremes of movements.
I will be cautious about the in tra-articular steroid injections as it can trigger the dormant bacillus and rekindle the infection.
OK, the patient comes back to you after 6 months and wants a shoulder joint replacement as her neighbour had one performed for arthritis a few weeks ago and is now pain-free and doing great with her shoulder. The patient wants the same operation. Will you offer her joint arthroplasty?
Again, I would be cautious to do so. I understand the principles of management of this case with the potential risk of recurrence of deep infection. This case will potentially require a biopsy, discussion with a microbiologist as part of an MDT meeting andas taged procedure. If active infection was present a two-stage procedure should be performed. Multiple tuberculosis drug therapy for several months. I would biopsy the shoulder again and if it was negative for infection I would proceed with the second stage. I would warn her of the risk of further reactivation and reoccurrence of infection in the future.
Would you offer her a one-stage procedure if active TB infection was present?
I am aware of a few case reports in which a primary single-stage cementless hemiarthroplasty has been performed for active TB with
The patient does not want to take this risk and wants to be left alone. Thankyou. Although the viva questions started in the same manner, this candidate with his/her knowledge took the viva to a good level of demonstration of his/her clinical judgement by asking specific questions and had control over the situation Certainly, this candidate deserves a good score.
Reference#
Immediate cementless hemiarthroplasty for severe destructive glenohumeral tuberculous arthritis .
Structured oral examination question 2#
Rotator cuff tear
Good afternoon. Can you tell me what is going on in this radiograph of the right shoulder (Figure 7.2)? This patient had anterior dislocation 2 years ago and has ongoing problems.
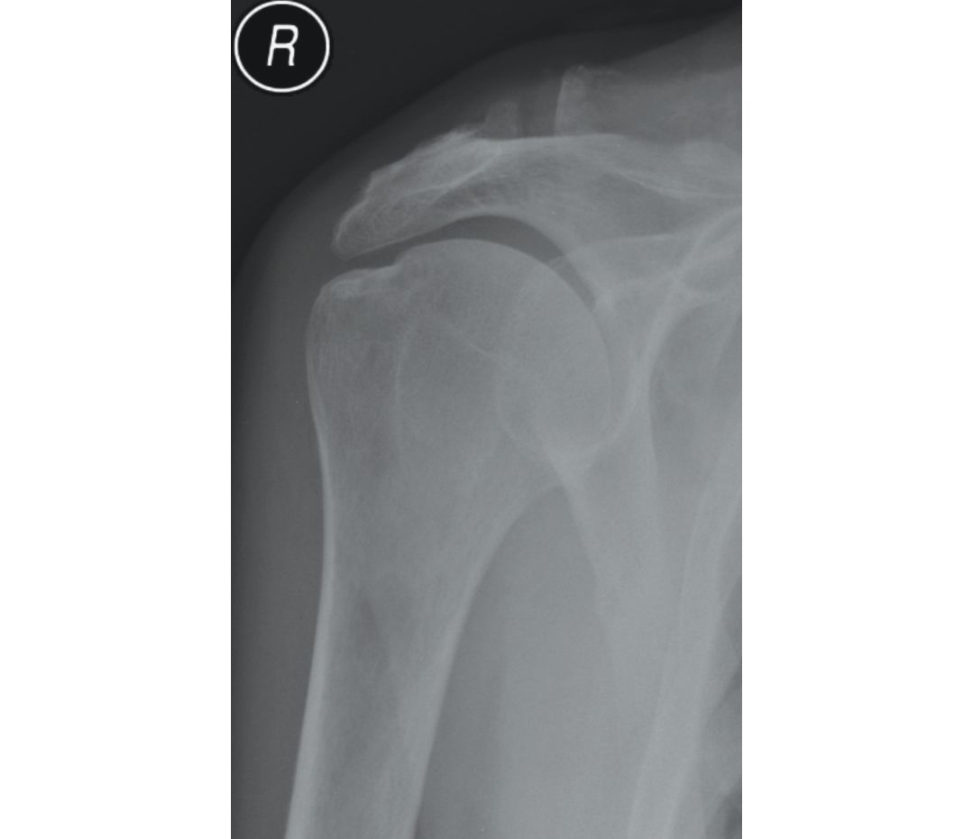
Well, this shoulder is reduced congruently. I cannot see any interposition of bony fragments.
What do you want to rule out?
Well, the risk of re-dislocation of the shoulder is much higher with anterior dislocation due to labral
This gentleman is claustrophobic!
I would talk to the radiologist and anaesthetist to find out if it could be done under sedation.
The anaesthetist is not happy! And your radiologist suggests an ultrasound examination of the shoulder.
Ultrasound examination is not the g old standard examination for labral pathology.
Well, the patient only had an ultrasound examination and it shows subscapularis tear!
There is then a high risk of having damaged the anterior labrum also ... I think I have to speak to the anaesthetist again ...
Figure 7.2 Anteroposterior (AP) radiograph of shoulder.
The candidate fails to start with the fundamental questions of age, how and when it happened and current problems and patient expectations, etc. This makes the entire viva go in the wrong direction and leads to a failing scenario.
Good afternoon. Can you tell me what is going on in this radiograph of the right shoulder? This patient had anterior dislocation 2 years ago and has ongoing problems.
Thanks. May I know the age of the patient and the nature of the ongoing problem, please?
This 76-year-old gentleman dislocated his shoulder 2 years ago. Now has got difficulties in overhead activities and we found out that he is claustrophobic!
I suspect rotator cuff tear in this age group following dislocation and als other e is a risk of infraclavicular
He has got weakness on internal rotation and r est of the cuff power is good. Neurologically he is intact.
I suspect rotator cuff tear from this clinical assessment and I would investigate this shoulder with an ultrasound examination as he is claustrophobic.
The ultrasound examination shows full-thickness cuff tear of 4 mm with retraction.
I would like to know, what has been done so farAnd what are his expectations?
Nothing has been done so far. He wants to play golf, which he has not been able to do in the last 2 years.
Well, I would assess his shoulder clinically to assess for any weakness, stiffness and deltoid muscle compensation before considering any intervention as its going on for 2 years and he is elderly.
Would you call this cuff arthropathy as it is going on for 2 years?
No. The radiograph does not show any evidence of proximal migration of the humeral head.
What will you do? How will you manage this patient?
both techniques have equally good results) with caution as evidence suggests/reports up to 30% re-rupture rates in people above 65 years of age. [Bell] This candidate knew the importance of age-related pathophysiology and succeeded well in the viva.
Structured oral examination question 3
This is a radiograph of the right shoulder of a lady who has got severe pain in her shoulder. Do you find anything interesting ( Figure 7.3a)?
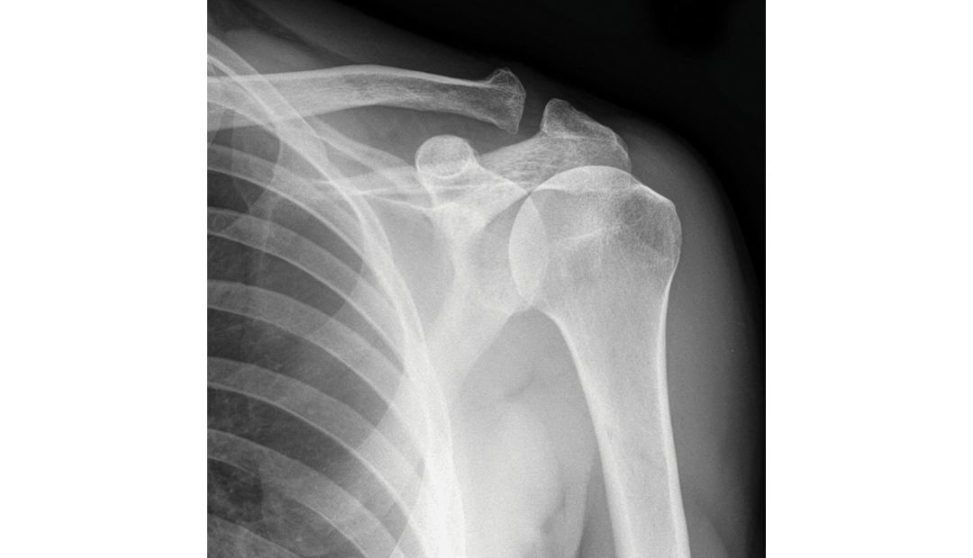
Well ... No not really ... I cannot see any abnormality or disease process in this radiograph.
She is in your clinic referred by her GP. What would you like to do for her?
I want to get the history ... then examine the patient ... to decide on the management plan.
Go ahead.
In the history I will first find out her age, job and dominant side ... and how and when the problem started.
She is 45, right-hand dominant and does clerical work. The pain started 8 months ago when she was reaching out for the seatbelt in her car.
The age and history suggest probable frozen shoulder ... I will proceed with the examination.
She has got global restriction of her movements.
That confirms frozen shoulder. So ...
What do you want to do?
I would offer intra-articular steroid injection for her shoulder and also advise stretching exercises by physiotherapists.
She has already had three intra-articular steroid injections and regular physiotherapy from her GP practice.
Well in that case I would advise her to have manipulation under anaesthesia (MU Aor arthroscopic arthrolysis.
What will you specifically offer the patient?
mmm ... MUA.
The patient wants to know the risks associated with MUA.
Well apart from the anaesthetic risks, there is a risk of fracturing the humerus as it can be osteopenic from disuse ... also the risk of recurrence.
If the bone fractures, what will be the management?
It is like any fracture. Can be treated in a castor operated.
The patient decides now to leave it alone.
I will then convince her to have an injection today and review her situation in 12 weeks.
Figure 7.3a AP radiograph of left shoulder .
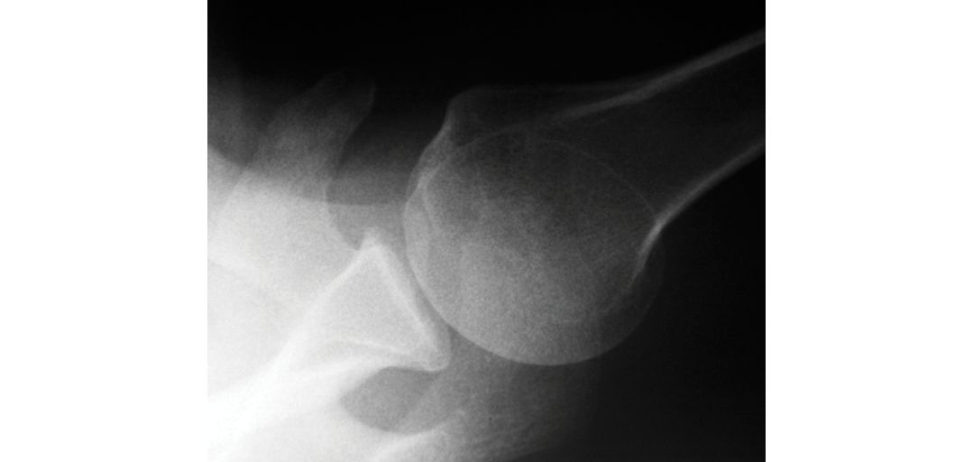
Figure 7.3b Axillary view of left shoulder .
Before we look at the next candidate, think how you would approach this differently!
This is a radiograph of the right shoulder of a lady who has got severe pain in her shoulder. Do you find anything interesting?
May I know the age of this patient and does she suffer from diabetes or thyroid-related problems?
Well, she is 45 and she has hypothyroidism. Is there anything else would you like to examine other than her shoulders?
Yes, I would like to look at her hand to see if she has any evidence of Dupuytren’s contracture as it has some association with frozen shoulder.
She is in your clinic referred by her GP. What would you like to do for her?
I want to know the history and examination findings.
She is right-hand dominant and does clerical work. The pain started 8 months ago when she was reaching out for the seatbelt in her car. She has global restriction of her movements.
Does this pain affect her sleep? What is the range of her external and internal rotation?
Yes, she struggles to sleep at night and her ER is only to neutral position and she cannot get her hand to her back to do up her clothes. What would you like to do for her?
I want to know what has been done for her so farand what is her expectation.
She had three intra-articular injections and physiotherapy from her GP practice. Shew ants to be able to wash and dress herself independently.
benefits and risks of both procedures and the importance of immediate post intervention physiotherapy and make her understand the disease process of frozen shoulder so that the patient could have a realistic expectation of the treatment process.
The patient understands your explanation very well and wants to have the keyhole surgery. What will you do in arthroscopic capsular release?
The anterior capsule release especially at the rotator interval, followed by middle gleno- humeral ligament release and the release of the coraco-humeral ligament.
What does the evidence say, which is better – MUA/capsular release?
The literature is divided between both treatment modalities. MU A is simple and capsular release is a bit more invasive. There is also hydro-dilatation which some centres perform.
Thankyou. When the examiner sensed his ability a small extra challenge was given – do you want to examine anywhere else? And the candidate was able to demonstrate his/her knowledge – association with
Dupuytren’s contracture – the candidate would have been given an extra point for these
Structured oral examination question 4
This is a radiograph of a 63-year-old gentleman’s right shoulder (Figure 7.4a). Proceed.
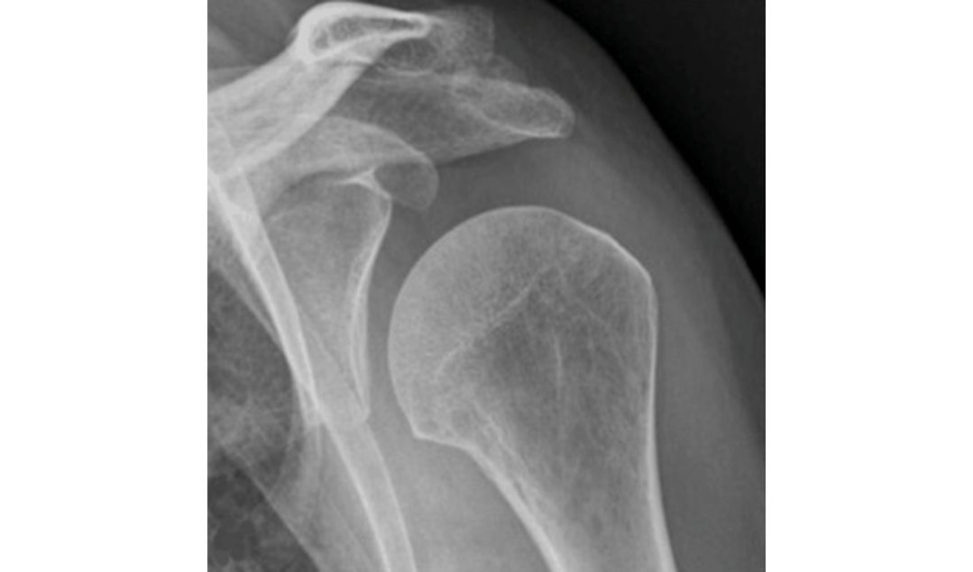
This plain AP radiograph shows normal glenohumeral joint and acromioclavicular joint, well- maintained subacromial space but the under surface of
Yes (Figure 7.4b).
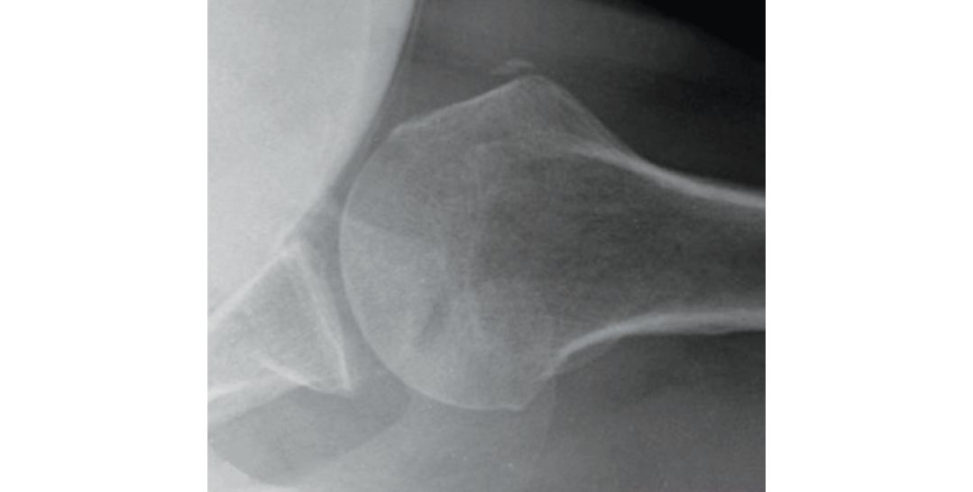
The calcification may be missed with one view of the shoulder, particularly with subscapularis involvement, soAP radiographs in internal and external rotation aswell as scapularY and/or axillary views of the shoulder are recommended.
What is your opinion about his pain in the shoulder?
Well, he could be struggling with calcific tendonitis.
What do you want to do?
I would like to know the patient symptoms, examination findings, the treatments he has had so farand his expectations.
He is a keen golfer and gradually over the last 2 years he has developed the pain on overhead activities. He has not had an y interventions sofar. He wants to continue playing golf without pain. He has got positive impingement signs.
Well, which is causing impingement symptoms, and review him in 8 weeks in clinic with repeat X-rays to assess the calcium deposits.
Incidentally there is also another X-ray of his right shoulder which was performed 2 years ago when he started to have the pain, which shows the same calcium deposits. Does it change your plan?
... Well, I would then book him now for arthroscopic excision of the calcium deposits.
Will you perform any other procedures during the surgery?
I will consent him for arthroscopy and proceed ... so that I can assess the shoulder and perform the necessary at the time of the surgery.
Figure 7.4a Anteroposterior (AP) view of right shoulder.
Figure 7.4b Axillary view of right shoulder.
Did he pickup the clues from the examiner and correct himself? What will be your scoring for this candidate?
Will you diagnose and manage this problem differently like the next candidate?
This is a radiograph of a 63-year-old gentleman’s right shoulder. Proceed.
This plain AP radiograph shows normal glenohumeral joint and acromioclavicular joint, well- maintained subacromial space but the under surface of
Yes.
There are deposits of calcium in the supraspinatus tendon ...
What is your opinion about his pain in the shoulder?
(EXAMINER: 2 years) and his age I feel he has got degenerative calcification in his cuff and subacromial impingement.
What do you want to do?
I would like to know the patient symptoms, examination findings, the treatments he has had so farand his expectations.
He is a keen golfer and gradually over the last 2 years he has developed the pain on overhead activities. He has not had an y interventions sofar. He wants to continue playing golf without pain. He has got positive impingement signs.
I want to know if he has had any X-rays in the past and would like to assess the status of his cuff with an ultrasound scan/MRI scan.
This is the X-ray taken 2 years ago – showing the same calcification. There cent ultrasound scan shows intact cuff.
Well, I would inject the subacromial bursa today with steroid and review the patient in 8 weeks
Suppose his old X-rays do not show any deposits and if it’s recent then will you do the same?
In which case, this could be recent onset and I would consider sending the patient for ultrasound-guided injection and
OK, He comes back in 8 weeks saying the pain was well controlled for 3 weeks and now the pain is back. What will you do?
This proves the pathology of subacromial impingement and I am going to talk to the patient about subacromial decompression.
Will you perform excision of the calcium deposits?
No, not necessarily. This degenerative calcification is a chronic one. It is not acute calcific tendonitis. I will perform subacromial decompression and assess his cuff for obvious calcific
Thankyou.
This second candidate was much clearer about the pathology and management plan, which will be rewarded by a better score. The previous candidate failed to understand these prompting clues.
Structured oral examination question 5#
Good afternoon. Can you tell me the findings from this radiograph of the left shoulder of a 76-year-old left-handed fit gentleman (Figure 7.5a)?
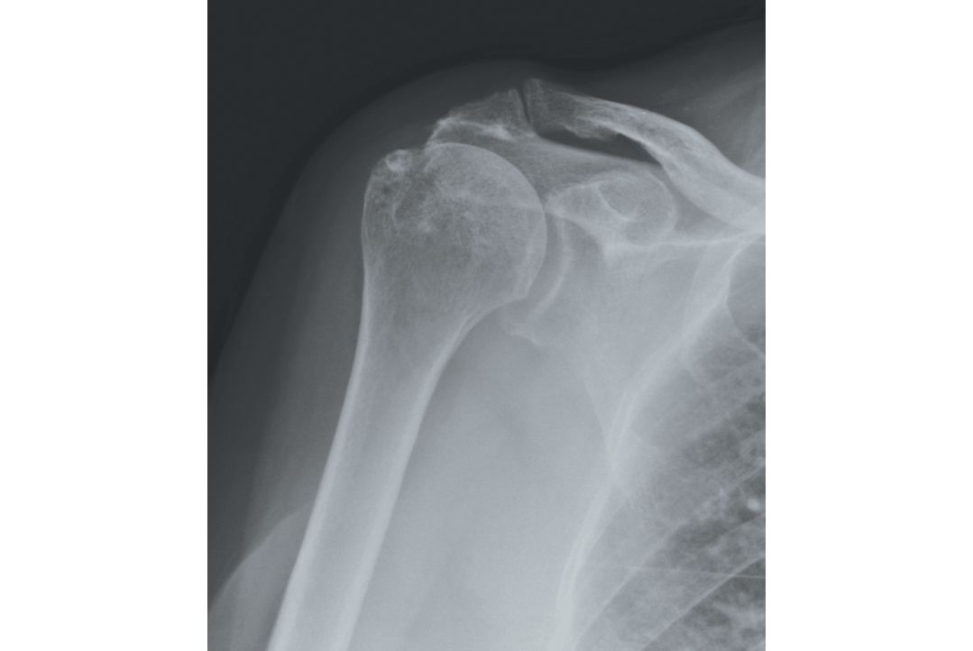
This anteroposterior view of the left shoulder shows no evidence of glenohumeral joint or acromioclavicular joint arthritis.
Would you like any other investigations ... prior to commiting yourself with a diagnosis?
I would like to have ultrasound of his shoulder ... and may I know his symptoms, please?
The ultrasound which was requested by his GP shows torn subscapularis and supraspinatus with massive retraction of the tendons. He has difficulties with overhead activities. Can you tell me what is wrong with this shoulder?
from the ultrasound scan ... which shows evidence of torn subscapularis and supraspinatus tendons and clinically he has got difficulties in overhead activities ...
Yes, it is a nice summary of the situation wasting time]
I think he has severe subacromial impingement and secondary cuff tear.
What would you do for this gentleman?
Well, first I would perform a steroid injection in to his subacromial space.
Can you tell me the landmarks and how you will perform the injection?
Yes, 2 cm inferior and medial to the posterolateral corner of the acromion, I will direct the
Is it necessary to be specific in this patient ... he has got a massive cuff tear?
??
Well he comes back to clinic in 8 weeks with no difference to his symptoms. Do you have any management plans?
I will then perform an arthroscopic debridement of the cuff and bursa and a subacromial decompression.
Thankyou.
Figure 7.5a Anteroposterior (AP) radiograph of left shoulder .
Do you recognize the candidate’s mistakes? What would you do differently? Did he treat the patient or the investigations?
Good afternoon. Can you tell me the findings from this radiograph of the left shoulder of a 76-year-old left-handed fit gentleman?
This anteroposterior view of left shoulder shows proximal migration of humeral head with narrowing of the
Would you like any other investigations ... prior to commiting yourself with a diagnosis?
I would like to have an axillary view of his shoulder.
Yes, we have axillary view. What are you looking for?
I am looking for anteroposterior subluxation of the humeral head in the axillary view ... yes, there is anterior subluxation suggesting torn anteriorly placed subscapularis and from the AP view,
What would you do for him?
I need to know the patient symptoms, what has been done for the patient so farand what are his expectations?
He has got difficulties in overhead activities. He has had three injections by his GP, which have made no difference, and being ana rtis the would like to have reasonable ability to abduct his shoulder to reach for the top of the canvas during painting.
Could you please tell me if he has any pain associated with his shoulder abduction?
No ... not at all.
I would start with non-operativ e management in terms of a deltoid muscle rehabilitation programme to compensate for the cuff deficiency. As he is not in pain and there is no established arthritis, this would be my initial management. I will also get a CT scan of the shoulder joint to assess the glenoid bone stock and version as preoperative planning.
He is very fit. Why do you prefer reverse shoulder to a total shoulder replacement?
The reverse shoulder (Figure 7.5b), although non-anatomical, brings the centre of rotation of the glenohumeral joint
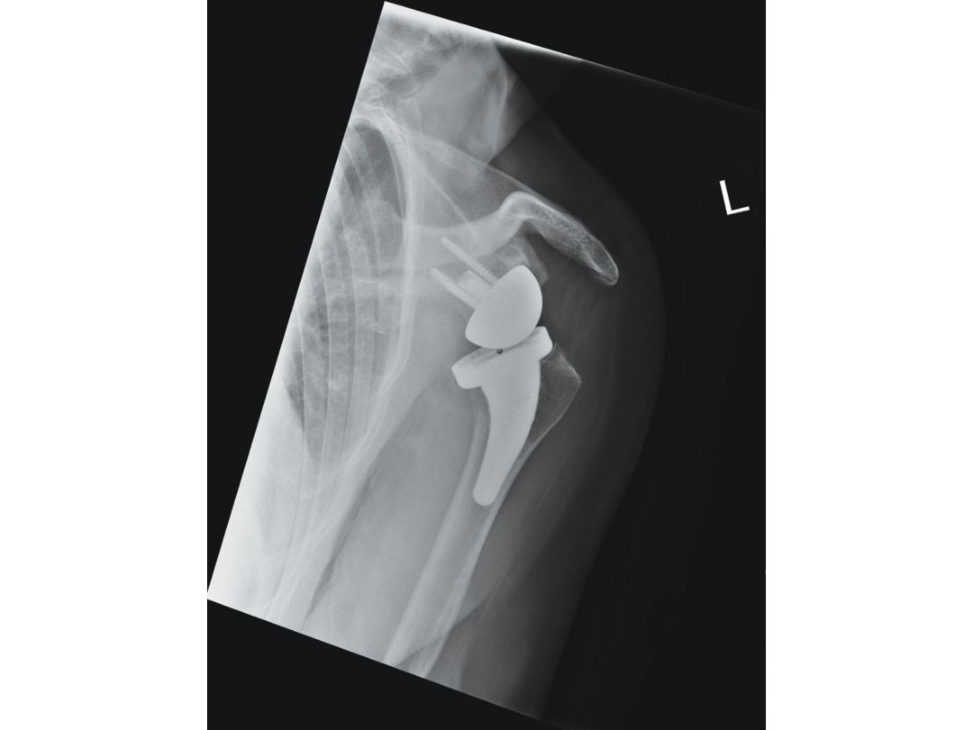
Would you not try to repair the cuff prior to this major surgery?
No. The radiographs show established cuff arthropathy and in this situation it is not possible to reverse the
Can you name some complications of the reverse polarity replacement?
Short term: infection dislocation, haematoma formation (duet o dead space), nerve injury (axillary, musculocutaneous) and periprosthetic fracture.
Well, we will move on to the next scenario. Whom do you think played the game well in this scenario? Analyze the candidate’s ability to show their knowledge to the examiner. Learn how not to waste time and not to lower the expectations of the examiner. When the examiner’s expectations godown, the questions may become simpler and the score drops. Show the knowledge appropriately to please the examiner. Make the game interesting for the examiners and you will walkaway with a good score. Treat each scenario as a separate exam to reach a good overall score. Remember: the examiners do not know your previous performance, either good or bad. Therefore, forget the previous performance and move on.
Figure 7.5b Reverse shoulder replacement.